How can i help you?
Latest Blogs
Explore All




When a thermometer shows 37.5°C or 38°C, the natural question is whether this is a normal temperature for a child or a fever. The number alone, however, does not tell the full story.
A child's age, the site where the temperature was measured, the type of thermometer, the measurement technique, activity level and even a recent bath can affect the reading.
For that reason, a temperature of 37.5°C measured under the arm should not automatically be interpreted in the same way as 37.5°C measured in the ear or mouth. There is also no reliable formula for adding or subtracting a fixed number of degrees to convert a reading from one measurement site to another. [1] [4]
There is no single temperature that is normal for every child at every moment. The American Academy of Pediatrics notes that normal body temperature varies with a child's age, activity level and time of day. The NHS describes the average normal temperature in babies and children as approximately 36.4°C, while noting that normal variation occurs. [1] [3]
For parents, the measurement site is particularly important because different parts of the body can produce slightly different readings.
The Canadian Paediatric Society provides the following reference ranges according to measurement site: [5]
| Measurement site | Approximate reference range | What to know |
|---|---|---|
| Armpit | 36.5–37.5°C | Easy and commonly used but less precise than some other methods. |
| Mouth | 35.5–37.5°C | Suitable for older children who can hold the thermometer correctly. |
| Ear | 35.8–37.9°C | Accuracy depends heavily on correct positioning in the ear canal. |
| Rectum | 36.6–37.9°C | Highly accurate but invasive and not routinely recommended by every guideline. |
These are reference ranges rather than rigid conversion or diagnostic rules. A temperature should always be interpreted alongside the measurement site, the child's age and the child's overall condition.
Different thermometers estimate body temperature from different parts of the body. The American Academy of Pediatrics considers rectal temperature the most accurate, followed by forehead measurements. Oral and ear measurements can also be accurate when performed correctly, while armpit temperatures are generally less accurate and are often used for screening. [1]
NICE takes a less invasive approach for routine temperature measurement in children younger than 5. It recommends an electronic thermometer in the armpit for infants younger than 4 weeks and either an axillary thermometer or infrared ear thermometer for children aged 4 weeks to 5 years. [2]
These recommendations are not necessarily contradictory. They reflect the balance between measurement accuracy, practicality and safe routine use.
Armpit, or axillary, measurement is widely used in babies and young children because it is simple and non-invasive. The Canadian Paediatric Society lists an approximate normal axillary range of 36.5–37.5°C. [5]
Technique matters. The thermometer tip should sit against the skin in the centre of the armpit, with the child's arm held firmly against the body until the thermometer completes the measurement. The NHS recommends digital armpit measurement for children younger than 5 years. [3]
| Age | Practical option | Important consideration |
|---|---|---|
| Newborns and young infants | Digital armpit measurement is a practical routine option supported by NICE and the NHS. | A temperature of 38°C or higher in a baby younger than 3 months needs urgent assessment. |
| From around 6 months | Armpit or a properly used ear thermometer. | The AAP does not recommend ear thermometers in younger infants because their ear canals are narrow. |
| Older children | Ear, oral or forehead measurement may be appropriate depending on the device and the child's ability to cooperate. | The AAP generally considers oral measurement suitable from about age 4 if the child can use the thermometer correctly. |
Although rectal measurements are considered highly accurate by some organisations, they are more invasive. NICE does not recommend routine oral or rectal temperature measurement in children aged 0 to 5 years. If a rectal measurement is considered necessary, parents should use an appropriate technique and follow medical advice. [1] [2]

No fixed amount should automatically be added to an armpit temperature.
A common rule of thumb is to add 0.5°C or even 1°C to an underarm reading to estimate the child's “real” temperature. This can create false precision.
Mayo Clinic explains that readings can differ depending on where temperature is measured, but there is no exact way to add or subtract a fixed degree value to make readings from different parts of the body match. When following a child's temperature over time, it is more useful to compare measurements taken in the same way. [4]
Therefore, if a child's temperature is 37.7°C under the arm, do not automatically convert it to 38.2°C or 38.7°C. Record it as 37.7°C axillary and interpret it with the child's age, symptoms and overall condition.
Small changes do not always mean the illness itself has suddenly changed. Temperature readings can be affected by:
The NHS recommends allowing a child to cool down for a few minutes before repeating the temperature if they have just had a bath, been very active, been heavily wrapped or stayed in a very warm room. [3]
If fever is confirmed, read our detailed guide to child fever treatment by age, temperature and symptoms.
| Reading | How to interpret it |
|---|---|
| 35.5°C | This may fall near the lower end of some measurement ranges, particularly oral readings, but would be relatively low for others. Repeat an unexpected reading, especially if the child feels cold or appears unwell. |
| 36°C | This can be normal depending on the child, measurement site and time of day. |
| 37.5°C | The site matters. This may sit near the upper end of normal reference ranges for some methods and should not be interpreted without knowing how it was measured. |
| 38°C | This is commonly used as a fever threshold. In a baby younger than 3 months, it requires urgent medical assessment. |
| 39°C | This is not a normal temperature. NICE considers 39°C or higher in children aged 3 to 6 months at least an intermediate-risk feature for serious illness. In children older than 6 months, the number alone does not determine illness severity. |
NICE specifically advises that in children older than 6 months, the height of the temperature alone should not be used to identify serious illness. The child's appearance and accompanying symptoms remain crucial. [2]
Normal temperature can vary somewhat with age, activity and time of day. In everyday home monitoring, however, parents do not need to memorise a different “normal number” for every age.
Age is more important because it affects which measurement method is appropriate and how urgently fever should be assessed.
For example, 38°C carries a very different level of concern in a 2-month-old baby than it does in an otherwise well 5-year-old child. [2]
Seek prompt medical assessment if:
If a seizure occurs with fever, see our guide to febrile seizure first aid and what to do in the first few minutes.
The goal of fever care is not to force the thermometer back to 37°C at all costs. The child's comfort, hydration, overall condition and the cause of the fever matter more than chasing a particular number.
A temperature falling after fever medicine does not prove that the underlying illness is minor, and a temperature that does not fall quickly does not by itself diagnose a serious illness.
For safe home care and common cooling mistakes to avoid, see: how to reduce a child's fever safely.
A child's normal temperature cannot be interpreted separately from the way it was measured. Armpit, ear, mouth, forehead and rectal measurements can produce different readings, while age, technique, activity and environmental conditions can also influence the result.
Do not automatically add 0.5°C or 1°C to an armpit temperature. Record the measurement site, make sure the thermometer is being used correctly and repeat an unexpected reading before interpreting it alongside your child's age and overall condition.
For specialist assessment of fever or other concerning symptoms, visit Pediatrics at Mouwasat Hospital.
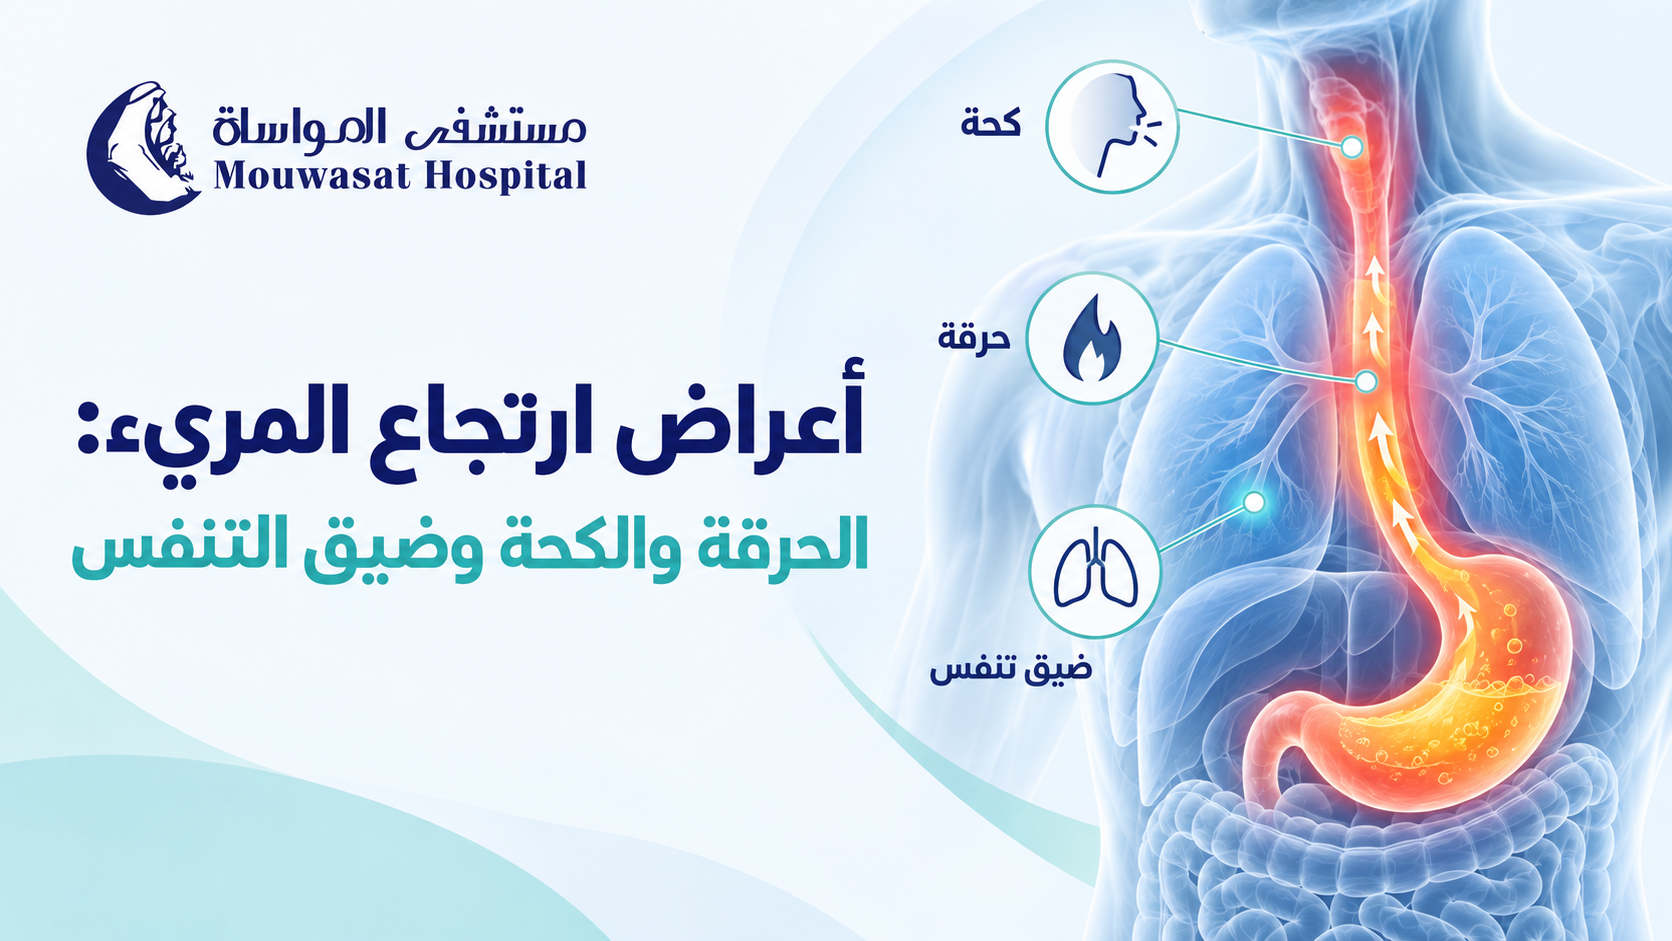
GERD symptoms vary from person to person. Heartburn behind the breastbone and regurgitation of stomach contents into the throat or mouth are among the most common symptoms, but some people may also experience cough, hoarseness, nausea, chest pain, or difficulty swallowing.
Not every symptom that occurs in someone with reflux is necessarily caused by GERD. Understanding which symptoms are typical, which may have several possible causes, and which require medical assessment can help avoid incorrect self-diagnosis.
The most common symptoms of gastroesophageal reflux disease are heartburn and regurgitation. Heartburn is typically felt as a burning sensation behind the breastbone, while regurgitation occurs when stomach contents travel back into the esophagus, throat, or mouth. [1]
Other symptoms may include:
Symptoms may become more noticeable:
The Saudi Ministry of Health notes that reflux symptoms may worsen after overeating and while bending or lying down. [2]
Occasional heartburn after a large meal does not automatically mean that a person has GERD. GERD becomes more likely when reflux causes recurrent troublesome symptoms or complications.
GERD-related heartburn is often described as a burning sensation in the middle of the chest behind the breastbone and may rise toward the throat. [1]
It may occur after eating or worsen when lying down or bending over, and it can occur together with a sour taste or regurgitation.
However, chest pain has many possible causes. A person should not assume that new or significant chest pain is simply acid reflux.
Some people experience throat or voice symptoms alongside more typical reflux symptoms. These can include:
These symptoms alone do not prove that reflux is the cause. GERD guidelines recommend evaluating other possible causes of extraesophageal symptoms before attributing them to reflux. [3]
Allergies, sinus and nasal disorders, respiratory disease, and laryngeal conditions can produce similar symptoms.
GERD can be associated with chronic cough in some people. Medical sources also recognize hoarseness and other throat or lung-related symptoms among possible extraesophageal manifestations. [1]
However, cough has many possible causes, so cough alone is not enough to diagnose GERD.
Phlegm is not one of the classic symptoms of GERD. Some patients may notice increased throat secretions or frequent throat clearing, but allergies, respiratory infections, or postnasal drainage should also be considered.
GERD may coexist with respiratory or laryngeal symptoms in some patients, and reflux has been associated with chronic cough, asthma, and voice symptoms. [4]
However, shortness of breath should not automatically be attributed to GERD. It has many potential causes involving the heart, lungs, airways, infections, and other conditions.
Some patients may also describe nighttime throat irritation or a choking sensation, but recurrent or significant breathing difficulty requires medical assessment rather than assuming reflux is responsible.
Dizziness and headache are not typical GERD symptoms.
They may occur in someone who also has GERD, but their presence does not establish reflux as the cause. Recurrent or severe dizziness or headaches should therefore be evaluated separately rather than automatically being linked to acid reflux.
A symptom occurring in someone with GERD is not necessarily caused by GERD. This is especially important for dizziness, headaches, breathing symptoms, and throat complaints.
Anxiety and stress are not diagnostic symptoms of GERD, but they may worsen reflux symptoms or make them more noticeable in some individuals.
The Saudi Ministry of Health lists anxiety and stress among factors that may trigger reflux symptoms. [2]
This distinction matters: stress may be a trigger or symptom amplifier, but it is not evidence by itself that a person has GERD.
| Symptom | Relationship to GERD | What matters? |
|---|---|---|
| Heartburn behind the breastbone | Typical symptom | Often worsens after eating or when lying down. |
| Regurgitation or sour taste | Typical symptom | Stomach contents travel back toward the throat or mouth. |
| Cough or hoarseness | May be associated | These symptoms have many other possible causes. |
| Shortness of breath | May coexist in some patients | Other heart or lung causes should not be overlooked. |
| Dizziness or headache | Not typical GERD symptoms | Persistent symptoms should be assessed for other causes. |
| Difficulty or pain with swallowing | Can occur with GERD | Persistent swallowing difficulty warrants medical evaluation. |
| Chest pain | Can occur with GERD | New or severe chest pain should not automatically be attributed to reflux. |
Yes. Not everyone with GERD experiences classic heartburn. NIDDK notes that some adults with GERD may instead experience chest pain, nausea, swallowing problems, chronic cough, or hoarseness. [1]
When only atypical symptoms are present, however, determining whether reflux is truly responsible can be more difficult because the same symptoms can arise from several other conditions.
Occasional mild reflux may improve with lifestyle measures. Recurrent, troublesome, or persistent symptoms deserve medical assessment and an appropriate treatment plan.
For a detailed look at management options, read: GERD Treatment: Available Options and When to See a Doctor.
For a broader overview of the condition, see: GERD: Symptoms, Causes, Diagnosis and Treatment.
Medical evaluation is recommended when reflux symptoms are frequent or persistent, swallowing becomes difficult, nausea or vomiting continues, unexplained weight loss develops, or symptoms do not improve despite treatment. [2]
NIDDK also recommends medical assessment for symptoms such as:
Mouwasat Hospital's Gastroenterology & Endoscopy Department provides evaluation, diagnosis and treatment for digestive disorders including reflux-related symptoms.
Yes. Nausea can occur in some people with GERD, although it is not the most typical symptom. [1]
GERD can be associated with chronic cough, but cough has many other possible causes and cannot diagnose GERD by itself.
Phlegm is not a classic GERD symptom. Throat secretions and frequent throat clearing may occur, but allergies, respiratory infections, and postnasal drainage should also be considered.
Respiratory symptoms may coexist with reflux in some patients, but shortness of breath has many possible causes and should not automatically be attributed to GERD.
Dizziness is not a typical symptom of GERD. Frequent or significant dizziness should be assessed for other possible causes.
Nighttime reflux may cause throat irritation or unpleasant sensations in some people, but recurrent choking or breathing difficulty during sleep can have other causes and should be medically evaluated.
GERD can cause chest pain or burning, but new or severe chest pain should not automatically be assumed to be acid reflux.
A fever is one of the most common reasons parents become concerned about a child, but child fever treatment should not be based on the thermometer reading alone.
The child's age, breathing, alertness, ability to drink and associated symptoms can be more important than trying to bring the temperature down as quickly as possible.
Temperature readings can vary depending on the child's age and how the temperature is measured, so a number should always be interpreted in context.
A temperature of 38°C (100.4°F) or higher is particularly important in young infants. NICE classifies babies younger than 3 months with a temperature of 38°C or higher as being at high risk of serious illness. [1]
For babies aged 3 to 6 months, a temperature of 39°C or higher is considered at least an intermediate-risk feature. [1]
For more detail about measuring temperature, see: Normal Child Temperature: Why the Measurement Site Changes the Reading.
| Age or situation | What it means practically |
|---|---|
| Under 3 months and 38°C or higher | Urgent medical assessment is needed. [1] |
| 3–6 months and 39°C or higher | Requires prompt clinical attention, particularly when other symptoms are present. [1] |
| Older than 6 months | The height of the temperature alone should not be used to identify serious illness. [1] |
| Any child who appears seriously unwell | Needs medical assessment regardless of the temperature reading. |
A temperature of 39°C in a young infant is not the same situation as 39°C in an older child who is drinking, interacting and breathing comfortably. Age and overall condition change how the number should be interpreted.
Parents may naturally focus on repeatedly checking the temperature, but the child's condition provides essential information.
Pay attention to:
NICE specifically advises that in children older than 6 months, the height of body temperature alone should not be used to identify serious illness. [1]
No.
NICE advises clinicians not to rely on whether a temperature falls after an antipyretic to distinguish serious from non-serious illness. [1]
A response to fever medicine tells you something about temperature and comfort. It is not a diagnostic test showing that the underlying illness is harmless.
If the child's age and symptoms make home monitoring appropriate and there are no warning signs, care focuses on comfort, fluids and observation.
Offer fluids regularly. For a breastfed baby, breast milk remains the most appropriate fluid. [1]
Do not over-wrap a child with fever, but do not deliberately underdress them either. Keep clothing comfortable and appropriate for the environment. [1]
Watch fluid intake, urine output, breathing, alertness and activity, and check on a feverish child during the night. [1]
For more detailed practical guidance, see: How to Reduce a Child's Fever Safely Without Common Home-Care Mistakes.
No. Fever medicine is not simply a treatment for a number on the thermometer.
NICE recommends considering either paracetamol (acetaminophen) or ibuprofen for children with fever who appear distressed, rather than using an antipyretic solely to lower body temperature. [1]
However, medication suitability depends on age, weight, medical conditions, hydration and the concentration of the specific product.
Paracetamol is used to reduce discomfort associated with fever in children, but the correct amount depends on factors including the child's weight and product concentration. The American Academy of Pediatrics highlights medication dosing errors as an important safety concern and recommends confirming appropriate dosing, particularly in young children. [2]
Ibuprofen can also be used in appropriate children, but it has age, weight and medical-condition restrictions and is not automatically suitable for every child. Discuss its use with the child's doctor or pharmacist when unsure. [3]
NICE advises against giving both at the same time. Switching or alternating medicines should not be done routinely without appropriate guidance from a healthcare professional. [1]
Do not give aspirin to a child on your own. It should only be used when specifically prescribed for an appropriate medical condition.
There is no need to chase the thermometer reading with harsh cooling measures or unproven home remedies.
NICE does not recommend tepid sponging as a routine fever treatment, and the American Academy of Pediatrics advises against methods such as alcohol baths, ice packs and aggressive cooling. [1] [4]
| Method | Safer approach |
|---|---|
| Ice or very cold water | Avoid; it can cause discomfort and shivering and does not treat the cause of fever. |
| Alcohol on the skin | Do not use. |
| Vinegar, lemon, onion or oils to lower fever | Do not rely on these to treat fever or delay medical assessment. |
| Over-wrapping the child | Use comfortable clothing appropriate for the room temperature. |
No.
NICE states that antipyretic medicines do not prevent febrile convulsions and should not be used specifically for that purpose. [1]
The Saudi Ministry of Health explains that febrile seizures typically occur between 6 months and 5 years of age and that having a febrile seizure does not mean a child has epilepsy. [5]
A first seizure or any seizure associated with fever requires appropriate medical assessment.
For first-aid guidance, see: Febrile Seizures in Children: What to Do in the First Few Minutes.
Fever is a symptom rather than a disease. Infection is the most common cause, often viral, although bacterial infections and other conditions can also cause fever.
Associated symptoms may help the clinician identify the source, including:
Fever with cough does not automatically mean bacterial infection or a need for antibiotics. If cough is the main symptom, see: Child Cough Treatment by Cough Type, Age and Associated Symptoms.
Teething may be associated with a very slight rise in temperature, but the Saudi Ministry of Health advises medical consultation if a child's temperature reaches 38°C or higher rather than assuming the fever is caused by teething. [6]
Attributing a significant fever in a baby to teething can delay assessment of an infection or another illness. A clear fever, particularly in a young infant, should not simply be dismissed as teething.
| Situation | Next step |
|---|---|
| Older child is responsive, drinking, breathing comfortably and has no warning signs | Home monitoring, fluids and comfort measures may be appropriate, with medical advice if concerns develop. |
| Baby under 3 months with a temperature of 38°C or higher | Urgent medical assessment is required. |
| Baby aged 3–6 months with 39°C or higher, or who appears unwell | Prompt medical assessment is appropriate. |
| Fever lasts 5 days or longer, or the child is becoming more unwell | Medical evaluation is needed to identify the cause. [1] |
| Severe breathing difficulty, abnormal color, marked lethargy, difficulty waking, seizure or a non-blanching rash | Seek emergency medical care immediately. |
Seek medical advice or assessment when a child with fever:
The American Academy of Pediatrics also emphasizes how the child looks and behaves and the presence of associated symptoms when deciding when a pediatrician should be contacted. [4]
Mouwasat Hospital's Pediatric Department provides comprehensive care for infants, children and adolescents, including general and specialized pediatric services.
Safe child fever treatment starts with the child's age and an accurate temperature measurement, followed by careful attention to breathing, hydration, alertness and associated symptoms.
Fever medicine may be appropriate to improve comfort in selected children, but it does not treat the underlying cause and should not be used solely to force the temperature back to normal.
In a young infant or any child with warning signs, medical assessment matters more than trying another method to lower the temperature at home.
It depends on age and associated symptoms. In children older than 6 months, temperature alone does not determine severity. In a baby aged 3–6 months, 39°C or higher is an important risk feature requiring medical assessment. [1]
No. Fever medicine is generally used to improve comfort rather than simply reduce the number. However, a baby younger than 3 months with a temperature of 38°C or higher needs urgent medical assessment. [1]
There is no single best choice for every child. Paracetamol or ibuprofen may be appropriate in certain children, but medicine selection and dosing depend on age, weight, medical history and product concentration. Confirm the appropriate choice and dose with a doctor or pharmacist.
Do not routinely give both together or alternate them without medical guidance. [1]
No. Antipyretic medicines do not prevent febrile seizures. [1]
No. The response to fever medicine cannot reliably distinguish serious from non-serious illness. [1]
Teething may cause only a slight rise in temperature. The Saudi Ministry of Health advises medical consultation if the temperature reaches 38°C or higher. [6]
GERD symptoms vary from person to person. Heartburn behind the breastbone and regurgitation of stomach contents into the throat or mouth are among the most common symptoms, but some people may also experience cough, hoarseness, nausea, chest pain, or difficulty swallowing.
Not every symptom that occurs in someone with reflux is necessarily caused by GERD. Understanding which symptoms are typical, which may have several possible causes, and which require medical assessment can help avoid incorrect self-diagnosis.
The most common symptoms of gastroesophageal reflux disease are heartburn and regurgitation. Heartburn is typically felt as a burning sensation behind the breastbone, while regurgitation occurs when stomach contents travel back into the esophagus, throat, or mouth. [1]
Other symptoms may include:
Symptoms may become more noticeable:
The Saudi Ministry of Health notes that reflux symptoms may worsen after overeating and while bending or lying down. [2]
Occasional heartburn after a large meal does not automatically mean that a person has GERD. GERD becomes more likely when reflux causes recurrent troublesome symptoms or complications.
GERD-related heartburn is often described as a burning sensation in the middle of the chest behind the breastbone and may rise toward the throat. [1]
It may occur after eating or worsen when lying down or bending over, and it can occur together with a sour taste or regurgitation.
However, chest pain has many possible causes. A person should not assume that new or significant chest pain is simply acid reflux.
Some people experience throat or voice symptoms alongside more typical reflux symptoms. These can include:
These symptoms alone do not prove that reflux is the cause. GERD guidelines recommend evaluating other possible causes of extraesophageal symptoms before attributing them to reflux. [3]
Allergies, sinus and nasal disorders, respiratory disease, and laryngeal conditions can produce similar symptoms.
GERD can be associated with chronic cough in some people. Medical sources also recognize hoarseness and other throat or lung-related symptoms among possible extraesophageal manifestations. [1]
However, cough has many possible causes, so cough alone is not enough to diagnose GERD.
Phlegm is not one of the classic symptoms of GERD. Some patients may notice increased throat secretions or frequent throat clearing, but allergies, respiratory infections, or postnasal drainage should also be considered.
GERD may coexist with respiratory or laryngeal symptoms in some patients, and reflux has been associated with chronic cough, asthma, and voice symptoms. [4]
However, shortness of breath should not automatically be attributed to GERD. It has many potential causes involving the heart, lungs, airways, infections, and other conditions.
Some patients may also describe nighttime throat irritation or a choking sensation, but recurrent or significant breathing difficulty requires medical assessment rather than assuming reflux is responsible.
Dizziness and headache are not typical GERD symptoms.
They may occur in someone who also has GERD, but their presence does not establish reflux as the cause. Recurrent or severe dizziness or headaches should therefore be evaluated separately rather than automatically being linked to acid reflux.
A symptom occurring in someone with GERD is not necessarily caused by GERD. This is especially important for dizziness, headaches, breathing symptoms, and throat complaints.
Anxiety and stress are not diagnostic symptoms of GERD, but they may worsen reflux symptoms or make them more noticeable in some individuals.
The Saudi Ministry of Health lists anxiety and stress among factors that may trigger reflux symptoms. [2]
This distinction matters: stress may be a trigger or symptom amplifier, but it is not evidence by itself that a person has GERD.
| Symptom | Relationship to GERD | What matters? |
|---|---|---|
| Heartburn behind the breastbone | Typical symptom | Often worsens after eating or when lying down. |
| Regurgitation or sour taste | Typical symptom | Stomach contents travel back toward the throat or mouth. |
| Cough or hoarseness | May be associated | These symptoms have many other possible causes. |
| Shortness of breath | May coexist in some patients | Other heart or lung causes should not be overlooked. |
| Dizziness or headache | Not typical GERD symptoms | Persistent symptoms should be assessed for other causes. |
| Difficulty or pain with swallowing | Can occur with GERD | Persistent swallowing difficulty warrants medical evaluation. |
| Chest pain | Can occur with GERD | New or severe chest pain should not automatically be attributed to reflux. |
Yes. Not everyone with GERD experiences classic heartburn. NIDDK notes that some adults with GERD may instead experience chest pain, nausea, swallowing problems, chronic cough, or hoarseness. [1]
When only atypical symptoms are present, however, determining whether reflux is truly responsible can be more difficult because the same symptoms can arise from several other conditions.
Occasional mild reflux may improve with lifestyle measures. Recurrent, troublesome, or persistent symptoms deserve medical assessment and an appropriate treatment plan.
For a detailed look at management options, read: GERD Treatment: Available Options and When to See a Doctor.
For a broader overview of the condition, see: GERD: Symptoms, Causes, Diagnosis and Treatment.
Medical evaluation is recommended when reflux symptoms are frequent or persistent, swallowing becomes difficult, nausea or vomiting continues, unexplained weight loss develops, or symptoms do not improve despite treatment. [2]
NIDDK also recommends medical assessment for symptoms such as:
Mouwasat Hospital's Gastroenterology & Endoscopy Department provides evaluation, diagnosis and treatment for digestive disorders including reflux-related symptoms.
Yes. Nausea can occur in some people with GERD, although it is not the most typical symptom. [1]
GERD can be associated with chronic cough, but cough has many other possible causes and cannot diagnose GERD by itself.
Phlegm is not a classic GERD symptom. Throat secretions and frequent throat clearing may occur, but allergies, respiratory infections, and postnasal drainage should also be considered.
Respiratory symptoms may coexist with reflux in some patients, but shortness of breath has many possible causes and should not automatically be attributed to GERD.
Dizziness is not a typical symptom of GERD. Frequent or significant dizziness should be assessed for other possible causes.
Nighttime reflux may cause throat irritation or unpleasant sensations in some people, but recurrent choking or breathing difficulty during sleep can have other causes and should be medically evaluated.
GERD can cause chest pain or burning, but new or severe chest pain should not automatically be assumed to be acid reflux.
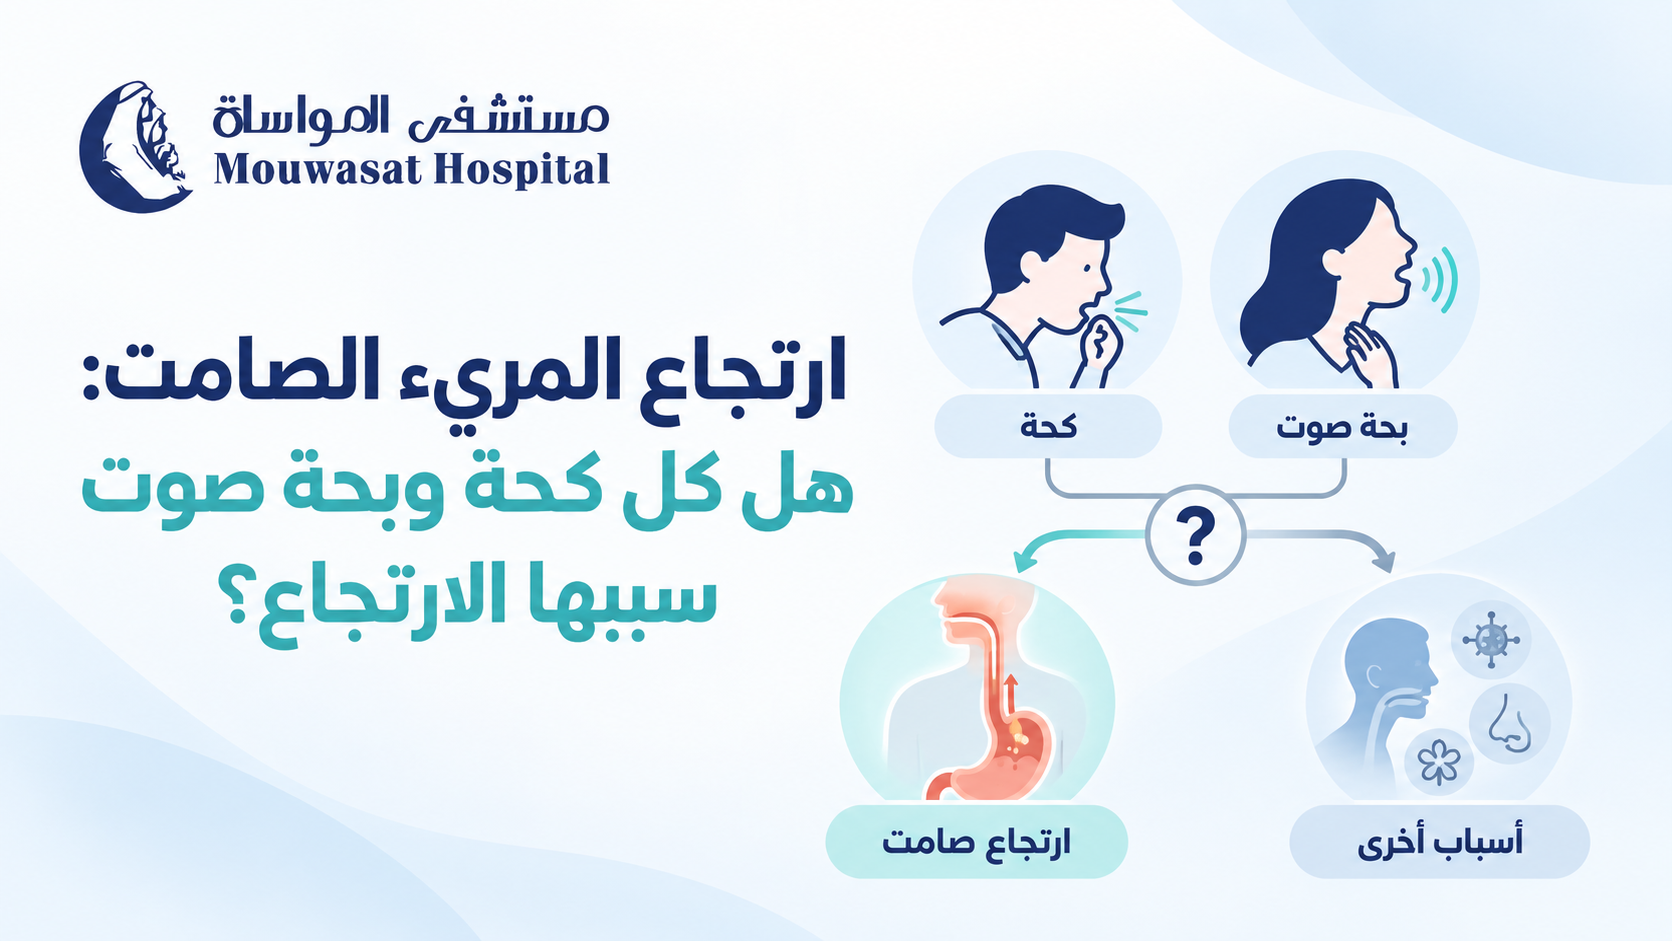
Silent reflux is commonly used to describe throat or voice symptoms such as chronic cough, hoarseness, frequent throat clearing, excess throat mucus, or a sensation of something being stuck in the throat, sometimes without classic heartburn.
However, one important point changes how these symptoms should be approached: having throat symptoms does not automatically mean that reflux is causing them. Cough, voice changes and throat discomfort can have many different causes, so modern recommendations distinguish between laryngopharyngeal symptoms and proven laryngopharyngeal reflux disease.
The term laryngopharyngeal reflux (LPR) has traditionally been used when reflux is suspected of contributing to symptoms involving the throat or larynx.
It is often called “silent” reflux because some people with throat or voice symptoms do not report the classic heartburn or acid regurgitation associated with GERD.
More recent guidance uses more precise terminology. The San Diego Consensus distinguishes between:
In other words, symptoms alone are not the diagnosis. [1]
For a broader overview of gastroesophageal reflux disease, read our guide to GERD symptoms, causes, diagnosis and treatment.
Symptoms that may be reported include:
The San Diego Consensus includes cough, voice changes, throat clearing, excess phlegm and throat pain among laryngopharyngeal symptoms that may be reflux-related, while emphasizing that these symptoms do not establish LPRD on their own. [1]
| Symptom | Can it occur with LPR? | Does it prove reflux? |
|---|---|---|
| Chronic cough | It may | No. Cough has many causes. |
| Hoarseness | It may | No. Other causes should be considered. |
| Frequent throat clearing | It may | No. |
| Lump-in-the-throat sensation | It may coexist | No. Several other conditions can cause it. |
| Phlegm or excess throat mucus | Some patients report it | No. Allergies and postnasal drainage are among other possibilities. |
| Heartburn or regurgitation | May be present or absent | Their presence adds context but does not by itself prove the cause of throat symptoms. |
Chronic cough, hoarseness, throat mucus and frequent throat clearing are not specific to reflux.
They can also occur with:
The American Gastroenterological Association emphasizes that extraesophageal symptoms are often multifactorial and may require evaluation across more than one specialty. [2]
Instead of asking, “Can reflux cause this cough?”
ask, “What evidence makes reflux a more likely explanation than the other possible causes of this cough?”
No single feature confirms LPRD. Doctors interpret the entire clinical picture.
| Situation | What it may suggest |
|---|---|
| Throat symptoms plus heartburn or regurgitation | Reflux is more plausible as a contributor than when throat symptoms occur alone. |
| Isolated cough or hoarseness without typical reflux symptoms | Other causes become especially important to evaluate. |
| Symptoms continue despite treatment | The diagnosis may need reassessment rather than automatic treatment escalation. |
| Invasive antireflux treatment is being considered | Objective confirmation of reflux becomes particularly important. |
The San Diego Consensus notes that patients with laryngopharyngeal symptoms plus typical esophageal reflux symptoms have a higher pretest probability of reflux-related disease than those with isolated throat symptoms. [1]
Not by itself.
Laryngoscopy can be valuable for examining the larynx and identifying other conditions that could explain symptoms. However, findings such as irritation or redness are not specific enough to establish reflux as the cause.
The San Diego Consensus specifically states that laryngoscopic findings alone cannot diagnose laryngopharyngeal reflux disease. [1]
Modern evaluation does not rely on one symptom or one test. Depending on the situation, it may include:
The doctor considers whether typical GERD symptoms such as heartburn or regurgitation occur alongside the throat symptoms, whether the symptoms are isolated, and whether another cause is more likely.
Laryngeal examination can help identify alternative explanations for voice, throat, or cough symptoms, even though it cannot establish reflux as the cause on its own.
Some patients may require upper GI endoscopy, particularly when warning symptoms, persistent complaints, or a broader evaluation of the esophagus is needed.
Tests such as 24-hour pH-impedance monitoring or longer wireless pH monitoring may be used in selected patients to objectively evaluate reflux exposure. [1]
Not necessarily.
A limited trial of acid-suppressing treatment may be reasonable in selected patients, particularly when typical GERD symptoms occur together with throat symptoms.
However, AGA guidance notes that improvement during a proton pump inhibitor trial does not by itself confirm that reflux caused the extraesophageal symptoms. [2]
This matters when a person enters a repeated cycle of:
medicine → partial improvement → symptoms return → stronger medicine → symptoms persist.
At some point, reassessing the diagnosis may be more useful than simply increasing treatment.
There is no single treatment plan for everyone because management should depend on how likely reflux is to be contributing to the symptoms.
Depending on the individual, recommendations may include:
These strategies are also recommended as part of GERD management more broadly. [4]
A doctor may recommend acid-suppressing therapy in selected patients, particularly when throat symptoms coexist with typical reflux symptoms.
Treatment choice should follow the diagnostic context rather than the presence of throat symptoms alone. [1]
For a detailed explanation of medical and lifestyle treatment, read: GERD Treatment: Available Options and When to See a Doctor.
There is no established herbal remedy that can be considered a proven permanent treatment for laryngopharyngeal reflux disease.
A person may feel better after a particular drink or natural product, but that improvement does not prove that reflux caused the symptoms or that the same approach will help someone else.
Online experiences often describe one person improving dramatically with reflux treatment while another person with apparently similar symptoms does not improve at all.
One major reason is that the same symptom can have different causes in different people.
For example, chronic cough may be related to reflux in one patient, while another patient's cough may be related to asthma, allergy, postnasal drainage, or a laryngeal disorder.
| Personal experience | What it cannot prove |
|---|---|
| “My cough improved on acid medication.” | It does not prove that all chronic cough is reflux-related. |
| “Herbal treatment soothed my throat.” | It does not establish treatment of reflux disease itself. |
| “My laryngoscopy showed irritation.” | Irritation alone does not prove reflux caused it. |
A combined gastroenterology and ENT approach may be particularly useful when throat or voice symptoms dominate, when symptoms persist despite treatment, or when typical GERD symptoms are absent.
AGA guidance supports multidisciplinary assessment because extraesophageal symptoms are frequently multifactorial. [2]
For a broader discussion of typical and atypical symptoms, see: GERD Symptoms: From Heartburn to Cough and Difficulty Swallowing.
Silent reflux should not automatically be described as dangerous, but persistent or unexplained throat symptoms should not simply be ignored either.
Sometimes the more important issue is not the severity of reflux itself, but whether symptoms such as hoarseness, swallowing difficulty, or chronic cough are being attributed to reflux without identifying their true cause.
Medical assessment is important for symptoms such as:
Mouwasat Hospital's Gastroenterology & Endoscopy Department provides evaluation and treatment for reflux and other digestive disorders.
Yes. Throat or voice symptoms may occur without classic heartburn. However, the absence of heartburn also makes it particularly important to consider other possible causes of isolated throat symptoms.
Some patients report excess throat mucus or frequent throat clearing, but phlegm is not specific to reflux and may also occur with allergies, postnasal drainage, or respiratory conditions.
Reflux may be one possible contributor to hoarseness, but hoarseness has many potential causes and cannot establish an LPR diagnosis by itself.
Nighttime throat symptoms may coexist with reflux, but recurrent choking or breathing difficulty during sleep can have other causes and should be evaluated when persistent or severe.
Laryngoscopy can identify laryngeal abnormalities and alternative causes of symptoms, but laryngoscopic findings alone cannot diagnose LPRD. [1]
No. Lack of improvement may mean that the diagnosis needs reassessment or that reflux is not the only—or primary—cause of the symptoms.
There is no proven herbal remedy that can be considered a definitive treatment for LPRD. Persistent symptoms deserve appropriate evaluation rather than relying indefinitely on unproven remedies.
When a child starts coughing, parents often want to know the fastest or best child cough treatment. But cough treatment should not begin with choosing a cough syrup. A cough is a symptom and a protective reflex, and its causes range from a simple viral cold to asthma, allergies, respiratory infections and, less commonly, an inhaled foreign object.
The safest approach therefore depends on the child's age, breathing, how long the cough has lasted, how it started, and the symptoms occurring with it.
Coughing is a natural protective reflex that helps clear mucus, irritants and other material from the throat and airways. [1]
This means that completely suppressing a cough is not always the goal. In some situations, coughing is helping the body clear respiratory secretions.
| Factor | Why it matters |
|---|---|
| Age | Infants, particularly very young babies, require greater caution with respiratory symptoms and fever. |
| Breathing | Fast, labored breathing or chest indrawing may be more important than the sound or frequency of the cough. |
| How it started | A sudden cough while eating or playing with small objects raises concern for an inhaled foreign body. |
| Duration | A cough lasting weeks needs a different assessment from a cough that began two days ago with a cold. |
| Overall condition | A child who is playing, drinking and breathing normally is different from one who is lethargic or unable to drink. |
A cough can sound dramatic without being dangerous. Breathing effort, alertness, hydration and associated symptoms often tell you more than the loudness of the cough.
The character of a cough can provide useful clues, but it does not diagnose the cause on its own.
A dry cough produces little or no obvious mucus and may occur with viral infections, throat irritation, allergies, asthma and other conditions.
A productive cough helps move respiratory secretions. The presence of mucus does not automatically mean that antibiotics are required.
Wheezing may occur when the lower airways narrow and can be seen with asthma and some respiratory infections. Recurrent wheezing or breathing difficulty deserves medical assessment.
A barking cough with hoarseness or a harsh sound when breathing in may occur with croup.
A sudden coughing episode while eating or playing with small objects raises concern for a foreign object entering the airway.
Read more in: Dry Cough or Phlegmy Cough in Children: The Difference That Changes the Approach.
Honey should not be given to infants younger than 12 months because of the risk of infant botulism. Extra caution is also needed before giving cough or cold medication to babies and young children. [3]
A small amount of honey may help soothe coughing in children over 1 year of age and may reduce nighttime coughing. [3]
Many cough and cold products contain more than one active ingredient. This can increase the risk of accidentally giving the same medicine twice through different products. [4]
When a child is breathing comfortably, drinking adequately and has no warning signs, supportive home care may be enough for many viral colds.
Adequate fluids help prevent dehydration and can keep respiratory secretions less thick.
Honey may soothe coughing in children over 1 year old, but should never be given to an infant younger than 12 months. [3]
Saline drops or spray and gentle removal of nasal secretions can be useful, particularly in younger children. [4]
A clean cool-mist humidifier may help when indoor air is dry. It should be cleaned regularly to prevent contamination. [4]
Children should be protected from cigarette and shisha smoke and other strong respiratory irritants.
For a more detailed guide, see: Child Cough Home Treatment: What Helps and What to Avoid.
There is no single cough syrup that is the best treatment for every child.
The Saudi Ministry of Health notes that cough medicine is not always necessary and does not recommend cough and cold medicines for children under 6 in the context of common viral respiratory illness. [1] [2]
The FDA also warns against cough and cold products containing decongestants or antihistamines in children younger than 2 because serious adverse effects can occur, while manufacturers commonly label these products not to be used in children younger than 4. [4]
What is causing the cough, how old is the child, and are there signs that the underlying condition needs treatment rather than simply suppressing the cough?
Most coughs associated with common colds do not.
Colds and many acute respiratory illnesses are caused by viruses, which antibiotics cannot treat. Antibiotics are used when a bacterial infection is diagnosed or strongly suspected by a clinician.
The color of mucus or the strength of the cough alone is not enough to decide that antibiotics are needed.
Not necessarily. Mucus color alone cannot reliably determine whether an infection is bacterial or viral. The child's age, fever, breathing, overall condition and medical examination matter more.
A cough can remain after other cold symptoms begin to improve. The American Academy of Pediatrics notes that coughing associated with a cold may commonly last around 2 to 3 weeks. [5]
A cough that persists for much longer, becomes progressively worse, or is associated with recurrent wheeze, breathing difficulty or other concerning symptoms should be evaluated.
Nighttime cough can become more noticeable because of nasal secretions draining toward the throat while lying down, but asthma, allergies, reflux and other conditions may also contribute.
A cough being worse at night does not automatically mean that the illness is more severe, but a repeated nighttime pattern can provide useful diagnostic information.
Read: Child Cough at Night May Be More Than Just a Cold.
| Situation | Possible next step |
|---|---|
| Active child, drinking normally, comfortable breathing and cough started with a cold | Supportive home care and monitoring may be appropriate. |
| Persistent or worsening cough, recurring wheeze, persistent fever or significant sleep/activity disruption | Pediatric assessment is appropriate to identify the cause. |
| Fast or labored breathing, chest indrawing or difficulty feeding/drinking | Urgent medical evaluation is needed. |
| Blue lips, severe breathing difficulty, pauses in breathing, marked lethargy or difficulty waking | Seek emergency medical care immediately. |
The World Health Organization identifies fast breathing and lower chest indrawing as important signs when evaluating a child with cough or difficult breathing, while inability to drink and marked lethargy are among important danger signs. [6]
Medical assessment is appropriate when the cough is getting worse instead of improving, lasts much longer than expected, is associated with repeated wheezing, persistent fever, reduced activity or feeding, or began suddenly after a choking episode.
Mouwasat Hospital's Pediatric Department provides care for common and specialized childhood conditions, including respiratory illnesses and Pediatric Pulmonology services.
There is no single immediate treatment for every cough. With a simple cold, fluids, saline nasal care, cool-mist humidification and honey after age 1 may help. Other causes such as asthma or pneumonia require treatment of the underlying condition.
It may help children aged 1 year and older. Honey must not be given to babies younger than 12 months because of the risk of infant botulism. [3]
Not necessarily. The presence of mucus alone does not determine severity. Breathing, alertness and associated symptoms are more important.
No. Asthma is one possible cause, but colds, nasal drainage, allergies and other conditions can also cause nighttime coughing.
Not necessarily. Mucus color alone is not enough to diagnose a bacterial infection or decide that antibiotics are required.
The cough becomes particularly concerning when accompanied by significant breathing difficulty, blue lips, chest indrawing, marked lethargy, inability to drink, or sudden onset following choking.
When a child develops a cough, parents often try to classify it first: is it a dry cough or a wet, phlegmy cough? That distinction can be useful, but it does not tell you the diagnosis or treatment by itself.
Two children can have similar-sounding coughs for completely different reasons. What matters is not only whether mucus is present, but also how long the cough has lasted, how it started, the child's age, breathing pattern and associated symptoms.
For the broader overview, see our guide to child cough treatment by cough type, age and associated symptoms.
Coughing is a protective reflex that helps clear mucus and irritants from the airways. A dry cough produces no obvious mucus, while a wet cough sounds as though respiratory secretions are being moved. [1]
| Feature | Dry cough | Wet cough |
|---|---|---|
| Sound | Dry, irritating or tickly without obvious secretions. | Sounds as though mucus or secretions are present. |
| Possible associations | Viral or post-viral cough, airway irritation, allergy, asthma and other causes. | Respiratory infections and, when persistent, several airway or lung conditions. |
| Does the type determine treatment? | No. The cause and clinical context come first. | No. Mucus alone does not mean antibiotics are required. |
| What else matters? | Duration, breathing, age, onset, timing and associated symptoms. | |
A wet cough that started four days ago with a cold is very different from a daily wet cough lasting more than four weeks. Duration can change the meaning of the symptom.
Pediatric cough guidelines recommend interpreting whether a cough is wet or dry alongside its duration, onset, timing and associated clinical history. [2]
A dry cough therefore does not automatically mean allergy or asthma, just as a wet cough does not automatically mean bacterial infection.
Dry cough can occur with viral illness or remain after an infection, while asthma, allergens and airway irritants are other possibilities. A wet cough can simply be part of an acute viral respiratory infection in which coughing helps clear secretions.
Most short-lasting coughs in otherwise well children are associated with viral respiratory infections and resolve without specific treatment. A dry cough can sometimes remain after other cold symptoms have improved. [2]
Cough can occur with asthma, particularly when there is wheezing, breathlessness or symptoms associated with exercise or recurring at characteristic times. However, cough alone does not diagnose asthma.
Smoke, dust, strong fumes, passive smoking and allergens may irritate a child's airways and trigger coughing.
A cough that begins suddenly while a child is eating or playing with a small object should not be assumed to be a routine dry cough. An inhaled foreign body needs to be considered.
A wet cough is not automatically more serious than a dry cough. During respiratory infections, coughing helps move secretions from the airways, so completely suppressing the cough is not always the goal. [4]
Young children also commonly swallow mucus rather than spit it out, so parents may hear a wet cough without seeing any sputum.
This can occur during viral respiratory infections and usually improves as the illness resolves.
This is where the pattern changes. Pediatric guidelines define a daily cough lasting more than 4 weeks as chronic cough and recommend further assessment. [2] [3]
Several conditions can cause chronic wet cough in children. One is protracted bacterial bronchitis (PBB), but other causes must also be considered by a clinician. The condition should not be diagnosed from mucus or cough sound alone.
A wet cough for four days and a daily wet cough for four weeks are not the same clinical situation. Sometimes duration matters more than how dramatic the cough sounds.
CHEST pediatric guidelines define chronic cough as a daily cough lasting more than 4 weeks. [3]
| Pattern | What it may mean practically |
|---|---|
| Short cough with cold symptoms in a well child | Often viral and gradually resolves. |
| Dry cough continuing after a cold | May be post-viral, but persistent or changing symptoms should be assessed. |
| Daily wet cough for more than 4 weeks | Requires medical assessment to establish the cause. |
| Recurring cough at night or with exercise plus wheeze or breathlessness | May warrant assessment for an airway condition such as asthma. |
If coughing becomes particularly noticeable during sleep, see: Child Cough at Night May Be More Than Just a Cold.
Not necessarily.
Mucus can become yellow or green during viral respiratory infections. Color alone does not establish that an infection is bacterial or that antibiotics are required. The American Academy of Pediatrics specifically notes that yellow or green mucus does not automatically mean a child needs antibiotics. [5]
Antibiotic decisions should therefore be based on the diagnosed condition, examination and overall clinical picture rather than mucus color alone.
It can be, but the underlying cause determines the treatment more than the label “dry” or “wet.”
For a simple viral cold, supportive care may be enough. If the cough is related to asthma, allergy, a specific infection or another condition, treatment is directed toward that cause.
Over-the-counter cough and cold medicines are not automatically appropriate for children. The American Academy of Pediatrics does not recommend them for children younger than 4 years, and from ages 4 to 6 they should only be used when recommended by the child's doctor. [4]
That question assumes the sound of the cough is the diagnosis. A safer starting point is the child's age, breathing, duration of symptoms and associated signs.
For age-appropriate supportive care, see: Child Cough Home Treatment: What Helps and What to Avoid.
Regardless of cough type, seek medical assessment when a child develops concerning features such as:
Distinguishing between dry and wet cough is useful, but it is only one part of pediatric cough assessment. A dry cough is not automatically asthma or allergy, and a wet cough is not automatically a bacterial infection.
The factors that change the next step are the likely cause, duration, breathing pattern, timing, onset and associated symptoms. One particularly important distinction is between a short wet cough during a cold and a daily wet cough persisting beyond 4 weeks.
Mouwasat Hospital's Pediatric Department provides care for common and specialized childhood conditions, including respiratory illnesses and pediatric pulmonology services.
Neither is automatically more serious. Severity depends more on breathing, the child's overall condition, duration and associated symptoms than on whether mucus is present.
A wet cough may sound deeper or as though mucus is moving in the airway. Young children often swallow mucus instead of coughing it out, so visible sputum is not required.
Yes. The character of a cough can change during a respiratory illness as airway secretions and inflammation change.
A daily wet cough persisting for more than 4 weeks warrants medical assessment, particularly if it is associated with breathing difficulty, recurrent pneumonia, blood, poor growth or other concerning symptoms.
No. Asthma can cause cough, but viral infections, allergies, irritants and other conditions can also cause a dry cough. Other symptoms and clinical assessment are needed.
No. Green or yellow mucus can occur during viral infections and does not by itself prove that antibiotics are needed. [5]
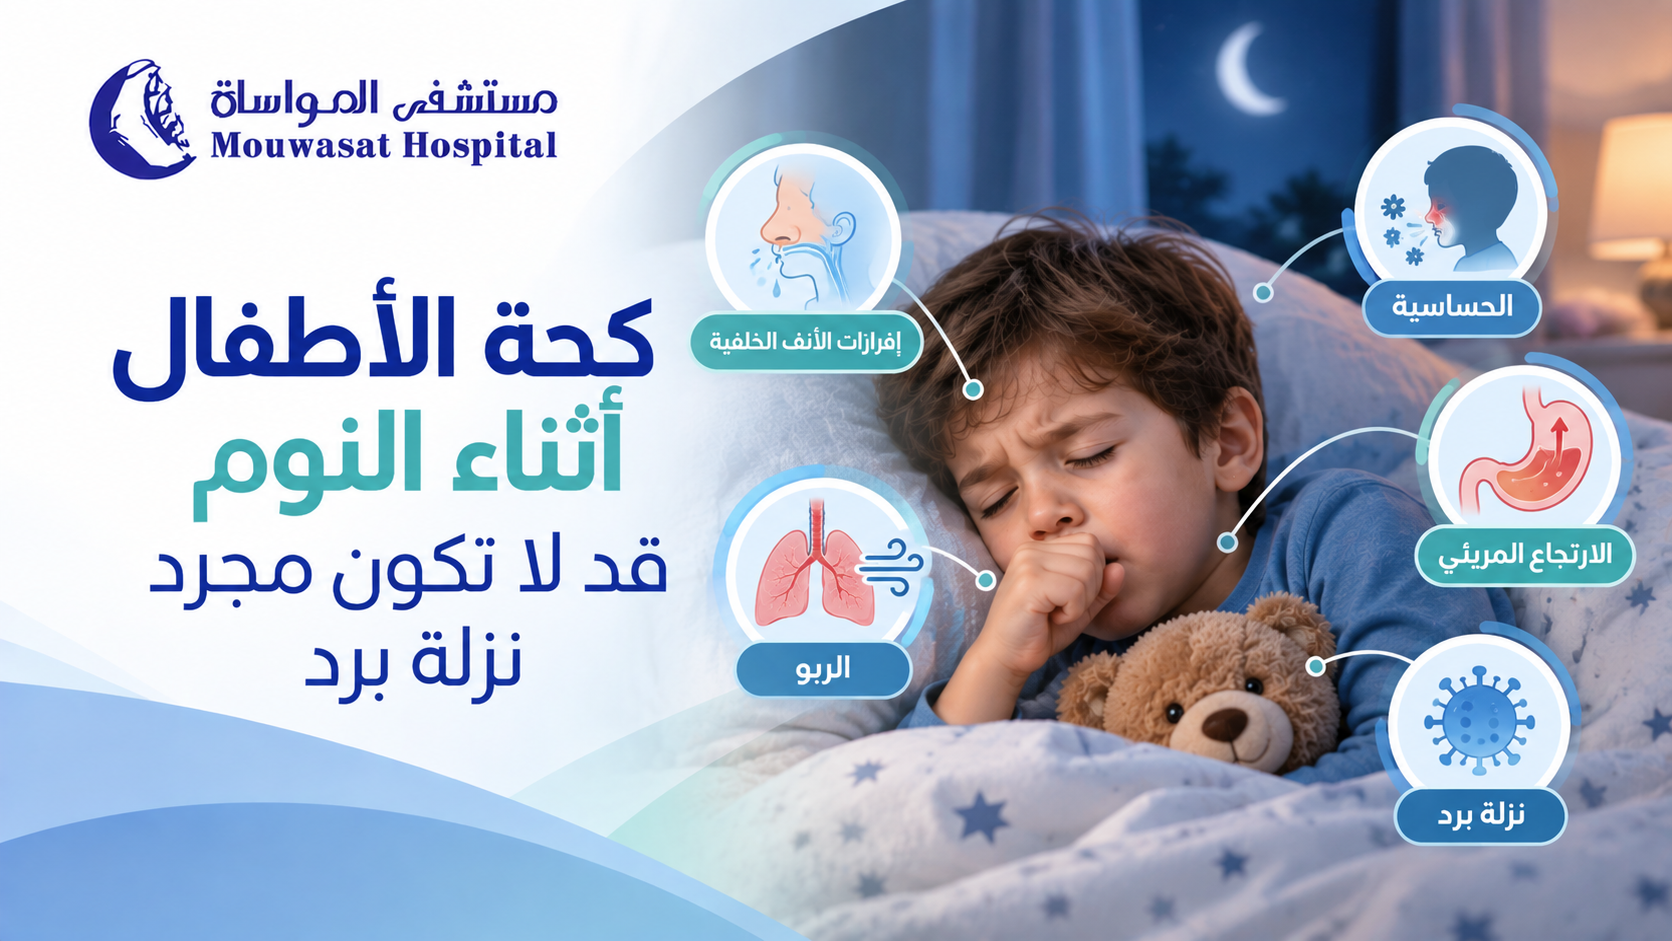
A child may seem relatively well during the day, only for coughing to begin or become noticeably worse after bedtime. A child cough at night is common and does not automatically mean something serious, but the nighttime pattern can provide useful clues.
Colds and nasal congestion can make coughing more noticeable when a child lies down, while asthma, croup and other conditions may also produce nighttime symptoms.
The important question is not simply whether the child coughs at night, but what the cough sounds like, how long it has lasted, how the child is breathing and what other symptoms occur with it.
For the broader picture, see: Child Cough Treatment by Cough Type, Age and Associated Symptoms.
Nighttime itself does not cause coughing, but several factors can make a cough more noticeable after bedtime.
When a child lies down, nasal secretions and airway irritation may become more noticeable. Some conditions, including asthma and croup, can also produce symptoms that become more prominent at night. [1] [2]
The key point is that a nighttime pattern is a clue rather than a diagnosis.
Did it begin two days ago with a cold, or does it return every night for weeks? Does the child cough with exercise? Is there wheezing? How is the child's breathing? Those details change the next step.
| Pattern | What may need to be considered? |
|---|---|
| Cough started with a runny or blocked nose a few days ago | Viral illness and irritation from nasal secretions are common possibilities. |
| Recurrent nighttime cough with wheezing, breathlessness or exercise symptoms | Assessment for asthma or another airway condition may be appropriate. |
| Barking cough with hoarseness or a harsh sound when breathing in | Croup may be a possibility and commonly becomes worse at night. |
| Daily cough lasting more than 4 weeks | This meets the pediatric definition of chronic cough and should be assessed. |
| Cough began suddenly while eating or playing with a small object | An inhaled foreign body needs to be considered. |
For more on cough characteristics, see: Dry vs Wet Cough in Children — The Difference Goes Beyond Mucus.
Often, yes. Viral respiratory infections commonly cause both nasal congestion and coughing, and secretions can irritate the throat.
If the cough began with a typical cold, the child remains reasonably active, drinks normally and breathes comfortably, the symptoms will often improve gradually as the infection resolves. [3]
However, a cough that continues to recur night after night should not automatically be attributed to nasal drainage without considering the rest of the child's symptoms.
Nighttime cough can occur with asthma, particularly when it is accompanied by:
The American Academy of Pediatrics notes that symptoms that are worse at night may be a warning sign of asthma and that cough can sometimes be one of its early symptoms. [4]
However, nighttime cough alone does not diagnose asthma. Diagnosis depends on the overall symptom pattern, history and clinical assessment.
Recurring nighttime cough or repeated waking because of respiratory symptoms can be a reason to discuss asthma control with the child's clinician rather than simply trying to suppress the cough.
A barking cough with a hoarse voice or a harsh, high-pitched sound while breathing in may occur with croup.
Croup commonly begins with cold-like symptoms, and the NHS notes that its symptoms are often worse at night. [5]
Reflux can be one of several possibilities in selected children, particularly when other compatible symptoms are present. However, nighttime cough by itself does not diagnose reflux.
Pediatric cough guidelines recommend assessing cough according to its characteristics and clinical history and treating the identified cause rather than relying on nonspecific treatment trials. [6]
If digestive symptoms are also present, see: GERD: Symptoms, Causes, Diagnosis and Treatment.
Parents may naturally want to elevate a baby's head when the baby is coughing or congested, but safe infant sleep rules still apply.
The American Academy of Pediatrics recommends that infants sleep on their backs on a firm, flat, non-inclined surface, including infants with reflux. Pillows, wedges and an elevated mattress should not be used to treat cough or congestion during sleep. [7] [8]
If your child is breathing comfortably and has no warning signs, supportive measures may help depending on the child's age and symptoms:
For a full home-care guide, see: Child Cough Home Treatment: What Helps and What to Avoid.
That pattern does not point to one single diagnosis. Nasal symptoms may become more noticeable when lying down, while asthma, allergy and other conditions may also produce nighttime symptoms.
If the pattern happens repeatedly, regularly wakes the child, or is associated with exercise, wheezing or breathing difficulty, it is worth evaluating why the cough keeps returning rather than focusing only on stopping it.
Is the pattern recurring? Two nights of coughing during a cold are different from a cough that wakes a child most nights or repeatedly appears with exercise.
CHEST pediatric guidelines define chronic cough as a daily cough lasting longer than 4 weeks. [10]
Duration therefore matters alongside the nighttime pattern.
| Situation | Possible next step |
|---|---|
| Cough with a cold, normal breathing, good fluid intake and normal activity | Supportive home care and monitoring are often reasonable. |
| Cough occurs most nights, is linked to exercise or wheezing, or repeatedly disrupts sleep | Arrange pediatric assessment to identify the cause. |
| Daily cough lasting more than 4 weeks | Evaluation for chronic cough is appropriate. |
| Severe breathing difficulty, blue lips, marked lethargy or stridor with respiratory distress | Seek emergency medical care immediately. |
A child cough at night is common and often accompanies colds and nasal congestion, but recurring nighttime cough may also be part of asthma, croup or another condition.
Rather than focusing only on the time the cough occurs, pay attention to its frequency, duration, character, breathing pattern and associated symptoms.
Mouwasat Hospital's Pediatric Department provides care for common and specialized childhood respiratory conditions, including Pediatric Pulmonology services.
Nasal secretions and airway irritation may become more noticeable when lying down, while asthma, allergy and other conditions may also cause nighttime symptoms. The pattern alone does not identify the cause.
No. Asthma is one possibility, particularly when the cough recurs with wheezing, shortness of breath or exercise, but many other causes can produce nighttime coughing.
This depends on age and cause. Fluids, saline nasal care when congestion is present, and honey for children older than 1 year may help some children. Persistent cough or cough with wheezing or breathing difficulty should be evaluated.
No. Infants should sleep on their backs on a firm, flat, non-inclined surface without pillows or wedges. [7]
Seek urgent care when coughing is accompanied by severe breathing difficulty, blue or grey lips, marked lethargy, or stridor with respiratory distress. A daily cough lasting longer than 4 weeks also needs medical assessment.
Croup commonly causes a barking cough and often becomes worse at night. Breathing difficulty or stridor while resting needs prompt medical evaluation.


































































