How can i help you?
Latest Blogs
Explore All

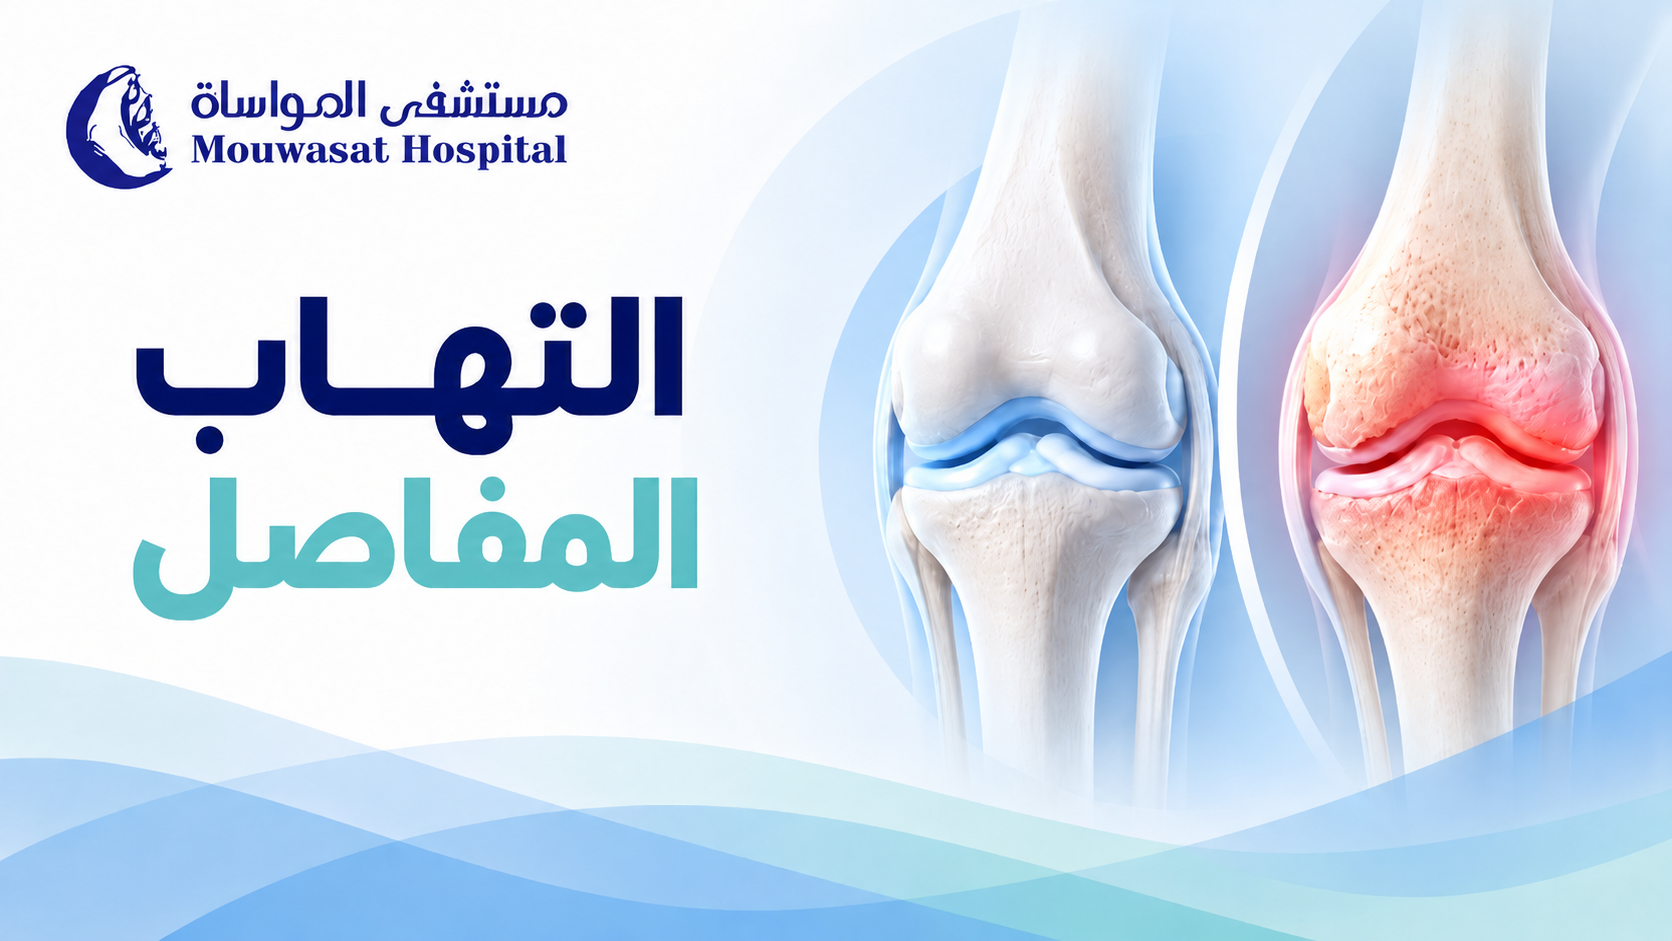


Rheumatoid arthritis can begin with symptoms that seem minor, such as morning stiffness in the hands, swelling of a few finger joints or difficulty making a fist. However, rheumatoid arthritis is more than joint pain. It is a chronic autoimmune inflammatory disease that can damage joints when inflammation remains uncontrolled. [1]
Important clues include joint swelling, morning stiffness lasting more than 30 minutes, involvement of the hands or feet on both sides of the body, and sometimes fatigue or low energy. [2]
Rheumatoid arthritis, or RA, is a chronic autoimmune disease.
The immune system mistakenly attacks the body's own tissues, with inflammation primarily affecting the synovium, the lining of the joints.
Persistent inflammation can eventually damage cartilage, bone and other structures supporting the joint. [2]
No.
Osteoarthritis involves progressive structural changes within the joint and surrounding tissues, whereas RA is an autoimmune inflammatory disease that can affect multiple joints and other parts of the body.
Possible early symptoms include:
Difficulty opening containers, buttoning clothes or moving the fingers normally in the morning can sometimes precede obvious joint deformity.
The hands and wrists are among the most commonly affected areas.
Symptoms can include:
RA often affects the wrists and several of the joints at the base and middle of the fingers. [2]
Usually not.
Joint deformity is more closely associated with structural damage from persistent disease and should not be the sign a person waits for before seeking evaluation.
RA can also begin or become prominent in the feet.
Symptoms may include:
RA commonly follows a symmetrical pattern.
For example, involvement of a joint in the right hand is often accompanied by involvement of the corresponding joint in the left hand.
However, this pattern is not absolute, especially early in the disease. [2]
Morning stiffness is one of the useful clinical clues in RA.
NIAMS notes that stiffness commonly lasts longer than 30 minutes after waking or after a prolonged period of rest. [2]
The duration of stiffness cannot diagnose RA by itself, but it contributes to the overall clinical pattern.
Yes.
RA is a systemic disease and can be associated with problems involving:
Some patients also develop rheumatoid nodules under the skin. [2]
Yes.
RA is approximately two to three times more common in women than in men. Researchers believe reproductive and hormonal factors may contribute in some people, alongside genetic and environmental factors. [2]
A person can have rheumatoid arthritis even when common antibody tests are negative.
The term seronegative RA is commonly used when antibodies such as rheumatoid factor and anti-CCP are not detected despite a clinical picture consistent with rheumatoid arthritis.
A negative rheumatoid factor does not rule out RA, and a positive rheumatoid factor does not prove RA. Some people with RA have normal blood tests, while some people without RA can have a positive RF. [3]
RF is an antibody found in many people with RA, but it is not present in everyone with the disease and can occur in people who do not have rheumatoid arthritis. [3]
Anti-cyclic citrullinated peptide antibodies are strongly associated with RA and may appear before symptoms in some people.
They are interpreted together with symptoms, physical examination and other findings. [3]
These tests help assess inflammation and may also be used to monitor disease activity and treatment response.
A CBC can identify issues such as anemia, which may occur in RA.
There is no single test that diagnoses rheumatoid arthritis. [3]
Doctors combine:
Yes.
X-rays may remain normal before structural joint damage becomes visible.
Ultrasound and MRI can help identify earlier inflammatory changes in selected situations. [3]

RA can begin causing joint damage during the first one or two years of disease, and established structural damage is generally not reversible. [3]
Early treatment therefore aims to:
There is currently no treatment that permanently eliminates rheumatoid arthritis.
However, modern treatment can allow many patients to reach:
Current EULAR recommendations continue to support a treat-to-target strategy, where treatment is adjusted according to whether the intended disease-control target is being achieved. [4]
Even after sustained remission, medications should not be stopped without medical supervision because complete discontinuation can lead to disease flare. [4]
RA treatment is designed to modify the disease itself rather than simply mask joint pain.
DMARDs are central to rheumatoid arthritis treatment.
Methotrexate is a major first-line treatment option for appropriate patients, while other conventional DMARDs include leflunomide and sulfasalazine. [4]
These can reduce symptoms, but they do not replace disease-modifying treatment when active RA is present.
Steroids may sometimes be used to control inflammation quickly, but their benefits must be balanced against potential adverse effects and they should be used under medical supervision.
Methotrexate has also been used at different doses and schedules in some cancer treatments, but in rheumatoid arthritis it is used as a disease-modifying immune therapy under a different treatment approach.
Receiving methotrexate for RA therefore does not mean a patient is receiving a cancer chemotherapy protocol.
It does require appropriate medical monitoring and laboratory testing.
Biologic DMARDs target specific parts of the immune system involved in RA inflammation.
They can be considered when the initial appropriate treatment strategy does not provide sufficient disease control. [4]
Targeted synthetic therapies such as JAK inhibitors are another option for selected patients, with individual assessment of cardiovascular, thromboembolic, malignancy and other risks. [4]
No.
A biologic is simply one treatment strategy used when it is appropriate for the patient's disease activity, previous treatment response and individual risk profile.
Yes.
Appropriate physical activity can help:
Physical and occupational therapists can also teach joint-protection techniques and strategies for daily activities. [3]
No food, supplement or herbal product has been shown to replace disease-modifying treatment for rheumatoid arthritis.
A balanced diet, healthy weight, regular appropriate activity and avoiding smoking can support overall health, but they do not replace control of autoimmune inflammation.
Yes. Long-term smoking is associated with an increased risk of developing RA and may be associated with more severe disease in people who continue to smoke. [2]
Consider assessment if you have:
Early signs can include swelling, pain and stiffness in the hands, wrists or feet, particularly when morning stiffness lasts more than 30 minutes.
Yes. Some people with RA have a negative rheumatoid factor, so RF alone cannot rule out the disease. [3]
Yes. A positive RF can occur in people who do not have RA, which is why the result must be interpreted in clinical context. [3]
It generally refers to rheumatoid arthritis in which commonly measured antibodies such as RF and anti-CCP are not detected.
Yes. Remission is a major treatment goal and means disease activity has become very low or clinically absent, although it does not necessarily mean the underlying tendency to RA has permanently disappeared.
Methotrexate is used in different medical settings. In rheumatoid arthritis it is used as a disease-modifying antirheumatic medicine under a treatment strategy that differs from cancer chemotherapy protocols.
There is currently no permanent cure, but modern treatment can control the disease effectively and allow many people to reach remission or low disease activity.
Rheumatoid arthritis is not simply joint pain. It is a chronic autoimmune inflammatory disease that may begin with swelling and stiffness in the hands or feet and prolonged morning stiffness.
A symmetrical pattern and stiffness lasting more than 30 minutes increase suspicion, but no single symptom or laboratory test is sufficient to diagnose RA.
A negative rheumatoid factor does not rule it out, and a positive result alone does not establish the diagnosis.
Early assessment is particularly important because permanent joint damage can begin during the early years of disease.
Although there is currently no permanent cure, modern disease-modifying treatment aims for remission or very low disease activity while protecting joint function and quality of life.
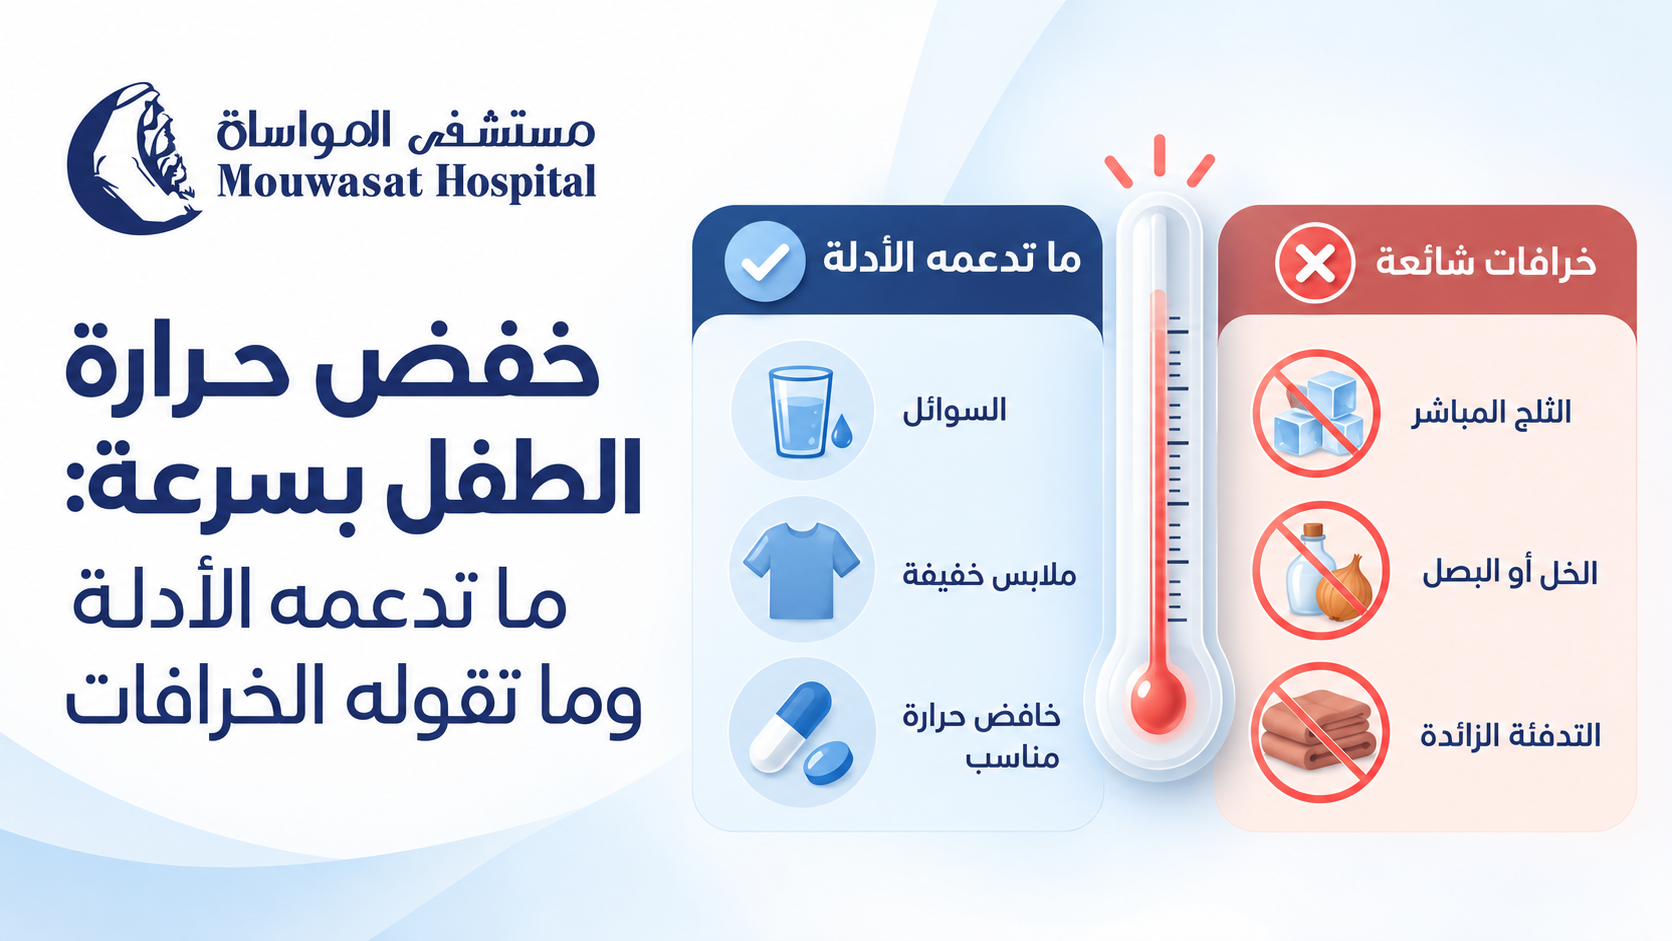
When a child's temperature rises, parents understandably want to know how to bring the fever down quickly. The safest approach, however, is not to force the thermometer back to 37°C as fast as possible.
Good fever care starts by asking whether the child appears well enough for home care or has warning signs that require medical assessment. The main goals are to keep the child comfortable, maintain hydration and monitor their overall condition. A fever falling after medicine does not prove that the illness is minor, and a fever that does not fall quickly does not by itself mean that the illness is serious. [1]
If your child is stable and has no warning signs, the fastest appropriate response is not an ice bath, cold compresses or a home remedy. Focus first on comfort, hydration and observation.
The NHS recommends regular fluids, continued breastfeeding, monitoring for dehydration and avoiding excessive clothing or bedding during a fever. [2]
Children can lose more fluid when they have a fever. Offer age-appropriate fluids regularly and continue normal breastfeeding or milk feeds in infants.
Watch for warning signs of dehydration such as a dry mouth, reduced tears, fewer wet nappies or reduced urination, and unusually low activity. Both NICE and the American Academy of Pediatrics emphasise hydration during fever care. [1] [3]
Do not wrap your child in heavy blankets in an attempt to make them sweat. At the same time, aggressive undressing is not necessary. Use comfortable clothing appropriate for the room temperature.
NICE advises that children with fever should be neither underdressed nor over-wrapped. [1]
A child with a temperature of 38.5°C who remains alert, drinks and interacts can look very different from another child with a lower temperature who is unusually sleepy, dehydrated or struggling to breathe.
Monitor alertness, breathing, drinking, urination, skin colour and associated symptoms as well as the temperature itself.
If you are unsure whether a reading is actually abnormal, see our guide to normal temperature in children and how the measurement site changes the reading.
NICE recommends considering either paracetamol (acetaminophen) or ibuprofen when a child with fever appears distressed or uncomfortable. Fever medicine should not be used solely to reduce the thermometer reading. [1]
This distinction matters. Fever-reducing medicine can make a child feel better, but it does not necessarily treat the cause of the illness or shorten its duration. [3]
NICE advises against giving both medicines at the same time. Changing from one medicine to the other or alternating them may only be considered in specific circumstances when distress continues or returns before the next dose is due. The NHS also advises parents not to alternate them unless a doctor or nurse recommends it. [1] [2]
Always check whether another cold, pain or fever product already contains the same active ingredient before giving more than one medicine.
Parents often become more worried when a fever remains high or decreases only slightly after medicine.
Avoid two common mistakes:
NICE specifically advises healthcare professionals not to use a decrease—or lack of decrease—in temperature after antipyretic medicine to distinguish serious from non-serious illness. [1]
Instead, look at your child. Are they more comfortable? Are they drinking? Are they alert and interacting? Is their breathing normal? Have any new warning signs appeared?
For a broader guide to interpreting fever by age and symptoms, see child fever treatment by age, temperature and symptoms.
Cooling the skin is traditionally used to bring a fever down, but modern guidelines do not recommend physical cooling as the main treatment for routine fever.
NICE does not recommend tepid sponging for treating fever, and the NHS advises against sponging or undressing a child in an attempt to cool them. [1] [2]
Fever is not simply excess heat sitting on the skin. During an infection, the body's temperature regulation changes. Aggressive external cooling may therefore cause discomfort or shivering without treating the underlying cause.
Not necessarily. A comfortable lukewarm bath may feel pleasant to some children, but it should not be used aggressively to chase a thermometer number. Cold water and ice baths should be avoided because they can cause shivering and discomfort. [3]
Saudi Ministry of Health guidance mentions room-temperature water compresses in the specific context of care after a febrile seizure has stopped. That does not mean compresses are the primary treatment for every childhood fever. [5]
A home remedy can be popular in search results without being proven safe or effective. Fever care should distinguish evidence-supported measures from traditional practices.
| Remedy | What the evidence says | Better approach |
|---|---|---|
| Vinegar compresses | Vinegar compresses should not be used to treat fever. Chemical burns have been reported after using vinegar in an attempt to lower fever. [6] | Avoid vinegar and use evidence-based fever care. |
| Rubbing alcohol | Unsafe. Isopropyl alcohol can be inhaled or absorbed through the skin and can cause poisoning. [7] | Never use rubbing alcohol on a child's body to reduce fever. |
| Lemon | A 2026 study reported a temperature reduction after a lemon juice and coconut oil compress, but it used a one-group pre-test/post-test design without a control group. This is not enough to establish effectiveness or overturn current guideline-based fever care. [8] | Do not treat lemon compresses as an established childhood fever therapy. |
| Onion on the feet | This is not part of recommended fever management in NICE, NHS or AAP guidance. | Do not rely on it or allow it to delay appropriate assessment. |
| Olive oil or other oils on the skin | These are not recommended fever-reduction treatments in the clinical guidelines used for this article. | Do not substitute topical oils for recommended fever care. |
| Ice or very cold water | Cold exposure can cause shivering and discomfort and does not treat the cause of the fever. [3] | Avoid aggressive cooling. |
Repeatedly checking the thermometer and trying to reach a specific number can distract from more important signs such as alertness, breathing and hydration.
Antipyretic medicines are mainly intended to relieve distress and discomfort rather than simply normalise body temperature. [1]
Do not change the dose or timing based on one temperature reading. Follow approved instructions and professional advice.
Some cold, flu and pain products may contain paracetamol or another ingredient already given separately. Always check the label.
Alternating medicines can increase the chance of timing or dosing errors and is not a routine approach for every child with fever. [1] [2]
These practices are either unsupported as routine fever treatment or, in the case of vinegar and rubbing alcohol, can cause direct harm. [6] [7]
A falling temperature does not rule out serious illness. Warning signs should be acted on regardless of the response to fever medicine. [1]
No. This is an important misconception because fear of seizures can lead parents to aggressively cool a child or repeatedly give fever medicine.
NICE states that antipyretic medicines do not prevent febrile seizures and should not be used specifically for that purpose. The American Academy of Pediatrics likewise notes that acetaminophen and ibuprofen may lower fever and improve comfort but do not prevent febrile seizures. [1] [4]
If a seizure occurs, do not try to force medicine into the child's mouth and do not put any object between their teeth. Managing the seizure safely becomes the immediate priority.
See our dedicated guide: febrile seizures in children: what to do in the first few minutes.
Seek medical assessment if:
In children older than 6 months, NICE advises that the height of the temperature alone should not be used to identify serious illness. The child's overall condition and accompanying symptoms remain essential. [1]
If you are trying to reduce your child's fever quickly, do not let speed lead to vinegar, rubbing alcohol, ice baths, extra medicine or unsupervised alternating of medicines.
Start by checking for warning signs. Then focus on fluids, breastfeeding, rest and comfortable clothing. If your child is distressed, an appropriate fever medicine may be used according to approved instructions and professional advice.
Remember that the response to fever medicine is not a test of how serious an illness is. The real goal is a more comfortable, adequately hydrated child whose overall condition is being monitored—not a thermometer forced back to 37°C.
For specialist assessment, visit Pediatrics at Mouwasat Hospital.
Arthritis is not a single disease, and joint pain does not automatically mean rheumatoid arthritis. The term covers more than 100 conditions affecting the joints and surrounding tissues, including osteoarthritis, rheumatoid arthritis, gout and psoriatic arthritis. These conditions have different causes, symptom patterns and treatments. [1]
Several clues can help distinguish them initially: when the pain occurs, whether the joint is swollen or warm, how long morning stiffness lasts, whether several joints are affected symmetrically and whether symptoms developed suddenly or gradually. However, symptoms alone cannot confirm the diagnosis.
Arthritis is a broad term for conditions affecting joints, tissues surrounding the joints and other connective tissues.
There are more than 100 different forms of arthritis, and their causes and treatment can be very different. [1]
Common examples include:
No.
Joint pain can also result from:
This is why the pattern of symptoms matters: the location, duration, swelling, warmth, morning stiffness and number of affected joints all help narrow the diagnosis.
Osteoarthritis is the most common form of arthritis. It involves progressive changes in the whole joint, including cartilage, bone and surrounding tissues, and commonly affects the knees, hips, hands and spine. [2]
Rheumatoid arthritis is a chronic autoimmune disease in which the immune system attacks the body's own tissues, especially the lining of the joints. It causes inflammation, pain, swelling and stiffness and may also affect organs outside the joints. [3]
Gout is an inflammatory arthritis caused by urate crystal deposition in and around joints. It commonly produces sudden episodes of severe pain and swelling. [5]
Psoriatic arthritis is an immune-mediated inflammatory condition associated with psoriasis. It can affect joints, the spine and the places where tendons and ligaments attach to bone. [6]
| Feature | Osteoarthritis | Rheumatoid arthritis | Gout | Psoriatic arthritis |
|---|---|---|---|---|
| Onset | Usually gradual | Can develop gradually or over a shorter period | Often sudden during a flare | Highly variable |
| Pain pattern | Often worse with use or loading | Can occur at rest and with movement | Often extremely painful during attacks | Inflammatory pain and stiffness |
| Morning stiffness | Usually shorter | Often longer than 30 minutes | Not usually the main feature | Often worse after rest or in the morning |
| Swelling and warmth | Variable | Common during active inflammation | Can be pronounced | Common |
| Helpful clues | Pain with activity, reduced movement | Symmetrical joints, fatigue | Big toe is common, sudden attacks | Psoriasis, nail changes, swollen whole digit |
These patterns are useful clues but cannot replace a medical assessment.
Osteoarthritis is a chronic joint condition that involves progressive changes in the joint and surrounding tissues. It is different from rheumatoid arthritis because it is not primarily an autoimmune attack on the joints. [2]
The most commonly affected joints include:
According to the World Health Organization, the knee is the most frequently affected joint worldwide. [2]
Rheumatoid arthritis is a chronic autoimmune inflammatory disease.
It commonly affects the wrists, hands, feet and other joints and often follows a symmetrical pattern. [3]
Rheumatoid arthritis can begin damaging joints relatively early in the disease. Treatment aims to control inflammation before permanent damage develops or progresses. [4]
No.
“Rheumatism” is often used as a broad, non-specific term for rheumatic or musculoskeletal complaints.
Rheumatoid arthritis is a specific autoimmune inflammatory disease with defined diagnostic criteria.
Gout develops when excess urate contributes to crystal formation in and around a joint, triggering inflammation. [5]
A typical flare may cause:
No. Some people have elevated serum urate without ever developing gout, so the blood level alone does not establish the diagnosis. [5]
Psoriatic arthritis is an inflammatory immune-mediated condition that often occurs in people with psoriasis.
Possible clues include:
A small number of people develop joint symptoms before the typical psoriasis rash appears. [6]
Symptoms vary by cause but can include:
The length and pattern of stiffness after waking or resting can help distinguish inflammatory from mechanical joint problems.
In rheumatoid arthritis, stiffness commonly lasts more than 30 minutes after waking or a long period of rest. [3]
In osteoarthritis, stiffness after inactivity is common but is usually shorter, while pain may become more noticeable during joint use or loading.
Stiffness duration alone, however, cannot confirm a diagnosis.
Medical assessment is particularly important if you have:
Seek prompt medical care for:
Gout and other inflammatory disorders can cause similar symptoms, but septic arthritis must be considered because a joint infection requires urgent treatment. [7]
| A rheumatologist may be particularly appropriate for | An orthopaedic doctor may be particularly appropriate for |
|---|---|
| Inflammation in several joints | Fractures, injuries or ligament problems |
| Suspected rheumatoid or autoimmune disease | Mechanical or surgical joint problems |
| Prolonged morning stiffness | Advanced structural joint damage needing surgical assessment |
| Recurrent gout or psoriatic arthritis | Traumatic cartilage or joint injury |
Some patients benefit from coordinated care involving rheumatology, orthopaedics, rehabilitation and physiotherapy.
There is no single test that diagnoses every form of arthritis.
The doctor may assess:
Additional testing may include:
Rheumatoid arthritis is not diagnosed by one laboratory result alone. Diagnosis combines the medical history, physical examination, laboratory tests and imaging when appropriate. [4]
Treatment depends on the diagnosis.
Management may include:
Exercise and healthy weight management are important parts of osteoarthritis care. [2]
The goal is not merely to relieve pain but to suppress inflammation and prevent or slow joint damage.
Treatment can include disease-modifying antirheumatic drugs and other therapies selected by a rheumatologist. [4]
Treatment of an acute gout flare is different from long-term treatment aimed at reducing urate levels and preventing future attacks. [5]
Treatment aims to control inflammation, protect joints and manage associated skin disease when present. [6]
Not necessarily.
For many people with arthritis, regular appropriate physical activity helps maintain movement, strengthen surrounding muscles and improve function.
The type and intensity of activity should be adjusted according to:
There is no single diet that cures all forms of arthritis.
Maintaining a healthy weight can reduce stress on weight-bearing joints, while conditions such as gout have their own dietary and metabolic considerations.
A single list of “foods to avoid for arthritis” therefore should not be applied to every patient.
Pain, stiffness or swelling in one or more joints may be the first sign, but the pattern varies greatly between arthritis types.
Persistent swelling in several joints, prolonged morning stiffness and symmetrical hand or foot symptoms raise suspicion, but medical evaluation is needed for diagnosis.
Osteoarthritis involves progressive structural changes in the joint, while rheumatoid arthritis is a systemic autoimmune inflammatory disease.
Yes. Arthritis is not limited to older adults. Rheumatoid arthritis, psoriatic arthritis and several other inflammatory conditions can occur in younger people.
No. Elevated serum urate can occur without gout, and the diagnosis depends on the overall clinical picture. [5]
Appropriate walking can be beneficial for many people, but activity may need modification during severe active inflammation, acute injury or when pain clearly worsens with loading.
No. Rheumatism is a broad term, while rheumatoid arthritis is a specific autoimmune inflammatory disease.
It depends on the cause. Many common forms are chronic, but modern treatment can control symptoms, suppress inflammation and reduce joint damage substantially.
Arthritis is not one diagnosis. Osteoarthritis, rheumatoid arthritis, gout and psoriatic arthritis can produce joint pain but differ significantly in their cause, symptom pattern and treatment.
Gradual pain that becomes worse with use may suggest osteoarthritis, while prolonged morning stiffness and symmetrical swollen joints can suggest inflammatory disease such as rheumatoid arthritis. Sudden severe pain and swelling in one joint may occur with gout or other acute conditions.
A suddenly hot, swollen and severely painful joint, particularly with fever or feeling unwell, needs prompt medical assessment.
The most useful first step is therefore not finding the strongest painkiller, but identifying which type of joint disease is causing the symptoms.
When a child's temperature rises, parents understandably want to know how to bring the fever down quickly. The safest approach, however, is not to force the thermometer back to 37°C as fast as possible.
Good fever care starts by asking whether the child appears well enough for home care or has warning signs that require medical assessment. The main goals are to keep the child comfortable, maintain hydration and monitor their overall condition. A fever falling after medicine does not prove that the illness is minor, and a fever that does not fall quickly does not by itself mean that the illness is serious. [1]
If your child is stable and has no warning signs, the fastest appropriate response is not an ice bath, cold compresses or a home remedy. Focus first on comfort, hydration and observation.
The NHS recommends regular fluids, continued breastfeeding, monitoring for dehydration and avoiding excessive clothing or bedding during a fever. [2]
Children can lose more fluid when they have a fever. Offer age-appropriate fluids regularly and continue normal breastfeeding or milk feeds in infants.
Watch for warning signs of dehydration such as a dry mouth, reduced tears, fewer wet nappies or reduced urination, and unusually low activity. Both NICE and the American Academy of Pediatrics emphasise hydration during fever care. [1] [3]
Do not wrap your child in heavy blankets in an attempt to make them sweat. At the same time, aggressive undressing is not necessary. Use comfortable clothing appropriate for the room temperature.
NICE advises that children with fever should be neither underdressed nor over-wrapped. [1]
A child with a temperature of 38.5°C who remains alert, drinks and interacts can look very different from another child with a lower temperature who is unusually sleepy, dehydrated or struggling to breathe.
Monitor alertness, breathing, drinking, urination, skin colour and associated symptoms as well as the temperature itself.
If you are unsure whether a reading is actually abnormal, see our guide to normal temperature in children and how the measurement site changes the reading.
NICE recommends considering either paracetamol (acetaminophen) or ibuprofen when a child with fever appears distressed or uncomfortable. Fever medicine should not be used solely to reduce the thermometer reading. [1]
This distinction matters. Fever-reducing medicine can make a child feel better, but it does not necessarily treat the cause of the illness or shorten its duration. [3]
NICE advises against giving both medicines at the same time. Changing from one medicine to the other or alternating them may only be considered in specific circumstances when distress continues or returns before the next dose is due. The NHS also advises parents not to alternate them unless a doctor or nurse recommends it. [1] [2]
Always check whether another cold, pain or fever product already contains the same active ingredient before giving more than one medicine.
Parents often become more worried when a fever remains high or decreases only slightly after medicine.
Avoid two common mistakes:
NICE specifically advises healthcare professionals not to use a decrease—or lack of decrease—in temperature after antipyretic medicine to distinguish serious from non-serious illness. [1]
Instead, look at your child. Are they more comfortable? Are they drinking? Are they alert and interacting? Is their breathing normal? Have any new warning signs appeared?
For a broader guide to interpreting fever by age and symptoms, see child fever treatment by age, temperature and symptoms.
Cooling the skin is traditionally used to bring a fever down, but modern guidelines do not recommend physical cooling as the main treatment for routine fever.
NICE does not recommend tepid sponging for treating fever, and the NHS advises against sponging or undressing a child in an attempt to cool them. [1] [2]
Fever is not simply excess heat sitting on the skin. During an infection, the body's temperature regulation changes. Aggressive external cooling may therefore cause discomfort or shivering without treating the underlying cause.
Not necessarily. A comfortable lukewarm bath may feel pleasant to some children, but it should not be used aggressively to chase a thermometer number. Cold water and ice baths should be avoided because they can cause shivering and discomfort. [3]
Saudi Ministry of Health guidance mentions room-temperature water compresses in the specific context of care after a febrile seizure has stopped. That does not mean compresses are the primary treatment for every childhood fever. [5]
A home remedy can be popular in search results without being proven safe or effective. Fever care should distinguish evidence-supported measures from traditional practices.
| Remedy | What the evidence says | Better approach |
|---|---|---|
| Vinegar compresses | Vinegar compresses should not be used to treat fever. Chemical burns have been reported after using vinegar in an attempt to lower fever. [6] | Avoid vinegar and use evidence-based fever care. |
| Rubbing alcohol | Unsafe. Isopropyl alcohol can be inhaled or absorbed through the skin and can cause poisoning. [7] | Never use rubbing alcohol on a child's body to reduce fever. |
| Lemon | A 2026 study reported a temperature reduction after a lemon juice and coconut oil compress, but it used a one-group pre-test/post-test design without a control group. This is not enough to establish effectiveness or overturn current guideline-based fever care. [8] | Do not treat lemon compresses as an established childhood fever therapy. |
| Onion on the feet | This is not part of recommended fever management in NICE, NHS or AAP guidance. | Do not rely on it or allow it to delay appropriate assessment. |
| Olive oil or other oils on the skin | These are not recommended fever-reduction treatments in the clinical guidelines used for this article. | Do not substitute topical oils for recommended fever care. |
| Ice or very cold water | Cold exposure can cause shivering and discomfort and does not treat the cause of the fever. [3] | Avoid aggressive cooling. |
Repeatedly checking the thermometer and trying to reach a specific number can distract from more important signs such as alertness, breathing and hydration.
Antipyretic medicines are mainly intended to relieve distress and discomfort rather than simply normalise body temperature. [1]
Do not change the dose or timing based on one temperature reading. Follow approved instructions and professional advice.
Some cold, flu and pain products may contain paracetamol or another ingredient already given separately. Always check the label.
Alternating medicines can increase the chance of timing or dosing errors and is not a routine approach for every child with fever. [1] [2]
These practices are either unsupported as routine fever treatment or, in the case of vinegar and rubbing alcohol, can cause direct harm. [6] [7]
A falling temperature does not rule out serious illness. Warning signs should be acted on regardless of the response to fever medicine. [1]
No. This is an important misconception because fear of seizures can lead parents to aggressively cool a child or repeatedly give fever medicine.
NICE states that antipyretic medicines do not prevent febrile seizures and should not be used specifically for that purpose. The American Academy of Pediatrics likewise notes that acetaminophen and ibuprofen may lower fever and improve comfort but do not prevent febrile seizures. [1] [4]
If a seizure occurs, do not try to force medicine into the child's mouth and do not put any object between their teeth. Managing the seizure safely becomes the immediate priority.
See our dedicated guide: febrile seizures in children: what to do in the first few minutes.
Seek medical assessment if:
In children older than 6 months, NICE advises that the height of the temperature alone should not be used to identify serious illness. The child's overall condition and accompanying symptoms remain essential. [1]
If you are trying to reduce your child's fever quickly, do not let speed lead to vinegar, rubbing alcohol, ice baths, extra medicine or unsupervised alternating of medicines.
Start by checking for warning signs. Then focus on fluids, breastfeeding, rest and comfortable clothing. If your child is distressed, an appropriate fever medicine may be used according to approved instructions and professional advice.
Remember that the response to fever medicine is not a test of how serious an illness is. The real goal is a more comfortable, adequately hydrated child whose overall condition is being monitored—not a thermometer forced back to 37°C.
For specialist assessment, visit Pediatrics at Mouwasat Hospital.

Seeing a child have a seizure during a fever can be frightening. In those first moments, however, the priority is not to force the seizure to stop or immediately cool the child's body. The most important actions are to protect the child from injury, place them safely on their side, time the seizure and know when emergency medical help is needed.
Most febrile seizures are short and do not cause long-term harm. Some situations do require urgent medical attention, particularly when a seizure lasts more than 5 minutes, it is the child's first seizure, breathing is difficult, or the child does not recover normally afterwards. [1] [2] [3]
Seek emergency medical help if the seizure lasts more than 5 minutes, this is the child's first seizure, breathing is difficult, or the child does not recover normally afterwards. [1] [2]
If your child starts having a seizure, focus on keeping them safe until the seizure stops or emergency help arrives.
Place your child on the floor or another low, safe surface. Move furniture, hard objects and anything sharp out of the way.
Saudi Ministry of Health guidance and the American Academy of Pediatrics recommend placing the child on their side so saliva or vomit can drain from the mouth rather than enter the airway. [1] [3]
Look at the clock as soon as the seizure begins. During a frightening event, a short seizure can feel much longer than it actually is, so accurate timing is extremely useful for both emergency decisions and medical assessment.
If possible, also observe whether the whole body is involved or only one side, whether another seizure occurs, and how the child behaves afterwards.
Do not hold the child's arms or legs down. Restraining the child will not stop the seizure and may cause injury.
A child cannot swallow their tongue. A spoon, cloth, finger or other object in the mouth can injure the teeth or jaw and may obstruct the airway. [2] [3]
Do not leave the child alone. Observe their breathing and skin colour and continue timing the event until the movements stop.
| Do not | Why? |
|---|---|
| Put anything in the mouth | It can injure the mouth or teeth and interfere with the airway. |
| Hold the child down | Restraint does not stop the seizure and can cause injury. |
| Give food, water or oral medicine | The child may not be able to swallow safely during the seizure or before fully recovering. |
| Place the child in a bath | During the seizure, airway safety and preventing injury matter more than trying to lower the temperature. |
| Automatically perform CPR while the child is convulsing | Most children resume normal breathing after the seizure. If breathing does not return after it stops, follow emergency-service instructions immediately. |
Seek emergency medical help if:
Saudi Ministry of Health seizure first-aid guidance identifies a first seizure, a seizure lasting longer than 5 minutes, breathing or waking difficulties, another seizure shortly afterwards, and injury during a seizure as reasons to seek emergency care. [2]
A child may be sleepy or confused for a while after a seizure. This can occur during the normal post-seizure recovery period.
After the movements stop:
Once your child is fully conscious, fever and discomfort can be managed appropriately. However, reducing the temperature does not reliably prevent another febrile seizure. [4]
For safe fever care after your child has recovered, read: how to reduce a child's fever: what the evidence supports and what the myths claim.
The two numbers answer different questions:
| Time | What it means |
|---|---|
| 5 minutes | An emergency-action threshold. An ongoing seizure beyond 5 minutes requires urgent medical help and may require treatment to stop it. |
| 15 minutes | One medical criterion used to distinguish simple from complex febrile seizures. It is not a time to wait before seeking help. |
A simple febrile seizure is typically generalised, lasts less than 15 minutes and does not recur within 24 hours. A complex febrile seizure may last longer, have focal features or recur during the same 24-hour period. [7]
A febrile seizure is a seizure that occurs in some young children around the time of an illness causing fever. They occur most commonly from about 6 months to 5 years of age, and the seizure may occasionally be the first sign that the child is becoming ill. [1] [3]
A child may temporarily lose consciousness, become stiff, have jerking movements of the arms and legs, roll their eyes or have a brief change in facial colour.
A very high fever is not always required. Febrile seizures can occur early in an illness, which is one reason aggressively chasing the thermometer number does not reliably prevent them.
Although the event can look frightening, short, simple febrile seizures generally do not cause brain damage, paralysis, intellectual disability or long-term neurological problems. [3]
Long, recurrent or focal seizures, or a child who does not recover normally, need urgent medical assessment because further treatment or investigation may be needed.
No. Having a febrile seizure does not mean that a child has epilepsy.
Epilepsy involves a tendency to have seizures that are not explained solely by fever or another temporary trigger, whereas febrile seizures occur in association with a febrile illness in young children.
Children who have experienced febrile seizures have a slightly higher future risk of epilepsy than children who have not, but the large majority do not develop epilepsy. [5]
Yes. Some children will have another febrile seizure during a future infection, but many will not.
Recent guidance from Cambridge University Hospitals reports recurrence in approximately 4 in 10 children who have experienced a febrile convulsion. Recurrence is more likely when the first event happens at a younger age or when there is a family history of seizures. [5]
A recurrence does not mean that the child has developed epilepsy, and it does not mean that parents failed to reduce the fever quickly enough.
This is one of the most common misconceptions about febrile seizures.
Paracetamol or ibuprofen may improve comfort during a fever, but they do not reliably prevent febrile seizures.
NICE specifically states that antipyretic medicines do not prevent febrile convulsions and should not be used specifically for this purpose. The American Academy of Pediatrics gives the same advice. [3] [4]
Do not give fever medicine to a child without fever solely because they have previously had a febrile seizure, and do not use extra doses or shorten dosing intervals in an attempt to prevent a seizure.
Useful details include:
If you are unsure whether the temperature itself is abnormal, see: normal temperature in children by measurement site.
For a broader guide to fever severity by age and symptoms, see: child fever treatment by age, temperature and symptoms.
If your child has a febrile seizure, the most important first-aid steps are to turn them onto their side in a safe place, remove objects that could cause injury, time the seizure, avoid restraining them and never put anything in their mouth.
Seek emergency medical help if the seizure lasts more than 5 minutes, it is the child's first seizure, breathing is difficult, seizures recur, or the child does not recover normally afterwards.
Most simple febrile seizures do not cause brain damage and do not mean that a child has epilepsy. Fever-reducing medicines also do not reliably prevent future febrile seizures.
For specialist assessment and follow-up, visit Pediatrics at Mouwasat Hospital.

A fever is one of the most common reasons parents become concerned about a child, but child fever treatment should not be based on the thermometer reading alone.
The child's age, breathing, alertness, ability to drink and associated symptoms can be more important than trying to bring the temperature down as quickly as possible.
Temperature readings can vary depending on the child's age and how the temperature is measured, so a number should always be interpreted in context.
A temperature of 38°C (100.4°F) or higher is particularly important in young infants. NICE classifies babies younger than 3 months with a temperature of 38°C or higher as being at high risk of serious illness. [1]
For babies aged 3 to 6 months, a temperature of 39°C or higher is considered at least an intermediate-risk feature. [1]
For more detail about measuring temperature, see: Normal Child Temperature: Why the Measurement Site Changes the Reading.
| Age or situation | What it means practically |
|---|---|
| Under 3 months and 38°C or higher | Urgent medical assessment is needed. [1] |
| 3–6 months and 39°C or higher | Requires prompt clinical attention, particularly when other symptoms are present. [1] |
| Older than 6 months | The height of the temperature alone should not be used to identify serious illness. [1] |
| Any child who appears seriously unwell | Needs medical assessment regardless of the temperature reading. |
A temperature of 39°C in a young infant is not the same situation as 39°C in an older child who is drinking, interacting and breathing comfortably. Age and overall condition change how the number should be interpreted.
Parents may naturally focus on repeatedly checking the temperature, but the child's condition provides essential information.
Pay attention to:
NICE specifically advises that in children older than 6 months, the height of body temperature alone should not be used to identify serious illness. [1]
No.
NICE advises clinicians not to rely on whether a temperature falls after an antipyretic to distinguish serious from non-serious illness. [1]
A response to fever medicine tells you something about temperature and comfort. It is not a diagnostic test showing that the underlying illness is harmless.
If the child's age and symptoms make home monitoring appropriate and there are no warning signs, care focuses on comfort, fluids and observation.
Offer fluids regularly. For a breastfed baby, breast milk remains the most appropriate fluid. [1]
Do not over-wrap a child with fever, but do not deliberately underdress them either. Keep clothing comfortable and appropriate for the environment. [1]
Watch fluid intake, urine output, breathing, alertness and activity, and check on a feverish child during the night. [1]
For more detailed practical guidance, see: How to Reduce a Child's Fever Safely Without Common Home-Care Mistakes.
No. Fever medicine is not simply a treatment for a number on the thermometer.
NICE recommends considering either paracetamol (acetaminophen) or ibuprofen for children with fever who appear distressed, rather than using an antipyretic solely to lower body temperature. [1]
However, medication suitability depends on age, weight, medical conditions, hydration and the concentration of the specific product.
Paracetamol is used to reduce discomfort associated with fever in children, but the correct amount depends on factors including the child's weight and product concentration. The American Academy of Pediatrics highlights medication dosing errors as an important safety concern and recommends confirming appropriate dosing, particularly in young children. [2]
Ibuprofen can also be used in appropriate children, but it has age, weight and medical-condition restrictions and is not automatically suitable for every child. Discuss its use with the child's doctor or pharmacist when unsure. [3]
NICE advises against giving both at the same time. Switching or alternating medicines should not be done routinely without appropriate guidance from a healthcare professional. [1]
Do not give aspirin to a child on your own. It should only be used when specifically prescribed for an appropriate medical condition.
There is no need to chase the thermometer reading with harsh cooling measures or unproven home remedies.
NICE does not recommend tepid sponging as a routine fever treatment, and the American Academy of Pediatrics advises against methods such as alcohol baths, ice packs and aggressive cooling. [1] [4]
| Method | Safer approach |
|---|---|
| Ice or very cold water | Avoid; it can cause discomfort and shivering and does not treat the cause of fever. |
| Alcohol on the skin | Do not use. |
| Vinegar, lemon, onion or oils to lower fever | Do not rely on these to treat fever or delay medical assessment. |
| Over-wrapping the child | Use comfortable clothing appropriate for the room temperature. |
No.
NICE states that antipyretic medicines do not prevent febrile convulsions and should not be used specifically for that purpose. [1]
The Saudi Ministry of Health explains that febrile seizures typically occur between 6 months and 5 years of age and that having a febrile seizure does not mean a child has epilepsy. [5]
A first seizure or any seizure associated with fever requires appropriate medical assessment.
For first-aid guidance, see: Febrile Seizures in Children: What to Do in the First Few Minutes.
Fever is a symptom rather than a disease. Infection is the most common cause, often viral, although bacterial infections and other conditions can also cause fever.
Associated symptoms may help the clinician identify the source, including:
Fever with cough does not automatically mean bacterial infection or a need for antibiotics. If cough is the main symptom, see: Child Cough Treatment by Cough Type, Age and Associated Symptoms.
Teething may be associated with a very slight rise in temperature, but the Saudi Ministry of Health advises medical consultation if a child's temperature reaches 38°C or higher rather than assuming the fever is caused by teething. [6]
Attributing a significant fever in a baby to teething can delay assessment of an infection or another illness. A clear fever, particularly in a young infant, should not simply be dismissed as teething.
| Situation | Next step |
|---|---|
| Older child is responsive, drinking, breathing comfortably and has no warning signs | Home monitoring, fluids and comfort measures may be appropriate, with medical advice if concerns develop. |
| Baby under 3 months with a temperature of 38°C or higher | Urgent medical assessment is required. |
| Baby aged 3–6 months with 39°C or higher, or who appears unwell | Prompt medical assessment is appropriate. |
| Fever lasts 5 days or longer, or the child is becoming more unwell | Medical evaluation is needed to identify the cause. [1] |
| Severe breathing difficulty, abnormal color, marked lethargy, difficulty waking, seizure or a non-blanching rash | Seek emergency medical care immediately. |
Seek medical advice or assessment when a child with fever:
The American Academy of Pediatrics also emphasizes how the child looks and behaves and the presence of associated symptoms when deciding when a pediatrician should be contacted. [4]
Mouwasat Hospital's Pediatric Department provides comprehensive care for infants, children and adolescents, including general and specialized pediatric services.
Safe child fever treatment starts with the child's age and an accurate temperature measurement, followed by careful attention to breathing, hydration, alertness and associated symptoms.
Fever medicine may be appropriate to improve comfort in selected children, but it does not treat the underlying cause and should not be used solely to force the temperature back to normal.
In a young infant or any child with warning signs, medical assessment matters more than trying another method to lower the temperature at home.
It depends on age and associated symptoms. In children older than 6 months, temperature alone does not determine severity. In a baby aged 3–6 months, 39°C or higher is an important risk feature requiring medical assessment. [1]
No. Fever medicine is generally used to improve comfort rather than simply reduce the number. However, a baby younger than 3 months with a temperature of 38°C or higher needs urgent medical assessment. [1]
There is no single best choice for every child. Paracetamol or ibuprofen may be appropriate in certain children, but medicine selection and dosing depend on age, weight, medical history and product concentration. Confirm the appropriate choice and dose with a doctor or pharmacist.
Do not routinely give both together or alternate them without medical guidance. [1]
No. Antipyretic medicines do not prevent febrile seizures. [1]
No. The response to fever medicine cannot reliably distinguish serious from non-serious illness. [1]
Teething may cause only a slight rise in temperature. The Saudi Ministry of Health advises medical consultation if the temperature reaches 38°C or higher. [6]

When a thermometer shows 37.5°C or 38°C, the natural question is whether this is a normal temperature for a child or a fever. The number alone, however, does not tell the full story.
A child's age, the site where the temperature was measured, the type of thermometer, the measurement technique, activity level and even a recent bath can affect the reading.
For that reason, a temperature of 37.5°C measured under the arm should not automatically be interpreted in the same way as 37.5°C measured in the ear or mouth. There is also no reliable formula for adding or subtracting a fixed number of degrees to convert a reading from one measurement site to another. [1] [4]
There is no single temperature that is normal for every child at every moment. The American Academy of Pediatrics notes that normal body temperature varies with a child's age, activity level and time of day. The NHS describes the average normal temperature in babies and children as approximately 36.4°C, while noting that normal variation occurs. [1] [3]
For parents, the measurement site is particularly important because different parts of the body can produce slightly different readings.
The Canadian Paediatric Society provides the following reference ranges according to measurement site: [5]
| Measurement site | Approximate reference range | What to know |
|---|---|---|
| Armpit | 36.5–37.5°C | Easy and commonly used but less precise than some other methods. |
| Mouth | 35.5–37.5°C | Suitable for older children who can hold the thermometer correctly. |
| Ear | 35.8–37.9°C | Accuracy depends heavily on correct positioning in the ear canal. |
| Rectum | 36.6–37.9°C | Highly accurate but invasive and not routinely recommended by every guideline. |
These are reference ranges rather than rigid conversion or diagnostic rules. A temperature should always be interpreted alongside the measurement site, the child's age and the child's overall condition.
Different thermometers estimate body temperature from different parts of the body. The American Academy of Pediatrics considers rectal temperature the most accurate, followed by forehead measurements. Oral and ear measurements can also be accurate when performed correctly, while armpit temperatures are generally less accurate and are often used for screening. [1]
NICE takes a less invasive approach for routine temperature measurement in children younger than 5. It recommends an electronic thermometer in the armpit for infants younger than 4 weeks and either an axillary thermometer or infrared ear thermometer for children aged 4 weeks to 5 years. [2]
These recommendations are not necessarily contradictory. They reflect the balance between measurement accuracy, practicality and safe routine use.
Armpit, or axillary, measurement is widely used in babies and young children because it is simple and non-invasive. The Canadian Paediatric Society lists an approximate normal axillary range of 36.5–37.5°C. [5]
Technique matters. The thermometer tip should sit against the skin in the centre of the armpit, with the child's arm held firmly against the body until the thermometer completes the measurement. The NHS recommends digital armpit measurement for children younger than 5 years. [3]
| Age | Practical option | Important consideration |
|---|---|---|
| Newborns and young infants | Digital armpit measurement is a practical routine option supported by NICE and the NHS. | A temperature of 38°C or higher in a baby younger than 3 months needs urgent assessment. |
| From around 6 months | Armpit or a properly used ear thermometer. | The AAP does not recommend ear thermometers in younger infants because their ear canals are narrow. |
| Older children | Ear, oral or forehead measurement may be appropriate depending on the device and the child's ability to cooperate. | The AAP generally considers oral measurement suitable from about age 4 if the child can use the thermometer correctly. |
Although rectal measurements are considered highly accurate by some organisations, they are more invasive. NICE does not recommend routine oral or rectal temperature measurement in children aged 0 to 5 years. If a rectal measurement is considered necessary, parents should use an appropriate technique and follow medical advice. [1] [2]
No fixed amount should automatically be added to an armpit temperature.
A common rule of thumb is to add 0.5°C or even 1°C to an underarm reading to estimate the child's “real” temperature. This can create false precision.
Mayo Clinic explains that readings can differ depending on where temperature is measured, but there is no exact way to add or subtract a fixed degree value to make readings from different parts of the body match. When following a child's temperature over time, it is more useful to compare measurements taken in the same way. [4]
Therefore, if a child's temperature is 37.7°C under the arm, do not automatically convert it to 38.2°C or 38.7°C. Record it as 37.7°C axillary and interpret it with the child's age, symptoms and overall condition.
Small changes do not always mean the illness itself has suddenly changed. Temperature readings can be affected by:
The NHS recommends allowing a child to cool down for a few minutes before repeating the temperature if they have just had a bath, been very active, been heavily wrapped or stayed in a very warm room. [3]
If fever is confirmed, read our detailed guide to child fever treatment by age, temperature and symptoms.
| Reading | How to interpret it |
|---|---|
| 35.5°C | This may fall near the lower end of some measurement ranges, particularly oral readings, but would be relatively low for others. Repeat an unexpected reading, especially if the child feels cold or appears unwell. |
| 36°C | This can be normal depending on the child, measurement site and time of day. |
| 37.5°C | The site matters. This may sit near the upper end of normal reference ranges for some methods and should not be interpreted without knowing how it was measured. |
| 38°C | This is commonly used as a fever threshold. In a baby younger than 3 months, it requires urgent medical assessment. |
| 39°C | This is not a normal temperature. NICE considers 39°C or higher in children aged 3 to 6 months at least an intermediate-risk feature for serious illness. In children older than 6 months, the number alone does not determine illness severity. |
NICE specifically advises that in children older than 6 months, the height of the temperature alone should not be used to identify serious illness. The child's appearance and accompanying symptoms remain crucial. [2]
Normal temperature can vary somewhat with age, activity and time of day. In everyday home monitoring, however, parents do not need to memorise a different “normal number” for every age.
Age is more important because it affects which measurement method is appropriate and how urgently fever should be assessed.
For example, 38°C carries a very different level of concern in a 2-month-old baby than it does in an otherwise well 5-year-old child. [2]
Seek prompt medical assessment if:
If a seizure occurs with fever, see our guide to febrile seizure first aid and what to do in the first few minutes.
The goal of fever care is not to force the thermometer back to 37°C at all costs. The child's comfort, hydration, overall condition and the cause of the fever matter more than chasing a particular number.
A temperature falling after fever medicine does not prove that the underlying illness is minor, and a temperature that does not fall quickly does not by itself diagnose a serious illness.
For safe home care and common cooling mistakes to avoid, see: how to reduce a child's fever safely.
A child's normal temperature cannot be interpreted separately from the way it was measured. Armpit, ear, mouth, forehead and rectal measurements can produce different readings, while age, technique, activity and environmental conditions can also influence the result.
Do not automatically add 0.5°C or 1°C to an armpit temperature. Record the measurement site, make sure the thermometer is being used correctly and repeat an unexpected reading before interpreting it alongside your child's age and overall condition.
For specialist assessment of fever or other concerning symptoms, visit Pediatrics at Mouwasat Hospital.
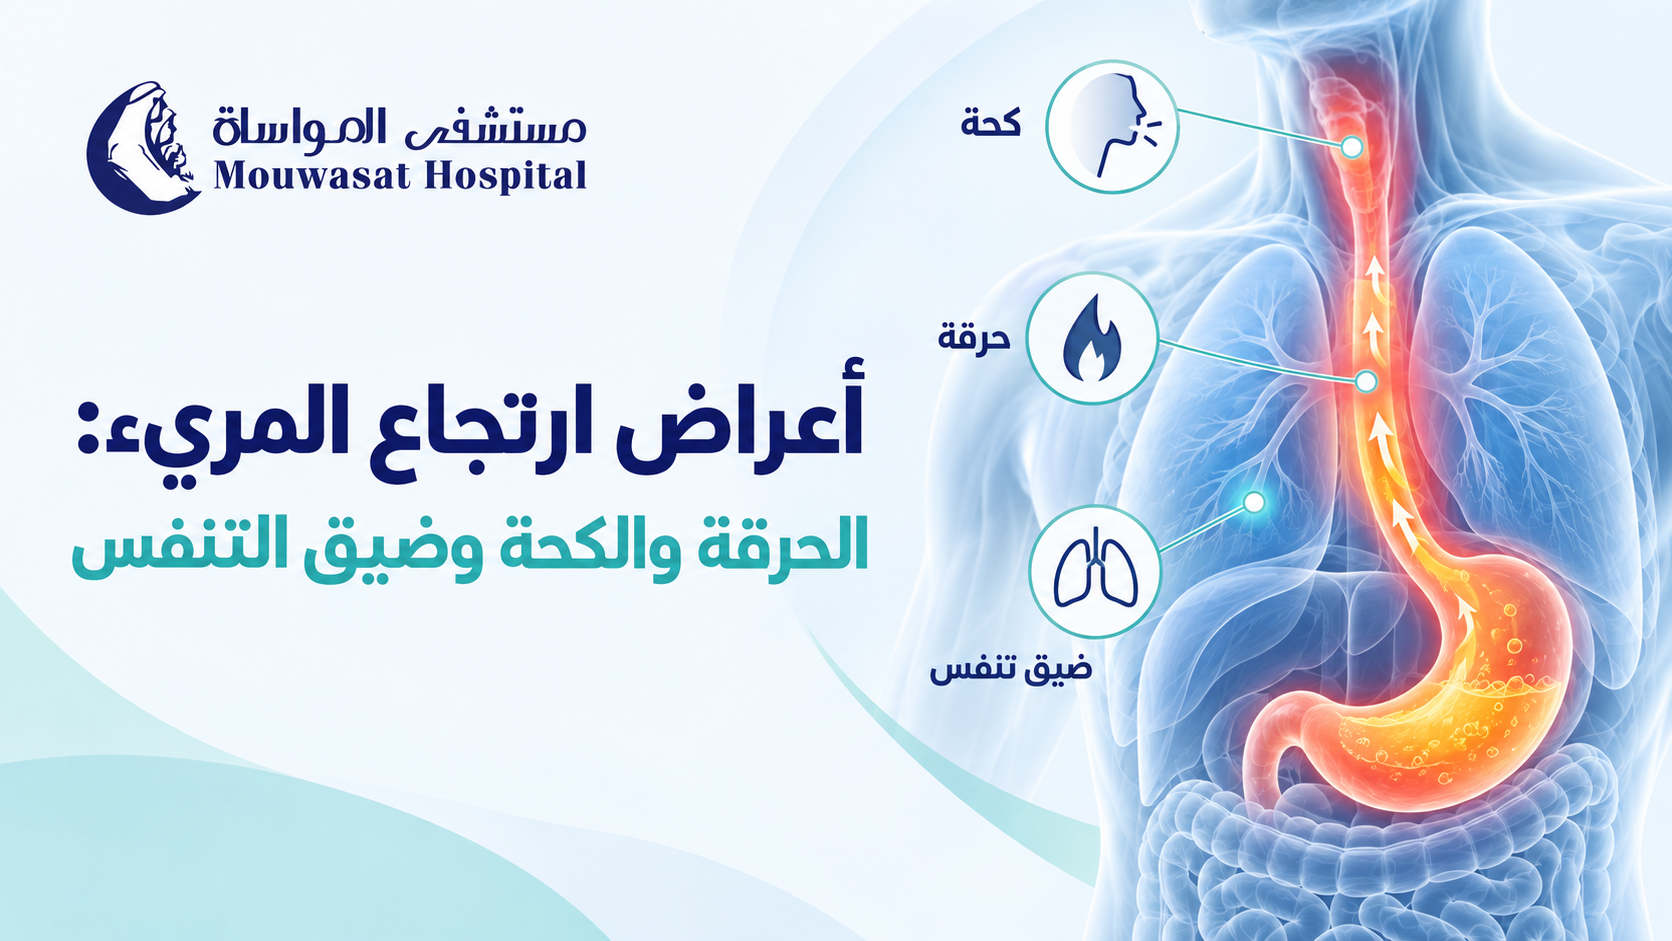
GERD symptoms vary from person to person. Heartburn behind the breastbone and regurgitation of stomach contents into the throat or mouth are among the most common symptoms, but some people may also experience cough, hoarseness, nausea, chest pain, or difficulty swallowing.
Not every symptom that occurs in someone with reflux is necessarily caused by GERD. Understanding which symptoms are typical, which may have several possible causes, and which require medical assessment can help avoid incorrect self-diagnosis.
The most common symptoms of gastroesophageal reflux disease are heartburn and regurgitation. Heartburn is typically felt as a burning sensation behind the breastbone, while regurgitation occurs when stomach contents travel back into the esophagus, throat, or mouth. [1]
Other symptoms may include:
Symptoms may become more noticeable:
The Saudi Ministry of Health notes that reflux symptoms may worsen after overeating and while bending or lying down. [2]
Occasional heartburn after a large meal does not automatically mean that a person has GERD. GERD becomes more likely when reflux causes recurrent troublesome symptoms or complications.
GERD-related heartburn is often described as a burning sensation in the middle of the chest behind the breastbone and may rise toward the throat. [1]
It may occur after eating or worsen when lying down or bending over, and it can occur together with a sour taste or regurgitation.
However, chest pain has many possible causes. A person should not assume that new or significant chest pain is simply acid reflux.
Some people experience throat or voice symptoms alongside more typical reflux symptoms. These can include:
These symptoms alone do not prove that reflux is the cause. GERD guidelines recommend evaluating other possible causes of extraesophageal symptoms before attributing them to reflux. [3]
Allergies, sinus and nasal disorders, respiratory disease, and laryngeal conditions can produce similar symptoms.
GERD can be associated with chronic cough in some people. Medical sources also recognize hoarseness and other throat or lung-related symptoms among possible extraesophageal manifestations. [1]
However, cough has many possible causes, so cough alone is not enough to diagnose GERD.
Phlegm is not one of the classic symptoms of GERD. Some patients may notice increased throat secretions or frequent throat clearing, but allergies, respiratory infections, or postnasal drainage should also be considered.
GERD may coexist with respiratory or laryngeal symptoms in some patients, and reflux has been associated with chronic cough, asthma, and voice symptoms. [4]
However, shortness of breath should not automatically be attributed to GERD. It has many potential causes involving the heart, lungs, airways, infections, and other conditions.
Some patients may also describe nighttime throat irritation or a choking sensation, but recurrent or significant breathing difficulty requires medical assessment rather than assuming reflux is responsible.
Dizziness and headache are not typical GERD symptoms.
They may occur in someone who also has GERD, but their presence does not establish reflux as the cause. Recurrent or severe dizziness or headaches should therefore be evaluated separately rather than automatically being linked to acid reflux.
A symptom occurring in someone with GERD is not necessarily caused by GERD. This is especially important for dizziness, headaches, breathing symptoms, and throat complaints.
Anxiety and stress are not diagnostic symptoms of GERD, but they may worsen reflux symptoms or make them more noticeable in some individuals.
The Saudi Ministry of Health lists anxiety and stress among factors that may trigger reflux symptoms. [2]
This distinction matters: stress may be a trigger or symptom amplifier, but it is not evidence by itself that a person has GERD.
| Symptom | Relationship to GERD | What matters? |
|---|---|---|
| Heartburn behind the breastbone | Typical symptom | Often worsens after eating or when lying down. |
| Regurgitation or sour taste | Typical symptom | Stomach contents travel back toward the throat or mouth. |
| Cough or hoarseness | May be associated | These symptoms have many other possible causes. |
| Shortness of breath | May coexist in some patients | Other heart or lung causes should not be overlooked. |
| Dizziness or headache | Not typical GERD symptoms | Persistent symptoms should be assessed for other causes. |
| Difficulty or pain with swallowing | Can occur with GERD | Persistent swallowing difficulty warrants medical evaluation. |
| Chest pain | Can occur with GERD | New or severe chest pain should not automatically be attributed to reflux. |
Yes. Not everyone with GERD experiences classic heartburn. NIDDK notes that some adults with GERD may instead experience chest pain, nausea, swallowing problems, chronic cough, or hoarseness. [1]
When only atypical symptoms are present, however, determining whether reflux is truly responsible can be more difficult because the same symptoms can arise from several other conditions.
Occasional mild reflux may improve with lifestyle measures. Recurrent, troublesome, or persistent symptoms deserve medical assessment and an appropriate treatment plan.
For a detailed look at management options, read: GERD Treatment: Available Options and When to See a Doctor.
For a broader overview of the condition, see: GERD: Symptoms, Causes, Diagnosis and Treatment.
Medical evaluation is recommended when reflux symptoms are frequent or persistent, swallowing becomes difficult, nausea or vomiting continues, unexplained weight loss develops, or symptoms do not improve despite treatment. [2]
NIDDK also recommends medical assessment for symptoms such as:
Mouwasat Hospital's Gastroenterology & Endoscopy Department provides evaluation, diagnosis and treatment for digestive disorders including reflux-related symptoms.
Yes. Nausea can occur in some people with GERD, although it is not the most typical symptom. [1]
GERD can be associated with chronic cough, but cough has many other possible causes and cannot diagnose GERD by itself.
Phlegm is not a classic GERD symptom. Throat secretions and frequent throat clearing may occur, but allergies, respiratory infections, and postnasal drainage should also be considered.
Respiratory symptoms may coexist with reflux in some patients, but shortness of breath has many possible causes and should not automatically be attributed to GERD.
Dizziness is not a typical symptom of GERD. Frequent or significant dizziness should be assessed for other possible causes.
Nighttime reflux may cause throat irritation or unpleasant sensations in some people, but recurrent choking or breathing difficulty during sleep can have other causes and should be medically evaluated.
GERD can cause chest pain or burning, but new or severe chest pain should not automatically be assumed to be acid reflux.
































