

How can i help you?

Blolgs

Prostatitis: Symptoms, Types, Treatment and When Is It Serious?

Prostatitis: Symptoms, Types, Treatment and When Is It Serious?

Prostatitis: Symptoms, Types, Treatment and When Is It Serious?

Prostatitis: Symptoms, Types, Treatment and When Is It Serious?
site.CALENDAR_IMAGE_ALT
09/11/2026

Prostatitis: Symptoms, Types, Treatment and When Is It Serious?

Pelvic or perineal pain, burning during urination, urinary frequency, or pain with ejaculation often lead men to assume they have a prostate infection and need antibiotics.

However, prostatitis is not one single condition, and not every case of prostate or pelvic pain is caused by bacteria. Acute bacterial prostatitis requires prompt antimicrobial treatment, while chronic pelvic pain syndrome can produce similar symptoms without a proven bacterial infection.[1][2]

Recognizing that difference is essential because the treatment of acute infection is very different from the management of chronic pelvic pain or pelvic-floor dysfunction.

Key points:
  • Prostatitis includes several different conditions, not all of which are bacterial.
  • Fever and chills with urinary pain or difficulty can indicate acute bacterial prostatitis and need prompt assessment.
  • Pelvic pain lasting months without evidence of infection may be chronic prostatitis/chronic pelvic pain syndrome.
  • Repeated antibiotics are not an appropriate long-term strategy when bacterial infection is not demonstrated.
  • Pelvic-floor muscle dysfunction can contribute to symptoms in some men.
  • Active prostatitis can temporarily elevate PSA.
  • Complete inability to urinate or urinary symptoms accompanied by fever and chills require urgent medical assessment.

What Is Prostatitis?

Prostatitis describes several conditions associated with inflammation, pain, or urinary symptoms involving the prostate and surrounding pelvic region.

The prostate sits below the bladder and surrounds part of the urethra, which helps explain why prostate conditions can produce urinary as well as pelvic symptoms.[3]

Prostatitis does not automatically mean infection

Modern classification distinguishes bacterial prostatitis from chronic pelvic pain syndrome, which can produce prostatitis-like symptoms without an ongoing bacterial infection.[1]

What Are the Different Types of Prostatitis?

Type Nature Typical pattern
Acute bacterial prostatitis Sudden bacterial infection Rapid onset of urinary symptoms, pelvic pain, fever and chills
Chronic bacterial prostatitis Persistent or recurrent bacterial infection Milder or recurring symptoms and recurrent urinary infections
Chronic prostatitis/chronic pelvic pain syndrome Multifactorial chronic pain condition, not necessarily infection Pelvic pain lasting or recurring for at least three months, sometimes with urinary or sexual symptoms
Asymptomatic inflammatory prostatitis Inflammation found incidentally No symptoms and usually no specific treatment required

What Are the Symptoms of Prostatitis?

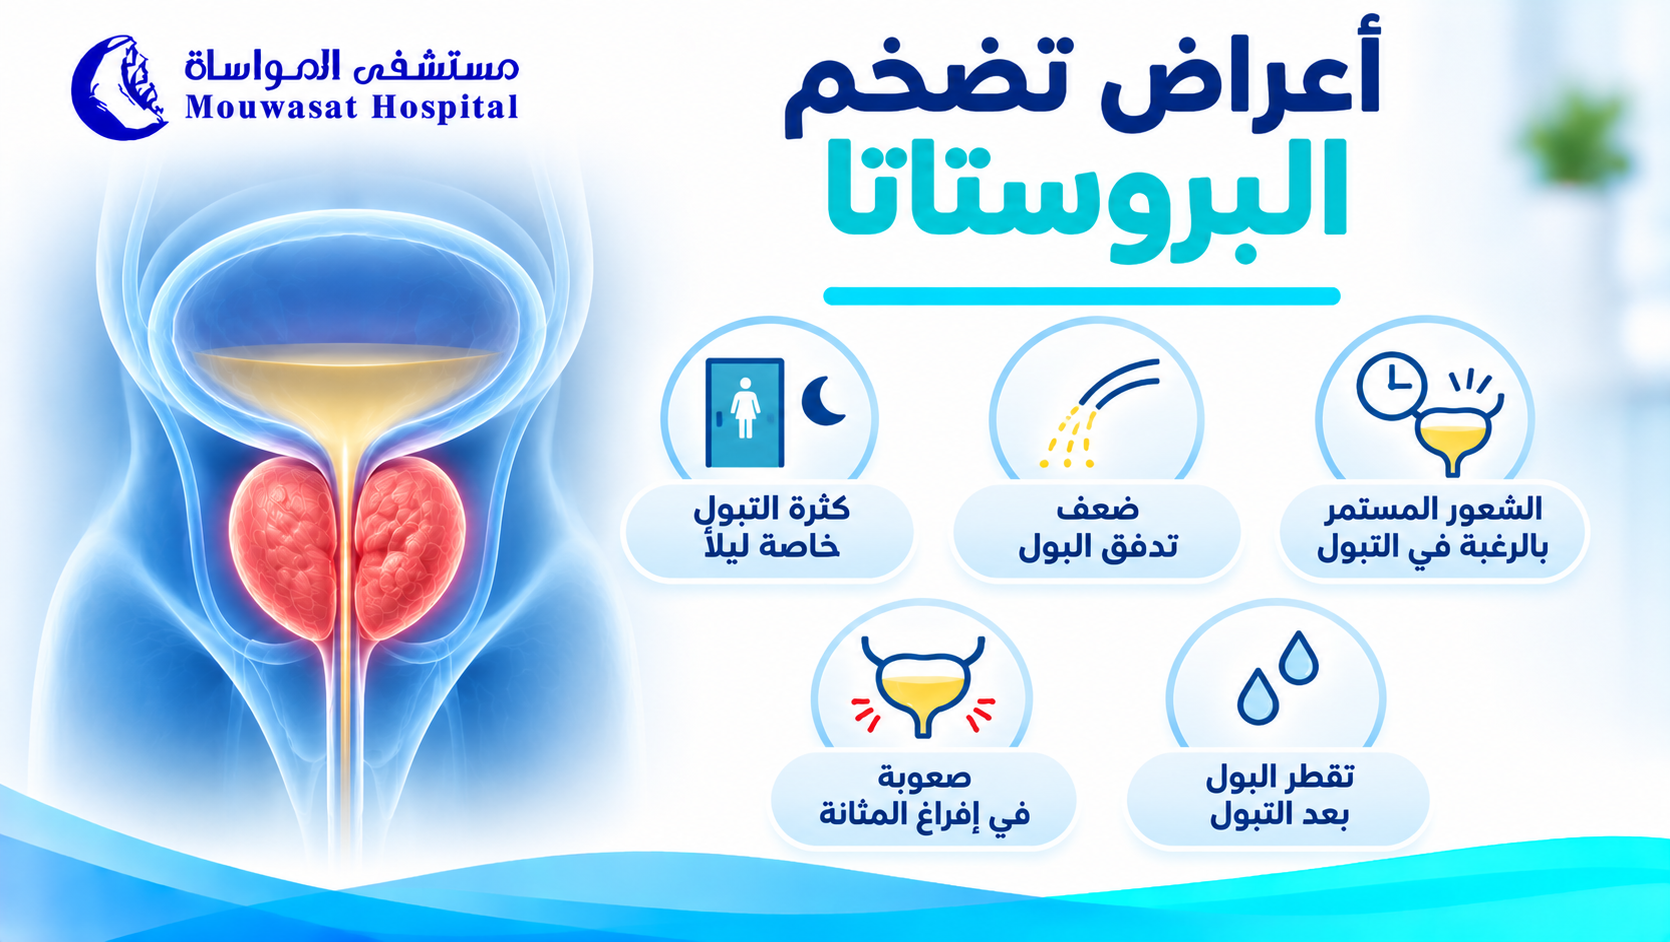
Symptoms vary by type and can include:

These symptoms can overlap with other urinary conditions. If weak flow, nocturia, or incomplete bladder emptying are dominant symptoms, see our guide to Enlarged Prostate Symptoms and Diagnosis.

What Are the Symptoms of Acute Bacterial Prostatitis?

Acute bacterial prostatitis typically begins suddenly and can cause significant systemic illness.

Possible symptoms include:

Fever and chills with urinary symptoms need prompt assessment

Acute bacterial prostatitis can occasionally lead to systemic infection or a prostatic abscess and should not be managed as routine pelvic discomfort.[1]

What Is Chronic Bacterial Prostatitis?

Chronic bacterial prostatitis is a recurrent or persistent bacterial infection that usually causes less dramatic symptoms than acute prostatitis.

Men may experience:

Symptoms can improve between episodes and then return.[3]

Chronic pelvic pain alone, however, does not establish a diagnosis of chronic bacterial infection.

What Is Chronic Prostatitis/Chronic Pelvic Pain Syndrome?

CP/CPPS is a chronic pain syndrome and is not necessarily caused by bacteria.

Pain or discomfort may persist or recur for at least three months in areas such as:

Pain during or after ejaculation is common, and urinary frequency, urgency, or weak flow may coexist.[3]

The condition can involve several mechanisms including pelvic-floor dysfunction, bladder symptoms, pain-processing pathways, and other biological and psychosocial factors.[2]

What Causes Prostatitis?

Bacterial prostatitis

Bacteria can travel from the urinary tract into the prostate. Recurrent or difficult-to-treat urinary infections can increase the likelihood of chronic bacterial prostatitis.[3]

CP/CPPS

There is usually no single demonstrated bacterial cause. Potential contributors can include:

How Do Bacterial Prostatitis and CP/CPPS Differ?

Feature Bacterial prostatitis CP/CPPS
Onset Can be sudden and severe in acute infection Usually chronic or recurrent
Fever/chills Common in acute infection Not typical
Cultures May demonstrate bacterial infection Do not usually demonstrate persistent infection
Treatment focus Antimicrobial treatment when infection is confirmed or strongly suspected Multimodal treatment tailored to pain and associated symptoms

How Is Prostatitis Diagnosed?

Diagnosis begins with symptoms, medical history, and examination and is then directed by the suspected type.

For suspected acute bacterial prostatitis, assessment may include:

Chronic symptoms require a broader evaluation because BPH, bladder dysfunction, urethral disease, sexually transmitted infection, and other pelvic pain conditions can produce overlapping complaints.

Book an appointment at Mouwasat Hospital

Is Prostate Massage Used for Diagnosis?

Urine samples obtained before and after prostate massage can be useful in selected cases of suspected chronic bacterial prostatitis.[1]

However:

Prostate massage should not be performed in acute bacterial prostatitis

Current EAU guidance advises against prostate massage during acute bacterial prostatitis because it can increase the risk of bacteria entering the bloodstream.[1]

Can Prostatitis Raise PSA?

Yes. PSA can rise during active prostatitis and the increase does not automatically mean prostate cancer.

Current EAU guidance notes that PSA testing provides no practical diagnostic information for active prostatitis and can complicate interpretation.[1]

For detailed PSA interpretation, read PSA Test: Normal Levels and What Results Mean.

If prostate-cancer risk remains a concern after infection has resolved and the patient has been appropriately reassessed, see our guide to Prostate Cancer Symptoms and Early Detection.

How Is Prostatitis Treated?

Treatment depends on whether the condition is a bacterial infection or a chronic pelvic pain syndrome.

How Is Acute Bacterial Prostatitis Treated?

Antibiotics are central to the treatment of acute bacterial prostatitis.[1]

Selection depends on illness severity, culture results when available, local antimicrobial resistance, and individual patient factors.

Patients with significant systemic illness may require:

Antibiotic choice and duration should therefore be determined medically rather than selected from an online list.

How Is Chronic Bacterial Prostatitis Treated?

Chronic bacterial prostatitis generally requires a longer antimicrobial course than straightforward acute urinary infections, preferably directed at the organism and susceptibility results when possible.[1]

Clinicians may also look for underlying urinary problems that contribute to repeated infection.

Persistent pelvic symptoms, however, should not automatically trigger repeated antibiotic courses when infection has not been established.

How Is CP/CPPS Treated?

Because chronic pelvic pain can involve several mechanisms, modern treatment is usually multimodal and individualized rather than based on one drug.[2]

Depending on the clinical pattern, management may include:

When are repeated antibiotics not the answer?

When bacterial infection is not demonstrated or an appropriate initial antimicrobial trial has not helped, the diagnosis and pain mechanisms should be reconsidered rather than repeating antibiotics indefinitely.[2]

What Is the Role of the Pelvic Floor?

Some men with chronic pelvic pain have painful or overactive pelvic-floor muscles.

This can contribute to:

When pelvic-floor dysfunction is identified, treatment by appropriately trained pelvic-health physiotherapists can form part of a broader pain-management strategy, using approaches such as myofascial treatment, relaxation, stretching, or biofeedback depending on the findings.[2]

Can Prostatitis Be Cured?

The answer depends on the type.

Acute bacterial prostatitis often resolves completely with appropriate treatment.

Chronic bacterial prostatitis may require longer treatment and can recur in some men.

CP/CPPS may behave as a chronic condition with periods of improvement and flare, but symptoms can often be substantially improved with appropriate multimodal management.

Can Prostatitis Affect Sexual Function?

Prostatitis and chronic pelvic pain can be associated with:

This does not mean that prostatitis inevitably causes permanent erectile dysfunction.

Addressing pain, pelvic-floor dysfunction, and associated factors can also improve sexual symptoms in some men.[2]

Can Prostatitis Affect Fertility?

The prostate contributes fluid to semen, and some inflammatory or infectious conditions can affect reproductive function.

However, prostatitis does not automatically mean infertility.

Men experiencing difficulty conceiving should have fertility evaluated directly rather than assuming prostatitis is the only cause.

When Is Prostatitis Serious?

Seek urgent medical assessment if you have:
  • Complete inability to urinate.
  • Painful, frequent, urgent urination with fever and chills.
  • Visible blood in the urine.
  • Severe lower abdominal or urinary-tract pain.
  • Significant systemic illness with urinary symptoms.[3]

Acute bacterial prostatitis can occasionally lead to bloodstream infection or prostatic abscess, so systemic symptoms should not be ignored.[1]

Prostatitis Assessment at Mouwasat Hospital

The Urology Department at Mouwasat Hospital evaluates prostate and urinary-tract symptoms.

The appropriate work-up depends on whether the presentation suggests acute infection, recurrent bacterial prostatitis, chronic pelvic pain, BPH, or another urinary condition.

The goal is not simply to treat the symptom label “prostatitis,” but to determine which type of problem is actually present.
Meet our doctors at Mouwasat Hospital

Frequently Asked Questions About Prostatitis

How do I know if I have prostatitis?

Pelvic or perineal pain, burning urination, urinary frequency, difficulty urinating, and painful ejaculation can occur with prostatitis, but similar symptoms occur in other conditions and require proper assessment.

Does every prostatitis case need antibiotics?

No. Antibiotics are essential for bacterial prostatitis, but chronic pelvic pain syndrome is not necessarily caused by bacteria and often requires different treatment.

What is the strongest antibiotic for prostatitis?

There is no universally “strongest” antibiotic. Treatment depends on the causative organism, susceptibility results, local resistance, severity, and the individual patient.

Does chronic prostatitis always require antibiotics?

No. Chronic bacterial prostatitis may require antimicrobial therapy, whereas CP/CPPS usually needs a broader multimodal approach.

Can prostatitis increase PSA?

Yes. Active prostatitis can raise PSA temporarily, which is why the result should be interpreted in the correct clinical context.[1]

Can prostatitis cause erectile dysfunction?

Chronic pelvic pain can be associated with sexual dysfunction in some men, but prostatitis does not automatically cause permanent erectile dysfunction.

Can prostatitis cause infertility?

Not automatically. Some infections or inflammation can affect reproductive function, but infertility requires its own evaluation.

How long does prostatitis take to heal?

There is no single timeline. Acute bacterial infection, chronic bacterial prostatitis, and CP/CPPS have very different courses and treatments.

Can masturbation cause prostatitis?

There is no evidence that masturbation is a general direct cause of bacterial prostatitis. Ejaculation may worsen or trigger pain in some men with CP/CPPS, but that does not prove infection.

When is prostatitis dangerous?

Acute bacterial prostatitis becomes particularly concerning when urinary symptoms are accompanied by fever, chills, urinary retention, severe pain, or systemic illness.

Final Thoughts: Identify the Type Before Treating “Prostatitis”

The most important step in prostatitis treatment is not finding the strongest antibiotic. It is identifying what type of condition is present.

Acute bacterial prostatitis requires prompt antimicrobial therapy, chronic bacterial prostatitis requires appropriate confirmation and targeted management, while chronic pelvic pain syndrome may require treatment of pain, urinary symptoms, pelvic-floor dysfunction, and other contributing factors.

This distinction reduces unnecessary antibiotic exposure while ensuring that a genuine acute bacterial infection is treated promptly.

Medical disclaimer: This article is intended for general health education and should not be used to diagnose prostatitis or select antibiotic therapy without medical assessment.

Medical References

  1. European Association of Urology — Urological Infections: Bacterial Prostatitis, 2026
  2. European Association of Urology — Chronic Pelvic Pain: Management, 2026
  3. National Institute of Diabetes and Digestive and Kidney Diseases — Prostatitis: Inflammation of the Prostate


Prev
08/11/2026

Prostate Cancer: Symptoms, Risk Factors, and How It Is Detected Early

When men think about prostate cancer, the first question is often: “What symptoms should I look for?”

But one fact matters even more: early prostate cancer may cause no noticeable symptoms at all. This means early detection should not depend on waiting for urinary problems or pain. At the same time, urinary symptoms do not automatically mean cancer, because benign prostate enlargement, prostatitis, and other conditions can cause similar complaints.[1][2]

Modern prostate cancer assessment therefore considers individual risk, PSA when appropriate, clinical assessment, prostate MRI, and biopsy when clinically indicated rather than relying on one symptom or one blood-test result.[3][4]

Key points:
  • Early prostate cancer may cause no symptoms.
  • Difficulty urinating or frequent urination does not automatically mean prostate cancer.
  • Risk increases with age, strong family history, and certain inherited genetic changes.
  • PSA helps estimate prostate cancer risk but cannot diagnose cancer by itself.
  • PSA can also rise with benign prostate enlargement or prostatitis.
  • Prostate MRI now plays an important role before biopsy in many men with suspected prostate cancer.
  • Biopsy usually provides the tissue diagnosis needed to confirm prostate cancer.
  • Not every prostate cancer requires immediate treatment; selected low-risk cancers may be managed with active surveillance.

What Is Prostate Cancer?

The prostate is a small gland in the male reproductive system located below the bladder and surrounding part of the urethra. It produces some of the fluid that makes up semen.

Prostate cancer develops when cells within the prostate begin growing and dividing abnormally.

Prostate cancers can behave very differently. Some grow so slowly that they may never cause a serious problem, while others are more aggressive and can spread beyond the prostate to lymph nodes, bones, or other organs.

This is why the words “prostate cancer” alone do not determine treatment. The grade, stage, risk group, overall health, and individual preferences all matter.

Can Prostate Cancer Develop Without Symptoms?

Yes.

Early localized prostate cancer usually does not cause noticeable symptoms, and some men are diagnosed while feeling completely well.[2]

No symptoms does not necessarily mean no prostate cancer

Men with relevant risk factors should not wait for pain or significant urinary difficulty before discussing whether prostate cancer screening is appropriate for them.

What Are the Symptoms of Prostate Cancer?

When prostate cancer does produce symptoms, they depend on the size, location, and extent of the disease.

Possible urinary symptoms include:

  • Difficulty starting urination.
  • A weak or interrupted urinary stream.
  • Frequent urination, especially at night.
  • Difficulty completely emptying the bladder.
  • Urinary urgency.
  • Blood in the urine in some cases.[1][6]

More advanced disease can cause symptoms such as:

  • Persistent pain in the back, hips, or pelvis.
  • Bone pain when cancer has spread to bone.
  • Other symptoms related to the location of metastatic disease.[6]
Symptoms alone cannot diagnose prostate cancer

Urinary symptoms are nonspecific and are often more suggestive of benign prostate enlargement than prostate cancer.[7]

Does Difficulty Urinating Mean Prostate Cancer?

No.

A weak stream, hesitancy, nocturia, urgency, and incomplete bladder emptying can occur with several conditions, particularly benign prostatic hyperplasia (BPH).

The National Cancer Institute notes that urinary obstruction symptoms are nonspecific and often more indicative of BPH than cancer.[7]

See Benign Prostatic Hyperplasia: Symptoms and When an Enlarged Prostate Needs Assessment.

Who Is at Higher Risk of Prostate Cancer?

Increasing Age

Prostate cancer risk rises with age, making age one of the strongest known risk factors.[2]

Family History

Having a father, brother, or son with prostate cancer can increase risk, particularly when several family members have been affected or diagnoses occurred at younger ages.[2]

Inherited Genetic Changes

Inherited changes involving genes such as BRCA1, BRCA2, or Lynch syndrome can increase prostate cancer risk in some families.[2]

Risk is not diagnosis

Risk factors help determine who may benefit from a more individualized discussion about early detection. They do not mean that prostate cancer is inevitable.

Can an Enlarged Prostate Turn Into Prostate Cancer?

No.

Benign prostatic hyperplasia and prostate cancer are different conditions.

BPH is not cancer and does not increase a person's risk of developing prostate cancer.[2]

However, both conditions become more common with age and can coexist, which is why urinary symptoms sometimes require assessment rather than self-diagnosis.

How Is Prostate Cancer Detected Early?

Early detection means looking for clinically important prostate cancer before it causes advanced symptoms.

There is no single test that provides the whole answer.

The pathway may involve:

  1. Assessing age, family history, inherited risk, and general health.
  2. Discussing the potential benefits and harms of PSA-based screening.
  3. Clinical prostate assessment when appropriate.
  4. Repeating PSA or refining risk when an initial result is unclear.
  5. Prostate MRI when cancer remains a relevant concern.
  6. Targeted or appropriate biopsy when the combined risk justifies tissue sampling.[3][4]

Book an appointment at Mouwasat Hospital

What Is the Role of PSA?

Prostate-specific antigen (PSA) is a protein produced by normal as well as malignant prostate cells.

PSA testing may be used for:

  • Early-detection discussions in appropriate men.
  • Evaluation of selected prostate-related symptoms.
  • Monitoring prostate cancer after diagnosis and treatment.[8]

Does a High PSA Mean Prostate Cancer?

No.

PSA may be elevated with:

  • Prostate cancer.
  • Benign prostatic hyperplasia.
  • Prostatitis or inflammation.
  • Other temporary factors that affect the prostate.[8]

There is no single PSA threshold that perfectly separates men with and without prostate cancer.

Read the dedicated guide: PSA Test: What Does the Result Mean and When Should Men Be Tested?.

PSA is not a simple positive-or-negative cancer test

Interpretation may consider age, previous PSA values, prostate size, risk factors, examination findings, MRI, and other tests.

What Is the Role of Prostate MRI?

Prostate MRI has become an important part of the modern diagnostic pathway for many men with suspected localized prostate cancer.

Current European guidance strongly recommends performing MRI before prostate biopsy in men with suspected organ-confined disease.[4]

MRI can:

  • Identify suspicious areas within the prostate.
  • Help estimate the likelihood of clinically significant cancer.
  • Guide targeted biopsy toward suspicious lesions.
  • Provide information about local disease extent.

Radiologists commonly use the PI-RADS system to classify MRI findings.

However, MRI is not an initial population-screening test, and a negative MRI does not exclude cancer in every patient. Clinical risk still matters.[4]

When Is a Prostate Biopsy Needed?

A prostate biopsy removes small tissue samples for examination under a microscope.

It is usually required to confirm prostate cancer and assess its microscopic characteristics.

Modern biopsy decisions consider more than PSA alone and may incorporate:

  • PSA level and previous results.
  • Family and genetic risk.
  • Clinical examination.
  • Prostate size and PSA density when relevant.
  • MRI findings and PI-RADS score.
  • Previous biopsy results.[3][4]

What Do Gleason Score and Grade Group Mean?

After cancer is identified on biopsy, the pathology report describes how abnormal the cancer cells look and how aggressively they are likely to behave.

The traditional Gleason score is now commonly translated into Grade Groups 1 through 5.

Grade Group General Meaning
1 Generally the least aggressive group
2–3 Intermediate features whose significance depends on other risk factors
4–5 More aggressive microscopic features and generally higher risk

Grade Group is interpreted together with PSA, stage, imaging, tumor volume, and other factors to determine the overall risk group.

What Are the Stages of Prostate Cancer?

A useful simplified framework is:

Disease Extent Meaning
Localized Cancer remains confined to the prostate.
Locally advanced Cancer has extended beyond the prostate into nearby tissues.
Metastatic Cancer has spread to distant lymph nodes, bones, or other organs.

Formal staging uses the TNM system together with PSA, Grade Group, imaging, and other clinical information.

Can Prostate Cancer Be Cured?

Many prostate cancers can be treated very successfully, particularly when disease is localized and suitable for curative treatment.

The outlook depends on:

  • Stage.
  • Grade Group.
  • PSA and overall risk group.
  • Whether cancer has spread.
  • Age and general health.
  • Response to treatment.

For metastatic disease, treatment may focus on long-term disease control, delaying progression, relieving symptoms, and preserving quality of life.

How Is Prostate Cancer Treated?

Treatment is individualized, and some men do not require immediate treatment.

Depending on stage and risk, options may include:[9]

  • Active surveillance for selected low-risk localized cancers.
  • Radical prostatectomy.
  • Radiation therapy.
  • Hormone therapy.
  • Chemotherapy, targeted therapies, and other systemic treatments in selected advanced disease.
Not treating immediately can sometimes be the correct treatment strategy

Active surveillance is a structured program for selected low-risk cancers. The cancer is monitored carefully, with treatment introduced if there is evidence that it is becoming more clinically significant.[9]

Prostate Cancer Care at Mouwasat Hospital

The Urology Department at Mouwasat Hospital evaluates and treats prostate disease, while the Oncology Department provides multidisciplinary care for localized, locally advanced, and metastatic prostate cancer.

Treatment may include active surveillance, surgery, hormonal therapy, and systemic treatment depending on the individual disease profile.

Selected urologic procedures at Mouwasat can also be performed using robotic surgery, including radical prostate surgery in appropriately selected patients.[10]

Meet our doctors at Mouwasat Hospital

When Should You See a Urologist?

Medical assessment is appropriate if:

  • You develop new or persistent urinary symptoms.
  • You notice blood in the urine or semen.
  • You have a strong family history of prostate cancer and want to discuss early detection.
  • Your PSA is elevated and needs appropriate interpretation.
  • You have an abnormal prostate examination or MRI result.
  • You want to know whether prostate cancer screening is appropriate for your individual risk.
Seek urgent assessment for new neurological symptoms with severe back pain

In a person with known or suspected prostate cancer, severe back pain accompanied by leg weakness or numbness or new loss of bladder or bowel control requires urgent assessment for possible spinal cord compression.

Frequently Asked Questions About Prostate Cancer

What are the first symptoms of prostate cancer?

There may be no early symptoms at all. Localized prostate cancer is often asymptomatic.[2]

Does frequent urination at night mean prostate cancer?

No. Nocturia has many causes and is commonly associated with benign prostate enlargement and other urinary conditions.

Can a weak urine stream be caused by prostate cancer?

It can occur with locally progressive disease, but it is nonspecific and is more commonly associated with benign prostate enlargement.[7]

Does an enlarged prostate become cancer?

No. BPH is a benign condition and is not a precancerous stage of prostate cancer.[2]

Does prostatitis cause prostate cancer?

A direct cause-and-effect relationship has not been established. Prostatitis can, however, raise PSA and complicate interpretation of the blood test.

Does a high PSA mean cancer?

No. PSA can rise because of cancer, BPH, prostatitis, and other factors.[8]

Does a normal PSA completely rule out prostate cancer?

No. There is no single PSA value that can exclude every prostate cancer.

Does every elevated PSA require a biopsy?

No. Repeat PSA, risk assessment, biomarkers, MRI, and other clinical information may be used before deciding whether biopsy is appropriate.[3][4]

Can MRI replace prostate biopsy?

Not in every patient. MRI helps identify and target suspicious lesions, but tissue sampling is still required in many men to confirm the diagnosis.[4]

Is prostate cancer always slow growing?

No. Some tumors grow very slowly, while others behave aggressively. Grade Group, stage, PSA, imaging, and other factors help distinguish risk.

Can prostate cancer be treated without surgery?

Yes. Depending on risk and stage, options can include active surveillance, radiation, hormone therapy, and other treatments.[9]

When should men be screened for prostate cancer?

There is no single age or schedule appropriate for every man. Screening decisions should account for age, family and genetic risk, general health, and individual preferences. These details are covered in our dedicated PSA and prostate screening guide.

Final Thoughts: Do Not Wait for Symptoms to Think About Prostate Health

Prostate cancer can be silent in its early stages, so the absence of pain or urinary symptoms does not automatically mean that early-detection discussions are unnecessary in men at relevant risk.

At the same time, urinary symptoms do not automatically mean cancer. Benign prostate enlargement, prostatitis, and other conditions are common causes of similar complaints.

Modern assessment combines individual risk with PSA when appropriate, clinical evaluation, prostate MRI, and biopsy when needed rather than relying on one symptom or one test result.

Once prostate cancer is diagnosed, stage, Grade Group, overall risk, health, and personal preferences determine whether active surveillance, surgery, radiation, hormone therapy, or another treatment strategy is most appropriate.

Medical disclaimer: This article provides general health education and does not replace individualized medical assessment or a discussion with your healthcare professional about the potential benefits and harms of prostate cancer screening.

Medical References

  1. Saudi Ministry of Health — Prostate Cancer
  2. National Cancer Institute — Understanding Prostate Changes
  3. AUA/SUO — Updates to Early Detection of Prostate Cancer Guideline, 2026
  4. European Association of Urology — Prostate Cancer: Diagnostic Evaluation
  5. National Cancer Institute — Prostate Cancer Screening
  6. National Cancer Institute — Prostate Cancer Treatment: Patient Version
  7. National Cancer Institute — Prostate Cancer: Clinical Presentation
  8. National Cancer Institute — Prostate-Specific Antigen (PSA) Test
  9. National Cancer Institute — Prostate Cancer Treatment Options
  10. Mouwasat Hospital — Robotic Urologic Surgery
Prostatitis: Symptoms, Types, Treatment and When Is It Serious?

Next
Prostatitis: Symptoms, Types, Treatment and When Is It Serious?
09/11/2026

Enlarged Prostate Treatment: When Are Medications Enough and When Is a Procedure Needed?

Once benign prostatic hyperplasia starts interfering with sleep, urination, or quality of life, one question usually follows: What is the best treatment for an enlarged prostate?

There is no single best option for every man. One patient may need monitoring only, another may respond well to medication, while another may benefit more from a minimally invasive procedure, laser treatment, or surgery.

The choice depends on symptom burden, prostate size and anatomy, degree of obstruction, risk of urinary retention, general health, sexual and ejaculatory priorities, and the balance between treatment durability and invasiveness.[1]

Key points:
  • Not every enlarged prostate requires immediate treatment.
  • Medications that relieve symptoms quickly are different from those that shrink the prostate and reduce progression risk.
  • Complications or persistent severe symptoms can shift the balance toward a procedure.
  • Rezūm and UroLift can offer less invasive treatment for appropriately selected men.
  • TURP remains an effective standard surgical treatment despite the development of newer techniques.
  • HoLEP and thulium laser enucleation can provide powerful relief of obstruction in appropriately selected patients.
  • No single treatment provides the best balance of symptom relief, durability, recovery, and sexual preservation for every patient.

Does Every Enlarged Prostate Need Treatment?

No.

Men with mild or moderately bothersome uncomplicated symptoms may sometimes be managed with watchful waiting rather than immediate medication or surgery.

Current European guidance recommends watchful waiting for men whose symptoms cause little bother, because many remain stable for years without developing major complications.[1]

For an explanation of symptoms and diagnostic assessment, read Enlarged Prostate Symptoms: Causes and Diagnosis.

What Is the Best Treatment for BPH?

There is no universally best treatment.

The better question is: which treatment offers the best balance for this patient's anatomy, symptoms, risks, and priorities?

Important factors include:

  • Symptom severity and quality-of-life impact.
  • Prostate size.
  • Prostate anatomy, including a potentially obstructing middle lobe.
  • Residual urine and degree of obstruction.
  • Previous urinary retention.
  • Recurrent infection, stones, bleeding, or other complications.
  • Age, medical conditions, and other medications.
  • Use of anticoagulant or antiplatelet therapy.
  • The importance of preserving ejaculation.
  • How much retreatment risk the patient is willing to accept for a less invasive procedure.
The newest treatment is not automatically the best treatment

Good treatment selection balances symptom relief, durability, recovery, complications, sexual priorities, and the patient's individual anatomy.

When Are Watchful Waiting and Lifestyle Measures Enough?

For men with mild symptoms and no significant complications, conservative management may include:

  • Adjusting fluid intake when nocturia is troublesome.
  • Reducing caffeine when it worsens urinary frequency or urgency.
  • Reviewing the timing of diuretic medications with a clinician.
  • Double voiding in selected patients.
  • Bladder training when storage symptoms are important.
  • Managing constipation and other lifestyle factors that worsen symptoms.

These measures may improve symptoms, but they should not be interpreted as evidence that specific foods or herbal products can reliably shrink an enlarged prostate.[1]

What Medications Are Used for an Enlarged Prostate?

BPH medications do not all serve the same purpose.

Goal Treatment class Main role
Relatively rapid symptom improvement Alpha blockers Reduce smooth-muscle tone and improve urinary symptoms without substantially shrinking the prostate.
Reduce prostate size and progression risk 5-alpha reductase inhibitors Work more slowly but can reduce prostate volume, retention risk, and future surgery in selected men.

Alpha Blockers: Faster Symptom Relief

Alpha blockers are commonly used in men with bothersome moderate-to-severe lower urinary tract symptoms.

They reduce smooth-muscle tone in and around the prostate and bladder outlet, which can improve urine flow and urinary symptoms relatively quickly.[1][2]

However, they do not significantly shrink the prostate and do not by themselves prevent future urinary retention or surgery.

The choice of drug also matters because different agents have different effects on blood pressure and ejaculation.

5-Alpha Reductase Inhibitors: Treating Prostate Growth

This medication class works differently by reducing hormonal stimulation of prostate growth.

It is generally more useful when genuine prostate enlargement is present and the risk of progression is greater.[1][2]

Potential benefits include:

  • Gradual reduction in prostate volume.
  • Improvement of symptoms over time.
  • Reduced risk of acute urinary retention.
  • Reduced likelihood of future BPH-related surgery in appropriate men.

The effect is slower than with alpha blockers, and sexual adverse effects can occur in some patients.

When Is Combination Therapy Used?

An alpha blocker and a prostate-shrinking medication may be combined when a man has significant symptoms together with demonstrable enlargement and a higher risk of progression.

The rationale is to combine quicker symptom improvement with longer-term reduction in progression risk.

The tradeoff is exposure to the adverse-effect profiles of both medication classes.[2]

What Is the Role of Tadalafil and Storage-Symptom Treatment?

Tadalafil can be considered as a treatment option for lower urinary tract symptoms attributed to BPH in selected men, including men who also have erectile dysfunction.[2]

Some patients have predominantly storage symptoms such as urgency, frequency, or overactive bladder rather than obstruction alone.

In appropriate men, bladder-directed medication may therefore be considered after evaluating bladder emptying and the overall clinical picture.

Book an appointment at Mouwasat Hospital

When Is Medication No Longer Enough?

A patient does not need to remain on medication indefinitely if symptoms remain unacceptable or complications develop.

A procedure may be considered when:

  • Symptoms remain significantly bothersome despite appropriate therapy.
  • Urinary flow remains substantially impaired.
  • A large amount of urine remains in the bladder after voiding.
  • Urinary retention recurs.
  • The patient prefers a procedure rather than long-term medication.
  • Complications change the risk-benefit balance.

When Is BPH Surgery or a Procedure Needed?

Current guidelines identify several situations in which procedural treatment becomes particularly important, including:[1][2]

  • Recurrent or refractory urinary retention.
  • Recurrent urinary tract infection related to obstruction.
  • Recurrent bladder stones.
  • Persistent visible bleeding attributable to BPH.
  • Upper urinary tract or kidney impairment from obstruction.
  • Bothersome symptoms that remain inadequately controlled with conservative or medical therapy.

What Is Rezūm Therapy?

Rezūm is a minimally invasive treatment that delivers controlled water-vapor thermal energy into selected areas of enlarged prostate tissue.

The treated tissue gradually shrinks, creating more room for urine to pass.

Potential advantages include:

  • A less invasive approach than major tissue-removing surgery.
  • Meaningful symptom improvement in appropriately selected patients.
  • Generally favorable preservation of erectile and ejaculatory function.

However, Rezūm is not automatically better than surgery.

More tissue-removing procedures may provide stronger objective relief of obstruction in some men, and some patients treated with minimally invasive approaches may require retreatment later.[1]

What Is UroLift?

UroLift, or prostatic urethral lift, uses small implants to retract obstructing prostate tissue away from the urethra rather than removing large amounts of tissue.

Its attractions include:

  • Relatively quick recovery.
  • A minimally invasive approach.
  • Low rates of ejaculatory dysfunction in appropriately selected men.

Its tradeoff is that symptom and flow improvement may be less pronounced than TURP, while retreatment is more common over time.[1]

Current EAU guidance particularly supports the option in men interested in preserving ejaculation whose prostate size and anatomy fit the selection criteria.[1]

What Is TURP?

Transurethral resection of the prostate (TURP) removes obstructing prostate tissue through the urethra without a traditional external surgical incision.

Despite the availability of newer technologies, TURP remains an effective standard procedure for appropriately selected men with BPH-related obstruction.[1]

Its strengths include:

  • Strong symptom improvement.
  • Meaningful improvement in urinary flow.
  • A large body of long-term clinical experience.

Patients should also discuss recovery, bleeding risk, and the likelihood of changes in ejaculation with their urologist.

What Is HoLEP?

HoLEP stands for holmium laser enucleation of the prostate.

It uses a holmium laser to separate obstructing adenoma from the prostate capsule before the tissue is removed.

EAU guidance supports HoLEP as an effective alternative to TURP or open prostate surgery in appropriate men.[1]

Advantages can include:

  • Powerful relief of obstruction.
  • Use across a broad range of prostate sizes in experienced hands.
  • Durable long-term outcomes.

Operator experience is particularly important because HoLEP has a meaningful technical learning curve.

What About Thulium Laser Treatment?

Thulium laser can be used for prostate vaporization or enucleation, depending on the technique.

Current European evidence supports thulium enucleation as an effective alternative to TURP, bipolar enucleation, or HoLEP in appropriate settings.[1]

Choice between holmium and thulium technology should therefore be based on patient anatomy, clinical circumstances, equipment, and surgeon expertise rather than assuming one laser is universally superior.

What Is Prostatic Artery Embolization?

Prostatic artery embolization (PAE) is an interventional radiology procedure that reduces blood flow to selected prostate arteries, leading to gradual shrinkage of prostate tissue.

It can be considered by selected men interested in a less invasive option.

However, evidence suggests that TURP generally provides greater improvements in urinary symptoms and flow, while PAE is associated with higher retreatment rates.[1]

Current European guidance recommends that patient selection and follow-up occur through collaboration between urologists and appropriately trained interventional radiologists.

How Does a Doctor Choose Between the Options?

Patient priority Options that may be discussed Important tradeoff
Symptoms are mild Watchful waiting and lifestyle measures Avoid unnecessary treatment while monitoring progression
Relatively fast medication relief Alpha blocker in an appropriate patient Improves symptoms but does not substantially shrink the prostate
Large prostate and higher progression risk Prostate-shrinking therapy ± combination treatment Slower symptom relief but reduced progression risk
Preserving ejaculation is a major priority UroLift or selected minimally invasive options Potentially less de-obstruction or greater retreatment risk
Strong and durable relief of obstruction TURP or laser enucleation depending on anatomy More invasive treatment with different recovery and ejaculatory effects
Recurrent retention or complications Procedural treatment becomes a stronger consideration The goal is preventing ongoing harm as well as relieving symptoms

What Is the Best BPH Treatment for Older Men?

Age alone should not determine treatment.

An active man in his seventies may be an excellent candidate for a procedure, while conservative management may be more suitable for a younger man with mild symptoms.

In older adults, clinicians also consider:

  • Blood pressure and fall risk.
  • Cardiovascular medications and blood thinners.
  • Kidney function.
  • Polypharmacy and medication interactions.
  • Urinary retention and residual urine.
  • Recurrent infections or bladder stones.
  • Anaesthetic and procedural risk.
  • Functional independence and quality of life.

How Do BPH Treatments Affect Ejaculation and Sexual Function?

This should be discussed before choosing a treatment.

Different medications and procedures carry different risks of ejaculatory and sexual side effects.

UroLift and some minimally invasive treatments tend to preserve ejaculation better in appropriately selected men, while TURP and tissue-removing procedures have a greater likelihood of changing ejaculation.[1]

That does not make ejaculation-preserving treatment universally superior; some men prioritize maximal relief of obstruction or durability instead.

BPH Treatment at Mouwasat Hospital

The Urology Department at Mouwasat Hospital evaluates and treats prostate and urinary tract conditions. Treatment availability varies by hospital, physician, and patient suitability.

Published Mouwasat physician profiles demonstrate experience with several BPH treatment options.

For example, a urology consultant at Mouwasat Hospital Dammam lists prostate treatment with holmium and thulium laser, TURP, UroLift, and Rezūm among the conditions and procedures treated.[3]

A urology consultant at Mouwasat Hospital Riyadh also lists medical and surgical management of benign prostate disease using TURP or Rezūm.[4]

Availability of a technique does not mean it is suitable for every patient or available at every Mouwasat location.

Meet our doctors at Mouwasat Hospital

Frequently Asked Questions About BPH Treatment

What is the fastest treatment for an enlarged prostate?

Some alpha-blocking medications can improve urinary symptoms relatively quickly, but faster symptom relief does not mean they shrink the prostate or prevent progression.

Can BPH be treated without surgery?

Yes. Many men can be managed with observation, lifestyle measures, medication, or minimally invasive procedures. Surgery becomes more important when symptoms remain severe or complications develop.

Can herbs cure an enlarged prostate?

Herbal products should not be treated as proven substitutes for established BPH therapies. Their composition and evidence vary, and they may interact with other medicines.

Do BPH medications shrink the prostate?

Not all of them. Alpha blockers primarily improve symptoms, while 5-alpha reductase inhibitors can gradually reduce prostate volume in appropriately selected men.

Do you need to take BPH medication for life?

It depends on the drug, response, risk of progression, prostate characteristics, and whether the patient later chooses a procedure.

Which is better: Rezūm or UroLift?

Neither is universally better. Prostate anatomy, size, middle-lobe anatomy, ejaculatory priorities, desired symptom relief, and tolerance for future retreatment all influence the choice.

Which is better: laser treatment or TURP?

Both can be highly effective. The best choice depends on prostate size, the specific laser technique, surgeon expertise, bleeding risk, comorbidities, and patient priorities.

Is HoLEP suitable for a large prostate?

HoLEP can be particularly effective in larger prostates when performed by an appropriately experienced surgeon.

Can the prostate grow back after a procedure?

The need for future treatment depends on the procedure and how much tissue was treated or removed. Some minimally invasive options have higher retreatment rates than more extensive tissue-removing procedures.

Does BPH surgery cause erectile dysfunction?

Different procedures have different sexual side-effect profiles. Changes in ejaculation are generally more common than new erectile dysfunction after several prostate procedures.

Does UroLift preserve ejaculation?

Preservation of ejaculatory function is one of the main advantages of UroLift in appropriately selected men.[1]

Does Rezūm affect sexual function?

Rezūm generally has a favorable sexual-function profile, but no procedure can guarantee that every patient will experience no sexual or ejaculatory changes.

When does BPH require surgery?

Surgery becomes a stronger consideration with recurrent retention, recurrent infection, bladder stones, persistent BPH-related bleeding, kidney or upper urinary tract effects from obstruction, or severe symptoms that remain inadequately controlled.

Final Thoughts: Treat the Patient's Problem, Not the Name of the Procedure

BPH treatment is not a contest between medication, Rezūm, UroLift, TURP, and laser surgery.

Observation may be ideal for one man, medication for another, while a patient with recurrent retention or severe obstruction may benefit more from definitive tissue-removing treatment.

Recovery time, durability, preservation of ejaculation, bleeding risk, and the strength of de-obstruction are all legitimate treatment priorities.

The right treatment therefore begins with symptoms, prostate anatomy, bladder function, complications, overall health, and patient goals and only then moves to comparing the options that actually fit that individual case.

Medical disclaimer: This article provides general health education and should not be used to select medication or a procedure without individualized medical assessment.

Medical References

  1. European Association of Urology — Management of Non-neurogenic Male LUTS: Disease Management, 2026
  2. American Urological Association — Management of Lower Urinary Tract Symptoms Attributed to BPH
  3. Mouwasat Hospital Dammam — Urology Treatment Profile
  4. Mouwasat Hospital Riyadh — Urology Treatment Profile
Next
Prev
  • 09/11/2026

    Enlarged Prostate Treatment: When Are Medications Enough and When Is a Procedure Needed?

    Once benign prostatic hyperplasia starts interfering with sleep, urination, or quality of life, one question usually follows: What is the best treatment for an enlarged prostate?

    There is no single best option for every man. One patient may need monitoring only, another may respond well to medication, while another may benefit more from a minimally invasive procedure, laser treatment, or surgery.

    The choice depends on symptom burden, prostate size and anatomy, degree of obstruction, risk of urinary retention, general health, sexual and ejaculatory priorities, and the balance between treatment durability and invasiveness.[1]

    Key points:
    • Not every enlarged prostate requires immediate treatment.
    • Medications that relieve symptoms quickly are different from those that shrink the prostate and reduce progression risk.
    • Complications or persistent severe symptoms can shift the balance toward a procedure.
    • Rezūm and UroLift can offer less invasive treatment for appropriately selected men.
    • TURP remains an effective standard surgical treatment despite the development of newer techniques.
    • HoLEP and thulium laser enucleation can provide powerful relief of obstruction in appropriately selected patients.
    • No single treatment provides the best balance of symptom relief, durability, recovery, and sexual preservation for every patient.

    Does Every Enlarged Prostate Need Treatment?

    No.

    Men with mild or moderately bothersome uncomplicated symptoms may sometimes be managed with watchful waiting rather than immediate medication or surgery.

    Current European guidance recommends watchful waiting for men whose symptoms cause little bother, because many remain stable for years without developing major complications.[1]

    For an explanation of symptoms and diagnostic assessment, read Enlarged Prostate Symptoms: Causes and Diagnosis.

    What Is the Best Treatment for BPH?

    There is no universally best treatment.

    The better question is: which treatment offers the best balance for this patient's anatomy, symptoms, risks, and priorities?

    Important factors include:

    • Symptom severity and quality-of-life impact.
    • Prostate size.
    • Prostate anatomy, including a potentially obstructing middle lobe.
    • Residual urine and degree of obstruction.
    • Previous urinary retention.
    • Recurrent infection, stones, bleeding, or other complications.
    • Age, medical conditions, and other medications.
    • Use of anticoagulant or antiplatelet therapy.
    • The importance of preserving ejaculation.
    • How much retreatment risk the patient is willing to accept for a less invasive procedure.
    The newest treatment is not automatically the best treatment

    Good treatment selection balances symptom relief, durability, recovery, complications, sexual priorities, and the patient's individual anatomy.

    When Are Watchful Waiting and Lifestyle Measures Enough?

    For men with mild symptoms and no significant complications, conservative management may include:

    • Adjusting fluid intake when nocturia is troublesome.
    • Reducing caffeine when it worsens urinary frequency or urgency.
    • Reviewing the timing of diuretic medications with a clinician.
    • Double voiding in selected patients.
    • Bladder training when storage symptoms are important.
    • Managing constipation and other lifestyle factors that worsen symptoms.

    These measures may improve symptoms, but they should not be interpreted as evidence that specific foods or herbal products can reliably shrink an enlarged prostate.[1]

    What Medications Are Used for an Enlarged Prostate?

    BPH medications do not all serve the same purpose.

    Goal Treatment class Main role
    Relatively rapid symptom improvement Alpha blockers Reduce smooth-muscle tone and improve urinary symptoms without substantially shrinking the prostate.
    Reduce prostate size and progression risk 5-alpha reductase inhibitors Work more slowly but can reduce prostate volume, retention risk, and future surgery in selected men.

    Alpha Blockers: Faster Symptom Relief

    Alpha blockers are commonly used in men with bothersome moderate-to-severe lower urinary tract symptoms.

    They reduce smooth-muscle tone in and around the prostate and bladder outlet, which can improve urine flow and urinary symptoms relatively quickly.[1][2]

    However, they do not significantly shrink the prostate and do not by themselves prevent future urinary retention or surgery.

    The choice of drug also matters because different agents have different effects on blood pressure and ejaculation.

    5-Alpha Reductase Inhibitors: Treating Prostate Growth

    This medication class works differently by reducing hormonal stimulation of prostate growth.

    It is generally more useful when genuine prostate enlargement is present and the risk of progression is greater.[1][2]

    Potential benefits include:

    • Gradual reduction in prostate volume.
    • Improvement of symptoms over time.
    • Reduced risk of acute urinary retention.
    • Reduced likelihood of future BPH-related surgery in appropriate men.

    The effect is slower than with alpha blockers, and sexual adverse effects can occur in some patients.

    When Is Combination Therapy Used?

    An alpha blocker and a prostate-shrinking medication may be combined when a man has significant symptoms together with demonstrable enlargement and a higher risk of progression.

    The rationale is to combine quicker symptom improvement with longer-term reduction in progression risk.

    The tradeoff is exposure to the adverse-effect profiles of both medication classes.[2]

    What Is the Role of Tadalafil and Storage-Symptom Treatment?

    Tadalafil can be considered as a treatment option for lower urinary tract symptoms attributed to BPH in selected men, including men who also have erectile dysfunction.[2]

    Some patients have predominantly storage symptoms such as urgency, frequency, or overactive bladder rather than obstruction alone.

    In appropriate men, bladder-directed medication may therefore be considered after evaluating bladder emptying and the overall clinical picture.

    Book an appointment at Mouwasat Hospital

    When Is Medication No Longer Enough?

    A patient does not need to remain on medication indefinitely if symptoms remain unacceptable or complications develop.

    A procedure may be considered when:

    • Symptoms remain significantly bothersome despite appropriate therapy.
    • Urinary flow remains substantially impaired.
    • A large amount of urine remains in the bladder after voiding.
    • Urinary retention recurs.
    • The patient prefers a procedure rather than long-term medication.
    • Complications change the risk-benefit balance.

    When Is BPH Surgery or a Procedure Needed?

    Current guidelines identify several situations in which procedural treatment becomes particularly important, including:[1][2]

    • Recurrent or refractory urinary retention.
    • Recurrent urinary tract infection related to obstruction.
    • Recurrent bladder stones.
    • Persistent visible bleeding attributable to BPH.
    • Upper urinary tract or kidney impairment from obstruction.
    • Bothersome symptoms that remain inadequately controlled with conservative or medical therapy.

    What Is Rezūm Therapy?

    Rezūm is a minimally invasive treatment that delivers controlled water-vapor thermal energy into selected areas of enlarged prostate tissue.

    The treated tissue gradually shrinks, creating more room for urine to pass.

    Potential advantages include:

    • A less invasive approach than major tissue-removing surgery.
    • Meaningful symptom improvement in appropriately selected patients.
    • Generally favorable preservation of erectile and ejaculatory function.

    However, Rezūm is not automatically better than surgery.

    More tissue-removing procedures may provide stronger objective relief of obstruction in some men, and some patients treated with minimally invasive approaches may require retreatment later.[1]

    What Is UroLift?

    UroLift, or prostatic urethral lift, uses small implants to retract obstructing prostate tissue away from the urethra rather than removing large amounts of tissue.

    Its attractions include:

    • Relatively quick recovery.
    • A minimally invasive approach.
    • Low rates of ejaculatory dysfunction in appropriately selected men.

    Its tradeoff is that symptom and flow improvement may be less pronounced than TURP, while retreatment is more common over time.[1]

    Current EAU guidance particularly supports the option in men interested in preserving ejaculation whose prostate size and anatomy fit the selection criteria.[1]

    What Is TURP?

    Transurethral resection of the prostate (TURP) removes obstructing prostate tissue through the urethra without a traditional external surgical incision.

    Despite the availability of newer technologies, TURP remains an effective standard procedure for appropriately selected men with BPH-related obstruction.[1]

    Its strengths include:

    • Strong symptom improvement.
    • Meaningful improvement in urinary flow.
    • A large body of long-term clinical experience.

    Patients should also discuss recovery, bleeding risk, and the likelihood of changes in ejaculation with their urologist.

    What Is HoLEP?

    HoLEP stands for holmium laser enucleation of the prostate.

    It uses a holmium laser to separate obstructing adenoma from the prostate capsule before the tissue is removed.

    EAU guidance supports HoLEP as an effective alternative to TURP or open prostate surgery in appropriate men.[1]

    Advantages can include:

    • Powerful relief of obstruction.
    • Use across a broad range of prostate sizes in experienced hands.
    • Durable long-term outcomes.

    Operator experience is particularly important because HoLEP has a meaningful technical learning curve.

    What About Thulium Laser Treatment?

    Thulium laser can be used for prostate vaporization or enucleation, depending on the technique.

    Current European evidence supports thulium enucleation as an effective alternative to TURP, bipolar enucleation, or HoLEP in appropriate settings.[1]

    Choice between holmium and thulium technology should therefore be based on patient anatomy, clinical circumstances, equipment, and surgeon expertise rather than assuming one laser is universally superior.

    What Is Prostatic Artery Embolization?

    Prostatic artery embolization (PAE) is an interventional radiology procedure that reduces blood flow to selected prostate arteries, leading to gradual shrinkage of prostate tissue.

    It can be considered by selected men interested in a less invasive option.

    However, evidence suggests that TURP generally provides greater improvements in urinary symptoms and flow, while PAE is associated with higher retreatment rates.[1]

    Current European guidance recommends that patient selection and follow-up occur through collaboration between urologists and appropriately trained interventional radiologists.

    How Does a Doctor Choose Between the Options?

    Patient priority Options that may be discussed Important tradeoff
    Symptoms are mild Watchful waiting and lifestyle measures Avoid unnecessary treatment while monitoring progression
    Relatively fast medication relief Alpha blocker in an appropriate patient Improves symptoms but does not substantially shrink the prostate
    Large prostate and higher progression risk Prostate-shrinking therapy ± combination treatment Slower symptom relief but reduced progression risk
    Preserving ejaculation is a major priority UroLift or selected minimally invasive options Potentially less de-obstruction or greater retreatment risk
    Strong and durable relief of obstruction TURP or laser enucleation depending on anatomy More invasive treatment with different recovery and ejaculatory effects
    Recurrent retention or complications Procedural treatment becomes a stronger consideration The goal is preventing ongoing harm as well as relieving symptoms

    What Is the Best BPH Treatment for Older Men?

    Age alone should not determine treatment.

    An active man in his seventies may be an excellent candidate for a procedure, while conservative management may be more suitable for a younger man with mild symptoms.

    In older adults, clinicians also consider:

    • Blood pressure and fall risk.
    • Cardiovascular medications and blood thinners.
    • Kidney function.
    • Polypharmacy and medication interactions.
    • Urinary retention and residual urine.
    • Recurrent infections or bladder stones.
    • Anaesthetic and procedural risk.
    • Functional independence and quality of life.

    How Do BPH Treatments Affect Ejaculation and Sexual Function?

    This should be discussed before choosing a treatment.

    Different medications and procedures carry different risks of ejaculatory and sexual side effects.

    UroLift and some minimally invasive treatments tend to preserve ejaculation better in appropriately selected men, while TURP and tissue-removing procedures have a greater likelihood of changing ejaculation.[1]

    That does not make ejaculation-preserving treatment universally superior; some men prioritize maximal relief of obstruction or durability instead.

    BPH Treatment at Mouwasat Hospital

    The Urology Department at Mouwasat Hospital evaluates and treats prostate and urinary tract conditions. Treatment availability varies by hospital, physician, and patient suitability.

    Published Mouwasat physician profiles demonstrate experience with several BPH treatment options.

    For example, a urology consultant at Mouwasat Hospital Dammam lists prostate treatment with holmium and thulium laser, TURP, UroLift, and Rezūm among the conditions and procedures treated.[3]

    A urology consultant at Mouwasat Hospital Riyadh also lists medical and surgical management of benign prostate disease using TURP or Rezūm.[4]

    Availability of a technique does not mean it is suitable for every patient or available at every Mouwasat location.

    Meet our doctors at Mouwasat Hospital

    Frequently Asked Questions About BPH Treatment

    What is the fastest treatment for an enlarged prostate?

    Some alpha-blocking medications can improve urinary symptoms relatively quickly, but faster symptom relief does not mean they shrink the prostate or prevent progression.

    Can BPH be treated without surgery?

    Yes. Many men can be managed with observation, lifestyle measures, medication, or minimally invasive procedures. Surgery becomes more important when symptoms remain severe or complications develop.

    Can herbs cure an enlarged prostate?

    Herbal products should not be treated as proven substitutes for established BPH therapies. Their composition and evidence vary, and they may interact with other medicines.

    Do BPH medications shrink the prostate?

    Not all of them. Alpha blockers primarily improve symptoms, while 5-alpha reductase inhibitors can gradually reduce prostate volume in appropriately selected men.

    Do you need to take BPH medication for life?

    It depends on the drug, response, risk of progression, prostate characteristics, and whether the patient later chooses a procedure.

    Which is better: Rezūm or UroLift?

    Neither is universally better. Prostate anatomy, size, middle-lobe anatomy, ejaculatory priorities, desired symptom relief, and tolerance for future retreatment all influence the choice.

    Which is better: laser treatment or TURP?

    Both can be highly effective. The best choice depends on prostate size, the specific laser technique, surgeon expertise, bleeding risk, comorbidities, and patient priorities.

    Is HoLEP suitable for a large prostate?

    HoLEP can be particularly effective in larger prostates when performed by an appropriately experienced surgeon.

    Can the prostate grow back after a procedure?

    The need for future treatment depends on the procedure and how much tissue was treated or removed. Some minimally invasive options have higher retreatment rates than more extensive tissue-removing procedures.

    Does BPH surgery cause erectile dysfunction?

    Different procedures have different sexual side-effect profiles. Changes in ejaculation are generally more common than new erectile dysfunction after several prostate procedures.

    Does UroLift preserve ejaculation?

    Preservation of ejaculatory function is one of the main advantages of UroLift in appropriately selected men.[1]

    Does Rezūm affect sexual function?

    Rezūm generally has a favorable sexual-function profile, but no procedure can guarantee that every patient will experience no sexual or ejaculatory changes.

    When does BPH require surgery?

    Surgery becomes a stronger consideration with recurrent retention, recurrent infection, bladder stones, persistent BPH-related bleeding, kidney or upper urinary tract effects from obstruction, or severe symptoms that remain inadequately controlled.

    Final Thoughts: Treat the Patient's Problem, Not the Name of the Procedure

    BPH treatment is not a contest between medication, Rezūm, UroLift, TURP, and laser surgery.

    Observation may be ideal for one man, medication for another, while a patient with recurrent retention or severe obstruction may benefit more from definitive tissue-removing treatment.

    Recovery time, durability, preservation of ejaculation, bleeding risk, and the strength of de-obstruction are all legitimate treatment priorities.

    The right treatment therefore begins with symptoms, prostate anatomy, bladder function, complications, overall health, and patient goals and only then moves to comparing the options that actually fit that individual case.

    Medical disclaimer: This article provides general health education and should not be used to select medication or a procedure without individualized medical assessment.

    Medical References

    1. European Association of Urology — Management of Non-neurogenic Male LUTS: Disease Management, 2026
    2. American Urological Association — Management of Lower Urinary Tract Symptoms Attributed to BPH
    3. Mouwasat Hospital Dammam — Urology Treatment Profile
    4. Mouwasat Hospital Riyadh — Urology Treatment Profile
  • 08/11/2026

    Prostate Cancer: Symptoms, Risk Factors, and How It Is Detected Early

    When men think about prostate cancer, the first question is often: “What symptoms should I look for?”

    But one fact matters even more: early prostate cancer may cause no noticeable symptoms at all. This means early detection should not depend on waiting for urinary problems or pain. At the same time, urinary symptoms do not automatically mean cancer, because benign prostate enlargement, prostatitis, and other conditions can cause similar complaints.[1][2]

    Modern prostate cancer assessment therefore considers individual risk, PSA when appropriate, clinical assessment, prostate MRI, and biopsy when clinically indicated rather than relying on one symptom or one blood-test result.[3][4]

    Key points:
    • Early prostate cancer may cause no symptoms.
    • Difficulty urinating or frequent urination does not automatically mean prostate cancer.
    • Risk increases with age, strong family history, and certain inherited genetic changes.
    • PSA helps estimate prostate cancer risk but cannot diagnose cancer by itself.
    • PSA can also rise with benign prostate enlargement or prostatitis.
    • Prostate MRI now plays an important role before biopsy in many men with suspected prostate cancer.
    • Biopsy usually provides the tissue diagnosis needed to confirm prostate cancer.
    • Not every prostate cancer requires immediate treatment; selected low-risk cancers may be managed with active surveillance.

    What Is Prostate Cancer?

    The prostate is a small gland in the male reproductive system located below the bladder and surrounding part of the urethra. It produces some of the fluid that makes up semen.

    Prostate cancer develops when cells within the prostate begin growing and dividing abnormally.

    Prostate cancers can behave very differently. Some grow so slowly that they may never cause a serious problem, while others are more aggressive and can spread beyond the prostate to lymph nodes, bones, or other organs.

    This is why the words “prostate cancer” alone do not determine treatment. The grade, stage, risk group, overall health, and individual preferences all matter.

    Can Prostate Cancer Develop Without Symptoms?

    Yes.

    Early localized prostate cancer usually does not cause noticeable symptoms, and some men are diagnosed while feeling completely well.[2]

    No symptoms does not necessarily mean no prostate cancer

    Men with relevant risk factors should not wait for pain or significant urinary difficulty before discussing whether prostate cancer screening is appropriate for them.

    What Are the Symptoms of Prostate Cancer?

    When prostate cancer does produce symptoms, they depend on the size, location, and extent of the disease.

    Possible urinary symptoms include:

    • Difficulty starting urination.
    • A weak or interrupted urinary stream.
    • Frequent urination, especially at night.
    • Difficulty completely emptying the bladder.
    • Urinary urgency.
    • Blood in the urine in some cases.[1][6]

    More advanced disease can cause symptoms such as:

    • Persistent pain in the back, hips, or pelvis.
    • Bone pain when cancer has spread to bone.
    • Other symptoms related to the location of metastatic disease.[6]
    Symptoms alone cannot diagnose prostate cancer

    Urinary symptoms are nonspecific and are often more suggestive of benign prostate enlargement than prostate cancer.[7]

    Does Difficulty Urinating Mean Prostate Cancer?

    No.

    A weak stream, hesitancy, nocturia, urgency, and incomplete bladder emptying can occur with several conditions, particularly benign prostatic hyperplasia (BPH).

    The National Cancer Institute notes that urinary obstruction symptoms are nonspecific and often more indicative of BPH than cancer.[7]

    See Benign Prostatic Hyperplasia: Symptoms and When an Enlarged Prostate Needs Assessment.

    Who Is at Higher Risk of Prostate Cancer?

    Increasing Age

    Prostate cancer risk rises with age, making age one of the strongest known risk factors.[2]

    Family History

    Having a father, brother, or son with prostate cancer can increase risk, particularly when several family members have been affected or diagnoses occurred at younger ages.[2]

    Inherited Genetic Changes

    Inherited changes involving genes such as BRCA1, BRCA2, or Lynch syndrome can increase prostate cancer risk in some families.[2]

    Risk is not diagnosis

    Risk factors help determine who may benefit from a more individualized discussion about early detection. They do not mean that prostate cancer is inevitable.

    Can an Enlarged Prostate Turn Into Prostate Cancer?

    No.

    Benign prostatic hyperplasia and prostate cancer are different conditions.

    BPH is not cancer and does not increase a person's risk of developing prostate cancer.[2]

    However, both conditions become more common with age and can coexist, which is why urinary symptoms sometimes require assessment rather than self-diagnosis.

    How Is Prostate Cancer Detected Early?

    Early detection means looking for clinically important prostate cancer before it causes advanced symptoms.

    There is no single test that provides the whole answer.

    The pathway may involve:

    1. Assessing age, family history, inherited risk, and general health.
    2. Discussing the potential benefits and harms of PSA-based screening.
    3. Clinical prostate assessment when appropriate.
    4. Repeating PSA or refining risk when an initial result is unclear.
    5. Prostate MRI when cancer remains a relevant concern.
    6. Targeted or appropriate biopsy when the combined risk justifies tissue sampling.[3][4]

    Book an appointment at Mouwasat Hospital

    What Is the Role of PSA?

    Prostate-specific antigen (PSA) is a protein produced by normal as well as malignant prostate cells.

    PSA testing may be used for:

    • Early-detection discussions in appropriate men.
    • Evaluation of selected prostate-related symptoms.
    • Monitoring prostate cancer after diagnosis and treatment.[8]

    Does a High PSA Mean Prostate Cancer?

    No.

    PSA may be elevated with:

    • Prostate cancer.
    • Benign prostatic hyperplasia.
    • Prostatitis or inflammation.
    • Other temporary factors that affect the prostate.[8]

    There is no single PSA threshold that perfectly separates men with and without prostate cancer.

    Read the dedicated guide: PSA Test: What Does the Result Mean and When Should Men Be Tested?.

    PSA is not a simple positive-or-negative cancer test

    Interpretation may consider age, previous PSA values, prostate size, risk factors, examination findings, MRI, and other tests.

    What Is the Role of Prostate MRI?

    Prostate MRI has become an important part of the modern diagnostic pathway for many men with suspected localized prostate cancer.

    Current European guidance strongly recommends performing MRI before prostate biopsy in men with suspected organ-confined disease.[4]

    MRI can:

    • Identify suspicious areas within the prostate.
    • Help estimate the likelihood of clinically significant cancer.
    • Guide targeted biopsy toward suspicious lesions.
    • Provide information about local disease extent.

    Radiologists commonly use the PI-RADS system to classify MRI findings.

    However, MRI is not an initial population-screening test, and a negative MRI does not exclude cancer in every patient. Clinical risk still matters.[4]

    When Is a Prostate Biopsy Needed?

    A prostate biopsy removes small tissue samples for examination under a microscope.

    It is usually required to confirm prostate cancer and assess its microscopic characteristics.

    Modern biopsy decisions consider more than PSA alone and may incorporate:

    • PSA level and previous results.
    • Family and genetic risk.
    • Clinical examination.
    • Prostate size and PSA density when relevant.
    • MRI findings and PI-RADS score.
    • Previous biopsy results.[3][4]

    What Do Gleason Score and Grade Group Mean?

    After cancer is identified on biopsy, the pathology report describes how abnormal the cancer cells look and how aggressively they are likely to behave.

    The traditional Gleason score is now commonly translated into Grade Groups 1 through 5.

    Grade Group General Meaning
    1 Generally the least aggressive group
    2–3 Intermediate features whose significance depends on other risk factors
    4–5 More aggressive microscopic features and generally higher risk

    Grade Group is interpreted together with PSA, stage, imaging, tumor volume, and other factors to determine the overall risk group.

    What Are the Stages of Prostate Cancer?

    A useful simplified framework is:

    Disease Extent Meaning
    Localized Cancer remains confined to the prostate.
    Locally advanced Cancer has extended beyond the prostate into nearby tissues.
    Metastatic Cancer has spread to distant lymph nodes, bones, or other organs.

    Formal staging uses the TNM system together with PSA, Grade Group, imaging, and other clinical information.

    Can Prostate Cancer Be Cured?

    Many prostate cancers can be treated very successfully, particularly when disease is localized and suitable for curative treatment.

    The outlook depends on:

    • Stage.
    • Grade Group.
    • PSA and overall risk group.
    • Whether cancer has spread.
    • Age and general health.
    • Response to treatment.

    For metastatic disease, treatment may focus on long-term disease control, delaying progression, relieving symptoms, and preserving quality of life.

    How Is Prostate Cancer Treated?

    Treatment is individualized, and some men do not require immediate treatment.

    Depending on stage and risk, options may include:[9]

    • Active surveillance for selected low-risk localized cancers.
    • Radical prostatectomy.
    • Radiation therapy.
    • Hormone therapy.
    • Chemotherapy, targeted therapies, and other systemic treatments in selected advanced disease.
    Not treating immediately can sometimes be the correct treatment strategy

    Active surveillance is a structured program for selected low-risk cancers. The cancer is monitored carefully, with treatment introduced if there is evidence that it is becoming more clinically significant.[9]

    Prostate Cancer Care at Mouwasat Hospital

    The Urology Department at Mouwasat Hospital evaluates and treats prostate disease, while the Oncology Department provides multidisciplinary care for localized, locally advanced, and metastatic prostate cancer.

    Treatment may include active surveillance, surgery, hormonal therapy, and systemic treatment depending on the individual disease profile.

    Selected urologic procedures at Mouwasat can also be performed using robotic surgery, including radical prostate surgery in appropriately selected patients.[10]

    Meet our doctors at Mouwasat Hospital

    When Should You See a Urologist?

    Medical assessment is appropriate if:

    • You develop new or persistent urinary symptoms.
    • You notice blood in the urine or semen.
    • You have a strong family history of prostate cancer and want to discuss early detection.
    • Your PSA is elevated and needs appropriate interpretation.
    • You have an abnormal prostate examination or MRI result.
    • You want to know whether prostate cancer screening is appropriate for your individual risk.
    Seek urgent assessment for new neurological symptoms with severe back pain

    In a person with known or suspected prostate cancer, severe back pain accompanied by leg weakness or numbness or new loss of bladder or bowel control requires urgent assessment for possible spinal cord compression.

    Frequently Asked Questions About Prostate Cancer

    What are the first symptoms of prostate cancer?

    There may be no early symptoms at all. Localized prostate cancer is often asymptomatic.[2]

    Does frequent urination at night mean prostate cancer?

    No. Nocturia has many causes and is commonly associated with benign prostate enlargement and other urinary conditions.

    Can a weak urine stream be caused by prostate cancer?

    It can occur with locally progressive disease, but it is nonspecific and is more commonly associated with benign prostate enlargement.[7]

    Does an enlarged prostate become cancer?

    No. BPH is a benign condition and is not a precancerous stage of prostate cancer.[2]

    Does prostatitis cause prostate cancer?

    A direct cause-and-effect relationship has not been established. Prostatitis can, however, raise PSA and complicate interpretation of the blood test.

    Does a high PSA mean cancer?

    No. PSA can rise because of cancer, BPH, prostatitis, and other factors.[8]

    Does a normal PSA completely rule out prostate cancer?

    No. There is no single PSA value that can exclude every prostate cancer.

    Does every elevated PSA require a biopsy?

    No. Repeat PSA, risk assessment, biomarkers, MRI, and other clinical information may be used before deciding whether biopsy is appropriate.[3][4]

    Can MRI replace prostate biopsy?

    Not in every patient. MRI helps identify and target suspicious lesions, but tissue sampling is still required in many men to confirm the diagnosis.[4]

    Is prostate cancer always slow growing?

    No. Some tumors grow very slowly, while others behave aggressively. Grade Group, stage, PSA, imaging, and other factors help distinguish risk.

    Can prostate cancer be treated without surgery?

    Yes. Depending on risk and stage, options can include active surveillance, radiation, hormone therapy, and other treatments.[9]

    When should men be screened for prostate cancer?

    There is no single age or schedule appropriate for every man. Screening decisions should account for age, family and genetic risk, general health, and individual preferences. These details are covered in our dedicated PSA and prostate screening guide.

    Final Thoughts: Do Not Wait for Symptoms to Think About Prostate Health

    Prostate cancer can be silent in its early stages, so the absence of pain or urinary symptoms does not automatically mean that early-detection discussions are unnecessary in men at relevant risk.

    At the same time, urinary symptoms do not automatically mean cancer. Benign prostate enlargement, prostatitis, and other conditions are common causes of similar complaints.

    Modern assessment combines individual risk with PSA when appropriate, clinical evaluation, prostate MRI, and biopsy when needed rather than relying on one symptom or one test result.

    Once prostate cancer is diagnosed, stage, Grade Group, overall risk, health, and personal preferences determine whether active surveillance, surgery, radiation, hormone therapy, or another treatment strategy is most appropriate.

    Medical disclaimer: This article provides general health education and does not replace individualized medical assessment or a discussion with your healthcare professional about the potential benefits and harms of prostate cancer screening.

    Medical References

    1. Saudi Ministry of Health — Prostate Cancer
    2. National Cancer Institute — Understanding Prostate Changes
    3. AUA/SUO — Updates to Early Detection of Prostate Cancer Guideline, 2026
    4. European Association of Urology — Prostate Cancer: Diagnostic Evaluation
    5. National Cancer Institute — Prostate Cancer Screening
    6. National Cancer Institute — Prostate Cancer Treatment: Patient Version
    7. National Cancer Institute — Prostate Cancer: Clinical Presentation
    8. National Cancer Institute — Prostate-Specific Antigen (PSA) Test
    9. National Cancer Institute — Prostate Cancer Treatment Options
    10. Mouwasat Hospital — Robotic Urologic Surgery
  • 08/11/2026

    PSA Test: How to Understand the Result and When Should Men Consider Prostate Screening?

    An elevated PSA result can be alarming, particularly because many people associate the test directly with prostate cancer.

    However, PSA is not a simple positive-or-negative cancer test. PSA is produced by normal as well as malignant prostate cells, and its level can also rise because of benign prostate enlargement, prostatitis, or temporary factors unrelated to cancer.[1]

    There is also no single PSA value that is “normal” for every man. Age, prostate size, previous PSA results, medications, risk factors, and clinical findings all affect interpretation.

    Key points:
    • PSA is a blood test used in prostate assessment, but it cannot diagnose prostate cancer by itself.
    • There is no single cutoff that reliably separates a normal from an abnormal result in every man.
    • BPH, prostatitis, and temporary factors can elevate PSA without cancer.
    • A newly elevated PSA is often confirmed with a repeat test before proceeding directly to MRI or biopsy.
    • Free PSA and PSA density can help refine risk in selected situations.
    • Prostate MRI is not a first-line screening test for everyone but can be valuable before biopsy when suspicion remains.
    • The decision to undergo PSA screening should consider age, individual risk, overall health, benefits, harms, and personal preferences.

    What Is a PSA Test?

    PSA stands for prostate-specific antigen.

    It is a protein produced by normal prostate cells as well as prostate cancer cells. A small amount enters the bloodstream and can be measured with a blood test.[1]

    PSA is generally reported in ng/mL.

    Because normal prostate tissue also produces PSA, an elevated result is not synonymous with cancer.

    Why Is PSA Measured?

    PSA can be used for several different purposes:

    • Discussing early detection of prostate cancer in appropriate men.
    • Evaluating selected prostate or urinary symptoms.
    • Assessing men with concerning prostate examination findings.
    • Monitoring men who have already been diagnosed with prostate cancer.
    • Following PSA after treatment to look for evidence of recurrence.[1]

    Is PSA a Prostate Cancer Test?

    Not in the sense of a positive-or-negative diagnostic test.

    PSA helps estimate risk, but it cannot confirm or exclude prostate cancer by itself.

    A man can have an elevated PSA without cancer, and prostate cancer can occasionally be present without a striking PSA elevation.

    PSA is a risk signal, not a diagnosis

    Interpretation considers age, previous PSA values, prostate size, risk factors, medications, examination findings, and sometimes MRI or additional biomarkers.[2]

    What Is a Normal PSA Level?

    There is no single PSA threshold that reliably separates men with and without prostate cancer.[1]

    A PSA level of 4 ng/mL has historically been used as a common threshold for further evaluation, but it should not be interpreted as an absolute boundary between normal and abnormal.

    Age, prostate volume, medications, previous PSA values, family history, and other risk factors influence interpretation.

    Finding General interpretation
    Lower PSA Generally associated with lower risk, but does not exclude every prostate cancer.
    Higher-than-expected PSA Requires interpretation because BPH, inflammation, cancer, and temporary factors can all contribute.
    Changing PSA over time May influence risk assessment but should not diagnose cancer on its own.

    What Can Raise PSA Besides Prostate Cancer?

    Possible causes include:

    • Benign prostatic hyperplasia (BPH).
    • Prostatitis.
    • Urinary or prostate inflammation.
    • Recent prostate biopsy or certain prostate procedures.
    • Recent ejaculation.
    • Vigorous exercise such as cycling in some men.[1]

    Read our guide to Prostate Cancer: Symptoms, Risk Factors, and Early Detection for more about how cancer differs from common benign prostate conditions.

    What Can Lower PSA?

    Some medications used to treat benign prostate enlargement can significantly lower PSA.

    These include 5-alpha-reductase inhibitors such as finasteride and dutasteride.[1][4]

    Your healthcare professional should therefore know which medications you use before interpreting the result.

    How Should You Prepare for a PSA Test?

    The PSA test itself requires only a blood sample.

    However, several temporary factors can affect the result.

    Before testing, tell your healthcare professional about:

    • Recent urinary or prostate infection.
    • Recent prostate biopsy or procedures.
    • Medicines used for BPH.
    • Other factors that could temporarily influence PSA.

    The National Cancer Institute notes that ejaculation and vigorous exercise such as cycling can transiently increase PSA and generally recommends avoiding activities known to raise PSA for approximately two days before testing when relevant.[1]

    When PSA is being repeated, European guidance recommends standardized conditions and, when possible, using the same laboratory and assay for comparison.[4]

    What Happens If PSA Is Elevated?

    An elevated result does not automatically mean cancer or immediate biopsy.

    AUA guidance recommends repeating a newly elevated PSA before proceeding to a secondary biomarker, imaging, or biopsy when appropriate.[2]

    European guidance similarly recommends confirming selected moderately elevated results because PSA can vary between measurements.[4]

    The pathway is not: elevated PSA → cancer → biopsy

    It may instead be: review temporary causes → repeat PSA when appropriate → assess overall risk → MRI or additional tests → biopsy when the probability of clinically significant cancer remains sufficient.

    Book an appointment at Mouwasat Hospital

    What Is the Difference Between Total PSA and Free PSA?

    PSA circulates in the blood in different forms.

    • Total PSA: the total amount of PSA measured in blood.
    • Free PSA: PSA circulating without being bound to certain proteins.

    The percentage of free PSA relative to total PSA can help refine cancer risk in selected men whose total PSA result is not definitive.

    In general, a lower percentage of free PSA can be associated with a higher probability of prostate cancer in certain clinical settings.

    However, there is no percentage that can independently confirm or exclude cancer, so the result should be interpreted as part of the broader risk assessment.

    What Is PSA Density?

    PSA density compares PSA with prostate volume.

    This can be helpful because a larger benign prostate may produce more PSA simply because there is more prostate tissue.

    PSA density is increasingly used alongside MRI, family history, and other clinical factors when estimating whether a biopsy is necessary.[4]

    When Should Men Consider PSA Screening?

    There is no single age at which every man should automatically start annual PSA testing.

    Prostate cancer screening is a preference-sensitive decision. The potential benefit of finding an important cancer early must be balanced against false-positive results, unnecessary investigations, and overdiagnosis.

    AUA guidance therefore emphasizes shared decision-making before screening.[2]

    Average Risk

    The AUA framework allows clinicians to offer a baseline PSA discussion at approximately 45–50 years of age for appropriate average-risk individuals.[2]

    Higher Risk

    Discussion can begin earlier, around 40–45 years, for selected men at increased risk, including those with a strong family history or certain inherited genetic variants.[2]

    The appropriate interval after that depends on the PSA level, risk profile, health, and individual preferences rather than automatically repeating the test every year.

    What Is the Role of a Digital Rectal Examination?

    During a digital rectal examination (DRE), a clinician feels part of the prostate through the rectum to assess features such as size, firmness, or a suspicious nodule.

    DRE does not diagnose cancer by itself and is not a replacement for PSA.

    It can, however, add information to the overall risk assessment in selected men.[2]

    Can You Examine Your Prostate Yourself?

    There is no reliable home prostate self-examination for prostate cancer screening.

    The prostate sits inside the pelvis, and even a clinician-performed DRE cannot confirm or exclude cancer on its own.

    Home self-examination is therefore not a substitute for appropriate PSA-based and clinical assessment.

    When Are Prostate MRI and Biopsy Needed?

    If concern remains after PSA and clinical risk assessment, the next step may include a prostate MRI.

    Current European guidance recommends MRI before prostate biopsy in men with suspected organ-confined prostate cancer.[4]

    MRI can help:

    • Identify suspicious prostate lesions.
    • Estimate the probability of clinically significant cancer.
    • Guide targeted biopsy.

    However, MRI is not recommended as an initial screening tool for everyone.[4]

    Some men with a negative MRI and low clinical suspicion may be monitored without immediate biopsy, while others still need tissue sampling because their overall risk remains meaningful.

    What Are the Benefits and Harms of PSA Screening?

    The potential benefit is earlier detection of clinically important prostate cancer, before it spreads and when curative treatment may be more feasible.

    Potential harms include:

    • False-positive PSA results.
    • Anxiety.
    • Additional imaging or biopsies that ultimately show no cancer.
    • Overdiagnosis of very slow-growing cancers that may never cause harm.
    • Overtreatment and avoidable urinary, sexual, or bowel side effects from treating cancers that may not have required immediate therapy.[1]

    This balance is why PSA screening should be an informed decision rather than an automatic test for every man.

    How Is PSA Used After Prostate Cancer Treatment?

    After prostate cancer treatment, PSA has a different purpose.

    It is used to monitor treatment response and look for evidence that cancer may have returned after surgery or radiation therapy.[1]

    Doctors usually assess the trend in PSA over time rather than interpreting one isolated measurement.

    PSA Testing at Mouwasat Hospital

    Prostate-specific antigen (PSA) is included among laboratory tests available through Mouwasat Hospital medical check-up services.[5]

    The Urology Department also evaluates prostate conditions and manages prostate cancer.

    For early detection, PSA testing is best considered within an informed discussion of age, individual risk, health status, and the potential benefits and harms of screening.

    Meet our doctors at Mouwasat Hospital

    Frequently Asked Questions About PSA

    Does a PSA above 4 mean prostate cancer?

    No. A value of 4 ng/mL has historically been used as a common threshold for additional assessment, but it cannot diagnose cancer and is not an absolute boundary.[1]

    What is a normal PSA level?

    There is no single normal value for every man. Interpretation depends on age, previous PSA results, prostate volume, medications, risk factors, and clinical findings.

    Should an elevated PSA be repeated?

    Often, yes. Guidelines recommend confirming a newly elevated result before moving directly to secondary biomarkers, imaging, or biopsy when clinically appropriate.[2]

    Can prostatitis raise PSA?

    Yes. Prostate inflammation can elevate PSA without cancer.[1]

    Can BPH raise PSA?

    Yes. Benign prostate enlargement is one of the common noncancerous causes of elevated PSA.

    What is the difference between total and free PSA?

    Total PSA measures all PSA in the blood, while free PSA measures the unbound portion. The free-to-total PSA relationship can help refine risk in selected situations but is not diagnostic by itself.

    Do you need to fast before a PSA test?

    PSA testing itself does not usually require fasting, although other blood tests performed at the same time may have different preparation requirements.

    Can ejaculation affect PSA?

    Yes. Ejaculation can temporarily raise PSA, which is why avoiding it for a short period before testing may be advised when accurate comparison is important.[1]

    Can cycling affect PSA?

    Vigorous cycling can transiently influence PSA in some men. Follow the preparation instructions given by your clinician or laboratory.[1]

    Can you check your prostate yourself?

    No reliable home self-examination can screen for prostate cancer.

    Does every elevated PSA require MRI?

    No. PSA may first be repeated, and overall risk may be assessed before MRI is considered.

    Does every elevated PSA require a biopsy?

    No. Modern evaluation combines PSA, clinical risk, MRI, and sometimes additional biomarkers to determine whether biopsy is appropriate.

    Final Thoughts: Think of PSA as a Risk Marker, Not a Final Verdict

    PSA is an important tool in prostate health, but an elevated result is not the same as a prostate cancer diagnosis.

    BPH, prostatitis, medications, and temporary factors can all change the result. A newly elevated PSA may therefore need confirmation before more invasive testing is considered.

    When concern persists, prostate MRI, PSA density, biomarkers, and other risk factors can help determine whether biopsy is appropriate.

    The decision to undergo PSA screening should likewise be individualized according to age, family history, inherited risk, general health, and personal preferences.

    Medical disclaimer: This article provides general health education and should not be used to interpret an individual PSA result or determine the need for MRI or biopsy without medical assessment.

    Medical References

    1. National Cancer Institute — Prostate-Specific Antigen (PSA) Test
    2. American Urological Association / Society of Urologic Oncology — Early Detection of Prostate Cancer Guideline
    3. AUA/SUO — Updates to Early Detection of Prostate Cancer Guideline, 2026
    4. European Association of Urology — Prostate Cancer: Diagnostic Evaluation
    5. Mouwasat Hospital — Medical Check-up
  • 08/11/2026

    Enlarged Prostate Symptoms: What Causes Them and When Should You Be Checked?

    A weak urinary stream, difficulty starting urination, and waking repeatedly at night to urinate often make men assume that they have an enlarged prostate.

    But the relationship is not that simple. Urinary symptoms do not automatically mean benign prostatic hyperplasia (BPH), and prostate size does not reliably predict how severe the symptoms will be. A relatively large prostate may cause few symptoms, while a smaller enlargement can significantly interfere with urination.[1][2]

    Modern assessment therefore starts by understanding the pattern of urinary symptoms and their impact on daily life, then looking for the underlying cause rather than treating prostate size alone.

    Key points:
    • BPH becomes increasingly common with age but is not prostate cancer.
    • A weak stream, nocturia, urgency, and incomplete emptying can occur with BPH but are not specific to it.
    • Prostate size does not always correlate with symptom severity.
    • Urinary obstruction, bladder function, and other conditions can matter as much as prostate size.
    • Assessment usually begins with history, symptom evaluation, examination, and urinalysis.
    • PSA may be useful when it will influence further evaluation or treatment decisions.
    • Complete inability to urinate requires urgent medical assessment.

    What Is Benign Prostatic Hyperplasia?

    The prostate is located below the bladder, with part of the urethra passing through it.

    As men age, prostate tissue commonly grows. This noncancerous enlargement is known as benign prostatic hyperplasia (BPH).

    The word “benign” is important: BPH is not prostate cancer and is not a precancerous stage.[3]

    It becomes clinically important when enlargement is associated with bothersome lower urinary tract symptoms or contributes to obstruction of urine leaving the bladder.

    Three concepts that are not identical

    Prostate enlargement: an anatomical increase in prostate size.

    LUTS: urinary symptoms such as urgency, nocturia, or weak flow.

    Bladder outlet obstruction: functional resistance to urine leaving the bladder.

    These conditions frequently overlap, but they are not interchangeable.[2]

    What Causes an Enlarged Prostate?

    The exact cause of BPH is not fully understood.

    It is strongly associated with aging, and age-related changes in hormone balance are thought to contribute to continued prostate growth.[1]

    Factors associated with a higher likelihood of BPH include:

    • Increasing age.
    • A family history of BPH.
    • Obesity.
    • Type 2 diabetes.
    • Certain cardiovascular conditions.[1][3]

    What Are the Symptoms of an Enlarged Prostate?

    It is useful to group lower urinary tract symptoms according to when they occur.

    Storage symptoms

    • Frequent urination.
    • Sudden urinary urgency.
    • Waking at night to urinate, known as nocturia.

    Voiding symptoms

    • Difficulty starting urination.
    • A weak urinary stream.
    • A stream that stops and starts.
    • Needing to strain to urinate.

    Post-void symptoms

    • Feeling that the bladder has not completely emptied.
    • Dribbling after urination.[1][3]
    Symptom type Examples
    Storage Frequency, urgency, nocturia
    Voiding Hesitancy, weak stream, intermittent flow, straining
    Post-void Incomplete emptying sensation, post-void dribbling

    Does Prostate Size Determine How Severe the Symptoms Are?

    No.

    A larger prostate does not necessarily produce worse symptoms. Some men with considerable enlargement have relatively mild urinary problems, while smaller increases in prostate size can significantly affect urination in others.[1]

    Symptoms are influenced by more than volume, including:

    • The shape and location of prostate growth.
    • How much resistance exists at the bladder outlet.
    • Bladder muscle function.
    • Overactive bladder.
    • Other urinary conditions.
    Treat the patient's problem, not just the prostate measurement

    Treatment decisions therefore consider symptom severity, quality of life, obstruction, bladder function, complications, anatomy, and patient preferences rather than prostate volume alone.

    Are All Urinary Symptoms in Men Caused by BPH?

    No.

    Lower urinary tract symptoms may result from BPH, but other causes include:

    • Urinary tract infection.
    • Prostatitis.
    • Overactive or underactive bladder.
    • Urethral stricture.
    • Urinary stones.
    • Neurological conditions.
    • Certain medications.
    • Bladder or prostate cancer in some cases.[1][2]

    A weak stream alone is therefore not enough to diagnose BPH.

    Does an Enlarged Prostate Mean Prostate Cancer?

    No.

    BPH and prostate cancer are different conditions, and benign prostate enlargement is not a precancerous stage.[3]

    They can, however, occur in the same age groups and may produce overlapping urinary complaints.

    Read Prostate Cancer: Symptoms, Risk Factors, and Early Detection for a detailed explanation.

    What Is the Difference Between BPH and Prostatitis?

    Prostatitis is inflammation of the prostate and is different from age-related benign enlargement.

    It can cause pelvic pain, painful urination, painful ejaculation, frequency, and urgency. Acute bacterial prostatitis can also cause fever and chills.[4]

    BPH more commonly produces age-related lower urinary tract symptoms without the typical inflammatory pain pattern.

    Who Is More Likely to Develop BPH?

    BPH becomes increasingly common as men age and is the most common prostate problem among men older than 50.[1]

    Family history, obesity, diabetes, cardiovascular disease, and physical inactivity may also be associated with increased likelihood.[1]

    How Is an Enlarged Prostate Evaluated?

    Modern assessment is not simply an ultrasound measurement of prostate size.

    Current EAU guidance approaches the problem as male lower urinary tract symptoms and aims to identify the mechanism responsible for those symptoms.[2]

    Medical history

    The clinician asks about symptom duration, severity, medications, medical conditions, infections, hematuria, and how much the problem affects daily life.

    Symptom assessment

    A validated questionnaire such as the International Prostate Symptom Score (IPSS) may be used.

    Physical examination

    This may include a digital rectal examination to assess prostate characteristics.

    DRE can estimate prostate volume, but the EAU notes that its correlation with actual prostate volume is limited.[2]

    Urinalysis

    Urinalysis is recommended in the initial assessment of male LUTS because it can identify conditions such as urinary infection, blood in the urine, or glucose in the urine that may require further evaluation.[2]

    Book an appointment at Mouwasat Hospital

    What Is the IPSS?

    The International Prostate Symptom Score is a validated questionnaire used to measure the frequency and impact of common lower urinary tract symptoms.

    It helps shift the focus from “How large is the prostate?” to:

    • How frequently are symptoms occurring?
    • How severe are they?
    • How much are they affecting sleep, activities, and quality of life?

    EAU guidance recommends validated symptom questionnaires when assessing men with LUTS.[2]

    What Is the Role of PSA in BPH Assessment?

    PSA may be measured when assessing prostate cancer risk would change management or when the result can help guide treatment decisions.[2]

    PSA also has some value in predicting prostate volume, future prostate growth, and the risk of progression to acute urinary retention or BPH-related surgery.

    For detailed PSA interpretation, see PSA Test: How to Understand the Result and When Men Should Consider Screening.

    What Are PVR and Uroflowmetry?

    Post-void residual

    PVR measures how much urine remains in the bladder after urination.

    A high residual volume does not automatically prove prostate obstruction. It can result from bladder outlet obstruction, weak bladder muscle contraction, or a combination of both.[2]

    Uroflowmetry

    Uroflowmetry measures the rate and pattern of urine flow.

    A low flow rate may suggest increased resistance, but it cannot independently distinguish obstruction from reduced bladder muscle strength.

    Does Every Man With BPH Symptoms Need an Ultrasound?

    Not necessarily in the same way.

    Ultrasound can assess prostate size, bladder characteristics, and residual urine, and it becomes particularly important when prostate size will influence medication or procedural treatment selection.[2]

    Upper urinary tract imaging may also be considered in selected men, including those with large residual volumes, hematuria, or a history of urinary stones.

    However, knowing prostate size alone does not explain every urinary symptom.

    What Are the Possible Complications of BPH?

    Most men do not develop every complication, but significant or persistent obstruction can contribute to:

    • Acute urinary retention.
    • Recurrent urinary tract infections.
    • Bladder stones.
    • Blood in the urine.
    • Bladder dysfunction.
    • Kidney or upper urinary tract problems in selected advanced cases.[1][3]

    When Do Enlarged-Prostate Symptoms Require Urgent Care?

    Seek prompt medical assessment if you:
    • Cannot urinate at all.
    • Have severe lower abdominal discomfort with inability to pass urine.
    • Notice visible blood in the urine.
    • Have painful, frequent, urgent urination with fever or chills.[3]

    Acute urinary retention is an urgent condition in which the bladder fills but urine cannot be passed normally.

    Can an Enlarged Prostate Be Treated?

    Yes. BPH symptoms can often be controlled effectively, but not every man requires the same treatment.

    Mild symptoms that are not significantly affecting quality of life may sometimes be monitored, while more troublesome symptoms or complications may justify medication or a procedure.

    Treatment selection considers:

    • Symptom severity and bother.
    • Prostate anatomy and size.
    • The degree of urinary obstruction.
    • Retention or other complications.
    • General health.
    • The patient's priorities regarding sexual function and ejaculation.

    Our next guide examines BPH treatment in detail, including medications, minimally invasive procedures, laser therapies, and surgery and how these options differ.

    Enlarged Prostate Care at Mouwasat Hospital

    The Urology Department at Mouwasat Hospital evaluates and treats prostate and urinary tract conditions.

    The appropriate pathway depends on the cause and severity of symptoms and the findings of clinical assessment rather than prostate size alone.

    Meet our doctors at Mouwasat Hospital

    Frequently Asked Questions About BPH

    How do I know whether I have an enlarged prostate?

    A weak stream, hesitancy, nocturia, and incomplete emptying can suggest BPH, but assessment is needed because the same symptoms can have other causes.

    Does frequent nighttime urination mean BPH?

    No. BPH is one possible cause, but nocturia can also be related to bladder conditions, sleep disorders, diabetes, medications, fluid intake, and other factors.

    Does a weak urine stream mean the prostate is large?

    No. A weak stream may reflect obstruction, but it can also result from weak bladder muscle contraction or urethral narrowing.

    Does a larger prostate cause worse symptoms?

    Not necessarily. Prostate size and symptom severity do not consistently correlate.[1]

    Can BPH turn into prostate cancer?

    No. BPH is not a precancerous condition.[3]

    Is BPH dangerous?

    It is usually not dangerous by itself, but significant obstruction can lead to urinary retention, infection, stones, or other complications in some men.

    Can BPH be cured permanently?

    BPH is an age-related condition, but its symptoms can often be controlled very effectively. The meaning of “permanent cure” differs depending on the treatment and the individual condition.

    Does every enlarged prostate need treatment?

    No. Treatment depends on symptom burden and complications rather than enlargement alone.

    Does PSA diagnose BPH?

    No. PSA can contribute useful information but cannot diagnose BPH or prostate cancer by itself.

    Is ultrasound enough to diagnose BPH?

    No. Ultrasound can provide useful anatomical information, but diagnosis also considers symptoms, physical examination, urinalysis, bladder emptying, and other tests when needed.

    When is urinary retention an emergency?

    Complete inability to urinate, particularly with bladder fullness or lower abdominal pain, requires urgent medical assessment.

    What is the difference between BPH and prostatitis?

    BPH is commonly associated with aging and urinary symptoms, while prostatitis may cause pelvic pain, painful urination or ejaculation, and sometimes fever or chills.

    Final Thoughts: Do Not Judge Prostate Problems by Size Alone

    Benign prostate enlargement is common with age, but a large prostate does not automatically mean severe symptoms, and urinary symptoms do not automatically prove BPH.

    Good assessment starts with the type and impact of the symptoms, then uses history, physical examination, urinalysis, and selected tests such as PSA, PVR, uroflowmetry, or imaging to determine the actual mechanism.

    This helps distinguish prostate enlargement from bladder dysfunction, prostatitis, urethral obstruction, and other causes and allows treatment to target the patient's actual problem rather than the prostate measurement alone.

    Medical disclaimer: This information is intended for general health education and does not replace medical assessment, particularly when urinary retention, visible blood, fever, severe pain, or rapidly worsening symptoms are present.

    Medical References

    1. National Institute of Diabetes and Digestive and Kidney Diseases — Enlarged Prostate (BPH)
    2. European Association of Urology — Management of Non-neurogenic Male LUTS: Diagnostic Evaluation, 2026
    3. Saudi Ministry of Health — Enlarged Prostate
    4. Saudi Ministry of Health — Prostatitis
  • 03/11/2026

    Hemorrhoid Symptoms: Bleeding, Pain, and When to Get Checked

    Bleeding after a bowel movement, itching, pain, or a lump around the anus can easily be assumed to mean hemorrhoids. However, the pattern of symptoms matters. Internal and external hemorrhoids behave differently, and other anorectal conditions—particularly anal fissures—can produce similar complaints.

    The most important rule is that rectal bleeding should not automatically be attributed to hemorrhoids. Hemorrhoids are common, but they are not the only possible cause of bleeding.[1]

    For an overview of types, grades, and causes, see Hemorrhoids: Types, Causes, Grades, and When to See a Doctor.

    Key points:
    • Painless bright-red bleeding with bowel movements is a classic symptom of internal hemorrhoids.
    • Internal hemorrhoids may prolapse and can cause irritation, mucus, or cleaning difficulties when they protrude.
    • External hemorrhoids may cause itching, discomfort, or a lump near the anus.
    • Sudden severe pain with a tender external lump is more typical of a thrombosed external hemorrhoid.
    • Sharp pain during a bowel movement that continues afterward can suggest an anal fissure.
    • Heavy or ongoing bleeding with dizziness or faintness requires urgent assessment.

    What Are the Most Common Hemorrhoid Symptoms?

    Symptoms differ considerably depending on the type of hemorrhoid.

    They may include:

    • Bright-red rectal bleeding during or after a bowel movement.

    • Prolapse of tissue through the anal opening.
    • A lump or swelling around the anus.
    • Anal itching or irritation.
    • Pain, pressure, or discomfort in selected cases.
    • Difficulty keeping the area clean when prolapse is present.[2]
    You do not need to have every symptom

    Bleeding may be the only symptom of an internal hemorrhoid, whereas an external hemorrhoid may mainly cause a lump, itching, or pain. The pattern provides useful clues but does not replace examination when the diagnosis is uncertain.

    What Are the Symptoms of Internal Hemorrhoids?

    Internal hemorrhoids are located in a part of the anal canal that has relatively little pain sensation. Therefore, non-prolapsed internal hemorrhoids are usually not painful.[3]

    Typical features include:

    • Painless bright-red bleeding during or after bowel movements.
    • Blood on toilet paper, on the surface of stool, or dripping into the toilet.
    • Tissue protruding through the anal opening during bowel movements.
    • Prolapsed tissue that returns inside by itself or may need manual reduction.
    • Itching or irritation when prolapse occurs.
    • Mucus discharge or difficulty cleaning after a bowel movement in some patients.[2]

    Are Internal Hemorrhoids Painful?

    Pain is not the classic feature of uncomplicated internal hemorrhoids.

    Discomfort or significant pain may occur with marked prolapse or when prolapsed tissue becomes trapped.[2]

    Severe pain with bowel movements?

    Sharp pain that begins during defecation and continues afterward is more characteristic of an anal fissure than uncomplicated internal hemorrhoids. Because both can bleed, examination may be needed to distinguish them.

    What Are the Symptoms of External Hemorrhoids?

    External hemorrhoids develop beneath sensitive skin around the anus.

    Symptoms may include:[3]

    • Anal itching or irritation.
    • One or more lumps near the anus.
    • Aching or discomfort.
    • Pain that may be more noticeable while sitting.
    • Swelling around the anus.

    An external lump is not always an active hemorrhoid. A painless skin tag can remain after a previous thrombosed external hemorrhoid.[2]

    Read more in External Hemorrhoids: What Does a Painful Lump Mean and When Should It Be Checked?.

    What Does a Thrombosed External Hemorrhoid Feel Like?

    A blood clot can form inside an external hemorrhoid, producing a thrombosed external hemorrhoid.

    Typical features include:

    • Sudden and sometimes severe pain.
    • A hard, very tender lump near the anus.
    • Swelling and inflammation.
    • A bluish or darker-colored lump.
    • Discomfort when sitting or moving.[2][4]
    Pain can help distinguish the pattern

    Painless bright-red bleeding is more typical of internal hemorrhoids, while sudden severe pain with a tender external lump is more characteristic of external hemorrhoidal thrombosis.

    What Does Hemorrhoid Bleeding Look Like?

    Bleeding from internal hemorrhoids is usually bright red.[2][3]

    You may notice it:

    • On toilet paper.
    • Streaked on the outside of stool.
    • As drops of blood in the toilet.

    Is Hemorrhoid Bleeding Painful?

    Bleeding from internal hemorrhoids is often painless.

    When bright-red bleeding is accompanied by sharp pain during and after a bowel movement, an anal fissure becomes another important possibility.

    Can Hemorrhoids Bleed a Lot?

    Internal hemorrhoids can sometimes produce noticeable bleeding, but the amount of blood alone cannot confirm that hemorrhoids are the source.[2]

    Rectal bleeding should not automatically be called hemorrhoids

    Colorectal guidelines specifically caution against automatically attributing rectal bleeding to hemorrhoids because other colorectal conditions can produce the same symptom.[1]

    Book an appointment at Mouwasat Hospital

    Do Hemorrhoids Cause Severe Pain?

    They can, but severe pain is not typical of every type of hemorrhoid.

    Pain Pattern What It May Suggest
    Bleeding with little or no pain Typical of internal hemorrhoids
    Sudden constant pain with a tender lump May indicate a thrombosed external hemorrhoid
    Sharp pain during a bowel movement continuing afterward More typical of an anal fissure
    Severe worsening pain with systemic illness Requires assessment for another anorectal problem

    Can Hemorrhoids Cause Anal Itching?

    Yes. Itching and irritation can occur with external hemorrhoids and prolapsing internal hemorrhoids.[2][3]

    Possible contributors include difficulty cleaning the area, mucus or stool contacting the surrounding skin, and excessive rubbing or cleaning.

    However, itching alone does not diagnose hemorrhoids because skin disorders, infections, and other conditions can also cause anal itching.

    Are Hemorrhoid Symptoms Different in Women?

    The core symptoms are not fundamentally different in women and men.

    Women can experience bleeding, prolapse, itching, pain, or external swelling in the same way.

    The important difference is context: pregnancy is a recognized risk factor for hemorrhoids because pelvic pressure and bowel-habit changes can increase during pregnancy.[3]

    Pregnancy does not create a separate set of hemorrhoid symptoms

    Bleeding or unusual pain during pregnancy should still be discussed with a healthcare professional rather than automatically assumed to be hemorrhoids.

    Hemorrhoids or Anal Fissure: What Is the Difference?

    An anal fissure is a small tear in the skin lining the anal opening.

    Its characteristic symptom is severe pain during a bowel movement, often continuing for minutes or hours afterward, frequently with some bleeding.[5]

    Feature Internal Hemorrhoids Anal Fissure
    Bleeding Often bright red Bright-red bleeding can also occur
    Pain Often minimal or absent unless significantly prolapsed Often severe during and after bowel movements
    Prolapse or lump Prolapse may occur Not the primary feature

    These differences can guide understanding but should not be used as a substitute for examination.

    When Might the Symptoms Not Be Hemorrhoids?

    Hemorrhoids are common, but other conditions can cause similar symptoms.

    Possibilities include:

    • Anal fissure.
    • Anal abscess or fistula.
    • Proctitis or inflammatory bowel disease.
    • Rectal prolapse.
    • Other anal or colorectal disease, including malignancy.[1][3]

    Do Changes in Bowel Habits Matter?

    Yes.

    If rectal bleeding is accompanied by a new persistent change in bowel habits or unusual changes in stool color or consistency, medical assessment is important rather than simply assuming hemorrhoids are responsible.[4]

    Do Hemorrhoids Cause Colorectal Cancer?

    No. Hemorrhoids do not cause colorectal cancer.

    The concern is that colorectal disease can produce similar symptoms, particularly rectal bleeding.[2]

    When Do Hemorrhoid-Like Symptoms Need Urgent Assessment?

    Seek urgent medical attention if:
    • Rectal bleeding is heavy or continuous.
    • Bleeding is accompanied by dizziness, lightheadedness, marked weakness, or fainting.
    • You experience an unusual episode of significant rectal bleeding without a confirmed source.
    • Bleeding occurs with significant new changes in bowel habits that require assessment.[4]

    Repeated rectal bleeding also deserves medical assessment even when the amount seems small.[3]

    What Happens After Hemorrhoids Are Confirmed?

    The next step depends on hemorrhoid type, degree of prolapse, symptom severity, and impact on daily life.

    Some patients only need conservative measures, while others may eventually require an office procedure or surgery.

    For the full decision pathway, see Hemorrhoid Treatment: When Is Conservative Care Enough and When Is a Procedure Needed?.

    The General Surgery Department at Mouwasat Hospital provides care for anorectal conditions including hemorrhoids, anal fissures, and anal fistulas.

    Meet our doctors at Mouwasat Hospital

    Frequently Asked Questions About Hemorrhoid Symptoms

    What are the first signs of hemorrhoids?

    There is no universal first sign. Internal hemorrhoids may first appear as painless bright-red bleeding, while external hemorrhoids may present with itching, discomfort, or a lump.

    What color is hemorrhoid blood?

    Bleeding from internal hemorrhoids is typically bright red and may appear on toilet paper, on the surface of stool, or in the toilet.[2]

    Does bleeding mean the hemorrhoid is healing?

    No. Bleeding is not a sign that hemorrhoids are draining or healing. Recurrent bleeding should be assessed rather than interpreted as part of recovery.

    Can hemorrhoids cause buttock or anal pain?

    External hemorrhoids can cause pain or discomfort, particularly when thrombosed. Non-prolapsed internal hemorrhoids usually cause little or no pain.

    Can hemorrhoids cause itching?

    Yes. Itching can occur with external hemorrhoids or prolapsing internal hemorrhoids.

    How do I know whether an external lump is a hemorrhoid?

    An external hemorrhoid may produce a lump near the anus, particularly when thrombosed. However, not every anal lump is a hemorrhoid, so uncertain or persistent lumps should be examined.

    Are internal and external hemorrhoid symptoms different?

    Yes. Internal hemorrhoids are more strongly associated with bleeding and prolapse, whereas external hemorrhoids are more likely to cause a lump, itching, swelling, or pain.

    How does fissure pain differ from hemorrhoid pain?

    Anal fissures typically produce severe pain during bowel movements that continues afterward. A thrombosed external hemorrhoid is more likely to cause constant severe pain with a tender lump.[5]

    Are hemorrhoid symptoms different in women?

    The symptoms themselves are similar. Pregnancy, however, increases the likelihood of developing hemorrhoids in some women.

    Should minor rectal bleeding be checked?

    Rectal bleeding—particularly when recurrent or of uncertain origin—should be medically assessed rather than automatically diagnosed as hemorrhoids.[3]

    When is rectal bleeding an emergency?

    Heavy or continuous bleeding, especially when accompanied by dizziness, weakness, lightheadedness, or fainting, requires urgent medical care.[4]

    Final Thoughts: The Pattern of Symptoms Matters

    Hemorrhoid symptoms do not look the same in every patient.

    Painless bright-red bleeding is more characteristic of internal hemorrhoids. Sudden severe pain with an external tender lump raises the possibility of a thrombosed external hemorrhoid. Severe pain during and after defecation may point toward an anal fissure.

    These patterns are useful for understanding symptoms, but they do not replace diagnosis.

    Most importantly, having known hemorrhoids should not become a reason to ignore new or persistent rectal bleeding. Hemorrhoids can be present while another condition is also responsible for the symptom.

    Medical disclaimer: This article is intended for general health education and does not replace medical assessment for rectal bleeding, severe pain, or new or persistent symptoms.

    Medical References

    1. American Society of Colon and Rectal Surgeons — Clinical Practice Guidelines for the Management of Hemorrhoids, 2024
    2. American Society of Colon and Rectal Surgeons — Hemorrhoids: Expanded Information
    3. National Institute of Diabetes and Digestive and Kidney Diseases — Symptoms & Causes of Hemorrhoids
    4. Mayo Clinic — Hemorrhoids: Symptoms and Causes
    5. American Society of Colon and Rectal Surgeons — Anal Fissure: Expanded Information
  • 03/11/2026

    Hemorrhoid Treatment: When Is Conservative Care Enough and When Is a Procedure Needed?

    A search for hemorrhoid treatment quickly produces creams, suppositories, home remedies, banding, laser procedures, and surgery.

    But the right question is not simply “What is the strongest treatment?” It is: What type of hemorrhoids are present, what symptoms are they causing, and how much prolapse is there?

    Many patients start with dietary and bowel-habit measures. Some internal hemorrhoids that remain symptomatic can be treated with an office procedure, while a smaller group requires surgery.[1]

    If you are unsure about the type or grade, start with Hemorrhoids: Types, Causes and Grades. For bleeding and pain patterns, see Hemorrhoid Symptoms: Bleeding, Pain and When to Get Checked.

    Key points:
    • Dietary and bowel-habit modification is first-line treatment for symptomatic hemorrhoids.
    • Fiber is particularly useful for reducing bleeding and persistent symptoms.
    • Creams and suppositories may provide temporary symptom relief but do not correct every type of hemorrhoidal disease.
    • Grade I and II internal hemorrhoids and selected grade III disease may respond to office treatment when conservative care is insufficient.

    • Rubber band ligation is considered the most effective office-based procedure under current ASCRS guidance.
    • Surgery is more commonly considered for symptomatic external disease, advanced combined disease, or failure of less invasive treatment.

    • Laser is not automatically the best option; treatment choice involves balancing pain, recovery, durability, and the type of hemorrhoidal disease.

    How Is Hemorrhoid Treatment Chosen?

    Treatment depends on more than the word “hemorrhoids.”

    Important factors include:

    • Internal, external, or combined disease.
    • The degree of internal hemorrhoid prolapse.
    • Whether bleeding, prolapse, or pain is the main problem.
    • Duration and frequency of symptoms.
    • Response to previous conservative treatment.
    • General health and medications.
    • Patient preferences about recovery and recurrence risk.
    Situation Treatment Path Often Considered
    Mild symptoms without major prolapse Dietary and bowel-habit measures with symptom relief when required
    Persistent grade I or II internal hemorrhoids An office procedure may be considered after inadequate conservative treatment
    Selected grade III disease Office procedure or surgery depending on anatomy and response
    Significant external or advanced combined disease Surgical assessment and more advanced treatment options

    When Is Conservative or Home Treatment Enough?

    Dietary and behavioral changes are the primary first-line treatment for symptomatic hemorrhoidal disease.[1]

    Important measures include:

    • Increasing dietary fiber gradually.
    • Maintaining appropriate fluid intake.
    • Avoiding straining.
    • Responding appropriately to the urge to defecate.
    • Limiting prolonged toilet sitting.
    • Addressing constipation or other bowel-habit problems.

    Warm sitz baths may also provide relief from discomfort in some patients.[2]

    Conservative treatment is real treatment

    Improving stool consistency and reducing repeated straining addresses important contributors to hemorrhoidal symptoms. These measures remain useful even when an office procedure or surgery is eventually required.

    Why Is Fiber Important?

    Fiber improves stool consistency and helps reduce straining.

    Randomized evidence reviewed by ASCRS found that fiber significantly reduced persistent hemorrhoidal symptoms and bleeding, although its effect on prolapse, pain, and itching was more limited.[1]

    Fiber may come from food, and selected patients may discuss a fiber supplement with a healthcare professional.

    Fiber cannot correct every prolapse

    Bowel-habit improvement may reduce bleeding and irritation, but a persistent prolapsing internal hemorrhoid can still require an office procedure or surgery.

    Do Hemorrhoid Creams and Suppositories Work?

    Topical creams, ointments, foams, and suppositories can provide symptomatic relief for itching, mild pain, swelling, or irritation in selected patients.[1][2]

    However:

    • They do not treat every form of hemorrhoidal disease.
    • Symptom improvement does not mean that significant prolapse has disappeared.
    • Evidence supporting many individual topical products is limited.
    • Prolonged use of some topical agents is not supported by good long-term evidence and may cause local sensitivity.[1]

    Are Suppositories Better Than Creams?

    Not necessarily.

    The appropriate form depends on the location and nature of the symptoms and on the ingredients of the product. “Hemorrhoid suppositories” are not one standardized treatment.

    Do not spend months searching for a stronger cream

    Persistent bleeding, prolapse, or a severely painful external lump may require a different treatment pathway rather than repeated changes in topical medication.

    When Are Office Procedures Used?

    Many internal hemorrhoids can be treated without excisional surgery when conservative measures are no longer sufficient.

    Current ASCRS guidance states that most symptomatic grade I and II and selected grade III internal hemorrhoids refractory to conservative treatment can be effectively treated with office-based procedures.[1]

    Options include:

    • Rubber band ligation.
    • Injection sclerotherapy.
    • Infrared coagulation.

    These treatments are directed at internal hemorrhoids and are not interchangeable with treatment of external hemorrhoids.

    Book an appointment at Mouwasat Hospital

    What Is Rubber Band Ligation?

    Rubber band ligation places a small elastic band around the base of an appropriate internal hemorrhoidal column above the highly pain-sensitive area of the anal canal.

    The band interrupts blood supply, allowing the tissue to shrink and eventually separate while scar formation helps fix the remaining tissue in place.[1][3]

    ASCRS considers rubber band ligation the most effective office-based treatment for appropriate hemorrhoids.[1]

    Does Banding Hurt?

    Pressure, discomfort, or pain can occur after treatment, and mild bleeding may occur.

    Serious bleeding and infection are uncommon but important complications that require prompt assessment.[1]

    Is One Session Always Enough?

    No. Some patients require additional sessions depending on the extent of hemorrhoidal disease or recurrence.[3]

    What Other Office Treatments Are Available?

    Injection Sclerotherapy

    A sclerosing substance is injected into the hemorrhoidal tissue to produce fibrosis, shrinkage, and fixation.

    It is an option for selected internal hemorrhoids and may be useful when another office approach is less suitable.[1]

    Infrared Coagulation

    Infrared energy creates controlled coagulation that causes appropriate internal hemorrhoidal tissue to shrink.

    The choice between different office procedures depends on treatment response, discomfort, recurrence, and individual clinical factors.

    When Do Hemorrhoids Need Surgery?

    Surgery is not required for most patients.

    However, excisional hemorrhoidectomy is typically considered for selected patients with:[1]

    • Symptomatic external hemorrhoids.
    • Advanced combined internal and external disease.
    • Selected grade III or IV internal hemorrhoids.
    • Persistent or recurrent symptoms despite appropriate conservative and office treatment.

    Excisional surgery is highly effective but generally involves more postoperative pain and a longer recovery than less invasive options.

    For a detailed comparison of surgery and recovery, see Hemorrhoid Surgery: Options, Recovery, and When Surgery Is Recommended.

    Is Laser Treatment Better for Hemorrhoids?

    Not automatically.

    “Laser hemorrhoid treatment” can refer to different techniques, and outcomes depend on the procedure, hemorrhoid anatomy, grade, and surgeon experience.

    Laser hemorrhoidoplasty has been associated with less postoperative pain and faster recovery than conventional excisional hemorrhoidectomy in selected patients, but durability and recurrence must also be considered.[4]

    A randomized trial with five-year follow-up published in 2026 reported estimated symptom recurrence of 24% after excisional hemorrhoidectomy and 29% after laser hemorrhoidoplasty; the difference was not statistically significant in the relatively small study, while recovery following laser treatment was shorter and less painful.[4]

    Laser or conventional surgery?

    The decision is a tradeoff rather than a contest between two labels. Some patients prioritize lower postoperative pain and faster recovery; others have disease for which a more definitive excisional approach is better suited.

    Major ASCRS guidance still organizes treatment primarily around hemorrhoid type, grade, conservative treatment, office procedures, and appropriate surgery rather than recommending laser as the default treatment for all patients.[1]

    How Is External Hemorrhoid Treatment Different?

    External hemorrhoids are not managed in exactly the same way as internal disease.

    Rubber band ligation, for example, is designed for internal hemorrhoids and is not an external hemorrhoid treatment.

    Many external symptoms can be managed conservatively, while selected patients with a severely painful thrombosed external hemorrhoid may benefit from early excision.[1]

    See External Hemorrhoids: What Does a Painful Lump Mean? for the full pathway.

    Can Hemorrhoids Come Back After Treatment?

    Yes.

    No treatment guarantees that hemorrhoidal symptoms will never recur.

    Recurrence depends on factors including:

    • Hemorrhoid type and grade.
    • The procedure performed.
    • Ongoing constipation and straining.
    • Bowel habits.
    • Individual anatomy and other clinical factors.

    Healthy bowel habits therefore remain relevant even after successful office treatment or surgery.

    Can Hemorrhoids Be Cured Permanently?

    Symptomatic hemorrhoids can often be treated very successfully, and symptoms may remain absent long term.

    However, promising that any treatment will eliminate the possibility of future hemorrhoidal disease is not medically accurate.

    When Should You Stop Self-Treatment and See a Doctor?

    Medical assessment is appropriate when:

    • Rectal bleeding is recurrent or unexplained.
    • Symptoms continue despite appropriate conservative measures.
    • There is significant prolapse.
    • A severely painful external lump develops.
    • Symptoms repeatedly return.
    • You are not certain the condition is actually hemorrhoidal disease.
    Do not keep treating unexplained bleeding indefinitely

    Current colorectal guidance emphasizes that rectal bleeding should not automatically be attributed to hemorrhoids, and persistent bleeding after treatment requires further evaluation.[1]

    The General Surgery Department at Mouwasat Hospital provides assessment and treatment for anorectal conditions including hemorrhoids, anal fissures, and fistulas.

    Meet our doctors at Mouwasat Hospital

    Frequently Asked Questions About Hemorrhoid Treatment

    What is the best treatment for hemorrhoids?

    The best treatment depends on hemorrhoid type, prolapse grade, and symptoms. Most patients start with conservative care; selected patients need an office procedure or surgery.

    Can hemorrhoids be treated at home?

    Many mild cases improve with fiber, appropriate fluids, improved bowel habits, and avoidance of straining.[1][2]

    What is the best hemorrhoid cream?

    There is no single best cream for every patient. Topical products can relieve selected symptoms but do not correct every form of hemorrhoidal disease.

    Do suppositories cure hemorrhoids?

    They may relieve selected symptoms depending on their ingredients and the location of the problem, but they are not a substitute for assessment of persistent bleeding or prolapse.

    Do sitz baths help hemorrhoids?

    Warm sitz baths may help relieve discomfort but do not correct significant prolapse or advanced disease.[2]

    When is rubber band ligation used?

    It is commonly considered for symptomatic internal hemorrhoids, particularly grade I or II and selected grade III disease that remains symptomatic after conservative treatment.[1]

    Is banding better than surgery?

    They serve different patients. Banding is less invasive and effective for suitable internal hemorrhoids, while surgery is more appropriate for selected external, combined, or advanced disease.

    Is laser better than hemorrhoidectomy?

    Laser hemorrhoidoplasty can offer less pain and faster recovery in selected patients, but treatment durability and anatomy also matter. It is not automatically the best option for every case.[4]

    Can hemorrhoids go away without surgery?

    Yes. Most patients do not require surgery, and many improve with conservative measures or office-based treatment.

    Can hemorrhoids recur after surgery?

    Yes. Recurrence is possible after all treatment approaches, although rates vary between procedures and patient groups.

    Final Thoughts: Hemorrhoid Treatment Is a Pathway, Not One Product

    The best hemorrhoid treatment is the one that matches the type of disease, prolapse grade, and symptom being treated.

    Most treatment pathways begin with stool consistency and healthier bowel habits. Creams and suppositories may relieve symptoms, but they are not a solution to every hemorrhoid.

    If symptomatic internal disease persists, office procedures such as rubber band ligation can provide effective treatment without immediately moving to excisional surgery.

    More advanced external or combined disease may require a different approach.

    Most importantly, treatment should not be selected simply because an advertisement says “laser” or “without surgery.” The meaningful comparison is between the expected effectiveness, recovery, risks, recurrence, and suitability of each option for the actual condition.

    Medical disclaimer: This article provides general health education and does not replace individualized assessment before selecting medication, an office procedure, or surgery.

    Medical References

    1. American Society of Colon and Rectal Surgeons — Clinical Practice Guidelines for the Management of Hemorrhoids
    2. National Institute of Diabetes and Digestive and Kidney Diseases — Treatment of Hemorrhoids
    3. American Society of Colon and Rectal Surgeons — Hemorrhoids
    4. Diseases of the Colon & Rectum — Five-Year Follow-up Comparing Laser Hemorrhoidoplasty, Excisional Hemorrhoidectomy and Sutured Mucopexy, 2026

Doctors related to Prostatitis: Symptoms, Types, Treatment and When Is It Serious?

Book your appointment now with best doctors

Mouwasat Medical Dammam Dispensary in '75, evolved into LLC managing multiple facilities in '97 under same registration.

Contact Information

Unified Number:
site.QUOTES_IMAGE_ALT
+966 920 004 477