One of the most common questions after a breast cancer diagnosis is: What are my chances of recovery?
There is no single percentage that applies to everyone. Outlook varies substantially according to how far the cancer has spread at diagnosis, tumour subtype, ER and PR status, HER2 status, tumour grade, response to treatment and individual health factors.
Medical statistics also usually measure survival rather than “cure” directly.
A 5-year survival rate does not mean someone is expected to live only five years. It is a population statistic used to understand outcomes among large groups and cannot predict exactly what will happen to an individual.
Not exactly.
Most cancer registries use statistical measures such as:
This is why statements such as “breast cancer has a 90% cure rate” can be misleading unless the statistic, population and period are clearly defined.
No.
Five years is simply a standard reference point used in research. Many breast cancer survivors live for decades after diagnosis.
According to the Saudi Health Council's national Cancer Survival Report, age-standardised 5-year net survival among women with breast cancer was approximately 82.1% for patients diagnosed during 2015–2019. [1]
This figure should not be interpreted as an individual's chance of cure.
It describes a historical population and uses a different survival measure from the relative survival statistics commonly reported by US SEER databases.
Survival figures can differ because of the population studied, years of diagnosis, cancer stage distribution, tumour subtypes, access to treatment and the statistical method used.
How far the cancer has spread at diagnosis is one of the strongest factors affecting prognosis.
The American Cancer Society reports the following 5-year relative survival rates for women diagnosed with invasive breast cancer in the United States between 2015 and 2021. [2]
| SEER stage | Meaning | 5-year relative survival |
|---|---|---|
| Localized | Cancer has not spread outside the breast. | >99% |
| Regional | Cancer has spread to nearby structures or regional lymph nodes. | 87% |
| Distant | Cancer has spread to distant parts of the body. | 32% |
| All stages combined | All eligible cases combined. | 92% |
The localized figure applies to invasive breast cancer and does not include ductal carcinoma in situ (DCIS). [2]

Not exactly.
SEER survival statistics use a simplified system of localized, regional and distant disease, whereas clinical breast cancer staging uses the AJCC system with stages 0 through IV.
The systems overlap conceptually but are not interchangeable.
Modern prognostic breast cancer staging also incorporates information such as tumour grade and ER, PR and HER2 status in addition to TNM information. [3]
Tumour biology also matters.
The National Cancer Institute reports the following 5-year relative survival rates from SEER data for women diagnosed during 2013–2019. [4]
| Subtype | Overall | Localized | Regional | Distant |
|---|---|---|---|---|
| HR+/HER2- | 94.8% | 100.0% | 90.2% | 34.0% |
| HR+/HER2+ | 91.0% | 99.1% | 89.8% | 45.6% |
| HR-/HER2+ | 85.6% | 97.2% | 84.0% | 39.5% |
| Triple-negative | 77.6% | 91.8% | 66.2% | 12.8% |
These statistics describe populations, not individual outcomes, and newer treatments may not yet be fully reflected in historical survival datasets. [4]
Hormone receptor-positive breast cancer contains estrogen and/or progesterone receptors and can often be treated with endocrine therapy. [5]
In NCI data, overall 5-year relative survival was:
However, the extent of disease at diagnosis remains extremely important. Hormone receptor-positive metastatic cancer has a very different prognosis from localized hormone receptor-positive cancer.
Hormone receptor-positive cancers often have a favourable short-term outlook, but they can recur many years after initial treatment. [5]
Not necessarily.
HER2-positive tumours can grow more quickly, but modern HER2-targeted therapies have substantially changed the treatment landscape.
NCI data show overall 5-year relative survival of 91.0% for HR+/HER2+ disease and 85.6% for HR-/HER2+ disease, with large differences according to whether the cancer is localized, regional or metastatic. [4]
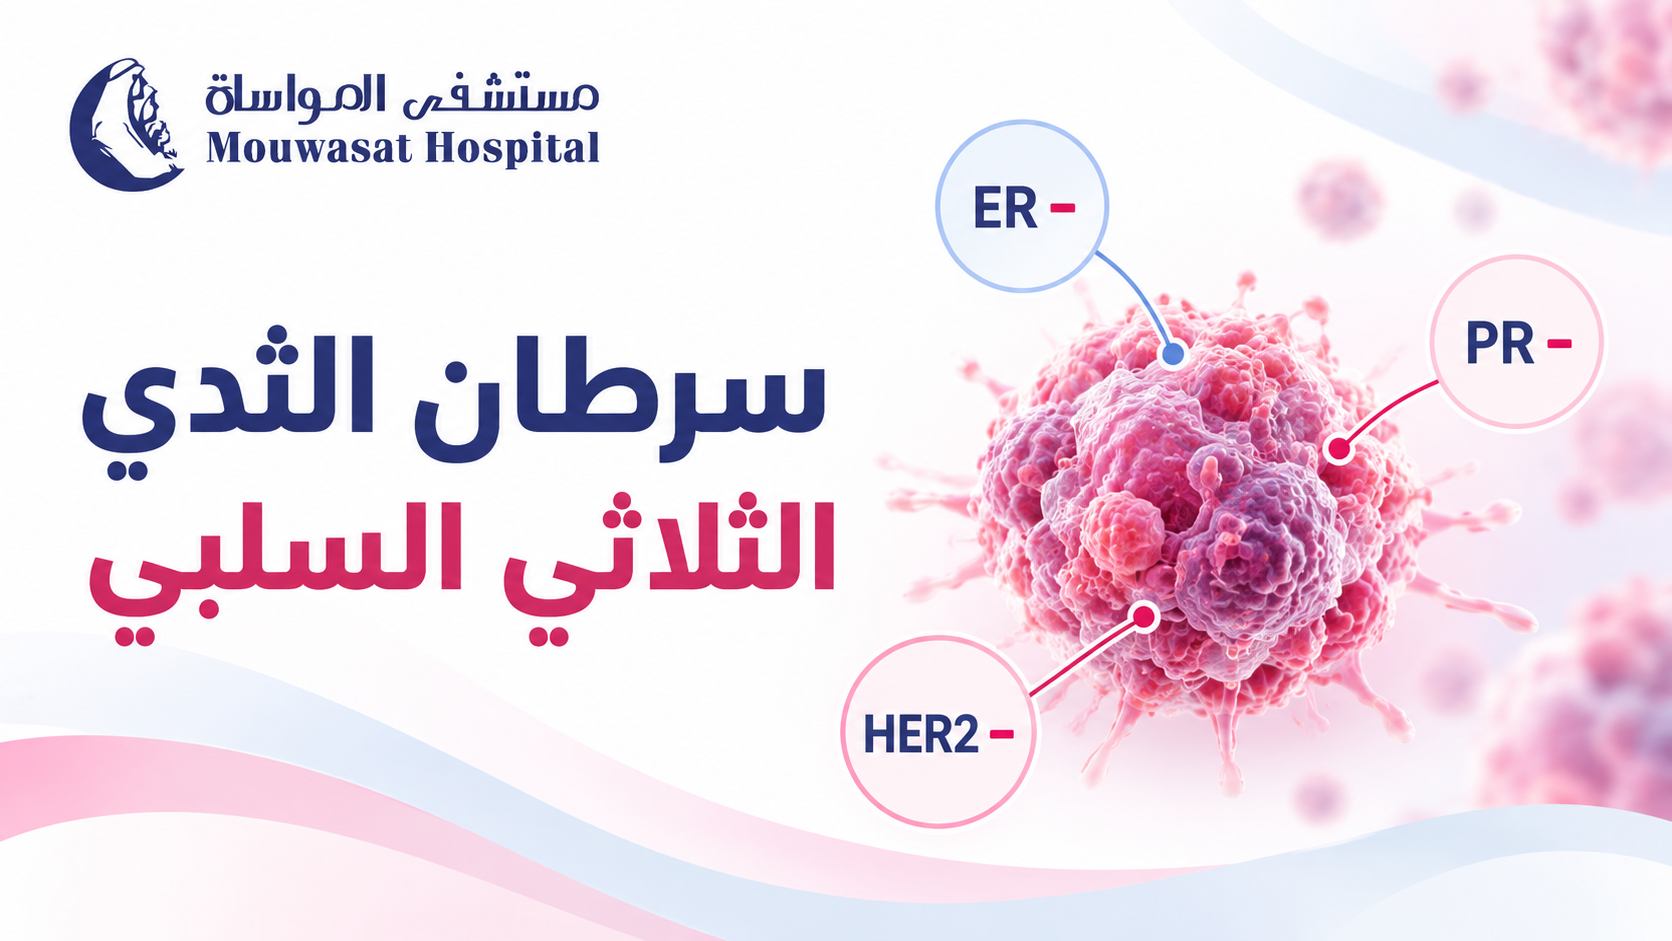
Triple-negative breast cancer lacks ER, PR and HER2 targets and tends, on average, to grow and recur more quickly than many other breast cancers. [6]
However, stage matters greatly:
These figures come from women diagnosed during 2013–2019 and should not be treated as an individual's predicted outcome. [4]
No.
Metastatic breast cancer is generally managed as a chronic disease requiring ongoing systemic treatment rather than the finite curative treatment approach commonly used for early breast cancer.
Modern treatment can control disease for meaningful periods in some patients, but duration of response varies widely.
No.
Five years is not a biological cut-off.
Hormone receptor-positive breast cancers in particular can sometimes recur many years after initial treatment, which is one reason endocrine therapy is usually prescribed for at least five years and may be extended in selected higher-risk cases. [7]
Important factors include:
Because survival databases combine thousands of people with different ages, tumour characteristics, treatments and responses into population averages.
They also describe people treated years earlier, so the full benefit of newer therapies may not yet appear in current survival statistics. [4]
What is my stage? What are my ER, PR and HER2 results? What is my tumour grade? Which features of my particular cancer increase or reduce recurrence risk, and what is the purpose of each treatment in my plan?
Many early-stage breast cancers are treated with curative intent, and survival outcomes are excellent when disease is diagnosed while still localized. No population statistic, however, can guarantee an individual's outcome.
Early breast cancer generally has an excellent outlook, although individual prognosis also depends on tumour biology, grade, lymph nodes and other factors.
NCI data show an overall 5-year relative survival rate of 94.8% for HR+/HER2- breast cancer, but the rate varies markedly according to extent of disease. [4]
No. Localized triple-negative breast cancer had a 5-year relative survival rate of 91.8% in NCI data. Outcomes are much less favourable after distant spread, which illustrates why stage is crucial. [4]
No. Five-year survival is a statistical measure. Some breast cancers, particularly hormone receptor-positive disease, can recur later.
Yes. Survival statistics necessarily describe people treated in the past, and improvements from newer treatments can take years to appear fully in population datasets. [4]
There is no single breast cancer cure rate.
Localized breast cancer generally has an excellent prognosis, while survival decreases when cancer spreads to regional lymph nodes and falls further after distant metastasis.
Tumour biology also matters. Hormone receptors, HER2 status and triple-negative status affect treatment options and prognosis, but none of these features can be interpreted without considering stage.
Population survival rates are useful for understanding broad patterns, but they cannot determine an individual's future. The most meaningful assessment combines stage, TNM, tumour grade, ER, PR, HER2, lymph node involvement, treatment response and overall health.