How can i help you?
Latest Blogs
Explore All



Not everyone needs BRCA testing, and having breast cancer in the family does not automatically mean the cancer is hereditary. However, genetic testing can be extremely important in selected situations because it may affect cancer risk assessment, family members, future screening and sometimes breast cancer treatment itself.
A positive BRCA result also does not mean that a person currently has cancer or will inevitably develop it. It means that a harmful inherited gene change has been identified that increases the risk of certain cancers. [1]
Breast cancer can be hereditary, but most breast cancers are not caused directly by an inherited cancer-predisposition variant.
The American Cancer Society estimates that about 5–10% of breast cancers are hereditary. [6]
BRCA1 and BRCA2 are among the best-known inherited breast cancer susceptibility genes, but they are not the only ones.
Other genes such as PALB2, TP53, PTEN and CDH1 can also be clinically important, which is why a multigene panel may be more appropriate than BRCA-only testing in some people. [2]
No.
Family patterns become more suggestive of inherited cancer risk when they include:
BRCA1 and BRCA2 are normal genes that produce proteins involved in repairing damaged DNA. [1]
Problems arise when a person inherits a harmful change, known as a pathogenic or likely pathogenic variant, in one of these genes.
According to the National Cancer Institute, more than 60% of women who inherit a harmful BRCA1 or BRCA2 change may develop breast cancer during their lifetime. [1]
This is a substantial increase in risk, but it is not a guarantee that cancer will occur.
Some people inherit harmful BRCA variants and never develop cancer.
Testing criteria can vary among health systems and professional guidelines, and the same criteria do not apply to people with cancer and people who have never had cancer.
The ASCO–Society of Surgical Oncology guideline recommends offering BRCA1/2 testing to all patients newly diagnosed with breast cancer at age 65 or younger. [2]
For patients older than 65, testing should also be offered in selected situations, including when:
Testing may also be important for recurrent breast cancer when PARP inhibitor therapy is being considered and for patients who develop a second primary breast cancer. [2]
A germline test can provide information that may affect several areas of care:
For a broader explanation of treatment decisions, read: Breast Cancer Treatment: How Does the Plan Change by Stage and Subtype?
Not every family history requires genetic testing, but a genetics assessment becomes more important when there is:
When possible, the National Cancer Institute recommends that testing for an inherited cancer syndrome begin with a relative who has had cancer. [3]
If a pathogenic variant is identified in the affected relative, other relatives can then be tested specifically for that variant.

Either parent.
A harmful inherited BRCA variant can come from the mother or the father, so cancer history on the father's side of the family is just as relevant to genetic risk assessment.
If a parent carries a BRCA mutation, each child has a 50% chance of inheriting it. [5]
Not necessarily.
Her breast cancer might not be hereditary. Even if she carries a BRCA variant, each child has a 50% chance of inheriting it, and inheriting the variant still does not guarantee cancer.
Inherited BRCA testing is commonly performed using:
An inherited germline variant is present throughout the body's cells, which is why blood or saliva can be used. [1]
No.
A clinician may recommend a multigene panel when the personal or family history suggests that genes other than BRCA1 and BRCA2 may be relevant. [2]
Some consumer tests examine only a limited number of known BRCA variants.
A negative result from such a test therefore may not rule out other clinically important BRCA variants. [1] [4]
| Test | What does it assess? | Does it prove inheritance? |
|---|---|---|
| Germline testing | Inherited variants present throughout the body. | Yes, when a pathogenic inherited variant is identified. |
| Tumour / somatic testing | Genetic changes within the cancer itself that may help guide treatment. | Not necessarily. |
A BRCA alteration found in a tumour may either be inherited or have arisen only in the tumour during a person's lifetime.
Therefore, if tumour testing identifies a harmful BRCA change, germline testing may be considered to determine whether it was inherited. [1] [3]
Germline testing is needed to clarify whether the finding is inherited.
A positive result means that a harmful or likely harmful genetic variant has been identified.
It can indicate:
A positive result does not predict exactly whether or when cancer will occur. [1]
The meaning depends on context.
If a specific pathogenic variant is already known in the family and a relative tests negative for that exact variant, this is a true negative: the person did not inherit that familial variant. [1]
If no familial variant has been identified, however, a negative result can be uninformative. Family history may still indicate increased risk, and another genetic cause may remain possible. [3]
A VUS is a genetic change for which there is not yet enough evidence to classify it as harmful or benign.
A VUS is not a positive pathogenic result.
The ASCO–SSO guideline states that variants of uncertain significance should not alter management. [2]
Many VUS findings are eventually reclassified as benign as more scientific data become available. [1]
If a germline BRCA variant is confirmed, blood relatives may also carry it.
Parents, siblings and adult children are usually among the closest relatives considered first, followed by other blood relatives based on the family tree.
Each child of a BRCA carrier has a 50% chance of inheriting the variant. [5]
BRCA testing is generally not recommended for children younger than 18 because BRCA-associated cancers are extremely uncommon in childhood and childhood management usually does not change based on the result. [1]
Management is individualized.
Depending on whether a person already has cancer, age, family history and other factors, options may include:
For more on breast screening, read: Mammogram Breast Cancer Screening: When Should You Start?
No.
Risk-reducing mastectomy can be discussed as one option for some BRCA carriers, but it is not an automatic requirement.
The decision can depend on:
The National Cancer Institute lists enhanced screening and risk-reducing surgery among the options available to people with inherited harmful BRCA variants. [1]
Yes, in selected situations.
BRCA-deficient cancer cells have impaired DNA repair, which can make certain treatment strategies particularly useful.
One important example is:
PARP inhibitors.
These targeted treatments can be used in specific cancers with harmful BRCA changes. [1]
However, a BRCA result alone does not determine treatment. The decision also depends on stage, whether the variant is germline or somatic, tumour subtype, previous therapies and approved treatment indications.
For some patients with breast cancer, the result can have direct treatment implications as well as implications for relatives.
Breast cancers in people with inherited harmful BRCA1 changes are more likely to be triple-negative than breast cancers in the general population. [1]
But not every triple-negative cancer is caused by BRCA, and not every BRCA-associated cancer is triple-negative.
Learn more: Breast Cancer Types and Stages: ER, PR, HER2 and Triple-Negative Disease.
Yes.
BRCA variants can be inherited and passed on by men as well as women.
BRCA2 in particular is associated with an increased risk of male breast cancer and prostate cancer, while BRCA variants can also be associated with pancreatic cancer risk. [1]
Male breast cancer itself is an important reason to consider hereditary cancer testing. [3]
Read: Male Breast Cancer: Signs That Can Be Missed and When to Seek Evaluation.
No.
BRCA testing detects inherited cancer susceptibility. It does not look for a tumour.
Breast cancer screening and diagnosis use tests such as mammography, breast MRI in selected high-risk people, and diagnostic imaging when symptoms or abnormal findings are present.
No.
Most breast cancers are not caused by an inherited BRCA variant, so routine or risk-based screening remains important even when BRCA testing is negative.
It is a genetic test that looks for harmful changes in BRCA1 and BRCA2 that can increase the risk of breast, ovarian and some other cancers.
No. It identifies genetic susceptibility rather than detecting a breast tumour.
Yes. BRCA can be inherited from either parent.
Each child has a 50% chance of inheriting the variant. [5]
Not automatically. The age at diagnosis, other cancers in the family and whether a pathogenic variant has already been found all affect whether testing is appropriate.
It means a harmful or likely harmful BRCA variant has been identified. It indicates increased cancer risk but does not guarantee that cancer will develop.
Its significance depends on whether a known familial variant exists. A true negative for a known family mutation is different from a negative test in a family where no genetic cause has yet been identified.
A variant of uncertain significance is a genetic change that cannot yet be classified as harmful or benign. It should not be treated as a pathogenic result. [2]
No. Risk is substantially increased, but some carriers never develop cancer.
Yes. In selected patients, BRCA status may affect eligibility for targeted treatments such as PARP inhibitors and can contribute to longer-term surgical and risk-management discussions.
A family history of breast cancer does not automatically mean that BRCA is present, and most breast cancers are not hereditary.
However, BRCA testing can be highly valuable when personal or family history suggests inherited cancer risk, and it is now offered more broadly to many people already diagnosed with breast cancer because the result can also influence treatment.
A positive result means increased risk, not inevitable cancer. A negative result does not always mean average risk, and a VUS should not be treated as a confirmed harmful mutation.
BRCA can be inherited from either the mother or the father, making the result relevant to both women and men within a family.
There is no single treatment duration that applies to every person with breast cancer. For some people, the intensive phase of treatment may be completed within several months, while other treatments—such as endocrine therapy for hormone receptor-positive disease—can continue for years.
The total breast cancer treatment timeline depends on the stage, tumour biology, ER, PR and HER2 status, whether chemotherapy or radiation is needed, and whether treatment starts with surgery or systemic therapy before surgery.
Breast cancer is not one disease with one standard timeline. Treatment planning takes several factors into account, including:
The National Cancer Institute notes that breast cancer treatment may involve a combination of surgery, radiation, chemotherapy, hormone therapy, targeted therapy and immunotherapy. [1]
| Treatment | General duration | Important note |
|---|---|---|
| Surgery | Usually one procedure plus several weeks of recovery | Recovery varies with lumpectomy, mastectomy and reconstruction. |
| Chemotherapy | Often 3–6 months | Applies broadly to adjuvant or neoadjuvant chemotherapy. |
| Whole-breast radiation | Often 3–4 weeks | Some schedules are as short as one week or as long as about six weeks. |
| Hormone therapy | Usually at least 5 years | Longer treatment may be advised for some higher-risk cancers. |
| HER2-targeted therapy | Often up to about 1 year in early disease | The drug and duration can change according to response and residual disease. |
| Metastatic disease | No fixed duration | Treatment is continued or changed based on benefit and side effects. |
Surgery is usually a defined procedure rather than a treatment lasting months, but recovery time varies significantly.
Breast-conserving surgery is often performed as an outpatient procedure, and many people can return to most regular activities within about two weeks. [6]
After mastectomy, many people can return to most daily activities within about four weeks, although recovery can take longer when reconstruction or more extensive surgery is performed. [7]
Recovery from surgery does not necessarily mean breast cancer treatment is complete. Chemotherapy, radiation, hormone therapy or targeted therapy may still be needed.
When chemotherapy is given before surgery or after surgery, it commonly lasts a total of about 3 to 6 months, depending on the drugs and schedule. [2]
Chemotherapy is delivered in cycles. A treatment dose or series of doses is followed by a recovery period before the next cycle.
Many cycles are two or three weeks long, although weekly and other schedules are also used. [2]
The duration can depend on:
Whole-breast radiation is commonly given five days a week for about 3 to 4 weeks. [3]
However, some modern schedules can be completed in about one week, while some people require longer courses of approximately six weeks.
Radiation is generally started after the surgical area has healed. The National Cancer Institute notes that this is commonly about one to two months after surgery. [8]
If chemotherapy is also required after surgery, radiation is generally delayed until chemotherapy has been completed. [8]
Hormone or endocrine therapy is used for hormone receptor-positive breast cancer.
It is usually taken for at least five years. Some people may be advised to continue for longer if their risk of recurrence is higher. [4]
This does not mean that the person remains in the same intensive phase of treatment for five years. Surgery, chemotherapy and radiation may already be complete while endocrine therapy continues as a long-term treatment to reduce recurrence risk.
HER2-positive breast cancer may require HER2-targeted treatment in addition to other therapies.
For early HER2-positive breast cancer, trastuzumab-based therapy is commonly given for a total of approximately one year. [5]
The treatment can begin before or after surgery. If cancer remains in the surgical specimen after preoperative treatment, the targeted treatment used afterward may change.
For advanced breast cancer, HER2-targeted treatment may continue for as long as it remains helpful and tolerable rather than following a predetermined one-year endpoint. [5]
No.
Many early-stage breast cancers are treated with surgery first, followed by additional treatment when needed. [1]
For larger, locally advanced or certain biologically aggressive tumours, chemotherapy and/or targeted therapy may be given first to shrink the tumour. This is known as neoadjuvant therapy.
| Possible pathway | Simplified example |
|---|---|
| Surgery first | Surgery → chemotherapy if needed → radiation → hormone/targeted treatment if appropriate |
| Systemic treatment first | Chemotherapy ± targeted treatment → surgery → radiation → additional systemic treatment if needed |
Yes, although stage is not the only factor.
DCIS treatment may involve surgery, radiation and sometimes endocrine therapy depending on the individual case. [1]
Many stage I cancers are treated with surgery first. Some people do not require chemotherapy, while radiation, hormone therapy or targeted treatment may still be recommended according to tumour biology.
Treatment is often more multimodal and may include systemic therapy before surgery, surgery, radiation and further treatment afterward. The intensive treatment pathway can therefore extend over several months. [1]
Metastatic breast cancer usually does not have a predetermined treatment endpoint.
Treatment is used to control the disease, slow progression, reduce symptoms and maintain quality of life. Therapy is continued or changed according to response, side effects and tumour biology.
No.
Some early breast cancers do not require chemotherapy. The decision may depend on stage, tumour grade, lymph nodes, hormone receptor status, HER2 status and sometimes genomic testing.
Chemotherapy is more likely to be considered in situations such as:
No.
Radiation is commonly recommended after breast-conserving surgery. After mastectomy, whether radiation is needed depends on features such as tumour size, lymph node involvement and local extent. [10]
That depends on what is meant by “finished.”
The intensive phase involving surgery, chemotherapy and radiation may be completed within several months, but endocrine or targeted treatment may continue much longer.
After active treatment, follow-up focuses on:
Some people may have surgery as their main short-term treatment, but many breast cancer plans include additional therapy lasting weeks, months or years.
Several months can be a common duration for the intensive phase of some treatment plans, especially when chemotherapy, surgery and radiation are required. However, there is no rule that all breast cancer treatment ends within six months.
Neoadjuvant breast cancer chemotherapy commonly falls within the overall 3-to-6-month range, depending on the regimen and response. [2]
Many whole-breast schedules are given five days a week for about 3 to 4 weeks, although shorter and longer schedules are available depending on the clinical situation. [3]
Not necessarily. Hormone therapy, for example, may continue for years in early-stage hormone receptor-positive breast cancer to reduce recurrence risk.
There is no single answer to how long breast cancer treatment takes.
Chemotherapy given before or after surgery often lasts about 3 to 6 months. Many modern radiation schedules take about 3 to 4 weeks. Hormone therapy usually continues for at least five years, and some HER2-targeted treatment for early breast cancer is given for about one year.
Treatment may begin with surgery in one patient and with chemotherapy or targeted therapy in another.
The most useful way to understand the timeline is to look at the entire treatment plan: which therapies are needed, in what order, which are part of an intensive temporary phase, and which are intended to continue long term.

Not every breast cancer requires chemotherapy, not every treatment plan starts with surgery, and stage alone does not determine treatment. The plan depends on a combination of cancer stage, tumour size, lymph node involvement, ER and PR status, HER2 status, tumour grade, certain gene changes, overall health and response to treatment. [1] [2]
One person with stage I breast cancer may need surgery followed by endocrine therapy, while another person with a similar stage may also need chemotherapy or HER2-targeted treatment because the biology of the tumour is different.
Treatment is not selected from the word “breast cancer” or the stage alone.
Important factors include:
The National Cancer Institute notes that most patients receive more than one type of treatment and that stage, subtype, overall health and other individual factors all contribute to treatment planning. [1]
They can identify treatment targets.
Biomarker testing helps doctors understand the tumour and choose treatments that are more likely to work. [2]
For more detail, read: Breast Cancer Types and Stages: Understanding ER, PR, HER2 and Triple-Negative Disease.
| Stage | Common treatment pathway | What can change the plan? |
|---|---|---|
| Stage 0 / DCIS | Surgery ± radiation; endocrine therapy may be discussed in selected cases. | Extent of DCIS, surgery type and hormone receptor status. |
| Stage I | Usually surgery first, followed by additional treatment when needed. | ER/PR, HER2, grade, nodes, tumour size and sometimes genomic tests. |
| Stage II | Surgery first in some cases; systemic treatment before surgery in others. | Tumour size, nodes and biological subtype. |
| Stage III | Often systemic treatment → surgery → radiation → additional systemic therapy. | Subtype, response and residual disease. |
| Stage IV | Systemic treatment is usually central; surgery or radiation may be used selectively. | HR/HER2 status, gene changes, sites of spread, symptoms and response. |
Stage 0 usually refers to ductal carcinoma in situ (DCIS), in which abnormal cells remain inside the breast ducts and have not become invasive.
Treatment may include:
Chemotherapy is not routinely required for DCIS because treatment is different from that of invasive breast cancer. [1]
Stage I breast cancer is early-stage disease, and treatment commonly begins with surgery. [1]
Surgery may involve:
No.
Some small, hormone receptor-positive, HER2-negative tumours with favourable features may have limited expected benefit from chemotherapy.
In certain HR-positive/HER2-negative cancers, genomic tests can help estimate whether chemotherapy is likely to add meaningful benefit. [3]
Chemotherapy or targeted treatment becomes more important when other tumour features indicate higher risk, such as certain HER2-positive or triple-negative cancers.
Radiation is commonly used after breast-conserving surgery to reduce the risk of cancer returning in the breast. [3]
Endocrine therapy is usually recommended to reduce recurrence risk. [5]
Stage II treatment can follow more than one pathway.
Some patients have surgery first, while others receive chemotherapy and/or targeted treatment before surgery. [1] [3]
Preoperative treatment may be considered when the tumour is larger, lymph nodes are involved, breast-conserving surgery could become easier after tumour shrinkage, or tumour subtype makes response to preoperative treatment particularly useful for later decisions.
HER2-positive and triple-negative disease are important examples where treatment before surgery may be preferred in appropriate cases. [3]
Stage III is generally considered locally advanced breast cancer.
Treatment often begins with systemic therapy, followed by surgery, radiation and additional systemic treatment based on subtype and response. [1]
A simplified pathway may look like:
Systemic therapy → surgery → radiation → additional treatment based on biomarkers and response.
The systemic treatment itself depends on tumour biology:
Stage IV means breast cancer has spread to distant parts of the body.
Systemic treatment is usually the foundation of care, with the goals of controlling the cancer, slowing progression, relieving symptoms and maintaining quality of life. [4]
The treatment selected depends heavily on tumour biology.
| Subtype | Systemic treatment that may be used |
|---|---|
| HR-positive / HER2-negative | Endocrine therapy, often combined with appropriate targeted therapy. |
| HER2-positive | HER2-directed therapies with other systemic treatment as appropriate. |
| Triple-negative | Chemotherapy, with immunotherapy or other targeted options in selected cases. |
| Selected BRCA-related cancers | PARP inhibitors may be an option in selected situations. |
HR-positive breast cancer contains estrogen and/or progesterone receptors, allowing endocrine therapy to target the role these hormones play in cancer growth. [2]
No.
The decision depends on factors including stage, nodes, tumour size, grade, HER2 status, recurrence risk and sometimes genomic test results.
This means one patient may receive surgery, radiation and endocrine therapy without chemotherapy, while another with HR-positive cancer may benefit from chemotherapy as well.
It is usually prescribed for at least five years, and longer treatment may be appropriate for some patients at higher risk of recurrence. [5]
For a full treatment timeline, read: How Long Does Breast Cancer Treatment Take?
HER2-positive breast cancer has increased HER2 activity, which provides an important treatment target. [2]
HER2-directed therapy may be combined with chemotherapy and can be given before or after surgery according to stage, tumour size and other factors. [3]
For many early HER2-positive treatment plans, HER2-targeted treatment continues for a total of approximately one year, although the exact approach varies. [3]
A tumour can have more than one actionable target.
Treatment may therefore include HER2-targeted therapy, chemotherapy when appropriate, endocrine therapy, surgery and radiation according to stage.
Triple-negative breast cancer lacks estrogen receptors, progesterone receptors and HER2 positivity. [7]
Therefore:
Triple-negative does not mean that treatment cannot work. It simply means that ER, PR and HER2 are not available as treatment targets.
BRCA1 and BRCA2 help cells repair DNA damage. Harmful inherited variants can increase the risk of breast and other cancers.
BRCA testing can sometimes affect treatment as well as inherited risk assessment. [8]
Selected patients with BRCA-related breast cancer may be candidates for targeted treatments known as PARP inhibitors. [6]
Many early breast cancers are treated with surgery first.
In other cases, systemic treatment is given first. This is known as neoadjuvant therapy.
Possible reasons include:
After neoadjuvant treatment, the tissue removed during surgery is examined by a pathologist.
If no invasive cancer remains in the breast or lymph nodes, this may be described as a pathologic complete response (pCR).
If residual cancer remains, this does not automatically mean treatment has failed.
The amount and type of residual disease can provide valuable information and may change the treatment recommended after surgery, particularly in HER2-positive and triple-negative breast cancer. [3]
No.
Surgery treats cancer in the breast and surgical area, whereas chemotherapy, endocrine therapy and targeted therapies are systemic treatments.
Some patients also require radiation after mastectomy depending on tumour size, lymph node involvement and other risk factors.
Yes, in selected cases.
For some early HR-positive cancers, a medically appropriate plan may involve surgery, radiation when needed and endocrine therapy without chemotherapy.
For other cancers, chemotherapy can be an important part of curative treatment.
The more useful question is therefore not simply “Do I need chemotherapy?” but:
“How much benefit is chemotherapy expected to add in my specific case?”
For early and locally advanced breast cancer that has not spread to distant organs, treatment is often delivered with curative intent.
For stage IV metastatic breast cancer, treatment usually focuses on long-term disease control, slowing progression, reducing symptoms and maintaining quality of life. [4]
For more on long-term outcomes, read: Breast Cancer Survival Rates by Stage and Subtype.
There is no single treatment that is best for every breast cancer. The best plan depends on stage, ER, PR, HER2, tumour grade, lymph nodes, gene changes, overall health and response to treatment.
Not always. Some lower-risk stage I cancers may have little expected benefit from chemotherapy, while other stage I cancers can benefit significantly because of their biological features.
Yes. Although treatment is usually more intensive and involves several treatment types, many stage III cancers that have not spread to distant organs are treated with curative intent.
Yes. Many systemic treatments can shrink or control metastatic breast cancer. Treatment is usually ongoing and adjusted according to response and side effects.
No. Some early HR-positive cancers are treated without chemotherapy, while higher-risk cancers may still benefit from it.
No. Triple-negative describes tumour biology, while stage III describes how far the cancer has spread. Triple-negative breast cancer can occur at different stages.
Surgery and the rest of the treatment plan are still determined by the oncology team. If no invasive cancer remains in the breast or lymph nodes at surgery, this may represent a pathologic complete response.
Breast cancer treatment is determined by much more than stage.
Stage I often begins with surgery and does not always require chemotherapy. Stage II may begin with either surgery or systemic treatment. Many stage III cancers are treated with systemic therapy before surgery, followed by surgery, radiation and additional treatment.
In stage IV disease, systemic treatment becomes central to long-term disease control.
Tumour biology also changes the plan: HR-positive disease can respond to endocrine therapy, HER2-positive disease can be targeted with HER2-directed treatments, and triple-negative disease relies on other systemic strategies such as chemotherapy and, in selected cases, immunotherapy.
The most useful questions after diagnosis are therefore not only “What stage is my cancer?” but also: What subtype is it? What are my ER, PR and HER2 results? Do I need treatment before surgery or after it, and what is the purpose of each part of my treatment plan?
There is no single treatment duration that applies to every person with breast cancer. For some people, the intensive phase of treatment may be completed within several months, while other treatments—such as endocrine therapy for hormone receptor-positive disease—can continue for years.
The total breast cancer treatment timeline depends on the stage, tumour biology, ER, PR and HER2 status, whether chemotherapy or radiation is needed, and whether treatment starts with surgery or systemic therapy before surgery.
Breast cancer is not one disease with one standard timeline. Treatment planning takes several factors into account, including:
The National Cancer Institute notes that breast cancer treatment may involve a combination of surgery, radiation, chemotherapy, hormone therapy, targeted therapy and immunotherapy. [1]
| Treatment | General duration | Important note |
|---|---|---|
| Surgery | Usually one procedure plus several weeks of recovery | Recovery varies with lumpectomy, mastectomy and reconstruction. |
| Chemotherapy | Often 3–6 months | Applies broadly to adjuvant or neoadjuvant chemotherapy. |
| Whole-breast radiation | Often 3–4 weeks | Some schedules are as short as one week or as long as about six weeks. |
| Hormone therapy | Usually at least 5 years | Longer treatment may be advised for some higher-risk cancers. |
| HER2-targeted therapy | Often up to about 1 year in early disease | The drug and duration can change according to response and residual disease. |
| Metastatic disease | No fixed duration | Treatment is continued or changed based on benefit and side effects. |
Surgery is usually a defined procedure rather than a treatment lasting months, but recovery time varies significantly.
Breast-conserving surgery is often performed as an outpatient procedure, and many people can return to most regular activities within about two weeks. [6]
After mastectomy, many people can return to most daily activities within about four weeks, although recovery can take longer when reconstruction or more extensive surgery is performed. [7]
Recovery from surgery does not necessarily mean breast cancer treatment is complete. Chemotherapy, radiation, hormone therapy or targeted therapy may still be needed.
When chemotherapy is given before surgery or after surgery, it commonly lasts a total of about 3 to 6 months, depending on the drugs and schedule. [2]
Chemotherapy is delivered in cycles. A treatment dose or series of doses is followed by a recovery period before the next cycle.
Many cycles are two or three weeks long, although weekly and other schedules are also used. [2]
The duration can depend on:
Whole-breast radiation is commonly given five days a week for about 3 to 4 weeks. [3]
However, some modern schedules can be completed in about one week, while some people require longer courses of approximately six weeks.
Radiation is generally started after the surgical area has healed. The National Cancer Institute notes that this is commonly about one to two months after surgery. [8]
If chemotherapy is also required after surgery, radiation is generally delayed until chemotherapy has been completed. [8]
Hormone or endocrine therapy is used for hormone receptor-positive breast cancer.
It is usually taken for at least five years. Some people may be advised to continue for longer if their risk of recurrence is higher. [4]
This does not mean that the person remains in the same intensive phase of treatment for five years. Surgery, chemotherapy and radiation may already be complete while endocrine therapy continues as a long-term treatment to reduce recurrence risk.
HER2-positive breast cancer may require HER2-targeted treatment in addition to other therapies.
For early HER2-positive breast cancer, trastuzumab-based therapy is commonly given for a total of approximately one year. [5]
The treatment can begin before or after surgery. If cancer remains in the surgical specimen after preoperative treatment, the targeted treatment used afterward may change.
For advanced breast cancer, HER2-targeted treatment may continue for as long as it remains helpful and tolerable rather than following a predetermined one-year endpoint. [5]
No.
Many early-stage breast cancers are treated with surgery first, followed by additional treatment when needed. [1]
For larger, locally advanced or certain biologically aggressive tumours, chemotherapy and/or targeted therapy may be given first to shrink the tumour. This is known as neoadjuvant therapy.
| Possible pathway | Simplified example |
|---|---|
| Surgery first | Surgery → chemotherapy if needed → radiation → hormone/targeted treatment if appropriate |
| Systemic treatment first | Chemotherapy ± targeted treatment → surgery → radiation → additional systemic treatment if needed |
Yes, although stage is not the only factor.
DCIS treatment may involve surgery, radiation and sometimes endocrine therapy depending on the individual case. [1]
Many stage I cancers are treated with surgery first. Some people do not require chemotherapy, while radiation, hormone therapy or targeted treatment may still be recommended according to tumour biology.
Treatment is often more multimodal and may include systemic therapy before surgery, surgery, radiation and further treatment afterward. The intensive treatment pathway can therefore extend over several months. [1]
Metastatic breast cancer usually does not have a predetermined treatment endpoint.
Treatment is used to control the disease, slow progression, reduce symptoms and maintain quality of life. Therapy is continued or changed according to response, side effects and tumour biology.
No.
Some early breast cancers do not require chemotherapy. The decision may depend on stage, tumour grade, lymph nodes, hormone receptor status, HER2 status and sometimes genomic testing.
Chemotherapy is more likely to be considered in situations such as:
No.
Radiation is commonly recommended after breast-conserving surgery. After mastectomy, whether radiation is needed depends on features such as tumour size, lymph node involvement and local extent. [10]
That depends on what is meant by “finished.”
The intensive phase involving surgery, chemotherapy and radiation may be completed within several months, but endocrine or targeted treatment may continue much longer.
After active treatment, follow-up focuses on:
Some people may have surgery as their main short-term treatment, but many breast cancer plans include additional therapy lasting weeks, months or years.
Several months can be a common duration for the intensive phase of some treatment plans, especially when chemotherapy, surgery and radiation are required. However, there is no rule that all breast cancer treatment ends within six months.
Neoadjuvant breast cancer chemotherapy commonly falls within the overall 3-to-6-month range, depending on the regimen and response. [2]
Many whole-breast schedules are given five days a week for about 3 to 4 weeks, although shorter and longer schedules are available depending on the clinical situation. [3]
Not necessarily. Hormone therapy, for example, may continue for years in early-stage hormone receptor-positive breast cancer to reduce recurrence risk.
There is no single answer to how long breast cancer treatment takes.
Chemotherapy given before or after surgery often lasts about 3 to 6 months. Many modern radiation schedules take about 3 to 4 weeks. Hormone therapy usually continues for at least five years, and some HER2-targeted treatment for early breast cancer is given for about one year.
Treatment may begin with surgery in one patient and with chemotherapy or targeted therapy in another.
The most useful way to understand the timeline is to look at the entire treatment plan: which therapies are needed, in what order, which are part of an intensive temporary phase, and which are intended to continue long term.

One of the most common questions after a breast cancer diagnosis is: What are my chances of recovery?
There is no single percentage that applies to everyone. Outlook varies substantially according to how far the cancer has spread at diagnosis, tumour subtype, ER and PR status, HER2 status, tumour grade, response to treatment and individual health factors.
Medical statistics also usually measure survival rather than “cure” directly.
A 5-year survival rate does not mean someone is expected to live only five years. It is a population statistic used to understand outcomes among large groups and cannot predict exactly what will happen to an individual.
Not exactly.
Most cancer registries use statistical measures such as:
This is why statements such as “breast cancer has a 90% cure rate” can be misleading unless the statistic, population and period are clearly defined.
No.
Five years is simply a standard reference point used in research. Many breast cancer survivors live for decades after diagnosis.
According to the Saudi Health Council's national Cancer Survival Report, age-standardised 5-year net survival among women with breast cancer was approximately 82.1% for patients diagnosed during 2015–2019. [1]
This figure should not be interpreted as an individual's chance of cure.
It describes a historical population and uses a different survival measure from the relative survival statistics commonly reported by US SEER databases.
Survival figures can differ because of the population studied, years of diagnosis, cancer stage distribution, tumour subtypes, access to treatment and the statistical method used.
How far the cancer has spread at diagnosis is one of the strongest factors affecting prognosis.
The American Cancer Society reports the following 5-year relative survival rates for women diagnosed with invasive breast cancer in the United States between 2015 and 2021. [2]
| SEER stage | Meaning | 5-year relative survival |
|---|---|---|
| Localized | Cancer has not spread outside the breast. | >99% |
| Regional | Cancer has spread to nearby structures or regional lymph nodes. | 87% |
| Distant | Cancer has spread to distant parts of the body. | 32% |
| All stages combined | All eligible cases combined. | 92% |
The localized figure applies to invasive breast cancer and does not include ductal carcinoma in situ (DCIS). [2]
Not exactly.
SEER survival statistics use a simplified system of localized, regional and distant disease, whereas clinical breast cancer staging uses the AJCC system with stages 0 through IV.
The systems overlap conceptually but are not interchangeable.
Modern prognostic breast cancer staging also incorporates information such as tumour grade and ER, PR and HER2 status in addition to TNM information. [3]
Tumour biology also matters.
The National Cancer Institute reports the following 5-year relative survival rates from SEER data for women diagnosed during 2013–2019. [4]
| Subtype | Overall | Localized | Regional | Distant |
|---|---|---|---|---|
| HR+/HER2- | 94.8% | 100.0% | 90.2% | 34.0% |
| HR+/HER2+ | 91.0% | 99.1% | 89.8% | 45.6% |
| HR-/HER2+ | 85.6% | 97.2% | 84.0% | 39.5% |
| Triple-negative | 77.6% | 91.8% | 66.2% | 12.8% |
These statistics describe populations, not individual outcomes, and newer treatments may not yet be fully reflected in historical survival datasets. [4]
Hormone receptor-positive breast cancer contains estrogen and/or progesterone receptors and can often be treated with endocrine therapy. [5]
In NCI data, overall 5-year relative survival was:
However, the extent of disease at diagnosis remains extremely important. Hormone receptor-positive metastatic cancer has a very different prognosis from localized hormone receptor-positive cancer.
Hormone receptor-positive cancers often have a favourable short-term outlook, but they can recur many years after initial treatment. [5]
Not necessarily.
HER2-positive tumours can grow more quickly, but modern HER2-targeted therapies have substantially changed the treatment landscape.
NCI data show overall 5-year relative survival of 91.0% for HR+/HER2+ disease and 85.6% for HR-/HER2+ disease, with large differences according to whether the cancer is localized, regional or metastatic. [4]
Triple-negative breast cancer lacks ER, PR and HER2 targets and tends, on average, to grow and recur more quickly than many other breast cancers. [6]
However, stage matters greatly:
These figures come from women diagnosed during 2013–2019 and should not be treated as an individual's predicted outcome. [4]
No.
Metastatic breast cancer is generally managed as a chronic disease requiring ongoing systemic treatment rather than the finite curative treatment approach commonly used for early breast cancer.
Modern treatment can control disease for meaningful periods in some patients, but duration of response varies widely.
No.
Five years is not a biological cut-off.
Hormone receptor-positive breast cancers in particular can sometimes recur many years after initial treatment, which is one reason endocrine therapy is usually prescribed for at least five years and may be extended in selected higher-risk cases. [7]
Important factors include:
Because survival databases combine thousands of people with different ages, tumour characteristics, treatments and responses into population averages.
They also describe people treated years earlier, so the full benefit of newer therapies may not yet appear in current survival statistics. [4]
What is my stage? What are my ER, PR and HER2 results? What is my tumour grade? Which features of my particular cancer increase or reduce recurrence risk, and what is the purpose of each treatment in my plan?
Many early-stage breast cancers are treated with curative intent, and survival outcomes are excellent when disease is diagnosed while still localized. No population statistic, however, can guarantee an individual's outcome.
Early breast cancer generally has an excellent outlook, although individual prognosis also depends on tumour biology, grade, lymph nodes and other factors.
NCI data show an overall 5-year relative survival rate of 94.8% for HR+/HER2- breast cancer, but the rate varies markedly according to extent of disease. [4]
No. Localized triple-negative breast cancer had a 5-year relative survival rate of 91.8% in NCI data. Outcomes are much less favourable after distant spread, which illustrates why stage is crucial. [4]
No. Five-year survival is a statistical measure. Some breast cancers, particularly hormone receptor-positive disease, can recur later.
Yes. Survival statistics necessarily describe people treated in the past, and improvements from newer treatments can take years to appear fully in population datasets. [4]
There is no single breast cancer cure rate.
Localized breast cancer generally has an excellent prognosis, while survival decreases when cancer spreads to regional lymph nodes and falls further after distant metastasis.
Tumour biology also matters. Hormone receptors, HER2 status and triple-negative status affect treatment options and prognosis, but none of these features can be interpreted without considering stage.
Population survival rates are useful for understanding broad patterns, but they cannot determine an individual's future. The most meaningful assessment combines stage, TNM, tumour grade, ER, PR, HER2, lymph node involvement, treatment response and overall health.
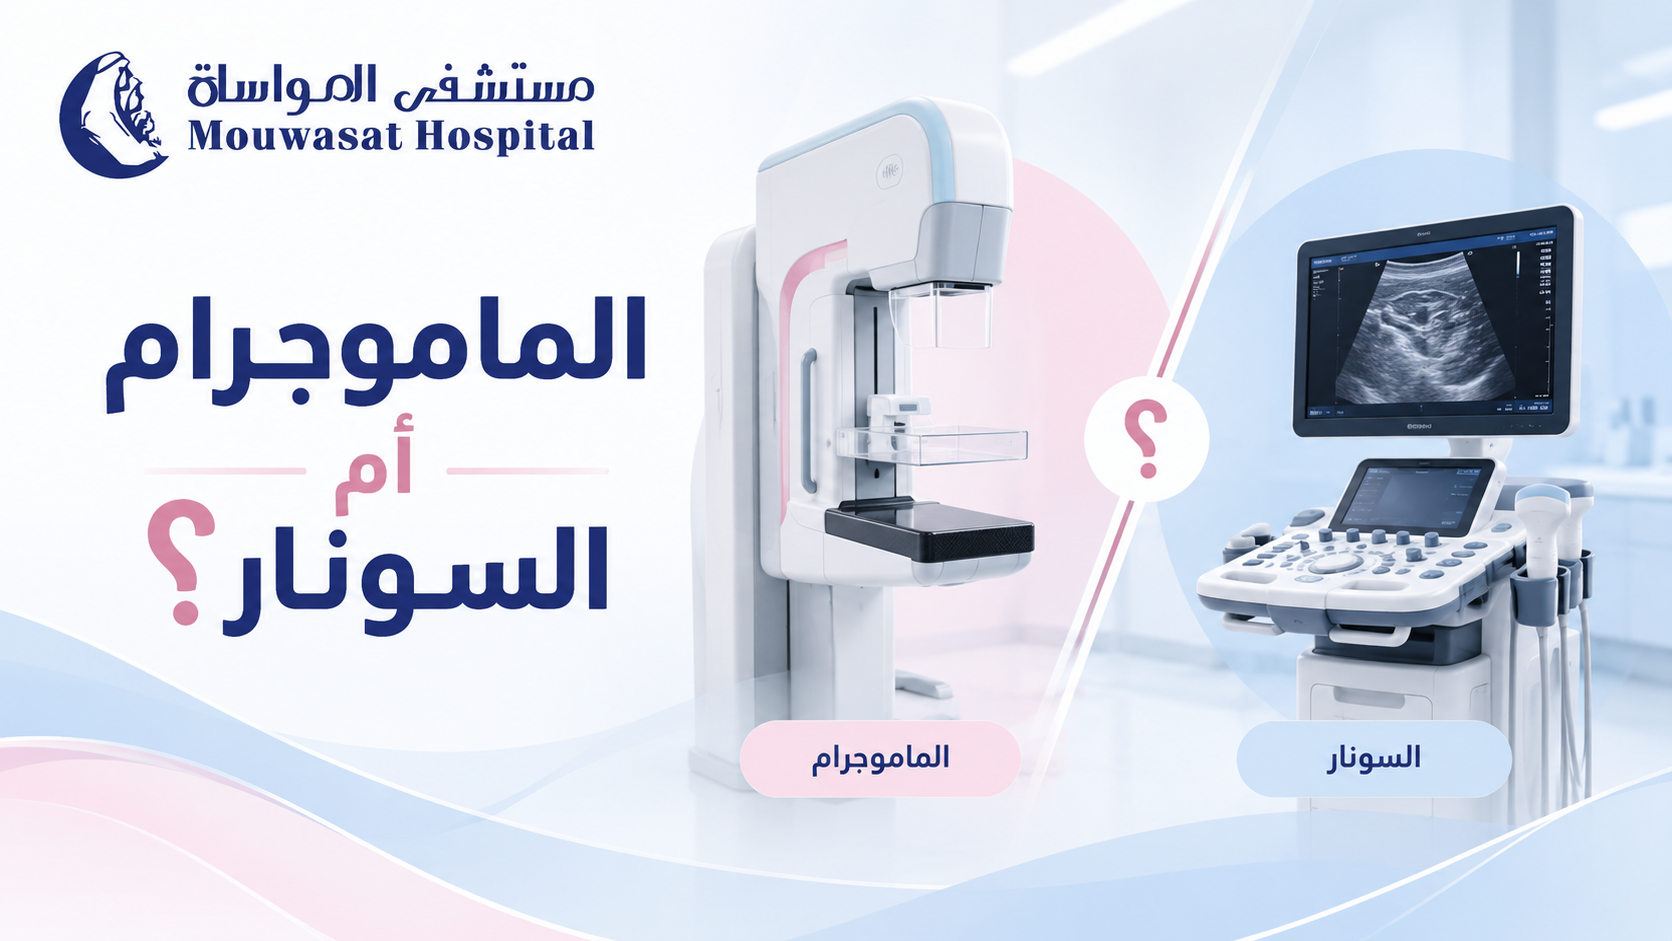
A mammogram and a breast ultrasound are both important breast imaging tests, but they are not interchangeable. Each works differently and answers different clinical questions.
Mammography uses low-dose X-rays and is the primary imaging method used for breast cancer screening. Ultrasound uses sound waves and is particularly useful for evaluating a specific breast lump or abnormality and determining whether a finding is solid or fluid-filled. In many situations, the two tests complement rather than replace each other. [1] [2]
| Feature | Mammogram | Breast ultrasound |
|---|---|---|
| Technology | Low-dose X-rays. | High-frequency sound waves. |
| Main role | Screening and diagnostic breast imaging. | Evaluating focal abnormalities and complementing mammography. |
| Radiation | Uses a low dose of ionising radiation. | Uses no ionising radiation. |
| Microcalcifications | Can detect small calcifications associated with some early breast cancers. | Some calcifications visible on mammography may not be visible on ultrasound. |
| Cysts vs solid masses | May identify a mass or abnormal area. | Very useful for determining whether a finding is fluid-filled or solid. |
The Saudi Ministry of Health describes mammography as low-dose X-ray imaging used for both screening and diagnosis. Breast ultrasound instead produces real-time images using sound waves and does not use radiation. [1] [2]
Mammography is particularly important when the goal is breast cancer screening before symptoms develop.
It can image the entire breast and identify changes that cannot be felt, including small calcifications that may be associated with ductal carcinoma in situ (DCIS) or other breast cancers. [3]
Diagnostic mammography is also used when a patient already has a breast concern, such as:
Breast ultrasound is a safe, non-invasive examination that uses sound waves to evaluate breast tissue. [2]
Common uses include:
| Situation | Typical imaging approach |
|---|---|
| Under 30 with a palpable lump | Breast ultrasound is usually the appropriate first test. |
| Age 30–39 with a new lump | Ultrasound and/or diagnostic mammography or tomosynthesis may be appropriate. |
| Age 40 or older with a new lump | Diagnostic mammography or tomosynthesis is commonly used, often with targeted ultrasound. |
American College of Radiology guidance generally recommends ultrasound first for a palpable mass in women younger than 30, while diagnostic mammography and ultrasound become complementary tools at older ages. [4]
Ultrasound can identify masses and abnormalities that may represent breast cancer, but it cannot detect every breast cancer and cannot always confirm whether a mass is malignant.
A suspicious solid mass may require tissue sampling. A biopsy examines the actual cells and can provide the definitive diagnosis when imaging alone cannot.
No. Radiologists assess characteristics such as shape, margins, orientation and internal appearance, but no single ultrasound image allows a patient to diagnose breast cancer by comparing pictures online.
Yes.
Some early breast cancers, particularly ductal carcinoma in situ (DCIS), may present mainly as small calcifications on mammography without a mass that is visible on ultrasound. This is one reason ultrasound does not replace mammography for breast cancer screening. [2] [3]
Yes. Ultrasound can identify some lesions that are difficult to see clearly on mammography, including some abnormalities in dense breast tissue and findings related to a specific palpable area.
The two tests therefore provide different information rather than competing to determine which is universally “better.”
Breast density refers to the relative amount of fibrous and glandular tissue compared with fatty tissue as seen on a mammogram. It cannot be determined simply by touching the breast. [5]
Dense tissue and many breast abnormalities both appear white on mammograms, which can make some cancers more difficult to detect.
Ultrasound may detect additional findings in women with dense breasts, but supplemental ultrasound also increases false-positive findings and may lead to extra testing or benign biopsies. [2]
No.
More imaging does not always mean better care. Additional ultrasound can identify benign abnormalities that lead to repeat imaging, aspiration or biopsy.
Using both tests is particularly useful when:
One result does not simply cancel out the other.
A palpable lump may not be clearly visible on mammography but can sometimes be characterised with targeted ultrasound. Conversely, suspicious calcifications may be visible on mammography without a corresponding ultrasound abnormality.
If a new palpable lump remains despite reassuring imaging, the clinical finding should still be followed up. Some cancers may have a normal appearance on initial imaging, and biopsy may occasionally be needed when the examination and imaging do not agree. [4]
Imaging can classify a finding as more or less suspicious, but it does not always provide a definitive tissue diagnosis.
Radiologists use the BI-RADS system to describe breast imaging findings and recommend the next step, which may range from routine screening to short-term follow-up, additional imaging or biopsy.
Breast MRI is not a routine replacement for mammography or ultrasound.
For some women at high risk of breast cancer, MRI may be used in addition to mammography because it is more sensitive for detecting certain cancers. [6]
MRI may also be used in selected diagnostic situations, but its greater sensitivity also means that it can detect findings that later prove to be benign.
| Situation | Typical approach |
|---|---|
| No symptoms; routine breast cancer screening | Mammography is the primary imaging test. |
| Palpable lump under age 30 | Ultrasound is usually the first examination. |
| Palpable lump from age 30 onward | Diagnostic mammography and/or ultrasound depending on age and findings. |
| Abnormality on mammography | Targeted ultrasound or additional mammographic views may be recommended. |
| Suspicious microcalcifications | Mammography is particularly important; biopsy may be recommended based on the findings. |
| Dense breasts without symptoms | Mammography remains important; supplemental imaging depends on overall risk. |
| Very high breast cancer risk | MRI may be added to mammography as part of an individualised screening plan. |
The difference between mammography and breast ultrasound is not that one is universally better than the other. They answer different clinical questions.
Mammography is the primary breast cancer screening test and can identify findings such as microcalcifications before a lump can be felt. Ultrasound is especially useful for evaluating a focal area and determining whether a mass is solid or fluid-filled.
Ultrasound therefore does not generally replace mammography, even in women with dense breasts. At the same time, a normal mammogram should not be used to dismiss a new persistent lump; targeted ultrasound or further evaluation may still be appropriate.
The best test is the one that matches the clinical question—and in some situations, the correct answer is to use both.
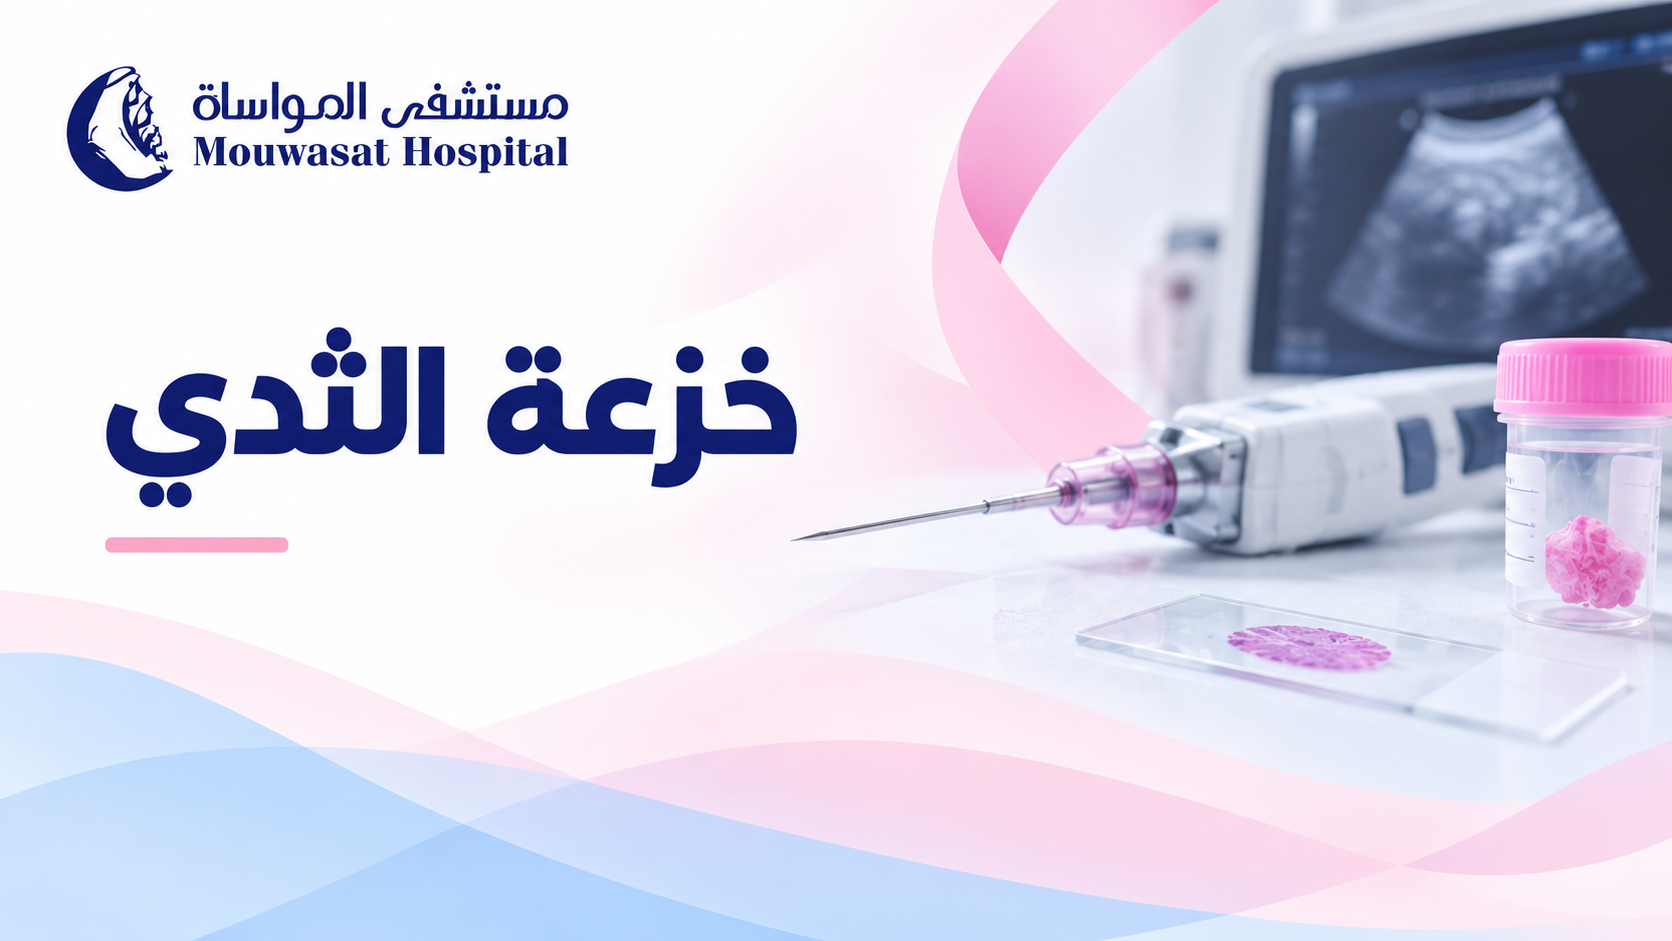
Being told that you need a breast biopsy can be frightening, but a biopsy recommendation does not mean that breast cancer has already been diagnosed. It means that a breast lump or imaging abnormality needs tissue analysis to determine what it actually is.
The American Cancer Society states that a biopsy is the only way to know for certain whether an abnormal breast area contains cancer cells. At the same time, most breast biopsy results are not cancer. [1]
A breast biopsy is a procedure that removes a small sample of breast tissue from an abnormal area so that it can be examined in a laboratory by a pathologist.
The sample may be obtained with a thin needle, a larger hollow core needle or, less commonly, through a surgical biopsy. [1]
In most needle biopsies, the purpose is not to remove the entire abnormality. It is to obtain enough tissue to determine what is happening at a cellular level.
A biopsy may be recommended when clinical examination or breast imaging identifies an abnormality that cannot be confidently classified as benign.
Examples include:
Imaging describes how an area looks. Biopsy answers a different question: what is the tissue actually made of?
No.
A biopsy is recommended because imaging or examination cannot provide a sufficiently certain answer. The American Cancer Society notes that most breast biopsy results are not cancer. [1]
The pathology result might show:
Evidence does not support the common belief that standard breast biopsy causes cancer to spread through the body.
The National Cancer Institute states that the chance that tumour biopsy or surgery will cause cancer to spread to other parts of the body is extremely low. Standard medical techniques are designed to minimise this risk. [2]
Avoiding a necessary biopsy because of this fear can be more harmful, because it may delay diagnosis and appropriate treatment if cancer is present.
Fine needle aspiration uses a very thin needle to withdraw fluid or groups of cells. It can be useful in selected situations but generally provides less tissue than a core needle biopsy. [3]
A core needle biopsy uses a hollow needle to remove several small cylinders of tissue.
The American Cancer Society describes core needle biopsy as often the preferred type of biopsy when breast cancer is suspected because it obtains more tissue than fine needle aspiration without requiring open surgery. [4]
A vacuum-assisted device can obtain multiple tissue samples through a single needle insertion and can be useful for selected imaging abnormalities.
A surgical biopsy removes part or all of an abnormal area through an incision.
Most patients who require breast biopsy can undergo a needle procedure rather than surgery. Surgical biopsy is reserved for situations in which needle sampling is not appropriate or has not provided a sufficiently clear answer. [1]
When an abnormal area cannot be reliably targeted by touch, imaging is used to guide the biopsy needle precisely to it.
| Guidance method | When it may be used |
|---|---|
| Ultrasound | When the mass or abnormality is clearly visible on ultrasound, allowing real-time needle guidance. |
| Stereotactic / mammographic guidance | Particularly useful for microcalcifications or abnormalities visible on mammography but not clearly seen on ultrasound. |
| MRI guidance | Used for abnormalities that are visible on MRI but cannot be adequately targeted with mammography or ultrasound. |
RadiologyInfo notes that stereotactic biopsy is particularly useful for small clusters of calcifications and abnormalities not visible on ultrasound, while MRI-guided biopsy is used for findings best seen on MRI. [5] [6]
Most needle breast biopsies are performed using local anaesthetic.
You may feel a brief sting when the anaesthetic is injected. Once the area is numb, pressure or movement may be more noticeable than sharp pain while samples are taken. [3]
Afterward, temporary soreness, bruising, swelling or minor bleeding at the biopsy site can occur.
A very small tissue marker or clip may be placed at the biopsy site.
Its purpose is to mark the exact area that was sampled so that it can be found on future imaging or during treatment if necessary.
The American Cancer Society notes that the marker is usually not visible or noticeable to the patient, can remain in place, is safe during MRI examinations and does not set off standard metal detectors. [4]
Tell your healthcare team about:
Follow the specific instructions given by your healthcare team.
After a needle biopsy, you may be advised to:
Bruising and mild swelling are common after core needle biopsy and can temporarily make the area appear larger. These usually improve with time. [4]
Contact the healthcare team if you develop persistent bleeding, rapidly increasing swelling, worsening pain, increasing redness or warmth, discharge from the biopsy site or fever.
There is no universal turnaround time for every breast biopsy.
The American Cancer Society notes that results typically take at least several days. Additional testing can make the final pathology report take longer. [1]
If breast cancer is identified, further tests on the tissue may include hormone receptor and HER2 testing, which can add information needed for treatment planning.
| Possible result | What it may mean |
|---|---|
| Benign | No cancer is identified; follow-up may be all that is needed if the pathology explains the imaging finding. |
| Atypical or high-risk lesion | Not necessarily cancer but may require additional assessment, surveillance or excision depending on the diagnosis. |
| In situ disease | Abnormal or malignant cells remain within the structure where they began, such as DCIS. |
| Invasive breast cancer | Cancer cells have invaded surrounding tissue and further characterisation is required to plan treatment. |
If invasive breast cancer is found, the biopsy tissue is commonly tested for estrogen receptors ER, progesterone receptors PR and HER2, among other tests when appropriate. These results can directly influence treatment choices. [7]
A benign pathology result needs to make sense in the context of the imaging and clinical examination.
Core needle biopsy provides a clear answer in most cases, but it can occasionally miss a cancer. The American Cancer Society notes that if the result is inconclusive or the doctor remains concerned, another core biopsy or a more extensive surgical biopsy may be needed. [4]
No.
BI-RADS is the standard system radiologists use to describe breast imaging findings and recommend the next step. Some categories require only routine screening, some call for short-term follow-up, while more suspicious categories are more likely to lead to a biopsy recommendation.
A breast biopsy does not mean that cancer has already been diagnosed. It is the procedure used to obtain tissue when examination and imaging cannot determine the nature of an abnormal area with enough certainty.
Most breast biopsies can be performed with a needle and local anaesthetic rather than surgery. Core needle biopsy is commonly used when breast cancer is suspected because it provides enough tissue for diagnosis and additional laboratory tests.
Current medical evidence also does not support the belief that routine breast biopsy “opens” a tumour or causes cancer to spread. The chance of biopsy causing cancer spread is extremely low.
If cancer is found, the tissue provides information beyond the diagnosis itself, including tumour type, grade, ER and PR receptor status and HER2 status. These findings help guide treatment.
If pathology is benign but does not adequately explain a suspicious imaging finding, further evaluation may still be necessary.
When you receive a mammogram report, you may see a number such as BI-RADS 1, BI-RADS 3 or BI-RADS 4. Without context, the number can sound alarming.
BI-RADS stands for Breast Imaging Reporting and Data System. Radiologists use this standardized system to describe breast imaging findings and recommend the next step, such as routine screening, additional imaging, short-term follow-up or biopsy. [1]
Most importantly, a BI-RADS category is not a breast cancer stage and is not itself a cancer diagnosis. It communicates how concerning an imaging finding appears and what should happen next. [2]
The American College of Radiology developed BI-RADS to standardize the language radiologists use when interpreting breast imaging.
The system is used for mammography, breast ultrasound and breast MRI, not mammography alone. [1]
The system helps communicate three practical pieces of information:
| Category | Meaning | Likelihood of malignancy | Typical next step |
|---|---|---|---|
| 0 | Incomplete assessment | Not assigned | Additional imaging and/or comparison with prior studies |
| 1 | Negative | No suspicious imaging finding | Routine screening as appropriate |
| 2 | Benign | Benign imaging finding | Routine screening |
| 3 | Probably benign | ≤2% | Short-interval imaging follow-up, often around six months |
| 4 | Suspicious | >2% to <95% | Tissue diagnosis/biopsy is generally recommended |
| 5 | Highly suggestive of malignancy | ≥95% | Biopsy and appropriate clinical action |
| 6 | Known biopsy-proven malignancy | Cancer has already been confirmed by tissue diagnosis | Treatment planning or response assessment |
BI-RADS 0 does not mean cancer.
It means the radiologist cannot yet assign a final category because additional information is needed. This may include extra mammographic views, magnification, spot compression, ultrasound or comparison with previous mammograms. [2]
Once the additional evaluation is completed, a final BI-RADS category is usually assigned.
BI-RADS 1 means the imaging examination is negative, with no suspicious mass, architectural distortion or suspicious calcification identified. [2]
For someone without symptoms, routine screening is generally appropriate.
However, a negative imaging assessment does not mean that a new persistent clinical symptom should be ignored. A palpable lump or other ongoing breast change should still be discussed with a clinician.
BI-RADS 2 means a finding is present but has a clearly benign imaging appearance.
Examples can include benign calcifications, cysts, lymph nodes or expected changes following a previous breast procedure. [2]
The difference between BI-RADS 1 and 2 is therefore not that category 2 is more dangerous. BI-RADS 1 is negative, while BI-RADS 2 documents a finding known to be benign.
BI-RADS 3 means probably benign.
The likelihood of cancer is no more than 2%. [1]
Rather than immediately performing a biopsy, radiologists commonly recommend short-term follow-up imaging to confirm that the finding remains stable.
The American Cancer Society notes that repeat imaging is often performed within 6 to 12 months and then periodically until the finding has remained stable for a suitable period, commonly at least two years. [2]
If the finding changes during follow-up, the BI-RADS assessment and recommended management may change.
BI-RADS 4 describes a suspicious imaging finding for which tissue diagnosis is generally recommended.
Because category 4 covers a very wide range of cancer likelihoods, it is commonly divided into three subcategories. [1]
| Category | Level of suspicion | Likelihood of malignancy |
|---|---|---|
| 4A | Low suspicion | >2% to ≤10% |
| 4B | Moderate suspicion | >10% to ≤50% |
| 4C | High suspicion | >50% to <95% |
A BI-RADS 4 result therefore does not mean that cancer has been confirmed.
In BI-RADS 4A, for example, most biopsies will not show cancer. However, the level of suspicion is high enough that tissue sampling is appropriate rather than observation alone.
BI-RADS 5 means the imaging appearance is highly suggestive of malignancy, with a likelihood of cancer of at least 95%. [1]
Biopsy is strongly recommended to confirm the diagnosis and provide tissue for further testing.
BI-RADS 6 is fundamentally different from the preceding categories.
It means that the abnormality has already been proven to be malignant by biopsy. [1]
Imaging classified as BI-RADS 6 may be used to assess a known cancer before treatment, during treatment planning or to evaluate response to neoadjuvant therapy.
BI-RADS 6 therefore does not mean “a more advanced cancer than BI-RADS 5.” It simply indicates that tissue diagnosis has already established malignancy.
Not necessarily.
BI-RADS 4 covers a broad range of probabilities, while BI-RADS 5 has a very high likelihood of malignancy. Neither category substitutes for pathology.
A biopsy may show:
If breast cancer is diagnosed, additional tests such as ER, PR and HER2 assessment may be performed on the tissue to help guide treatment.
A benign result can be reassuring, but the pathology result must also be concordant with the imaging finding.
In other words, the benign diagnosis should reasonably explain the abnormality that prompted the biopsy.
If pathology and imaging do not match, additional tissue sampling or further evaluation may be recommended.
No. The same BI-RADS assessment system is also used for breast ultrasound and breast MRI. [1]
No.
BI-RADS reporting also describes breast density using four categories labelled A through D, but these letters do not represent cancer suspicion. [2]
| Density | General meaning |
|---|---|
| A | Breasts are almost entirely fatty. |
| B | Scattered areas of fibroglandular density. |
| C | Heterogeneously dense. |
| D | Extremely dense. |
A report can therefore say:
Breast Density C + BI-RADS 1
without any contradiction. The letter describes breast density; the BI-RADS number describes the imaging assessment.
No.
BI-RADS is an imaging assessment system. Breast cancer staging—such as Stage I, II, III or IV—is determined only after cancer has been diagnosed and additional information about tumour size, lymph nodes, spread and tumour biology has been gathered.
Look at three parts of the report:
| BI-RADS | General next step |
|---|---|
| 0 | Complete the additional imaging or comparison requested. |
| 1–2 | Continue routine screening unless symptoms require separate evaluation. |
| 3 | Attend the recommended short-interval follow-up. |
| 4 | Discuss the recommended biopsy or tissue diagnosis. |
| 5 | Proceed with tissue diagnosis and appropriate clinical evaluation without unnecessary delay. |
| 6 | Continue treatment planning or response assessment for biopsy-proven cancer. |
BI-RADS 3 does not mean that a benign lesion is “turning into” cancer. It means the imaging appearance is probably benign and carries no more than a 2% likelihood of malignancy. Follow-up is used to confirm stability.
No. BI-RADS 4 means the finding is suspicious enough to justify biopsy. Many BI-RADS 4 findings—particularly category 4A—ultimately prove to be benign.
Yes, but it is uncommon. Category 5 carries at least a 95% likelihood of malignancy, which is why tissue confirmation is strongly recommended.
The number itself does not indicate how dangerous the finding is. BI-RADS 0 simply means the assessment is incomplete and more information is needed before a final category can be assigned.
Yes. Additional imaging, comparison with prior studies or follow-up can change the assessment. For example, an initial BI-RADS 0 result may become BI-RADS 1, 2, 3 or 4 after the work-up is completed.
BI-RADS turns breast imaging findings into a standardized assessment and management recommendation. It is not a breast cancer stage and does not itself diagnose cancer.
BI-RADS 0 means the assessment is incomplete; categories 1 and 2 are reassuring; category 3 is probably benign with no more than a 2% likelihood of malignancy and usually requires short-term follow-up.
BI-RADS 4 is suspicious and generally leads to biopsy, with 4A, 4B and 4C representing progressively higher levels of suspicion. BI-RADS 5 carries at least a 95% likelihood of malignancy but still requires tissue confirmation.
BI-RADS 6 is reserved for a cancer that has already been proven by biopsy.
When reading a report, do not focus only on the number. The radiologist's recommendation for the next step is just as important.

