How can i help you?
Latest Blogs
Explore All
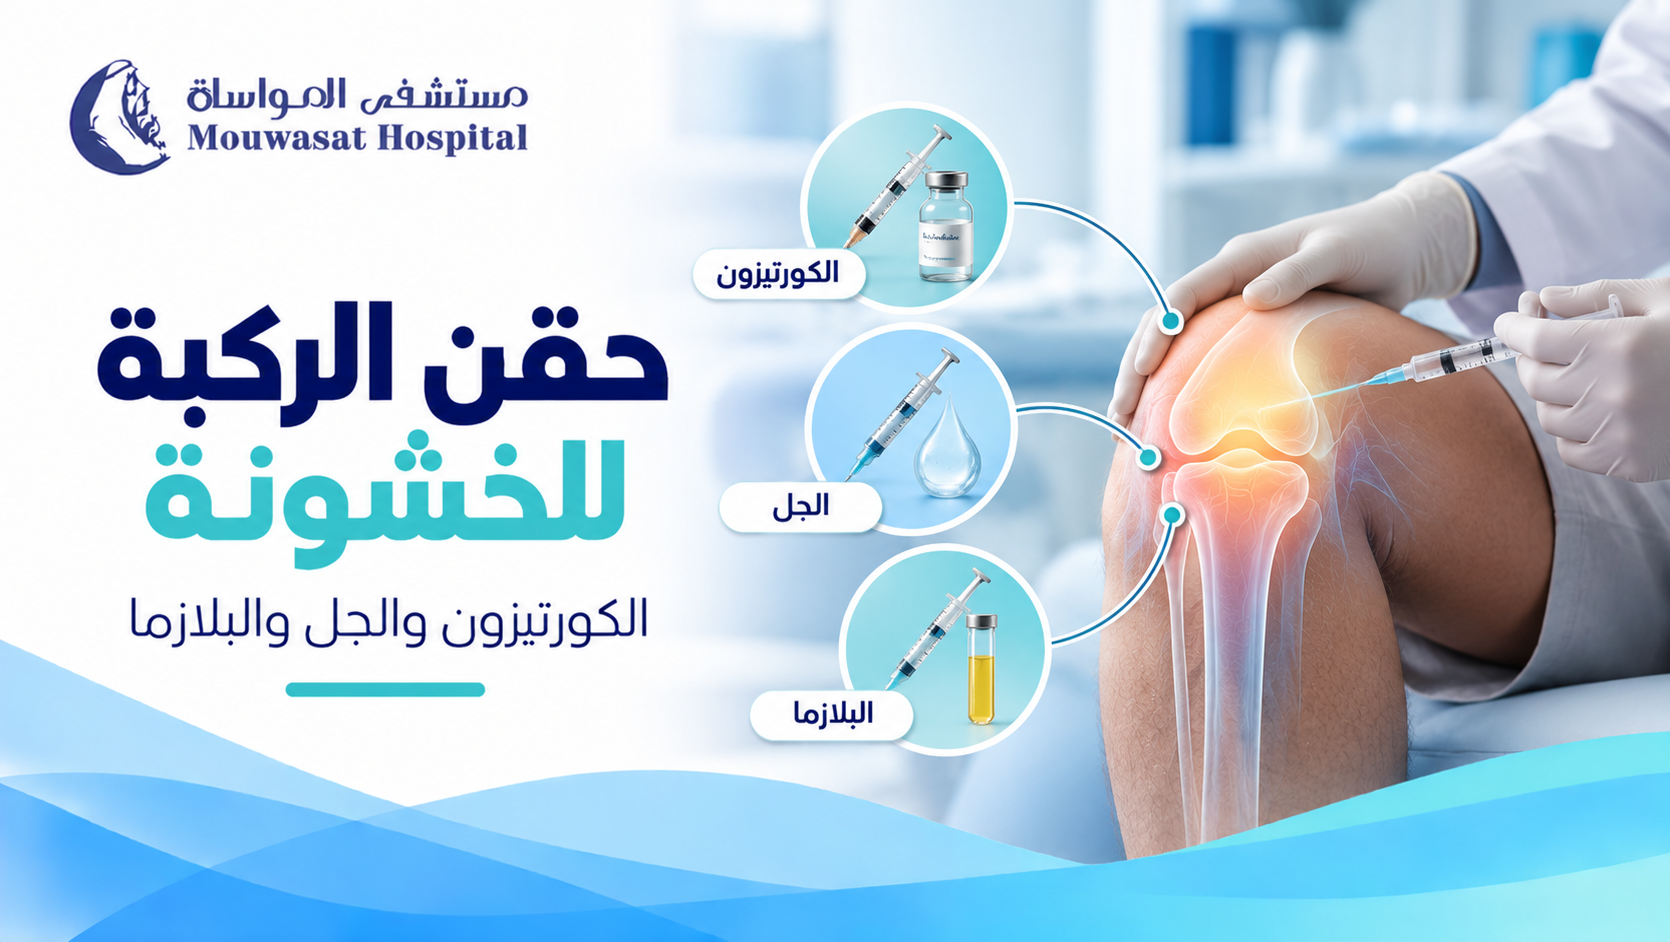


When knee osteoarthritis pain continues despite appropriate exercise, activity modification, and other treatments, your doctor may discuss an injection into the joint. But is a cortisone injection better than a gel injection? And can platelet-rich plasma (PRP) rebuild damaged knee cartilage?
Knee osteoarthritis injections differ in how they work, how well they have been studied, the benefits patients may experience, and their potential risks. Some can provide temporary symptom relief, while others are not recommended for routine use by major medical guidelines because clinically meaningful benefits remain uncertain.
This guide compares corticosteroid, hyaluronic acid, and PRP injections for knee osteoarthritis, using recommendations from NICE, AAOS, and the American College of Rheumatology (ACR). It also explains what to consider before an injection, what to expect afterward, and when another treatment approach may be more appropriate.
Seek urgent medical assessment if your knee suddenly becomes severely painful, hot, or swollen, particularly if you have a fever or feel generally unwell. Septic arthritis and other serious conditions must be considered. An elective osteoarthritis injection should not proceed in a joint where infection is suspected until the condition has been appropriately evaluated. [7]
Knee osteoarthritis is a long-term condition affecting the joint and surrounding tissues. It may cause pain, stiffness, swelling, and difficulty with walking, standing, and stair climbing.
When joint injections are used, their main purpose is generally to reduce symptoms or improve function in selected patients.
However, injections should not be presented as a guaranteed way to reverse cartilage damage, stop osteoarthritis progression, or eliminate the possibility of knee replacement surgery.
The potential value of an injection depends on the substance used, symptom severity, previous treatments, other health conditions, and the available evidence for that particular intervention.
NICE identifies individualized therapeutic exercise and weight management, when appropriate, as core treatments for osteoarthritis. Joint injections are considered separately as selected additional interventions. [1]
For a broader overview, read Knee Osteoarthritis: Does Walking Help or Make Pain Worse?.
These injections contain a corticosteroid medication, such as a glucocorticoid, that reduces inflammation.
The medication is injected into the knee joint by a suitably trained healthcare professional when it is clinically appropriate.
Intra-articular corticosteroids may temporarily reduce knee osteoarthritis pain and help some patients move more comfortably.
Short-term symptom relief may also make participation in therapeutic exercise and rehabilitation easier.
NICE recommends considering intra-articular corticosteroid injections when other pharmacological treatments are ineffective or unsuitable, or to support therapeutic exercise. [1]
Improvement may begin after several days, although the response varies between patients.
NICE explains that the expected benefit is short-term, generally lasting 2 to 10 weeks based on the evidence underlying its recommendation.
This does not mean every patient will experience relief for that long, and some may not notice meaningful improvement. [1] [5]
No. Reducing joint inflammation and pain is not equivalent to restoring damaged cartilage.
Repeated corticosteroid injections should not be viewed as a cartilage-repair treatment.
Potential adverse effects include:
There are also concerns about possible cartilage effects with repeated intra-articular corticosteroid exposure. Therefore, repeat injections should be considered individually rather than assuming that more injections will provide better or safer outcomes. [5] [6]
There is no single repeat-injection schedule suitable for every patient.
A clinician considers the previous response, time between injections, underlying medical conditions, potential risks, and the overall treatment plan.
If knee replacement is being considered in the near future, the surgeon should be informed about recent corticosteroid injections because injection timing can affect surgical planning and infection-risk considerations. [5]
Gel injections for the knee usually contain hyaluronic acid, a substance related to a component naturally present in joint fluid.
The procedure is also known as viscosupplementation.
Its purpose is to attempt to improve the lubricating and cushioning properties of joint fluid and reduce symptoms.
Although these products are sometimes informally called lubricating injections, this does not mean that they rebuild cartilage or replace the damaged joint surface.
This is an important area where widespread clinical use should not be confused with strong evidence of meaningful benefit for every patient.
These positions reflect evidence that any observed benefits have not consistently demonstrated clinically important improvements compared with control injections in the higher-quality research. [1] [2] [3]
There is no reliable evidence supporting hyaluronic acid injections as a proven way to regenerate damaged knee cartilage or guarantee that knee replacement will never be necessary.
Some patients report improvement after treatment, but an individual positive experience does not establish how much of the improvement is attributable to the injection or whether similar results can be expected in others.
Potential reactions include temporary pain, swelling, or irritation after the injection.
Some patients experience a more pronounced inflammatory reaction. As with other joint injections, infection is a possible complication.
Relevant allergies, medical conditions, and previous injection reactions should be discussed before treatment.
Platelet-rich plasma injections have attracted considerable attention as a possible treatment for joint and tendon problems.
PRP is generally prepared by collecting a sample of the patient's blood and processing it to obtain a platelet-enriched component for injection.
Platelets contain biological factors involved in natural healing processes. However, this does not establish that PRP injections can regenerate cartilage damaged by knee osteoarthritis.
Some studies have reported improvements in pain or physical function following PRP injections, while others have not demonstrated a meaningful benefit compared with placebo.
Interpreting the evidence is challenging because studies use different PRP preparation methods, platelet concentrations, white blood cell content, injection schedules, and patient populations.
Professional guidelines have evaluated the evidence differently:
Therefore, PRP should not be promoted as a consistently effective or guaranteed treatment for everyone with knee osteoarthritis. [2] [3] [4]
The RESTORE randomized controlled trial, published in JAMA, included 288 participants with mild to moderate knee osteoarthritis.
At 12 months, PRP injections did not produce a statistically significant improvement in knee pain or cartilage volume change compared with saline placebo injections.
The trial does not mean that every previous PRP study reached the same conclusion, but it provides important evidence against claiming that PRP has a guaranteed benefit or reliably restores damaged cartilage. [8]
PRP has not been reliably demonstrated to restore osteoarthritis-damaged knee cartilage to its original condition.
Claims that it permanently cures osteoarthritis, rebuilds the joint, or guarantees avoidance of surgery are not supported by the available evidence.
Temporary pain, swelling, and stiffness may occur after the injection.
The procedure also carries risks related to injecting a joint, including bleeding and infection.
The fact that PRP is prepared from a patient's own blood does not mean that the procedure is risk-free.
Some comparative studies have favored PRP over hyaluronic acid on selected measures of pain or function.
However, differences in methods, study quality, and patient selection make it inappropriate to promise superior outcomes for every patient.
Furthermore, outperforming a treatment with uncertain efficacy does not by itself prove a clinically important benefit over placebo.
Some regenerative treatments are marketed as ways to repair knee cartilage or avoid knee replacement surgery permanently.
These include certain stem cell or cell-based injections.
However, sufficiently reliable clinical evidence has not established these treatments as proven methods for restoring osteoarthritis-damaged cartilage to its original state.
The ACR strongly recommends against stem cell injections for knee osteoarthritis because of uncertainty, product heterogeneity, and a lack of standardized, high-quality evidence. [3]
A procedure being available at a clinic does not automatically establish its clinical effectiveness, suitability for an individual patient, or regulatory approval for a specific indication.
| Feature | Corticosteroid | Hyaluronic acid | PRP |
|---|---|---|---|
| Main purpose | Temporary reduction in inflammation and pain | Attempted symptom relief using a joint-fluid-related substance | Platelet-based intervention with evolving evidence |
| Established benefit | Short-term relief in selected patients | Inconsistent clinically meaningful benefit; not recommended routinely | Mixed results and differing guideline positions |
| Guideline position | May be considered in selected situations | NICE advises against offering; AAOS against routine use | AAOS: limited evidence; ACR: recommends against use |
| Cartilage regeneration | Not established | Not established | Not established |
| Important risks | Temporary glucose elevation, flare, rare infection, concerns about repetition | Pain, swelling, inflammatory reactions, rare infection | Post-injection pain, swelling, and procedure-related risks |
This table is intended to support informed discussion. It is not a tool for selecting an injection without an individualized medical assessment.
Selected injections may be discussed when pain continues to interfere with mobility, sleep, or everyday activities despite appropriate treatments, or when certain medications are unsuitable.
The decision may depend on:
Not every patient with advanced osteoarthritis benefits from injections, and mild osteoarthritis does not automatically mean that an injection is the next step.
Before undergoing a joint injection, inform the healthcare professional about relevant medical conditions, medications, and allergies.
Important information includes:
Important: Do not stop prescribed blood thinners or other medications on your own before an injection. Any changes require individualized advice because interrupting treatment may carry significant risks.
A trained healthcare professional performs the injection using an aseptic technique.
Ultrasound guidance may be used in selected situations to help place the needle accurately.
The procedure varies according to the injection type. Some injections may involve local anesthetic, while PRP requires a blood sample to be collected and processed before the platelet-rich preparation is injected.
Patients may feel a brief needle prick, pressure, or discomfort during the procedure. The experience varies between individuals.
Mild pain, fullness, or temporary irritation may occur after an injection.
Your clinician may recommend limiting strenuous knee activity for the first day or two, depending on the procedure and your circumstances.
After a corticosteroid injection, some patients experience a temporary increase in discomfort for one or two days before the medication begins to provide relief. [6]
Seek urgent assessment for severe worsening pain, marked swelling, joint warmth, redness, fever, or feeling generally unwell.
These symptoms should not automatically be dismissed as an expected injection flare because joint infection must be considered.
Breathing difficulty or swelling of the face or tongue after an injection can indicate a severe allergic reaction and requires immediate emergency assistance. [6] [7]
Many joint injections are performed without serious complications, but no invasive procedure is entirely free of risk.
Potential general complications include pain, bruising, bleeding, swelling, infection, and allergic reactions.
Some risks are treatment-specific, including temporary blood glucose elevation after corticosteroid injections.
Injections into the knee joint should also be distinguished from injections around tendons or bursae, because evidence and safety considerations may differ.
The expected benefit should be discussed alongside potential harm before treatment is selected.
Failure to improve after an injection does not mean that treatment options have been exhausted.
However, repeatedly using the same injection without reviewing the diagnosis and treatment plan may not be appropriate.
Clinical guidelines recommend individualized exercise, including strengthening and aerobic activity, as a core component of osteoarthritis care.
Explore 7 Knee Osteoarthritis Exercises to Improve Strength and Mobility, while selecting activities according to your condition and ability.
For patients who are overweight or living with obesity, sustained weight reduction may improve osteoarthritis-related pain and physical function when combined with appropriate exercise. [1]
Options may include topical anti-inflammatory medicines or selected oral medications when appropriate.
Medication choice should take account of kidney, cardiovascular, and gastrointestinal risks, as well as interactions with other treatments.
If osteoarthritis symptoms substantially affect quality of life and persist despite appropriate nonsurgical treatment, referral for a knee replacement assessment may be reasonable.
The decision is based on symptoms, physical function, individual goals, and response to treatment, not on X-ray appearance or age alone.
There is no single price for all types of knee osteoarthritis injections in Saudi Arabia.
Costs may vary according to the product or procedure used, the number of sessions, associated services, the healthcare facility, and insurance coverage and policy conditions.
Before paying for treatment, ask about the expected total cost, what is included, the likelihood of a meaningful benefit for your condition, and the available alternatives.
A higher price does not necessarily mean that an injection is more effective or that its results will last longer.
If knee osteoarthritis pain continues despite suitable rehabilitation and other treatments, or if you are considering a joint injection, an orthopedic assessment can help clarify the expected benefits and risks.
Learn about the Orthopedic Department at Mouwasat Hospital and the Physiotherapy Department, including relevant assessment and treatment services available at your preferred location.

There is no single injection that is best for everyone. Corticosteroids can provide short-term relief in selected situations. Hyaluronic acid is not recommended routinely by major guidelines, while PRP evidence and recommendations remain mixed.
No. PRP has not been shown to reliably restore damaged cartilage or permanently cure knee osteoarthritis. Results differ between studies and individual patients.
Not necessarily. Corticosteroid injections have evidence supporting short-term symptom relief, while major guidelines do not support routine hyaluronic acid use because consistent clinically meaningful benefits have not been established.
Improvement may begin within several days, although a temporary pain flare may occur first. NICE describes the expected relief as short-term, generally around 2 to 10 weeks.
There are concerns about the effects of repeated corticosteroid injections on cartilage. Each injection and any repeat treatment should therefore be considered in the context of potential benefits and risks.
Some injection options may be appropriate depending on the patient's condition. Corticosteroids can temporarily raise blood glucose, so suitable monitoring should be discussed before treatment.
Some discomfort may occur during or after the injection, and temporary swelling or stiffness is possible. Individual experiences vary.
No. An individual may experience meaningful improvement, but testimonials cannot establish treatment effectiveness across different patients. Controlled clinical studies provide more reliable evidence.
More injections do not necessarily produce better results. The diagnosis, expected benefit, risks, and evidence should be reviewed before any repeat procedure is considered.
No. Appropriate exercise remains a core component of knee osteoarthritis care. Even when a corticosteroid injection is used, one aim may be to make therapeutic exercise more tolerable.
None of the injection types discussed has been proven to guarantee avoidance of knee replacement. Some patients experience symptom relief, but the need for surgery depends on their overall clinical condition and response to treatment.
Severe worsening pain, pronounced swelling, a hot or red joint, fever, or feeling unwell after an injection requires urgent medical evaluation to exclude infection or another significant complication.
Knee osteoarthritis injections differ substantially in their evidence, expected benefits, and risks.
Corticosteroids may provide short-term symptom relief for selected patients. Major guidelines do not support routine use of hyaluronic acid injections, while PRP remains an area of differing recommendations and uncertain clinical benefit.
None of these injections should be presented as a proven method for regenerating damaged cartilage or guaranteeing that surgery will not be needed.
The most appropriate decision comes from an individualized assessment, realistic expectations, and a clear discussion of benefits, risks, costs, and alternatives.
Therapeutic exercise and weight management, when appropriate, remain essential parts of treatment.
Learn more about Orthopedic Care and Physiotherapy at Mouwasat Hospital.
Medical disclaimer: This article is intended for general health education and does not replace individualized medical assessment. Do not choose a treatment based solely on advertisements or another patient's experience, and seek urgent care for symptoms suggesting joint infection or another serious complication.
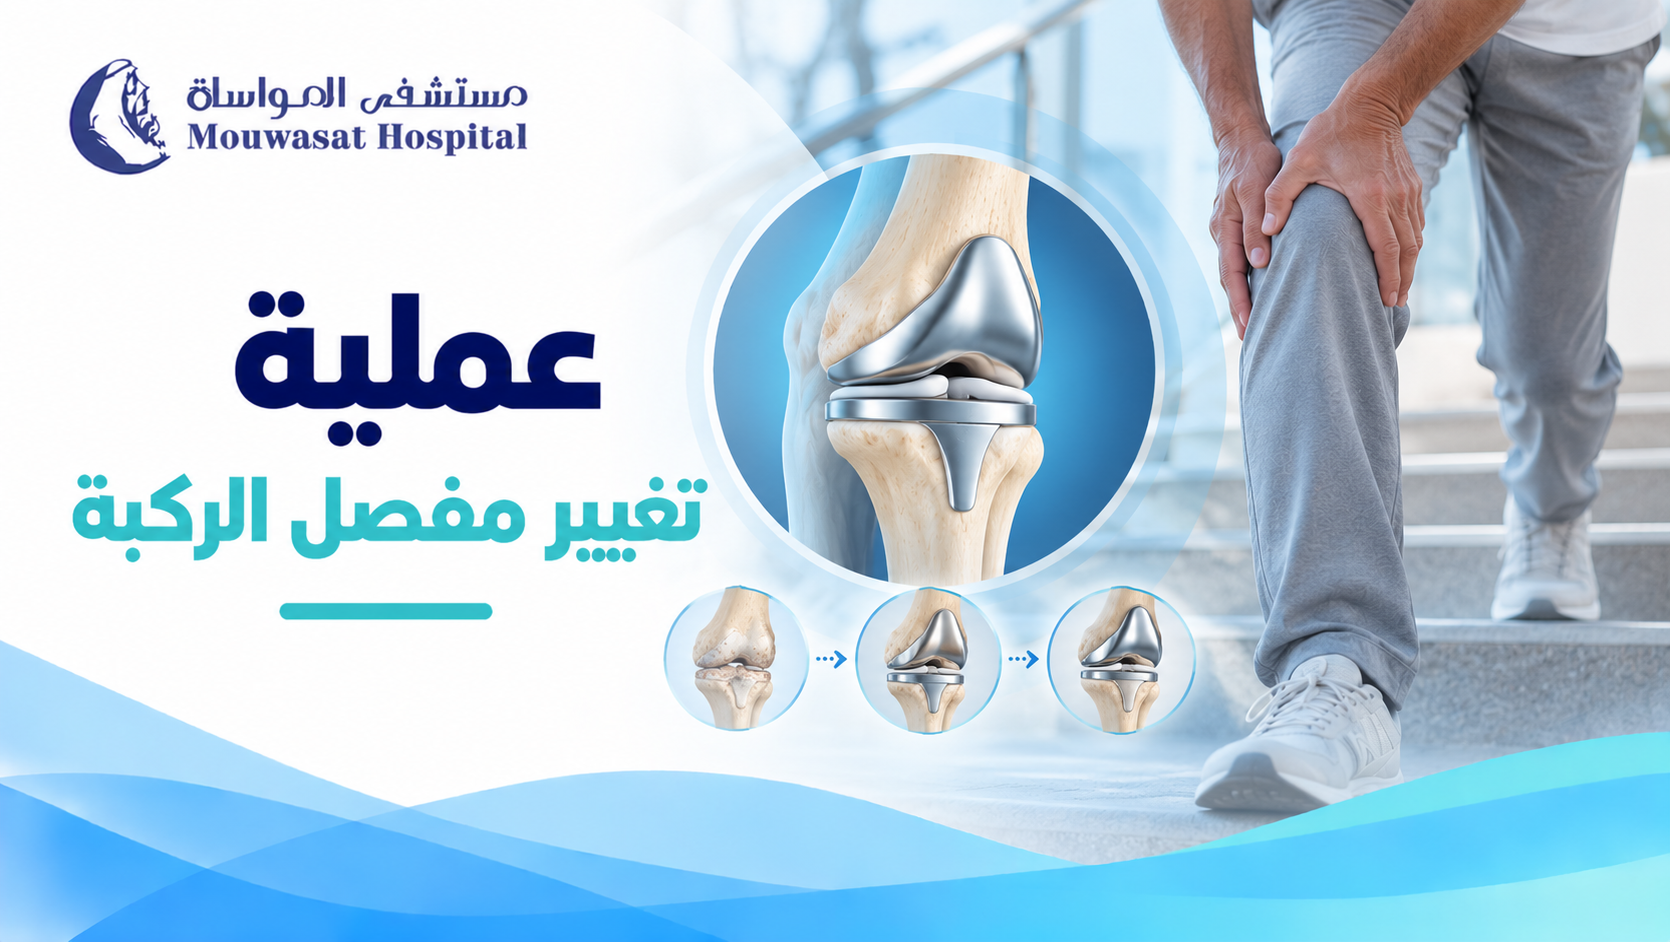
When knee osteoarthritis pain makes walking, climbing stairs, sleeping, or performing everyday activities difficult, and nonsurgical treatments no longer provide enough relief, knee replacement surgery may become an option.
But does severe pain automatically mean you need surgery? What is the difference between a total and partial knee replacement? How long will it take to walk comfortably, return to work, and resume your normal routine?
Knee replacement surgery, also known as knee arthroplasty, replaces damaged joint surfaces with artificial components designed to reduce pain and improve movement and function.
This guide explains when surgery may be appropriate, the available procedures, robotic-assisted knee replacement, how to prepare, what happens during the operation, the recovery timeline, potential complications, and important questions to discuss with your orthopedic surgeon.
Seek urgent medical assessment for increasing pain, warmth, redness, wound drainage, or fever after knee replacement, as these may indicate infection. New calf pain or swelling requires urgent assessment for a possible blood clot. Sudden breathlessness or chest pain requires immediate emergency assistance. [9]
Knee replacement is an orthopedic procedure in which damaged cartilage surfaces and small amounts of underlying bone are removed and replaced with artificial components.
The implants typically include metal and specialized medical-grade plastic components, designed to create new joint surfaces and support movement.
Although the procedure is commonly called knee replacement, the surgeon does not remove the entire knee. Instead, the damaged joint surfaces are replaced or resurfaced. [2]
The primary goal is to reduce pain caused by significant joint damage and improve everyday activities such as walking, standing, stair climbing, and getting out of a chair.
Surgery may also help correct certain deformities associated with advanced joint damage.
However, knee replacement cannot guarantee that the joint will feel exactly as it did before arthritis, and some patients may continue to experience pain or stiffness afterward.
The decision is based on more than the diagnosis of osteoarthritis. The impact of symptoms on everyday life and the response to appropriate nonsurgical treatments are especially important.
NICE recommends considering referral for joint replacement when pain, stiffness, reduced function, or progressive deformity substantially affects quality of life and nonsurgical treatments are ineffective or unsuitable. [1]
These findings do not mean that surgery is inevitable, but they are reasonable reasons to discuss the options with an orthopedic specialist. [2]
Not necessarily. Appropriate nonsurgical management is important, but every patient does not need to undergo every available injection or medication before surgery can be considered.
The 2023 ACR/AAHKS guideline conditionally recommends against routinely delaying surgery for additional nonsurgical treatments in patients who already have symptomatic and radiographically moderate-to-severe osteoarthritis, have not benefited sufficiently from appropriate nonsurgical treatment, and have chosen to proceed with joint replacement.
This recommendation applies to a specific patient group and should not be interpreted as advice to skip appropriate nonsurgical care in early osteoarthritis. [11]
No. Advanced X-ray changes can support the clinical assessment, but they do not independently determine whether knee replacement is necessary.
One patient may have substantial radiographic changes but relatively manageable symptoms, while another may experience severe limitations in daily life.
The decision should therefore consider symptoms, physical examination, relevant imaging, previous treatments, patient preferences, and realistic treatment goals.
Age alone should not exclude someone from being assessed for knee replacement. Body mass index (BMI) alone should not automatically prevent referral either.
However, age, weight, smoking, medical conditions, and other health factors may influence individual surgical risks and the preparation needed before an operation. [1]
Total knee replacement, or total knee arthroplasty (TKA), is the most common knee replacement procedure.
It involves resurfacing the main joint surfaces between the thighbone and shinbone with artificial components. The underside of the kneecap may also be treated, depending on the surgical plan.
It may be appropriate when damage affects multiple joint compartments or when a partial replacement would not meet the patient's needs.
Partial knee replacement, also known as unicompartmental knee replacement, involves replacing the damaged surfaces within one compartment while preserving suitable unaffected structures.
It requires specific anatomical and functional conditions, including assessment of the remaining joint surfaces and ligaments.
Recovery may be faster for selected patients, but partial replacement is not suitable for everyone and may require revision surgery in the future.
NICE recommends offering a choice between partial and total replacement for suitable patients with isolated medial compartment osteoarthritis and discussing the benefits and risks of both approaches. [4] [5]
| Feature | Total replacement | Partial replacement |
|---|---|---|
| Extent of replacement | Main joint surfaces | One affected compartment |
| Typical suitability | May suit damage involving multiple compartments | Requires specific joint and ligament conditions |
| Recovery | May take several months | May be faster in selected patients |
| Procedure selection | Based on damage, stability, and functional goals | Based on the condition of remaining joint structures |
Some orthopedic centers use robotic-assisted systems to support surgical planning and precise positioning of knee replacement components.
Robotic assistance does not mean the robot operates independently. The procedure remains controlled by the surgical team, with the level and type of assistance varying between systems.
NICE guidance on robotic-assisted orthopedic procedures indicates that these systems can improve the precision of implant alignment and positioning.
However, available comparative evidence has not consistently demonstrated better overall patient-reported outcomes or lower complication rates than conventional surgery. Longer-term evidence continues to develop. [12]
Therefore, the choice should not be based on the word "robotic" alone. The surgeon's expertise, patient characteristics, proposed procedure, and expected benefits and risks are also important.
Preparation can help identify risks and improve your ability to participate in postoperative rehabilitation.
Your healthcare team may review your medical history, current medications, and overall health, and perform appropriate examinations, X-rays, blood tests, or an electrocardiogram when indicated.
Patients with conditions such as diabetes, heart disease, or kidney disease may require additional assessment. [2] [6]
Your doctor may recommend improving blood glucose control, stopping smoking, addressing active infections, and optimizing nutrition and appropriate physical activity before surgery.
These decisions should be individualized rather than using age or BMI alone as an automatic reason to exclude someone from surgical assessment.
Tell your surgeon about all medications, particularly anticoagulants, anti-inflammatory medicines, and diabetes treatments, as well as recent injections into the affected knee.
Do not stop prescribed medication without medical instructions. Your surgeon and anesthesia team will advise whether changes are needed.
NHS guidance emphasizes practical home preparation, arranging support, and planning for temporary limitations in driving and working. [6]
Knee replacement takes place in a hospital under general anesthesia, spinal anesthesia, or other appropriate regional anesthesia techniques, depending on the individual's circumstances.
The operation commonly takes approximately 1 to 2 hours, although total time in the operating area may be longer and complex procedures may require additional time. [5]
Specific steps differ between total and partial replacement and according to the selected surgical technique. [2] [5]
Full recovery can take several months or longer. The timeline varies according to age, overall health, preoperative muscle strength, the type of procedure, and any postoperative complications.
Recovery after partial knee replacement may be shorter than after total replacement for suitable patients. [7]
Healthcare professionals generally help patients begin standing and walking early, when medically safe, using a walker or crutches initially.
Pain management, blood clot prevention, and early functional rehabilitation are important during this stage.
Some selected patients may go home on the day of surgery, while others remain in the hospital for several days according to recovery and mobility needs.
Recovery focuses on wound care, swelling management, safe walking, and gradually improving knee bending and straightening under the rehabilitation plan.
Pain, swelling, and sleep difficulties can still occur, but recovery should generally show gradual progress rather than continued deterioration.
Walking, standing from a chair, and other daily activities may become easier.
Some patients gradually move to less supportive walking aids as strength and balance improve.
Reaching six weeks does not automatically mean every patient is ready to walk unaided or resume driving.
Many patients regain greater independence, and some may return to work, particularly if their job is not physically demanding.
Work involving heavy lifting, prolonged standing, or repetitive movement may require a longer recovery period.
Muscle strength, movement, and physical endurance may continue to improve over subsequent months.
Early discomfort or limited movement should not be used alone to judge the final result of surgery.
| Stage | What to expect | Main priority |
|---|---|---|
| First day and following days | Monitoring, pain control, and assisted mobilization | Safety and complication prevention |
| First two weeks | Wound care, prescribed exercises, and gradual walking | Managing swelling and restoring movement |
| Weeks 3–6 | Gradual improvement in mobility and independence | Strength, balance, and everyday function |
| Weeks 6–12 | Return to some work and daily activities | Increasing activity when appropriate |
| Several months and beyond | Continued gains in strength and endurance | Sustainable return to daily life |
Important: This timeline is illustrative rather than a fixed rehabilitation prescription. Your surgeon and physiotherapist should guide weight-bearing, exercises, walking aids, driving, and returning to work. [7] [13]
Physiotherapy plays an important role in restoring mobility, muscle strength, balance, and safe walking after knee replacement surgery.
Depending on the individual's condition, rehabilitation may focus on:
No single exercise program or fixed repetition schedule is appropriate for every patient after knee replacement.
AAOS emphasizes regular, individualized rehabilitation and a gradual return to daily activities as important parts of recovery. [8]
Explore the Physiotherapy Department at Mouwasat Hospital, which includes rehabilitation after orthopedic procedures and joint replacement.
Precautions depend on the procedure and surgeon's instructions. The following points are general guidance, not universal restrictions for every patient.
Your doctor may prescribe anticoagulant medication, compression devices, or other measures according to your individual risk.
Follow the prescribed plan and do not change medications without medical advice.
Use walking aids when needed and keep your environment free of trip hazards.
Avoid rapid twisting or unstable movements when your knee strength and balance are still recovering.
Prolonged positioning with the knee flexed may make it harder to regain full knee extension.
Follow your rehabilitation team's instructions for safe resting positions and leg elevation.
NHS guidance generally advises waiting at least six weeks after total knee replacement, or three weeks after partial replacement, before driving, with confirmation that it is medically safe.
These are general guidelines rather than automatic clearance. Recovery, the operated leg, medications, driving ability, and local legal requirements should all be considered. [7]
Low-impact activities such as walking, stationary cycling, and swimming after wound healing and medical clearance may help maintain fitness.
High-impact activities such as running or jumping may place excessive demands on the artificial joint and should be discussed with your surgeon. [13]
Knee replacement can substantially improve pain and everyday function for many patients, but individual results vary.
It is important to distinguish three different outcomes:
Implant survival should not be presented as a measure of surgical success or patient satisfaction.
A systematic review and meta-analysis published in The Lancet in 2019 estimated that approximately 82% of total knee replacements lasted 25 years without revision, based on pooled joint registry data.
This is a population-level estimate, not a guarantee for any individual patient. Implant longevity can vary with age, activity, implant design, health conditions, and other factors. [10]
Yes. Some patients eventually require revision knee replacement because of implant loosening, wear, infection, instability, or other complications.
However, revision surgery is not inevitable, and new or worsening pain should be properly investigated rather than automatically attributed to implant failure.
Most patients do not experience serious complications, but knee replacement is major surgery and its risks must be understood before making a decision.
Infections may involve the skin wound or deeper tissues surrounding the implant.
A deep prosthetic joint infection can require specialized treatment and sometimes additional surgery.
Blood clots can develop in the leg veins after surgery.
Occasionally, a clot may travel to the lungs and cause a serious pulmonary embolism. This is why postoperative clot-prevention measures are important.
Some patients experience reduced movement or persistent discomfort despite an otherwise technically successful replacement.
Appropriate rehabilitation may help, but certain cases require further evaluation or treatment.
The components may wear or loosen over time, and selected patients may eventually require revision surgery.
These complications are uncommon but should be discussed according to the patient's health and the planned procedure. [2] [9]
Some pain and swelling are expected during early recovery. However, symptoms that progressively worsen, particularly with fever, increasing redness, or wound drainage, need prompt medical assessment.
New calf pain or swelling requires urgent assessment for possible DVT. Sudden breathlessness, chest pain, or fainting requires immediate emergency assistance.
The cost of knee replacement in Saudi Arabia varies according to the procedure, implant type, medical complexity, hospital, length of stay, and associated services.
Insurance coverage and prior authorization requirements may also affect the amount paid by the patient.
Before proceeding, it is useful to ask whether the estimated cost includes:
A higher price alone does not establish that a technique or implant will produce better results for an individual patient.
If knee pain, stiffness, and difficulty moving are substantially affecting your daily life despite appropriate treatment, an orthopedic assessment may help determine whether total or partial knee replacement is suitable.
Learn about the Orthopedic Department at Mouwasat Hospital and the Physiotherapy and Rehabilitation Department, including postoperative rehabilitation services available at your preferred hospital location.
It may be considered when symptoms significantly affect daily life and appropriate nonsurgical treatments have not provided enough improvement or are unsuitable. The decision should be made jointly by the patient and orthopedic surgeon.
It is major surgery with potential risks, including infection, blood clots, and stiffness. However, most patients do not experience serious complications. Individual risks vary with health and other factors.
Most patients experience meaningful improvement in pain and function, but no single percentage captures every aspect of success. Implant survival must not be confused with patient satisfaction or complete pain relief.
Many patients begin standing and walking with assistance soon after surgery when medically safe. Progress depends on the procedure, strength, balance, and overall health.
Walking and daily activities can improve gradually over the first several weeks, but full recovery may take several months or longer. There is no single timetable for everyone.
Some patients return within approximately 6 to 12 weeks, but physically demanding jobs may require more time. Your healthcare team should assess readiness based on your work requirements and recovery.
Movement often improves with recovery and rehabilitation, but final range of motion varies. It may depend on preoperative stiffness, health, and postoperative complications.
Artificial knees can last many years, but lifetime durability is not guaranteed. Registry-based research has estimated that approximately 82% of total knee replacements last 25 years without revision.
It may improve the precision of implant alignment, but current evidence does not establish consistently superior clinical outcomes compared with conventional surgery. The most suitable approach depends on the patient and surgical team.
Simultaneous bilateral knee replacement may be considered in selected patients. However, it has different risks and recovery requirements from replacing one knee and is not suitable for everyone.
These activities may remain difficult or uncomfortable for some patients. The ability to perform them depends on motion, strength, implant characteristics, and recovery. Do not attempt kneeling or substantial pressure on the operated knee without your surgeon's clearance.
NHS guidance generally advises waiting at least six weeks after total replacement and three weeks after partial replacement. Medical clearance, safe vehicle control, and freedom from medication-related impairment are essential.
Complications such as infection, loosening, stiffness, or persistent pain can occur, and some patients require revision surgery. However, failure is not the expected outcome for most patients.
It may be suitable for selected older adults. Age alone should not automatically exclude someone from surgical assessment. The decision depends on overall health, functional limitations, and the expected benefits and risks.
Knee replacement can help many people whose advanced osteoarthritis significantly limits everyday activities and has not responded adequately to appropriate nonsurgical treatment.
But a good outcome involves more than the operation itself. Selecting the right patient, discussing realistic expectations, preparing medically, and participating in rehabilitation are all important parts of care.
If you are wondering whether your knee osteoarthritis has reached the stage where joint replacement should be considered, an orthopedic assessment can help clarify your options.
Learn more about Orthopedic Care and Physiotherapy at Mouwasat Hospital.
Medical disclaimer: This article is intended for general health education and does not replace an individualized surgical assessment or treatment instructions. Surgical suitability, recovery, and precautions vary between patients. Seek urgent care for signs of infection, blood clots, or sudden breathing difficulties after surgery.
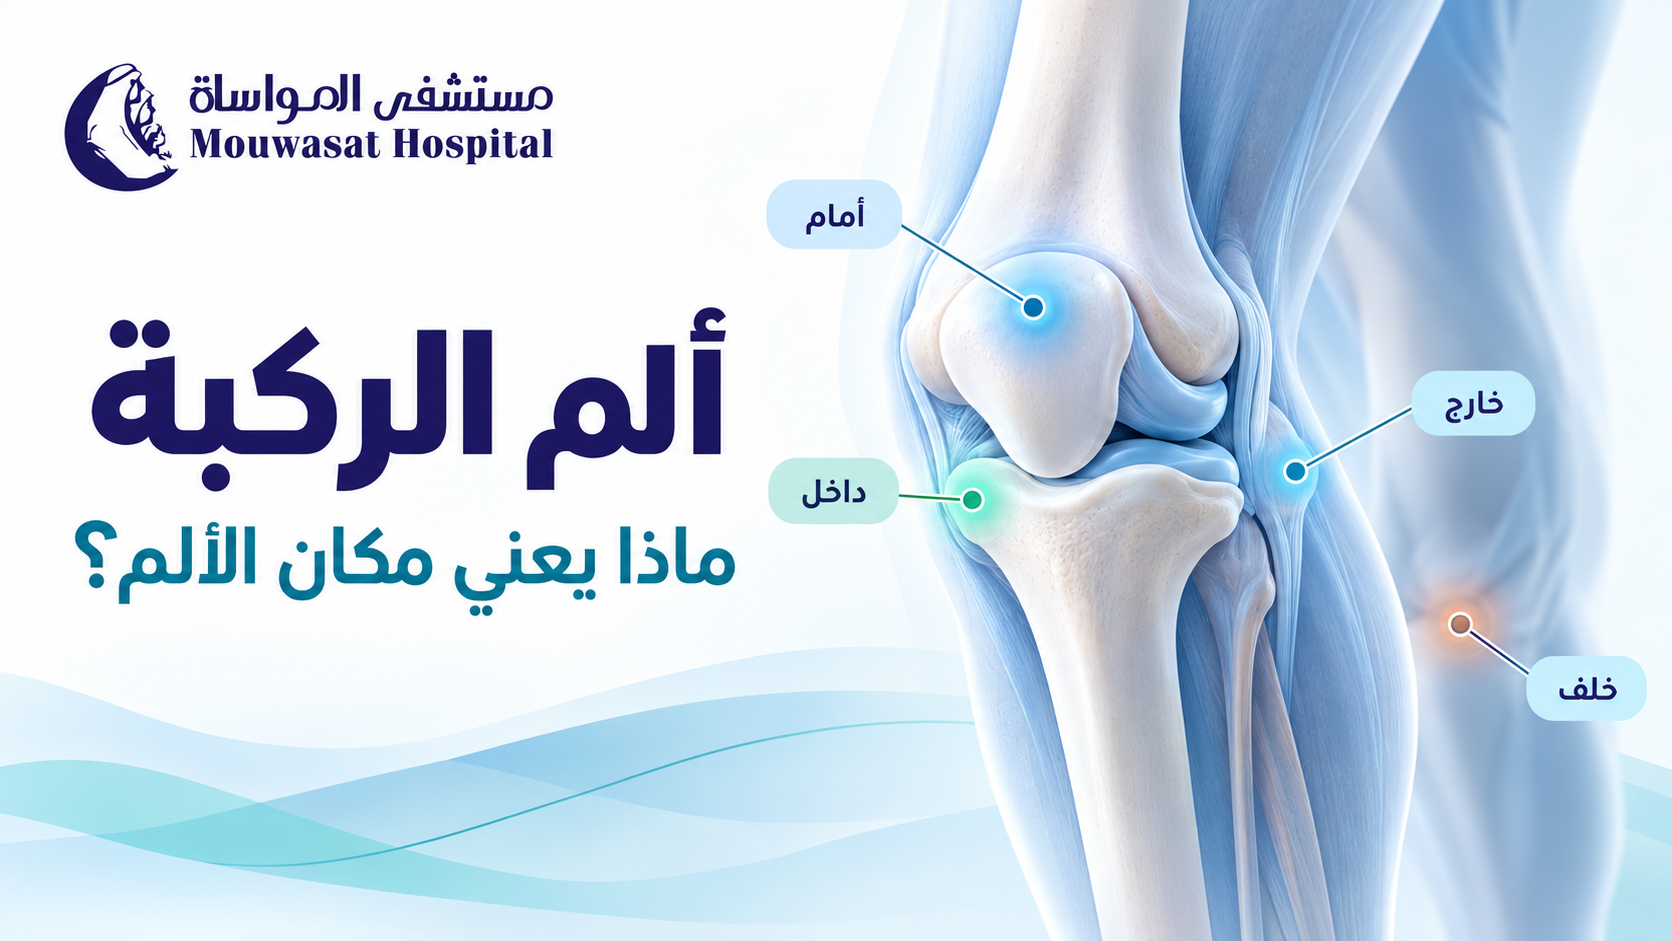
Do you experience pain at the front of your knee when climbing stairs, discomfort along the inner side of the joint, or tightness behind your knee when bending it? The location of knee pain can offer useful clues about possible causes, but location alone cannot establish a diagnosis.
Knee pain may result from osteoarthritis, meniscal or ligament injuries, patellofemoral pain, tendon disorders, or inflammation involving tissues around the joint. Different conditions may cause overlapping symptoms while requiring different treatment approaches. [1]
This guide explains the possible causes of knee pain by location, why pain may worsen when climbing stairs or bending the knee, how sudden pain differs from gradually developing symptoms, and when medical or emergency assessment is necessary.
If your knee suddenly becomes severely painful, swollen, hot, or red, especially when accompanied by fever or feeling generally unwell, seek urgent medical assessment. Septic arthritis and other acute conditions may need to be excluded. Joint infection can also occur without fever. [10]
New, unexplained pain or swelling in one leg, particularly in the calf, may require urgent assessment for deep vein thrombosis (DVT). If leg pain or swelling is accompanied by sudden breathlessness, chest pain, or fainting, call emergency services immediately because a pulmonary embolism is possible. [9]
The knee is a complex joint consisting of bones, cartilage, ligaments, tendons, muscles, bursae, nerves, and blood vessels.
Pain may originate from structures inside or around the joint. In some cases, pain perceived around the knee may even be related to a problem elsewhere, such as the hip.
Identifying the painful area can help guide a clinical examination, but it cannot independently confirm a specific condition. Different problems may cause pain in similar locations, and pain from one condition may spread across more than one area. [1]
A healthcare professional may ask:
These details, together with examination findings, help determine whether imaging or other investigations are necessary.
Anterior knee pain is common and may be felt around or behind the kneecap, particularly during activities involving repeated knee bending under load.
Patellofemoral pain syndrome (PFPS) is a possible cause of discomfort around or behind the patella, commonly called the kneecap.
Symptoms may develop gradually and become more noticeable during:
The American Academy of Orthopaedic Surgeons (AAOS) explains that patellofemoral pain can affect athletes and nonathletes. Initial management commonly involves activity modification and an appropriate therapeutic exercise program. [3]
Important: Patellofemoral pain syndrome is not synonymous with knee osteoarthritis, and it does not automatically mean that cartilage beneath the kneecap is worn away.
Osteoarthritis may affect the joint between the kneecap and thighbone.
This can cause anterior knee pain when climbing stairs, rising from a chair, kneeling, or bending the knee.
Stiffness or a grinding sensation may also occur. However, these symptoms alone cannot confirm osteoarthritis or establish its severity. [8]
For a detailed explanation of osteoarthritis symptoms, diagnosis, and treatment, read Knee Osteoarthritis: Does Walking Help or Make Pain Worse?.
Bursae are small, fluid-filled sacs that reduce friction between tissues.
Irritation or inflammation of a bursa around the knee may cause localized pain, swelling, warmth, or tenderness, particularly after repeated kneeling or pressure.
However, an infected bursa can also cause pain, swelling, and redness. Fever or other signs of infection require medical assessment rather than assuming the problem is uncomplicated bursitis. [11]
Pain directly below the kneecap may originate from the patellar tendon, which connects the kneecap to the shinbone and helps transmit forces involved in straightening the knee.
Patellar tendinopathy can develop in association with repeated loading, particularly activities involving jumping, running, and forceful knee extension.
Symptoms often include tenderness and pain just below the kneecap, sometimes worsening during physical activity.
Although commonly associated with jumping sports, the condition can also affect people who do not participate in these activities. [5]
Not all pain below the kneecap is caused by patellar tendinopathy. Other conditions may require consideration, particularly in children and adolescents or after a recent injury.
Medial knee pain refers to discomfort on the side closest to the opposite leg.
Possible sources include the meniscus, collateral ligament, joint surfaces, tendons, and bursae.
The menisci are cartilage structures that help distribute load within the knee joint.
Meniscal injury may occur after twisting the knee while bearing weight, while degenerative changes can also develop over time.
Symptoms may include:
Inner knee pain alone does not establish a meniscal tear. In addition, some changes seen on imaging may not be the primary cause of a person's current symptoms. [7]
The medial collateral ligament (MCL) supports the inner side of the knee.
It may be injured during sports or when a force places excessive stress on the inner-side ligament structures.
Symptoms can include medial knee pain, tenderness, swelling, or a feeling of instability, depending on injury severity.
Osteoarthritis may predominantly affect the inner compartment of the knee joint.
Pain may increase with walking, prolonged standing, and stair use, sometimes accompanied by stiffness after rest.
However, the painful location does not establish an osteoarthritis diagnosis or radiographic grade. A clinician considers symptoms, physical examination, and investigations when appropriate. [8]
Pes anserine bursitis involves irritation of a bursa located on the inner side of the upper shin, slightly below the knee joint.
It may cause localized tenderness and pain, sometimes associated with overuse or underlying joint conditions.
Examination is needed to distinguish it from meniscal, ligament, or osteoarthritis-related pain. [11]
Lateral knee pain occurs on the side farthest from the opposite leg.
Several structures may contribute to discomfort in this region, including the iliotibial band, lateral collateral ligament, and lateral meniscus.
The iliotibial (IT) band is a thick band of connective tissue running along the outside of the thigh toward the knee.
Repetitive loading or sudden increases in training may contribute to irritation around the outer knee, particularly in some runners and cyclists.
Symptoms often include activity-related lateral knee discomfort, sometimes accompanied by tenderness or a burning sensation.
Management commonly involves activity modification, gradual rehabilitation, and evaluation for other possible causes. [4]
The lateral collateral ligament (LCL) helps stabilize the outer side of the knee.
An injury may cause localized pain, swelling, tenderness, or instability, especially after trauma that places abnormal stress on the joint.
Assessment is important when the knee feels unstable or weight-bearing becomes difficult.
A lateral meniscus problem may cause pain along the outer joint line, particularly after twisting movements.
Symptoms such as catching, restricted movement, or swelling may occur, but isolated knee clicking is not sufficient to diagnose a meniscal injury. [7]
Posterior knee pain may arise from joint-related conditions or tissues behind the knee.
Some people describe tightness, fullness, or discomfort when bending or straightening the joint.
A Baker's cyst, also called a popliteal cyst, is a fluid-filled swelling that develops behind the knee.
In adults, it may occur alongside osteoarthritis, meniscal injury, or inflammatory joint conditions.
Possible symptoms include:
Some Baker's cysts cause few or no symptoms. A new lump behind the knee should be assessed to confirm its nature. [6]
Overuse, strain, or injury involving nearby muscles and tendons may contribute to posterior knee pain.
However, pain behind the knee should not automatically be attributed to a muscle problem, particularly when significant leg swelling occurs.
Deep vein thrombosis (DVT) is a blood clot within a deep vein, often affecting the leg.
Symptoms may include new pain and swelling in one leg, particularly the calf or thigh, sometimes with warmth or skin color changes.
DVT is not the cause of most posterior knee pain, but it requires urgent assessment when suspected.
A ruptured Baker's cyst may produce symptoms that resemble DVT, and clinical assessment with appropriate testing may be necessary to distinguish them. [6] [9]
Emergency warning: Sudden breathlessness, chest pain, or fainting alongside symptoms suggestive of DVT requires immediate emergency medical assistance.
The table below provides examples of possible explanations and should not be used for self-diagnosis.
| Pain location | Possible causes | Associated clues |
|---|---|---|
| Front of the knee or around the kneecap | Patellofemoral pain, osteoarthritis, bursitis | Pain during stairs, squatting, or prolonged sitting |
| Below the kneecap | Patellar tendinopathy and other overuse conditions | Localized tenderness with jumping, running, or tendon loading |
| Inner knee | Medial meniscus or MCL injury, osteoarthritis, pes anserine bursitis | Pain after twisting, activity-related pain, or tenderness below the joint |
| Outer knee | IT band syndrome, LCL injury, lateral meniscus injury | Pain with repetitive running or following an injury or twisting movement |
| Behind the knee | Baker's cyst, tendon or muscle conditions, other causes requiring assessment | Fullness behind the knee; sudden calf swelling needs urgent assessment |
Remember: Pain can spread or change location over time. The table cannot establish a diagnosis or reliably exclude serious conditions.
Stair climbing involves knee bending, muscle control, and joint loading that differ from walking on level ground.
As a result, several knee conditions may become more painful during stair use.
No. Osteoarthritis is one possible cause, but patellofemoral pain is also commonly associated with stair-related discomfort, particularly when the pain is felt around or behind the kneecap.
Pain may also be related to tendon disorders, previous injuries, or other mechanical problems. [3]
Descending stairs places different demands on muscle control and joint loading compared with ascending.
Some people therefore experience more discomfort while going downstairs.
However, this difference does not reliably distinguish patellofemoral pain from osteoarthritis or another knee condition.
No single stair-climbing technique is appropriate for everyone, particularly following an acute injury or when balance is impaired.
Pain when bending the knee or rising from a chair may occur with patellofemoral pain, osteoarthritis, meniscal problems, or other conditions.
Anterior knee pain after prolonged sitting with the knees bent is one recognized feature of patellofemoral pain syndrome. [3]
However, accompanying stiffness, swelling, or other symptoms may suggest that additional conditions need consideration.
Difficulty fully straightening the knee, particularly following a twisting injury, may indicate a mechanical problem within the joint.
True locking, in which the knee becomes physically unable to move through its normal range, is different from simple stiffness or clicking.
Sudden locking, especially after injury or with severe pain, warrants prompt assessment. [7]
How pain begins can provide important information about possible causes.
Gradual symptoms may occur with repetitive loading, osteoarthritis, patellofemoral pain, and certain tendon conditions.
However, a gradual onset does not establish a diagnosis, and chronic pain can still require professional evaluation.
Sudden pain after twisting, falling, or direct impact may indicate injury to a ligament, meniscus, bone, tendon, or another structure.
Urgent assessment is needed when the injury is accompanied by obvious deformity, rapid significant swelling, severe pain, or inability to bear weight. [1] [2]
Acute inflammatory conditions, gout, septic arthritis, and other problems may cause sudden severe knee pain even without trauma.
A newly hot, swollen, and severely painful joint requires urgent medical assessment to exclude infection, even if fever is absent. [10]
Most cases of knee pain are not emergencies. However, certain symptoms may indicate a serious injury, joint infection, or vascular condition.
| Warning sign | Recommended response |
|---|---|
| Sudden severe pain with a hot, swollen joint, with or without fever | Urgent same-day assessment to exclude joint infection. |
| Obvious deformity, severe traumatic pain, or inability to bear weight | Attend an emergency department. |
| Sudden inability to straighten or move the knee normally after injury | Prompt assessment for a possible internal knee injury. |
| New unexplained pain or swelling in one leg, particularly the calf | Urgent assessment to exclude deep vein thrombosis. |
| Leg pain or swelling with sudden breathlessness, chest pain, or fainting | Call emergency services immediately because pulmonary embolism is possible. |
These warning signs are based on NHS guidance for knee pain, septic arthritis, and deep vein thrombosis. [2] [9] [10]
When pain is persistent, recurring, or significantly affecting walking, sleep, or everyday activities without emergency features, arranging a medical appointment is preferable to repeatedly using pain medication without understanding the cause.
Diagnosis usually begins with a medical history and physical examination.
Knee pain does not automatically mean that an MRI or other imaging test is needed.
The clinician may ask about the pain location, onset, aggravating activities, previous injuries, swelling, stiffness, locking, and instability.
Relevant medical conditions and medications may also be reviewed.
Physical examination may include assessing movement, tenderness, swelling, muscle strength, joint stability, alignment, and walking.
The clinician may also examine the hip, calf, or circulation when symptoms suggest another possible source.
X-rays may be useful when a fracture, bone abnormality, or certain joint changes are suspected.
However, NICE recommends against routine imaging for typical osteoarthritis unless atypical features or another possible diagnosis warrant further investigation. [8]
An MRI may be considered when certain ligament, meniscal, or soft-tissue injuries are suspected, particularly if the results are likely to influence clinical management.
MRI is not routinely necessary for every patient with knee pain.
Ultrasound may help assess a lump behind the knee or other soft-tissue conditions. Vascular ultrasound may be needed when DVT is suspected.
Blood tests or joint fluid sampling may be required when infection or inflammatory joint disease is suspected. [6] [10]
There is no single investigation required for all patients. The choice depends on clinical findings, likely diagnoses, and urgency.
Some cases of mild knee pain without significant injury or warning signs may improve with appropriate initial self-care.
However, home treatment should never delay urgent assessment when serious symptoms are present.
Temporarily reduce activities that clearly worsen pain, such as running, jumping, or repeated stair climbing during a flare.
In many cases, complete or prolonged inactivity is unnecessary. Instead, activity can be adapted according to tolerance once serious causes have been excluded.
A cold pack wrapped in a towel may help relieve discomfort for a short period.
Do not apply ice directly to the skin. Additional caution or professional advice may be needed for people with impaired sensation or circulation. [2]
Some nonprescription medicines may provide temporary symptom relief when used appropriately.
However, treatment selection depends on medical history and other medications.
Nonsteroidal anti-inflammatory drugs (NSAIDs) are not suitable for everyone, including some people with kidney disease, stomach ulcers, cardiovascular conditions, or those taking anticoagulants.
Ask a healthcare professional or pharmacist for advice when appropriate, and do not use pain medication to conceal symptoms of a potentially serious injury.
Exercise may benefit certain conditions, including osteoarthritis and patellofemoral pain, but a rehabilitation program for an acute injury or an inflammatory condition may be very different.
If you have an established diagnosis of knee osteoarthritis, you can explore 7 Knee Osteoarthritis Exercises to Improve Strength and Mobility, with exercise selection adapted to your symptoms and clinical needs.
There is no single treatment that is appropriate for every form of knee pain.
Treatment depends on whether symptoms are related to osteoarthritis, injury, tendon disorders, inflammatory disease, infection, or another condition.
Physiotherapy may help with patellofemoral pain, osteoarthritis, selected tendon problems, and rehabilitation after injuries.
Programs can address muscle strength, mobility, movement control, and a gradual return to daily activities.
However, exercise intensity and technique must match the diagnosis rather than applying an identical program to every patient. [3] [8]
Osteoarthritis management commonly emphasizes individualized therapeutic exercise, weight management when appropriate, and selected approaches to pain relief.
Injection or surgery decisions should not be based only on pain location or the severity of X-ray findings.
Some injuries can be managed with activity modification, rehabilitation, and follow-up, while others may need specialist intervention.
The decision depends on the type and severity of injury, joint stability, functional limitations, and the individual's circumstances.
Not every meniscal tear requires surgery. [7]
Treatment for a Baker's cyst depends on symptoms and any underlying knee condition contributing to excess joint fluid.
Some cysts improve without an invasive procedure, while others may require treatment of the underlying joint problem.
New or sudden calf swelling must be appropriately assessed to exclude DVT before it is attributed to a Baker's cyst. [6]
Gout and other inflammatory joint conditions may require treatments that differ from those used for osteoarthritis or mechanical injuries.
Septic arthritis requires urgent medical care and may involve hospital admission, antibiotics, and drainage of infected joint fluid. [10]
For more about the wider causes of joint discomfort, read Joint Pain: Causes and When It May Be Serious.
Arrange medical assessment if knee pain persists, repeatedly returns, or begins to interfere with walking, work, sleep, or climbing stairs.
An orthopedic assessment may be appropriate when injury or a structural joint problem is suspected.
Physiotherapy may help improve strength, movement, and function as part of an appropriate treatment plan after the likely cause has been identified.
Explore the Orthopedic Department at Mouwasat Hospital and the Physiotherapy Department to learn about relevant services and available healthcare professionals.
Possible causes include patellofemoral pain, patellofemoral osteoarthritis, and other joint or tendon problems. Symptoms during stair climbing and pain location alone are not sufficient for diagnosis.
Not necessarily. Inner knee pain may arise from the meniscus, medial collateral ligament, osteoarthritis, or nearby bursae and tendons. A clinical assessment helps distinguish these possibilities.
Possible causes include a Baker's cyst, tendon or muscle problems, and other conditions. Sudden unexplained calf swelling or worsening leg pain requires urgent assessment to exclude DVT.
Descending stairs requires different patterns of muscle control and joint loading. This can make it more painful for some people, but the difference does not reliably identify one particular diagnosis.
The side affected does not determine the diagnosis. The precise pain location, onset, associated symptoms, and examination findings are more informative.
No. Knee clicking can occur without a significant joint condition. Clicking accompanied by pain, swelling, locking, or instability is more likely to require further assessment.
Yes. Osteoarthritis, patellofemoral pain, tendon disorders, inflammatory conditions, and other problems can produce symptoms without a specific traumatic event.
Urgent assessment is needed for sudden severe pain in a hot swollen joint, significant injury with inability to bear weight, suspected DVT, or other major warning signs. Leg swelling with sudden breathlessness or chest pain requires immediate emergency assistance.
Not always. An MRI is considered when clinical findings suggest an injury or condition for which the result would affect management. X-rays, ultrasound, or no imaging may be more appropriate in other situations.
It depends on the cause and severity of the pain. Appropriate walking may help some conditions, including osteoarthritis, but it is not a substitute for assessment when there has been an acute injury or severe, worsening symptoms.
When the diagnosis is unclear or symptoms involve injury, swelling, or recurrent significant pain, a medical assessment may be the appropriate first step. Physiotherapy can then help improve mobility, strength, and function when indicated.
The location of knee pain, whether at the front, back, inner side, or outer side, can help identify possible causes. However, an accurate diagnosis also requires understanding how the symptoms began, what makes them worse, whether other symptoms are present, and what the physical examination reveals.
Pain when climbing stairs does not automatically indicate osteoarthritis, just as discomfort behind the knee does not necessarily mean a Baker's cyst.
The most important priority is recognizing warning signs that may indicate joint infection, significant injury, or a blood clot, while seeking appropriate assessment for ongoing symptoms that interfere with everyday life.
If knee pain is affecting your mobility, a professional assessment can help determine whether you may benefit from orthopedic care, physiotherapy, or another treatment approach.
Medical disclaimer: This article provides general health education and does not replace professional medical evaluation, diagnosis, or individualized treatment. Seek prompt medical attention for serious warning signs or sudden severe symptoms.
When knee osteoarthritis pain makes walking, climbing stairs, sleeping, or performing everyday activities difficult, and nonsurgical treatments no longer provide enough relief, knee replacement surgery may become an option.
But does severe pain automatically mean you need surgery? What is the difference between a total and partial knee replacement? How long will it take to walk comfortably, return to work, and resume your normal routine?
Knee replacement surgery, also known as knee arthroplasty, replaces damaged joint surfaces with artificial components designed to reduce pain and improve movement and function.
This guide explains when surgery may be appropriate, the available procedures, robotic-assisted knee replacement, how to prepare, what happens during the operation, the recovery timeline, potential complications, and important questions to discuss with your orthopedic surgeon.
Seek urgent medical assessment for increasing pain, warmth, redness, wound drainage, or fever after knee replacement, as these may indicate infection. New calf pain or swelling requires urgent assessment for a possible blood clot. Sudden breathlessness or chest pain requires immediate emergency assistance. [9]
Knee replacement is an orthopedic procedure in which damaged cartilage surfaces and small amounts of underlying bone are removed and replaced with artificial components.
The implants typically include metal and specialized medical-grade plastic components, designed to create new joint surfaces and support movement.
Although the procedure is commonly called knee replacement, the surgeon does not remove the entire knee. Instead, the damaged joint surfaces are replaced or resurfaced. [2]
The primary goal is to reduce pain caused by significant joint damage and improve everyday activities such as walking, standing, stair climbing, and getting out of a chair.
Surgery may also help correct certain deformities associated with advanced joint damage.
However, knee replacement cannot guarantee that the joint will feel exactly as it did before arthritis, and some patients may continue to experience pain or stiffness afterward.
The decision is based on more than the diagnosis of osteoarthritis. The impact of symptoms on everyday life and the response to appropriate nonsurgical treatments are especially important.
NICE recommends considering referral for joint replacement when pain, stiffness, reduced function, or progressive deformity substantially affects quality of life and nonsurgical treatments are ineffective or unsuitable. [1]
These findings do not mean that surgery is inevitable, but they are reasonable reasons to discuss the options with an orthopedic specialist. [2]
Not necessarily. Appropriate nonsurgical management is important, but every patient does not need to undergo every available injection or medication before surgery can be considered.
The 2023 ACR/AAHKS guideline conditionally recommends against routinely delaying surgery for additional nonsurgical treatments in patients who already have symptomatic and radiographically moderate-to-severe osteoarthritis, have not benefited sufficiently from appropriate nonsurgical treatment, and have chosen to proceed with joint replacement.
This recommendation applies to a specific patient group and should not be interpreted as advice to skip appropriate nonsurgical care in early osteoarthritis. [11]
No. Advanced X-ray changes can support the clinical assessment, but they do not independently determine whether knee replacement is necessary.
One patient may have substantial radiographic changes but relatively manageable symptoms, while another may experience severe limitations in daily life.
The decision should therefore consider symptoms, physical examination, relevant imaging, previous treatments, patient preferences, and realistic treatment goals.
Age alone should not exclude someone from being assessed for knee replacement. Body mass index (BMI) alone should not automatically prevent referral either.
However, age, weight, smoking, medical conditions, and other health factors may influence individual surgical risks and the preparation needed before an operation. [1]
Total knee replacement, or total knee arthroplasty (TKA), is the most common knee replacement procedure.
It involves resurfacing the main joint surfaces between the thighbone and shinbone with artificial components. The underside of the kneecap may also be treated, depending on the surgical plan.
It may be appropriate when damage affects multiple joint compartments or when a partial replacement would not meet the patient's needs.
Partial knee replacement, also known as unicompartmental knee replacement, involves replacing the damaged surfaces within one compartment while preserving suitable unaffected structures.
It requires specific anatomical and functional conditions, including assessment of the remaining joint surfaces and ligaments.
Recovery may be faster for selected patients, but partial replacement is not suitable for everyone and may require revision surgery in the future.
NICE recommends offering a choice between partial and total replacement for suitable patients with isolated medial compartment osteoarthritis and discussing the benefits and risks of both approaches. [4] [5]
| Feature | Total replacement | Partial replacement |
|---|---|---|
| Extent of replacement | Main joint surfaces | One affected compartment |
| Typical suitability | May suit damage involving multiple compartments | Requires specific joint and ligament conditions |
| Recovery | May take several months | May be faster in selected patients |
| Procedure selection | Based on damage, stability, and functional goals | Based on the condition of remaining joint structures |
Some orthopedic centers use robotic-assisted systems to support surgical planning and precise positioning of knee replacement components.
Robotic assistance does not mean the robot operates independently. The procedure remains controlled by the surgical team, with the level and type of assistance varying between systems.
NICE guidance on robotic-assisted orthopedic procedures indicates that these systems can improve the precision of implant alignment and positioning.
However, available comparative evidence has not consistently demonstrated better overall patient-reported outcomes or lower complication rates than conventional surgery. Longer-term evidence continues to develop. [12]
Therefore, the choice should not be based on the word "robotic" alone. The surgeon's expertise, patient characteristics, proposed procedure, and expected benefits and risks are also important.
Preparation can help identify risks and improve your ability to participate in postoperative rehabilitation.
Your healthcare team may review your medical history, current medications, and overall health, and perform appropriate examinations, X-rays, blood tests, or an electrocardiogram when indicated.
Patients with conditions such as diabetes, heart disease, or kidney disease may require additional assessment. [2] [6]
Your doctor may recommend improving blood glucose control, stopping smoking, addressing active infections, and optimizing nutrition and appropriate physical activity before surgery.
These decisions should be individualized rather than using age or BMI alone as an automatic reason to exclude someone from surgical assessment.
Tell your surgeon about all medications, particularly anticoagulants, anti-inflammatory medicines, and diabetes treatments, as well as recent injections into the affected knee.
Do not stop prescribed medication without medical instructions. Your surgeon and anesthesia team will advise whether changes are needed.
NHS guidance emphasizes practical home preparation, arranging support, and planning for temporary limitations in driving and working. [6]
Knee replacement takes place in a hospital under general anesthesia, spinal anesthesia, or other appropriate regional anesthesia techniques, depending on the individual's circumstances.
The operation commonly takes approximately 1 to 2 hours, although total time in the operating area may be longer and complex procedures may require additional time. [5]
Specific steps differ between total and partial replacement and according to the selected surgical technique. [2] [5]
Full recovery can take several months or longer. The timeline varies according to age, overall health, preoperative muscle strength, the type of procedure, and any postoperative complications.
Recovery after partial knee replacement may be shorter than after total replacement for suitable patients. [7]
Healthcare professionals generally help patients begin standing and walking early, when medically safe, using a walker or crutches initially.
Pain management, blood clot prevention, and early functional rehabilitation are important during this stage.
Some selected patients may go home on the day of surgery, while others remain in the hospital for several days according to recovery and mobility needs.
Recovery focuses on wound care, swelling management, safe walking, and gradually improving knee bending and straightening under the rehabilitation plan.
Pain, swelling, and sleep difficulties can still occur, but recovery should generally show gradual progress rather than continued deterioration.
Walking, standing from a chair, and other daily activities may become easier.
Some patients gradually move to less supportive walking aids as strength and balance improve.
Reaching six weeks does not automatically mean every patient is ready to walk unaided or resume driving.
Many patients regain greater independence, and some may return to work, particularly if their job is not physically demanding.
Work involving heavy lifting, prolonged standing, or repetitive movement may require a longer recovery period.
Muscle strength, movement, and physical endurance may continue to improve over subsequent months.
Early discomfort or limited movement should not be used alone to judge the final result of surgery.
| Stage | What to expect | Main priority |
|---|---|---|
| First day and following days | Monitoring, pain control, and assisted mobilization | Safety and complication prevention |
| First two weeks | Wound care, prescribed exercises, and gradual walking | Managing swelling and restoring movement |
| Weeks 3–6 | Gradual improvement in mobility and independence | Strength, balance, and everyday function |
| Weeks 6–12 | Return to some work and daily activities | Increasing activity when appropriate |
| Several months and beyond | Continued gains in strength and endurance | Sustainable return to daily life |
Important: This timeline is illustrative rather than a fixed rehabilitation prescription. Your surgeon and physiotherapist should guide weight-bearing, exercises, walking aids, driving, and returning to work. [7] [13]
Physiotherapy plays an important role in restoring mobility, muscle strength, balance, and safe walking after knee replacement surgery.
Depending on the individual's condition, rehabilitation may focus on:
No single exercise program or fixed repetition schedule is appropriate for every patient after knee replacement.
AAOS emphasizes regular, individualized rehabilitation and a gradual return to daily activities as important parts of recovery. [8]
Explore the Physiotherapy Department at Mouwasat Hospital, which includes rehabilitation after orthopedic procedures and joint replacement.
Precautions depend on the procedure and surgeon's instructions. The following points are general guidance, not universal restrictions for every patient.
Your doctor may prescribe anticoagulant medication, compression devices, or other measures according to your individual risk.
Follow the prescribed plan and do not change medications without medical advice.
Use walking aids when needed and keep your environment free of trip hazards.
Avoid rapid twisting or unstable movements when your knee strength and balance are still recovering.
Prolonged positioning with the knee flexed may make it harder to regain full knee extension.
Follow your rehabilitation team's instructions for safe resting positions and leg elevation.
NHS guidance generally advises waiting at least six weeks after total knee replacement, or three weeks after partial replacement, before driving, with confirmation that it is medically safe.
These are general guidelines rather than automatic clearance. Recovery, the operated leg, medications, driving ability, and local legal requirements should all be considered. [7]
Low-impact activities such as walking, stationary cycling, and swimming after wound healing and medical clearance may help maintain fitness.
High-impact activities such as running or jumping may place excessive demands on the artificial joint and should be discussed with your surgeon. [13]
Knee replacement can substantially improve pain and everyday function for many patients, but individual results vary.
It is important to distinguish three different outcomes:
Implant survival should not be presented as a measure of surgical success or patient satisfaction.
A systematic review and meta-analysis published in The Lancet in 2019 estimated that approximately 82% of total knee replacements lasted 25 years without revision, based on pooled joint registry data.
This is a population-level estimate, not a guarantee for any individual patient. Implant longevity can vary with age, activity, implant design, health conditions, and other factors. [10]
Yes. Some patients eventually require revision knee replacement because of implant loosening, wear, infection, instability, or other complications.
However, revision surgery is not inevitable, and new or worsening pain should be properly investigated rather than automatically attributed to implant failure.
Most patients do not experience serious complications, but knee replacement is major surgery and its risks must be understood before making a decision.
Infections may involve the skin wound or deeper tissues surrounding the implant.
A deep prosthetic joint infection can require specialized treatment and sometimes additional surgery.
Blood clots can develop in the leg veins after surgery.
Occasionally, a clot may travel to the lungs and cause a serious pulmonary embolism. This is why postoperative clot-prevention measures are important.
Some patients experience reduced movement or persistent discomfort despite an otherwise technically successful replacement.
Appropriate rehabilitation may help, but certain cases require further evaluation or treatment.
The components may wear or loosen over time, and selected patients may eventually require revision surgery.
These complications are uncommon but should be discussed according to the patient's health and the planned procedure. [2] [9]
Some pain and swelling are expected during early recovery. However, symptoms that progressively worsen, particularly with fever, increasing redness, or wound drainage, need prompt medical assessment.
New calf pain or swelling requires urgent assessment for possible DVT. Sudden breathlessness, chest pain, or fainting requires immediate emergency assistance.
The cost of knee replacement in Saudi Arabia varies according to the procedure, implant type, medical complexity, hospital, length of stay, and associated services.
Insurance coverage and prior authorization requirements may also affect the amount paid by the patient.
Before proceeding, it is useful to ask whether the estimated cost includes:
A higher price alone does not establish that a technique or implant will produce better results for an individual patient.
If knee pain, stiffness, and difficulty moving are substantially affecting your daily life despite appropriate treatment, an orthopedic assessment may help determine whether total or partial knee replacement is suitable.
Learn about the Orthopedic Department at Mouwasat Hospital and the Physiotherapy and Rehabilitation Department, including postoperative rehabilitation services available at your preferred hospital location.
It may be considered when symptoms significantly affect daily life and appropriate nonsurgical treatments have not provided enough improvement or are unsuitable. The decision should be made jointly by the patient and orthopedic surgeon.
It is major surgery with potential risks, including infection, blood clots, and stiffness. However, most patients do not experience serious complications. Individual risks vary with health and other factors.
Most patients experience meaningful improvement in pain and function, but no single percentage captures every aspect of success. Implant survival must not be confused with patient satisfaction or complete pain relief.
Many patients begin standing and walking with assistance soon after surgery when medically safe. Progress depends on the procedure, strength, balance, and overall health.
Walking and daily activities can improve gradually over the first several weeks, but full recovery may take several months or longer. There is no single timetable for everyone.
Some patients return within approximately 6 to 12 weeks, but physically demanding jobs may require more time. Your healthcare team should assess readiness based on your work requirements and recovery.
Movement often improves with recovery and rehabilitation, but final range of motion varies. It may depend on preoperative stiffness, health, and postoperative complications.
Artificial knees can last many years, but lifetime durability is not guaranteed. Registry-based research has estimated that approximately 82% of total knee replacements last 25 years without revision.
It may improve the precision of implant alignment, but current evidence does not establish consistently superior clinical outcomes compared with conventional surgery. The most suitable approach depends on the patient and surgical team.
Simultaneous bilateral knee replacement may be considered in selected patients. However, it has different risks and recovery requirements from replacing one knee and is not suitable for everyone.
These activities may remain difficult or uncomfortable for some patients. The ability to perform them depends on motion, strength, implant characteristics, and recovery. Do not attempt kneeling or substantial pressure on the operated knee without your surgeon's clearance.
NHS guidance generally advises waiting at least six weeks after total replacement and three weeks after partial replacement. Medical clearance, safe vehicle control, and freedom from medication-related impairment are essential.
Complications such as infection, loosening, stiffness, or persistent pain can occur, and some patients require revision surgery. However, failure is not the expected outcome for most patients.
It may be suitable for selected older adults. Age alone should not automatically exclude someone from surgical assessment. The decision depends on overall health, functional limitations, and the expected benefits and risks.
Knee replacement can help many people whose advanced osteoarthritis significantly limits everyday activities and has not responded adequately to appropriate nonsurgical treatment.
But a good outcome involves more than the operation itself. Selecting the right patient, discussing realistic expectations, preparing medically, and participating in rehabilitation are all important parts of care.
If you are wondering whether your knee osteoarthritis has reached the stage where joint replacement should be considered, an orthopedic assessment can help clarify your options.
Learn more about Orthopedic Care and Physiotherapy at Mouwasat Hospital.
Medical disclaimer: This article is intended for general health education and does not replace an individualized surgical assessment or treatment instructions. Surgical suitability, recovery, and precautions vary between patients. Seek urgent care for signs of infection, blood clots, or sudden breathing difficulties after surgery.

Depression does not affect emotions alone. It can also cause physical symptoms such as persistent fatigue, sleep disturbances, changes in appetite and weight, headaches, muscle or back pain, and digestive problems. These symptoms are real and may significantly affect daily life, even when a person cannot identify an obvious explanation for them.
However, fatigue, pain, or sleep problems do not automatically mean someone has depression. Similar symptoms may occur with anemia, thyroid disorders, sleep conditions, chronic illnesses, or medication effects. An appropriate assessment therefore considers physical and emotional symptoms together rather than assuming that unexplained physical complaints must have a psychological cause. [1] [2]
Do not assume that sudden persistent chest pain, severe difficulty breathing, sudden weakness on one side of the body, or difficulty speaking is caused by depression or anxiety. These symptoms may indicate a medical emergency. Suicidal thoughts accompanied by intent or a plan to harm oneself also require urgent intervention. In an immediate emergency in Saudi Arabia, call 997 for ambulance assistance or seek care at the nearest emergency department. [6] [7] [8]
Physical symptoms of depression can involve changes in energy levels, sleep, appetite, movement, pain perception, and other bodily functions. They may occur as part of a depressive episode or alongside a separate medical condition.
The National Institute of Mental Health (NIMH) identifies fatigue, low energy, sleep disturbances, appetite and weight changes, physical aches, headaches, cramps, and digestive complaints among the symptoms that may accompany depression.
The NHS also describes physical symptoms such as constipation, slowed movement or speech, low sex drive, and disrupted sleep. [1] [2]
The pattern varies considerably. One person may experience insomnia and a loss of appetite, while another sleeps longer than usual and develops an increased appetite.
It is important to distinguish these symptoms from a clinical diagnosis. Physical complaints alone cannot establish major depressive disorder. Clinical evaluation also considers persistent low mood or loss of interest or pleasure, along with other symptoms, their duration, and their effects on daily life. [5]
For an explanation of the emotional and behavioral signs, read Depression Symptoms: How to Recognize the Signs and Distinguish Depression from Sadness.
Persistent fatigue is one of the most frequently reported physical symptoms of depression. Everyday activities may begin to feel unusually demanding, including taking a shower, preparing meals, commuting to work, or completing routine household tasks.
Some people wake up exhausted despite spending sufficient time in bed. Others find it difficult to start tasks or maintain their usual level of activity throughout the day.
Several factors may contribute to fatigue during depression, including disrupted sleep, changes in motivation and activity levels, and difficulties maintaining everyday routines.
Reduced physical activity and persistent pain may also increase the overall burden of fatigue.
Depression-related tiredness should not be explained as a simple deficiency in a single brain chemical. The relationship between mood, sleep, energy regulation, and physical health is complex.
No. Tiredness is a common, nonspecific symptom and may also occur with:
Persistent unexplained fatigue should be discussed with a healthcare professional, particularly when accompanied by unusual breathlessness during activity, pallor, significant sleep changes, or unexplained weight changes.
Any investigations should be based on the person's symptoms and medical history rather than ordered routinely for everyone experiencing tiredness. [4]
Depression can affect sleep in different ways. Some people struggle to fall asleep or remain asleep, while others sleep for unusually long periods.
A person may spend a long time trying to fall asleep, experience repetitive thoughts at bedtime, or wake repeatedly during the night.
Ongoing sleep disruption can make daytime fatigue, irritability, and concentration difficulties more noticeable.
Some individuals with depression wake several hours earlier than intended and cannot easily return to sleep.
However, early waking alone does not confirm depression. It may also be associated with stress, changes in sleep schedules, or other sleep disorders.
Others experience excessive sleeping, sometimes described as hypersomnia, or a persistent desire to sleep despite spending many hours in bed.
This can occur with depression, but excessive daytime sleepiness may also indicate sleep apnea, medication effects, or another medical condition. [1]
Seek medical advice when sleep disturbances are persistent or interfere with daily functioning, particularly if they are accompanied by loud snoring, witnessed pauses in breathing, severe daytime sleepiness, or significant changes in mood and energy.
Sleep medications or sedatives should not be taken or adjusted without appropriate medical guidance.
Depression may affect how much a person eats, how interested they feel in food, and whether their weight changes over time.
Importantly, appetite does not always change in the same direction.
Some people experience reduced appetite, less interest in preparing meals, or a reduced desire to eat foods they previously enjoyed.
When these changes persist, they may contribute to unintended weight loss.
However, appetite loss and weight changes can also be associated with digestive disorders, chronic illnesses, and medication effects. They should not automatically be attributed to depression.
Other people notice an increase in appetite, more frequent eating, or greater interest in certain foods.
Some depressive presentations are associated with increased appetite and sleep, but these features alone do not identify a specific depression diagnosis. [1]
Medical evaluation is particularly important when changes are prolonged, involve unexplained weight loss, affect the ability to maintain adequate nutrition, or occur alongside other physical symptoms.
Both emotional and physical health should be considered, especially when appetite changes occur with fatigue, persistent sleep disturbances, or loss of interest in everyday activities.
Depression can occur alongside recurrent physical pain, including headaches, muscle aches, and back pain. In some people, no single physical explanation is identified for every symptom after appropriate assessment.
However, pain should never be dismissed as imaginary or "just psychological" because depression is present. Pain is a genuine physical experience and may require its own medical evaluation and treatment.
Depression may be associated with increased physical pain complaints. Stress, sleep disruption, and reduced activity may also influence how pain is experienced.
Nevertheless, muscle and back pain can have musculoskeletal, neurological, inflammatory, or other medical causes.
The location of pain alone cannot establish whether depression is contributing to it.
Headaches can occur alongside depression, but they are extremely common and have many possible causes, including tension-type headaches, migraine, dehydration, and sleep problems.
There is no particular headache location that reliably proves a headache is caused by depression.
A new, worsening, or unusually severe headache, especially when accompanied by neurological symptoms, requires appropriate medical evaluation.
The relationship can work in both directions.
Living with persistent pain may interfere with sleep, employment, social activities, and a person's sense of independence. These difficulties may contribute to depressive symptoms.
At the same time, depression can make pain harder to cope with, while disrupted sleep and reduced activity may add to the overall burden.
Mayo Clinic explains that pain and depression can reinforce each other. Some individuals benefit from a coordinated approach that addresses both conditions rather than treating only one. [3]
When persistent pain occurs alongside loss of enjoyment, low mood, or major changes in daily functioning, evaluating both physical and psychological symptoms can help guide appropriate care.
In addition to fatigue, sleep problems, and pain, depression may involve other physical changes that vary between individuals.
Some people experience constipation, abdominal discomfort, cramps, or changes in bowel habits alongside depressive symptoms.
Medical references recognize that digestive problems can accompany depression, but this does not mean all gastrointestinal symptoms are caused by a mental health condition. [1] [2]
Digestive symptoms may be related to diet, medications, or gastrointestinal disorders that require separate evaluation, particularly when accompanied by bleeding, unexplained weight loss, or increasing pain.
During some depressive episodes, a person may move or speak more slowly than usual.
Others experience noticeable restlessness, difficulty sitting still, or changes in their usual physical activity.
Clinicians may refer to these as psychomotor changes when they are sufficiently prominent and observable.
These changes can contribute to a depression assessment, but they are not enough to establish the diagnosis on their own. [5]
Depression may be accompanied by reduced sexual interest or changes in sexual functioning.
Some medications, including certain antidepressants, can also contribute to sexual side effects in some individuals.
It is therefore important to consider whether a symptom relates to depression, a medication, or another health issue.
People experiencing distressing sexual changes should discuss them with their clinician rather than stopping prescribed medication without guidance. [1] [2]
Some people notice dizziness, palpitations, or chest discomfort during periods of emotional distress. These symptoms may overlap with anxiety or panic attacks.
However, dizziness and palpitations are not specific diagnostic signs of depression.
They may also be associated with heart conditions, blood pressure changes, anemia, dehydration, or medication effects.
New or persistent chest pain, severe breathlessness, or fainting should not be assumed to have a psychological cause. Medical or emergency assessment may be necessary depending on the symptoms. [6]
The table below shows why fatigue, sleep disturbances, and pain should be considered within a broader medical assessment rather than used to diagnose depression independently.
| Physical symptom | Possible relationship with depression | Other possible causes | Appropriate next step |
|---|---|---|---|
| Fatigue and low energy | Low energy and difficulty completing normal activities. | Anemia, hypothyroidism, and sleep disorders. | Review symptom duration and associated signs; consider targeted investigations when indicated. |
| Insomnia or oversleeping | Sleep changes occurring during a depressive episode. | Sleep apnea, medication effects, and other sleep disorders. | Review sleep patterns, snoring, daytime sleepiness, and sleep quality. |
| Appetite or weight changes | Reduced or increased food intake during depressive symptoms. | Thyroid or digestive disorders and medication effects. | Assess weight changes and associated symptoms, especially when weight changes are unintentional. |
| Headaches, muscle pain, or back pain | Pain can coexist with depression, and each condition may increase the burden of the other. | Musculoskeletal, neurological, and inflammatory conditions or migraine. | Seek medical evaluation for new or persistent pain rather than automatically attributing it to mental health. |
| Constipation or abdominal pain | Digestive symptoms may accompany depression. | Gastrointestinal disorders, dietary changes, and medications. | Review symptoms, particularly when persistent or accompanied by warning signs. |
| Dizziness or palpitations | May occur with coexisting anxiety or emotional distress but are not core diagnostic signs of depression. | Dehydration, anemia, heart or blood pressure problems, and medication effects. | Obtain assessment according to severity, with emergency evaluation if serious warning signs appear. |
Important: The conditions listed are examples rather than an exhaustive differential diagnosis. This table cannot rule out medical conditions or establish depression. Investigations should be selected according to the clinical findings. [4] [5]
Yes. Some people seek care primarily because of fatigue, low energy, insomnia, or persistent pain, rather than a clearly expressed feeling of sadness.
An especially important symptom to consider is loss of interest or pleasure, also called anhedonia.
A person may no longer enjoy hobbies, social activities, family gatherings, or everyday experiences that were previously meaningful, even if they do not describe themselves as sad.
Loss of interest or pleasure is one of the core symptoms assessed when considering major depressive disorder, alongside depressed mood.
Nevertheless, physical symptoms by themselves cannot confirm depression. A comprehensive evaluation may need to consider mood, daily functioning, medical history, and medication use. [1] [5]
Physical symptoms of depression can affect both women and men.
People may differ in how they describe their symptoms or whether they seek help for physical discomfort before discussing emotional changes.
However, there is no reliable sex-specific list of physical symptoms that can independently diagnose depression.
An effective evaluation considers the full range of physical, emotional, and behavioral changes rather than making assumptions based on gender.
Yes. Depression, anxiety, and chronic medical conditions may share symptoms such as sleep disturbances, fatigue, concentration problems, and physical discomfort.
More than one condition may also be present at the same time.
The purpose of assessment is not to choose between a physical or psychological explanation too quickly, but to understand the possible contributing conditions and determine appropriate care.
For more information, read What Causes Depression? Risk Factors and Conditions That Mimic Its Symptoms.
The appropriate response depends on the type of symptom, its severity, how quickly it developed, and its effect on everyday functioning.
Arrange a professional assessment if:
Depression symptoms occurring most of the day, nearly every day, for at least two weeks may indicate a depressive episode that requires assessment.
However, people should not wait two weeks to seek help when symptoms are severe, rapidly worsening, or significantly distressing. [1]
Examples include:
The required urgency varies according to the details. These symptoms should not automatically be interpreted as manifestations of depression.
Seek emergency assistance if any of the following occur:
In Saudi Arabia, call 997 for an ambulance. Do not dismiss these symptoms as temporary emotional distress or rely on a routine appointment when urgent medical care is needed. [6] [7] [8]
A thorough assessment begins by understanding the person's main concerns, how symptoms have developed, and how they affect daily life.
The clinician then considers medical and psychological history and whether additional investigations or referrals are appropriate.
A healthcare professional may ask when fatigue, pain, or sleep problems began, whether they developed suddenly or gradually, and whether they vary throughout the day.
They may also ask whether symptoms relate to physical activity, eating patterns, medication changes, or other circumstances.
The assessment may cover persistent low mood, reduced enjoyment, concentration difficulties, anxiety, and the effects of symptoms on relationships, employment, and daily responsibilities.
Questionnaires such as the PHQ-9 may help identify and monitor depressive symptoms, but a questionnaire result alone does not provide a definitive diagnosis.
Clinicians consider chronic illnesses, sleep disorders, and medications that may contribute to fatigue, appetite changes, or pain.
They may also ask about previous periods of unusually elevated mood or increased activity, which can be important when distinguishing unipolar depression from bipolar disorder. [5]
Depending on the clinical findings, investigations may include a complete blood count when anemia is suspected, thyroid function tests when appropriate, or further assessment of a possible sleep disorder.
There is no universal blood-test panel that every patient with fatigue and depressive symptoms must undergo.
Normal laboratory results also do not rule out depression.
It may be helpful to record:
These details can help guide the assessment and reduce the likelihood of unnecessary investigations. [1] [5]
To explore specialist care, visit the Psychiatry Department at Mouwasat Hospital and review the physicians available at your preferred hospital location.
Physical symptoms such as fatigue, sleep disturbances, and appetite changes may improve as depression responds to treatment.
However, the timing and extent of improvement vary. Not every physical symptom improves at the same rate, and some may have an independent medical cause.
Persistent pain, a separate sleep disorder, or another health condition may require additional treatment even after emotional symptoms improve. [3]
Evidence-based psychological treatments, including cognitive behavioral therapy and interpersonal therapy, can help improve depressive symptoms by addressing relevant thoughts, behaviors, relationships, and coping strategies.
Psychological interventions may also help individuals manage the emotional and practical impact of chronic pain.
However, they should not replace appropriate medical treatment when a physical cause of pain is identified.
Depending on the diagnosis, symptom severity, and medical history, a clinician may recommend antidepressant medication.
Some people notice changes in sleep, appetite, or concentration before their overall mood improves.
A meaningful treatment response often develops gradually over several weeks, and both benefits and side effects vary between individuals.
Do not stop antidepressants abruptly or change prescribed doses without medical advice. [1]
Maintaining regular sleep and wake times, eating balanced meals, choosing physical activities appropriate for one's health, and staying connected with supportive people may help overall well-being and complement treatment.
These measures should not be considered guaranteed substitutes for professional care, particularly when depression is moderate, severe, or persistent.
For more information on treatment options and recovery timelines, read Depression Treatment: Therapy, Medication, and When Improvement Begins.
You can also explore our guide to the types of depression, including major, persistent, and seasonal patterns, to better understand differences in presentation and clinical course.
Yes. Fatigue and low energy are recognized symptoms of depression, sometimes occurring even when a person has not been physically active. However, persistent tiredness may also result from anemia, thyroid problems, or sleep disorders and should be evaluated in context.
Yes. Excessive sleeping can occur in some people with depression, while others experience insomnia or early-morning awakening. Sleep duration alone cannot determine the cause, particularly when loud snoring or severe daytime sleepiness is present.
Depression may occur alongside widespread or recurring aches and pains and can make chronic pain harder to manage. However, widespread pain has several possible medical causes and should not automatically be considered psychological.
Headaches can accompany depression, but they are not specific to it. Migraine, tension-type headaches, sleep problems, and other conditions may also cause headaches. New, worsening, or neurologically concerning headaches require medical evaluation.
Yes. Some people experience reduced appetite and unintended weight loss during depression. Others experience increased appetite and weight gain. Unexplained or persistent weight changes should be assessed, particularly when other symptoms are present.
These complaints may occur during anxiety or emotional distress, but they are not core diagnostic signs of depression. They can also reflect medical conditions and should be evaluated according to their severity, circumstances, and associated symptoms.
Yes. Some people first notice fatigue, sleep difficulties, or pain before recognizing changes in mood or loss of pleasure. Nevertheless, physical complaints alone are not sufficient for diagnosis, and the full health picture should be considered.
Some physical pain may improve as mood, sleep, and daily functioning improve, but results vary. If pain has an independent medical cause or continues after depressive symptoms improve, additional assessment and treatment may be needed.
Fatigue alone cannot reliably distinguish the two. A clinician considers emotional symptoms, loss of pleasure, sleep patterns, medical history, medications, physical examination findings, and targeted investigations when appropriate.
Depression may cause fatigue, low energy, sleep disturbances, appetite changes, and physical pain. For some people, these symptoms have as much impact on everyday life as emotional difficulties.
However, similar symptoms may also result from other medical conditions, and depression can coexist with chronic illness or persistent pain.
The most appropriate approach is neither to dismiss physical symptoms as psychological nor to overlook possible depression. A professional assessment should consider physical and mental health together.
If symptoms are persistent or interfere with your sleep, activities, or relationships, explore the Psychiatry Department at Mouwasat Hospital and review available physicians at your preferred location.
Medical disclaimer: This article provides general health information and does not replace professional medical examination, diagnosis, or treatment.

Someone may laugh with friends, perform well at work, and appear confident in social situations while privately struggling with depressive symptoms. This experience is often described as smiling depression, a popular term for depression that may not be obvious from a person's outward appearance or behavior.
However, smiling depression is not a formally recognized, separate psychiatric diagnosis. A person may experience genuine depression while continuing to work, socialize, and smile, but these behaviors alone cannot establish or rule out a mental health condition. An appropriate diagnosis depends on the person's symptoms, medical history, and professional clinical assessment. [1] [2]
This article explores the meaning of smiling depression, the less visible signs of emotional distress, why some people hide their symptoms, and how to support someone who may be struggling without making assumptions about their mental health.
If someone expresses suicidal thoughts accompanied by intent or a plan to harm themselves, or there is an immediate threat to their safety, seek emergency assistance. Do not leave a person alone when they are at immediate risk. In Saudi Arabia, call 997 for an ambulance or go to the nearest emergency department. A person's smile or apparently normal behavior should never be used as evidence that they are safe when serious warning signs are present. [2] [8]
Smiling depression describes a situation in which someone experiences depressive symptoms while presenting themselves to others as happy, sociable, or generally well-functioning.
They may be known for their optimism, professional accomplishments, or willingness to help others, yet privately experience exhaustion, emptiness, hopelessness, or a reduced ability to enjoy life.
Importantly, smiling depression is not an independent diagnosis in established psychiatric classification systems.
Some people described by this term may meet the criteria for major depressive disorder or persistent depressive disorder. Others may be experiencing emotional distress without meeting the full criteria for a depressive disorder.
Only an appropriate clinical assessment can determine what is happening. [1] [3]
A smile, therefore, does not prove that depression is absent. Equally, concealing emotions does not prove that someone has depression.
People sometimes choose not to discuss personal difficulties at work or during social occasions. This is a common human behavior and does not automatically indicate a mental health disorder.
Clinical depression, by contrast, involves a pattern of symptoms that may include persistent low mood or loss of interest and pleasure, together with changes in sleep, appetite, energy, thinking, and daily functioning.
For major depressive disorder, relevant symptoms generally occur for most of the day, nearly every day, for at least two weeks, alongside other diagnostic criteria.
However, someone experiencing severe distress or safety concerns should seek help without waiting for that duration. [1]
To learn more about the core symptoms, read Depression Symptoms: How to Recognize the Signs and Distinguish Depression from Sadness.
Yes. Someone with depression can laugh, enjoy particular moments, and perform well at work. Depression does not necessarily mean looking sad every minute of the day.
Depressive disorders do not always eliminate every positive emotion. Similarly, being able to fulfill certain responsibilities does not mean that a person is free from emotional difficulties.
For example, an employee may appear enthusiastic during meetings, make jokes with colleagues, and complete important assignments, yet struggle with motivation and sleep after returning home.
Another person may maintain friendships and family responsibilities while privately feeling disconnected from activities they previously enjoyed.
These examples illustrate how outward functioning and internal experiences can differ. They are not diagnostic scenarios: fatigue, reduced motivation, and sleep difficulties can also result from stress or medical conditions.
Not always.
Some individuals consciously choose not to share their emotional difficulties. Others continue their usual social behavior without intentionally concealing anything.
A person may also struggle to recognize depressive symptoms in themselves, particularly when changes develop gradually.
It is therefore inappropriate to assume that someone is secretly depressed simply because they appear cheerful around others but sometimes prefer to spend time alone.
There is no separate diagnostic checklist for smiling depression.
However, someone who conceals emotional distress may experience recognized symptoms of depression that are not immediately obvious in their social interactions.
A person may continue attending social events, practicing hobbies, or completing daily responsibilities without experiencing their usual sense of enjoyment or satisfaction.
They might participate because they feel obligated, want to maintain relationships, or prefer to preserve their routine.
Loss of interest or pleasure, also called anhedonia, is one of the core symptoms clinicians assess when evaluating possible depression. [1]
Some people feel they must make a considerable effort to appear cheerful or energetic around others.
After work or social gatherings, they may feel emotionally drained and seek time alone to recover.
However, feeling tired after a busy day does not by itself indicate depression. It can also reflect normal fatigue, insufficient sleep, or other health problems.
The symptom becomes more relevant when it is persistent and accompanied by other changes such as low mood or loss of pleasure.
Depression can involve insomnia, early-morning awakening, excessive sleeping, changes in appetite, and unintended weight changes.
These symptoms may remain unnoticed by friends and colleagues when the person continues presenting themselves as well and fulfilling their normal responsibilities.
Learn more in our article Physical Symptoms of Depression: Fatigue, Sleep, Appetite, and Body Pain.
Some individuals experience persistent emptiness, pessimism, or a loss of meaning despite appearing optimistic during ordinary conversations.
They may avoid discussing these feelings because they worry about upsetting loved ones or being judged for their emotional difficulties.
Persistent hopelessness deserves particular attention as part of an assessment of depression and individual safety.
Depression can affect concentration, decision-making, and the ability to manage tasks efficiently.
Someone who appears productive may privately notice that familiar responsibilities now require much greater effort.
They may also struggle to organize daily activities, maintain attention, or make ordinary decisions.
Someone may continue meeting essential obligations while gradually becoming less involved in friendships, hobbies, or activities they previously valued.
This withdrawal may be subtle and difficult for others to notice.
Nevertheless, enjoying solitude or needing personal time is not itself a sign of depression. Clinicians are more concerned with persistent changes from a person's usual behavior, especially when other depressive symptoms are present.
Some people regularly tell others that they are fine despite experiencing emotional difficulties.
They may change the subject when asked about their well-being or downplay the severity of their symptoms.
These behaviors may be relevant when combined with persistent depressive symptoms, but they cannot establish a diagnosis independently.
A 2025 research study examining the concealment of depression symptoms found that some individuals actively modify their social presentation, including displaying positive emotions while concealing distress. [4]
There is no single explanation for why someone may conceal depressive symptoms.
Individual reasons can involve social expectations, personal beliefs, relationships, and difficulties recognizing or communicating emotional experiences.
Some people worry that discussing mental health concerns will cause others to see them as weak, unreliable, or unable to manage their responsibilities.
They may also fear that being open about psychological difficulties could change how they are treated by relatives, friends, or colleagues.
Someone may keep their feelings private because they believe that sharing them will cause family members or friends unnecessary concern.
Although this may come from a desire to protect others, prolonged silence can sometimes reduce opportunities to receive helpful support.
People who are accustomed to supporting others may believe they must always appear capable, optimistic, or emotionally stable.
This pressure can be particularly challenging when a person has responsibilities at home or in the workplace.
Being responsible or resilient does not mean someone should have to manage mental health difficulties alone.
In some cases, concealment is not intentional.
A person may attribute low energy, sleep disturbances, or loss of enjoyment to a demanding job or a stressful period, without recognizing that the symptoms may warrant mental health assessment.
This can delay appropriate care, especially when the person remains able to perform their basic responsibilities.
A study titled Camouflaging Depression, published in Discover Mental Health in May 2025, examined behaviors related to concealing depressive symptoms among 292 participants with a history of depression or relevant depressive symptoms.
The researcher developed a measure to investigate these behaviors and identified associations between depression camouflaging and indicators of distress, fatigue, and internalized stigma. [4]
These findings are informative, but several limitations matter:
The practical message is that outward social behavior may not fully reflect someone's internal emotional experience, and direct, respectful communication is more useful than judging mental health from appearance alone.
Several terms appear in online discussions of mental health, including smiling depression, hidden depression, masked depression, and high-functioning depression.
These expressions are not necessarily interchangeable, and they should not all be presented as distinct medical diagnoses.
| Term | What it usually describes | Is it a separate diagnosis? |
|---|---|---|
| Smiling depression | Someone who appears happy or socially well-functioning despite experiencing depressive symptoms. | No. It is a popular descriptive term. |
| Hidden depression | Depressive symptoms that are not obvious to others or are not openly discussed. | No. It is a general descriptive expression. |
| High-functioning depression | Depressive symptoms in someone who continues performing some daily responsibilities. | No. It is not an independent formal diagnosis. |
| Depression with atypical features | A clinical pattern involving temporary mood improvement in response to positive events and other specific features. | A recognized clinical specifier, not a synonym for smiling depression. |
One defining feature of atypical depression is that mood may temporarily improve in response to positive events.
Other characteristics may include increased appetite, excessive sleeping, a heavy feeling in the limbs, and pronounced sensitivity to rejection.
These clinical features are not required for someone to be described informally as having smiling depression.
Similarly, smiling or being socially active does not establish atypical depression. [6]
For an explanation of recognized depressive disorders and patterns, explore Types of Depression: Major, Persistent, and Seasonal Patterns.
Depression can involve serious risks even when symptoms are not visible to others. However, there is insufficient evidence to classify smiling depression as automatically more dangerous than other forms of depression.
One potential concern is that friends, relatives, or colleagues may overlook emotional distress because someone appears successful, socially active, or cheerful.
The person may also delay seeking professional help because they believe that being able to work or laugh means they cannot be experiencing depression.
Nevertheless, appearance, professional functioning, and the number of outwardly visible symptoms do not provide a reliable assessment of individual risk.
A clinical evaluation considers several factors, including:
NICE recommends a comprehensive depression assessment rather than relying solely on symptom counts. Its guidance also emphasizes directly assessing suicidal thoughts and intent and arranging help appropriate to a person's needs and safety. [2]
Anyone who describes significant emotional distress deserves to be taken seriously, regardless of how happy or successful they may appear.
There is no reliable way to diagnose depression from facial expressions, photographs, or social media activity.
However, noticeable and persistent changes in a person's usual behavior may be an opportunity to check on their well-being without assuming that they have a particular condition.
These changes can have many explanations, including stress, anxiety, physical illness, or ordinary changes in circumstances.
They should therefore prompt understanding and conversation, not a diagnosis made by a friend or family member.
Not reliably.
People naturally select which parts of their lives they share online. Happy photographs do not prove an absence of depression, while sad posts or reduced activity do not prove that a person has it.
Direct, respectful conversation is more informative than trying to infer someone's mental health from their online image.
Talking about mental health can be difficult, particularly for someone who feels expected to remain strong or cheerful around others.
Supporting them does not require solving every problem. Listening without judgment, respecting their privacy, and encouraging appropriate professional care can make a meaningful difference. [5]
You might mention that you have noticed they seem unusually tired or that you care about how they are doing.
Give them the opportunity to speak without pressuring them to share details they are not ready to discuss.
Avoid assuming that a particular change in behavior means they have depression.
Statements suggesting that someone has no reason to feel depressed because their life looks good may discourage them from being open.
A more supportive approach is to acknowledge that emotional pain is not always visible and ask what kind of help would be useful.
| Instead of saying | Try saying | Why it helps |
|---|---|---|
| Your life is great. What do you have to be depressed about? | I know it may not be obvious what you're going through. I'm here to listen. | Acknowledges emotional distress without questioning its legitimacy. |
| You're always smiling. You can't be depressed. | I don't want to assume how you feel just from how you look. How have you really been? | Separates outward behavior from internal experience. |
| Just stop thinking negatively and you'll feel better. | Is there something I can help you with? We can look into professional support if you'd like. | Offers practical support instead of oversimplifying the problem. |
| You have to tell me everything right now. | You can share as much or as little as you're comfortable with. I'm here when you need me. | Respects privacy and reduces pressure. |
These are examples of supportive communication rather than substitutes for professional care when it is needed.
You can offer to help find a mental health professional, arrange an appointment if the person wishes, accompany them to a consultation, or check in regularly without becoming intrusive.
Respect confidentiality and avoid sharing their personal information without permission, except when disclosure is necessary to protect someone from a serious safety threat.
Take the concern seriously. Ask calmly and directly whether they are thinking about harming themselves, and whether they have any intention or plan to do so.
If there is an immediate threat, seek emergency help, do not leave the person alone, and help create a safer environment if you can do so without placing yourself or others at risk.
Do not promise to keep a secret when doing so would put someone's life in danger. [2]
There is no established, independent diagnostic test specifically for smiling depression. The term itself does not represent a separate psychiatric disorder.
Online quizzes may claim to identify smiling depression, but their results cannot confirm a depressive disorder, determine its severity, or predict an individual's safety risks.
The Patient Health Questionnaire-9 (PHQ-9) is one of several validated tools that healthcare professionals may use to screen for depressive symptoms, estimate symptom burden, and monitor change over time.
However, questionnaire scores do not replace a clinical assessment of the person's symptoms, medical and mental health history, functional impairment, and possible alternative explanations. [2] [3]
An evaluation may include:
The goal is not to prove that someone has a condition called smiling depression, but to determine whether they have a recognized depressive disorder or another condition that would benefit from appropriate care.
Effective treatment depends on the underlying diagnosis, symptom severity, medical history, and the individual's circumstances.
Being able to smile or function socially does not change the need for an appropriate clinical assessment.
Evidence-based treatment options for depression may include psychological therapy, medication when indicated, or a combination of both. [1] [2]
Psychological interventions, such as cognitive behavioral therapy and interpersonal therapy, can help people understand and address relevant thoughts, behaviors, emotional difficulties, and relationship patterns.
Therapy may also provide a confidential setting to discuss concerns about expressing vulnerability, seeking support, or maintaining an outward appearance of being well.
Depending on the diagnosis and severity of symptoms, a clinician may recommend antidepressant medication.
Meaningful improvement may take several weeks, and both the benefits and possible side effects vary between individuals.
Psychiatric medications should not be started, stopped, or adjusted without appropriate medical advice.
Consistent sleep routines, appropriate physical activity, supportive relationships, and manageable daily routines may complement a treatment plan.
However, these measures are not guaranteed substitutes for professional treatment and should not be used to suggest that depression can simply be overcome by choosing to think positively.
No. People have a right to privacy and can choose whom they trust with personal information.
Recovery does not require sharing every emotional experience with everyone.
What matters is that difficulty discussing symptoms does not prevent someone from accessing professional assessment or treatment when needed.
For a detailed discussion of available approaches, see Depression Treatment: Therapy, Medication, and When Improvement Begins.
You can also explore What Causes Depression? Risk Factors and Conditions That Mimic Its Symptoms to understand the different factors that may contribute to depressive symptoms.
Consider speaking with a healthcare professional if low mood, loss of enjoyment, sleep changes, reduced energy, concentration problems, or feelings of hopelessness persist or affect your quality of life.
Professional support may be appropriate even when you are still able to work, maintain relationships, and meet your usual responsibilities.
You do not need to wait until your symptoms become obvious to others or until everyday life feels completely unmanageable.
Seek urgent assistance if someone experiences:
In an immediate emergency in Saudi Arabia, call 997 for an ambulance or go to the nearest emergency department. A routine outpatient booking is not a substitute for emergency care. [8]
The Psychiatry Department at Mouwasat Hospital provides assessment and care for a range of mental health conditions, including depressive disorders, according to the services available at each hospital location.
You can explore available physicians and appointment options to find appropriate professional support.
Seeking help is a meaningful step even when your emotional difficulties are not visible to the people around you.
Smiling depression is a popular term describing someone who experiences depressive symptoms while appearing happy, sociable, or capable of maintaining daily responsibilities. It is not a separate clinical diagnosis, and professional assessment is needed to identify the actual condition.
Yes. Someone with depression can laugh, enjoy certain experiences, and continue working or socializing. These behaviors do not rule out depression, but smiling alone does not indicate that a person has it either.
There is insufficient evidence to rank smiling depression as inherently more dangerous. Concealed symptoms may be harder for others to notice, but actual risk depends on the severity of symptoms, individual circumstances, and any concerns about safety.
There is no independently established diagnostic test for smiling depression. Screening instruments such as the PHQ-9 may help assess depressive symptoms, but they cannot diagnose smiling depression as a separate condition or replace clinical evaluation.
The terms are sometimes used similarly in everyday language to describe emotional suffering that is not obvious to others. However, neither is a separate formal diagnosis, and they should not automatically be equated with atypical depression or persistent depressive disorder.
Possible reasons include fear of social judgment, reluctance to worry loved ones, pressure to appear strong, or difficulty discussing emotions. Motivations vary, and some people may not recognize their experiences as possible symptoms of depression.
Yes. Less visible depressive symptoms can occur in people of any gender. No single outward behavior or gender-specific sign reliably identifies depression.
No. Some individuals maintain professional performance despite experiencing significant depressive symptoms. However, professional success does not prove depression either. Diagnosis depends on clinical symptoms and assessment.
Listen without questioning the legitimacy of their feelings. Avoid assuming that their appearance fully reflects their emotional state. Encourage professional assessment when appropriate and offer practical support, while responding immediately to any signs of imminent self-harm risk.
Not everyone who smiles feels happy all the time, and not everyone with depression looks visibly sad.
Some individuals continue their work, maintain relationships, and appear cheerful despite experiencing depressive symptoms that deserve attention.
However, smiling depression remains a descriptive term rather than an independent medical diagnosis.
Recognizing meaningful symptoms, respecting people's experiences, and avoiding judgments based solely on appearance are more valuable than attempting to label someone according to how they look.
If you are experiencing persistent emotional difficulties, or are concerned about someone close to you, professional support can help clarify what is happening and guide appropriate care.
Learn more about the Psychiatry Department at Mouwasat Hospital and the physicians available at your preferred hospital location.
Medical disclaimer: This article is intended for general health education and does not replace professional medical assessment, diagnosis, or treatment.

Having a baby can bring significant physical, emotional, and lifestyle changes. While many mothers expect to feel happy after childbirth, some experience unexplained crying, anxiety, exhaustion, or a loss of interest in activities they previously enjoyed.
These feelings may be part of the temporary mood changes known as the baby blues, which usually improve within one to two weeks. However, persistent or more severe symptoms may indicate postpartum depression (PPD), a treatable mental health condition that can affect a mother's well-being and daily functioning.
Postpartum depression may begin during the first weeks after childbirth or develop later during the baby's first year. Some depressive symptoms may even begin during pregnancy. Recognizing the difference between baby blues and postpartum depression can help mothers and families understand when professional support is appropriate. [1] [2]
Importantly, postpartum depression does not define how much a mother loves her baby or how capable she is of caring for her child. It is a medical condition, and effective treatment options are available.
Hallucinations, delusions, severe confusion, or sudden and unusual behavioral changes after childbirth may indicate postpartum psychosis, a psychiatric emergency requiring immediate assessment.
Suicidal thoughts accompanied by intent or a plan to harm oneself or the baby, or any immediate threat to safety, also require emergency intervention. In Saudi Arabia, call 997 for an ambulance or go to the nearest emergency department. Do not leave the mother alone with the baby when there is an immediate safety concern. [4] [8]
Postpartum depression is a depressive condition that develops after childbirth and affects mood, thoughts, energy, and everyday functioning.
It may involve persistent sadness, anxiety, emptiness, or a loss of interest and pleasure, together with changes in sleep, appetite, concentration, and self-esteem.
The broader term perinatal depression includes depression occurring during pregnancy and after childbirth. Postpartum depression refers specifically to depressive symptoms occurring after the baby is born. [2]
A diagnosis is not based on sadness alone. Clinicians consider the overall pattern of symptoms, their duration, their effects on daily activities, and other medical or psychiatric explanations.
No. A mother may love her baby deeply while experiencing significant depressive symptoms.
Some mothers find it difficult to feel emotionally connected to their newborn or enjoy early interactions. Others maintain a strong sense of closeness despite having postpartum depression.
Difficulty bonding can be one possible symptom, but it is not required for diagnosis, and it does not mean that the mother is incapable of building a close relationship with her child. [2]
These experiences deserve understanding and support rather than blame or judgment.
The baby blues describe temporary emotional changes that many mothers experience shortly after childbirth.
They may involve crying easily, mood swings, anxiety, irritability, and feeling overwhelmed as the body and family adjust to life with a newborn.
According to the Saudi Ministry of Health, baby blues commonly begin around two to three days after delivery and generally improve within a few days to one or two weeks. [1]
These symptoms can occur alongside hormonal changes, recovery from delivery, disrupted sleep, and the adjustment to caring for a newborn.
If low mood, anxiety, or loss of pleasure continues beyond two weeks, becomes progressively worse, or significantly affects the mother's ability to function, professional evaluation is appropriate.
However, there is no need to wait two weeks when symptoms are severe from the beginning, when daily functioning is seriously affected, or when immediate safety concerns arise.
Although these conditions may occur after childbirth, they differ considerably in their symptoms, clinical significance, and appropriate response.
| Feature | Baby Blues | Postpartum Depression | Postpartum Psychosis |
|---|---|---|---|
| Usual onset | First few days after childbirth. | During the following weeks or months, potentially within the first year. | Often begins suddenly within the first two weeks, though later onset is possible. |
| Typical symptoms | Temporary crying, mood swings, and anxiety. | Persistent low mood, loss of pleasure, anxiety, fatigue, and changes in sleep or appetite. | Hallucinations, delusions, severe confusion, or sudden major mood and behavioral changes. |
| Duration | Usually improves within one to two weeks. | May continue for weeks, months, or longer without appropriate treatment. | Can worsen rapidly over hours or days. |
| Recommended response | Support, rest, and monitoring; seek assessment if symptoms persist or worsen. | Early professional assessment and an appropriate treatment plan. | Immediate emergency psychiatric assessment, usually requiring hospital care. |
This comparison is intended for education rather than self-diagnosis. Severe or concerning symptoms warrant assessment even before two weeks have passed. [1] [2] [4]
Postpartum depression does not look the same in every mother. Symptoms may affect emotions, thinking, physical health, relationships, and everyday activities.
A mother may experience sadness throughout much of the day, cry more often than usual, or feel emotionally empty or hopeless.
These feelings may persist even when she tries to maintain her normal routine.
Activities that were previously enjoyable may no longer feel rewarding.
A mother may lose interest in hobbies, social contact, or personal activities, even when she has opportunities to participate.
Loss of interest or pleasure is a core symptom assessed when evaluating a depressive disorder. [2]
Depression after childbirth may occur alongside substantial anxiety about the baby's health, safety, feeding, or the mother's ability to provide care.
Worry can become so persistent that it affects sleep, concentration, and the ability to relax, even when the baby is safe.
Newborns require frequent attention, so interrupted sleep is expected for many families.
However, some mothers with postpartum depression cannot sleep even when their baby is asleep and someone else is available to help.
Others experience early waking, excessive sleeping, or persistent exhaustion that does not improve with ordinary rest.
A mother may experience a substantial decrease or increase in appetite, sometimes accompanied by unintended changes in weight.
Although physical changes are common after childbirth, persistent difficulty eating adequately or significant unexplained weight changes deserve medical attention.
Some mothers feel responsible for difficulties beyond their control or believe that they are failing, even when they are making considerable efforts to care for their baby.
These thoughts may become persistent and affect self-esteem or contribute to feelings of hopelessness.
Concentration and decision-making may become unusually difficult, beyond what might be expected from temporary tiredness alone.
Everyday choices and responsibilities can feel overwhelming.
Some mothers describe feeling emotionally distant from their newborn or struggling to enjoy interactions with the baby.
Not everyone with postpartum depression experiences this symptom, and it does not determine how much a mother loves her child.
Some individuals experience thoughts about death, suicide, or not wanting to continue living.
These thoughts should be discussed with a healthcare professional and assessed appropriately. Intent, a plan, or an immediate safety threat requires urgent emergency assistance. [2]
For a broader overview of depressive symptoms, read Depression Symptoms: How to Recognize the Signs and Distinguish Depression from Sadness.
Postpartum depression often develops within the first weeks after delivery, but symptoms can begin later.
Depressive symptoms may develop during pregnancy, soon after childbirth, or at any point during the baby's first year. [2] [3]
Yes. Some mothers develop symptoms several months after delivery.
Sleep disruption, continuing stress, previous mental health conditions, and other circumstances may contribute, although no single factor explains every case.
Feeling emotionally well immediately after delivery does not rule out the possibility of later postpartum depression.
Baby blues usually improve within a few days to two weeks.
If symptoms persist, become more severe, or significantly affect daily functioning, the mother may need assessment for postpartum depression or another condition.
There is no single recovery timeline that applies to everyone.
Symptoms may continue for weeks, months, or longer, especially without appropriate treatment. Recovery depends on the individual, symptom severity, other health conditions, and response to treatment.
Professional care remains worthwhile even when symptoms have been present for a prolonged period.
No. The two-week duration can be relevant to diagnostic assessment, but it is not a waiting period for accessing care.
Severe symptoms, major difficulty with everyday functioning, or concerns about safety should be evaluated promptly.
Postpartum depression does not have one universal cause.
It may involve a combination of biological, psychological, and social factors. Some mothers develop postpartum depression even when pregnancy, delivery, and family support have been generally positive.
Major hormonal changes occur after childbirth and may contribute to mood changes in some women.
However, hormonal shifts alone do not explain every case of postpartum depression, and the disorder cannot be confirmed by a single hormone test. [1]
A history of depression, depressive symptoms during pregnancy, or postpartum depression following a previous birth may increase the likelihood of another episode.
A history of bipolar disorder or episodes of mania or hypomania is also particularly important because it can affect diagnosis, treatment choices, and safety planning.
Frequent nighttime waking and limited opportunities for rest can make the postpartum period physically and emotionally demanding.
Although poor sleep may contribute to distress, postpartum depression should not be dismissed as simple tiredness that will necessarily disappear with more sleep.
Relationship difficulties, financial concerns, major family changes, or insufficient practical support may add to a mother's emotional burden.
Medical complications, distressing experiences during childbirth, concerns about the baby's health, and ongoing caregiving challenges can also increase stress.
These are possible contributing factors rather than inevitable causes. A mother can develop postpartum depression without any of them.
For a broader explanation of depression risk factors and similar medical conditions, see What Causes Depression? Risk Factors and Conditions That Mimic Its Symptoms.
Yes. Postpartum depression can occur after either vaginal birth or cesarean delivery.
The experience of childbirth, complications, postoperative pain, reduced mobility, and difficulty sleeping may increase emotional stress for some mothers.
However, the mode of delivery alone does not determine whether someone will experience postpartum depression.
There is no clinical basis for assuming that postpartum depression occurs only after a cesarean delivery or cannot happen following an uncomplicated birth.
Some mothers experience painful feeding, concerns about milk supply, or difficulties establishing a feeding routine.
These challenges may increase distress, especially when practical or emotional support is limited.
However, breastfeeding difficulties do not automatically indicate depression, and developing postpartum depression does not mean that a mother is unable to breastfeed her child.
Feeding concerns and emotional symptoms should each receive appropriate attention, without blame or judgment.
Some new mothers experience unwanted, upsetting thoughts or mental images about something bad happening to their baby.
It is important to distinguish between intrusive thoughts that are unwanted and distressing, actual intentions to cause harm, and psychotic symptoms involving a loss of contact with reality.
Intrusive thoughts are unwanted thoughts or images that appear involuntarily and may conflict with a person's beliefs, intentions, or values.
A mother may feel frightened by a thought she does not want and make efforts to dismiss it or avoid situations that trigger it.
Intrusive thoughts can occur with anxiety or perinatal obsessive-compulsive disorder (OCD).
The International OCD Foundation explains that intrusive thoughts associated with perinatal OCD are not the same as the delusions or hallucinations experienced during psychosis. [7]
Not necessarily.
An unwanted thought that frightens a mother and conflicts with her desire to keep her baby safe does not automatically indicate an intention to act on it.
However, recurring or distressing thoughts deserve professional assessment, especially when they interfere with sleep, caregiving, or everyday functioning.
A clinician can assess the nature of the thoughts, whether another condition is present, and whether any safety measures are necessary.
In perinatal OCD, intrusive thoughts are generally experienced as unwanted and distressing, and the person usually recognizes that the thoughts do not reflect what they want.
Postpartum psychosis may involve hallucinations, delusions, severe confusion, or dramatic changes in mood and behavior.
Nevertheless, families should not attempt to make this distinction independently when serious symptoms are present.
Suspected psychosis, actual intent to cause harm, or an immediate risk to the mother or baby requires emergency assessment. [4] [7]
Some symptoms warrant a timely medical or psychiatric appointment, while others require emergency intervention.
Postpartum psychosis is a psychiatric emergency that can deteriorate rapidly. It requires immediate professional intervention and should not be managed as ordinary postpartum tiredness or mood changes. [4]
Postpartum depression is diagnosed through a clinical assessment of symptoms, their duration, their effects on everyday life, and the mother's medical and mental health history.
The clinician may ask about low mood, loss of interest, anxiety, sleep, appetite, concentration, energy, and emotional connection with the baby.
They may also explore whether symptoms interfere with essential self-care or daily responsibilities.
Common tools include:
A high questionnaire score does not establish a diagnosis on its own, and a low score does not eliminate the need for professional evaluation when meaningful symptoms or safety concerns are present.
The American College of Obstetricians and Gynecologists (ACOG) recommends screening for depression and anxiety during pregnancy and at postpartum visits using validated tools, with pathways for appropriate assessment, treatment, and follow-up. [5]
A history of depressive episodes, mania, or hypomania can be relevant to the diagnosis and treatment plan.
ACOG recommends screening for bipolar disorder before initiating medication for perinatal depression or anxiety when such screening has not previously been performed. [5]
Some medical conditions, including anemia and thyroid disorders, may contribute to fatigue or mood-related symptoms.
A clinician may recommend targeted investigations when appropriate, but there is no single blood test that diagnoses postpartum depression.
When self-harm thoughts, concerns about harming the baby, or psychotic symptoms arise, clinicians assess the situation directly and determine what level of intervention is required.
An online questionnaire is never an appropriate substitute for emergency care when serious warning signs are present.
Effective treatments are available for postpartum depression.
Clinical care is tailored to symptom severity, diagnosis, previous treatment response, medical history, breastfeeding circumstances, and individual preferences.
Options may include psychotherapy, medication, or a combination of approaches, together with monitoring and follow-up. [2] [6]
Evidence-based psychological therapies, including cognitive behavioral therapy (CBT) and interpersonal therapy (IPT), can help mothers manage depressive symptoms and address emotional or relationship challenges associated with the transition to parenthood.
Psychotherapy may be suitable as an initial treatment for some individuals or used alongside medication when appropriate.
A healthcare professional may recommend antidepressants depending on the mother's diagnosis and clinical needs.
Meaningful improvement often develops gradually over several weeks, and the response varies between individuals.
Medication benefits, possible side effects, and follow-up requirements should be discussed with the prescribing clinician.
Psychiatric medication should not be started, stopped, or adjusted without medical guidance, particularly during pregnancy or breastfeeding.
In some cases, yes.
Selected antidepressants may be appropriate during breastfeeding after an individualized assessment of benefits and potential risks.
Small amounts of certain medications may pass into breast milk, but this does not automatically mean that breastfeeding must be stopped.
The decision depends on the specific medication, maternal health, infant age and health, and any additional medical considerations. [6]
Mothers should not independently stop breastfeeding, discontinue treatment, or avoid needed mental health care because of uncertainty about medication safety.
The treating clinician may coordinate with a pediatrician when appropriate.
Specialized medications for postpartum depression have become available in some healthcare systems.
However, regulatory approval, treatment requirements, and availability vary between countries.
A medicine approved in another country should not be assumed to be licensed or available in Saudi Arabia. Treatment selection should follow appropriate medical assessment and applicable local regulations.
Practical help with infant care, opportunities for rest, balanced meals, and supportive relationships can reduce some of the daily burdens faced during the postpartum period.
These measures can complement treatment, but they do not necessarily replace professional care, especially when symptoms are moderate or severe.
For more information about treatment approaches and recovery, read Depression Treatment: Therapy, Medication, and When Improvement Begins.
Partners, relatives, and close friends may notice changes in a mother's well-being before she feels comfortable discussing them.
Practical assistance, emotional understanding, and support with accessing professional treatment can all be valuable.
| Mother's need | Helpful action | What to avoid |
|---|---|---|
| Rest and sleep | Share infant-care duties and household tasks, making time for the mother to rest. | Expecting her to handle every responsibility alone. |
| Emotional support | Ask how she is feeling and listen without criticism or interruption. | Suggesting that she must always feel happy because she has a baby. |
| Nutrition and self-care | Help prepare meals and manage everyday needs. | Minimizing her exhaustion or blaming her for reduced energy. |
| Access to treatment | Help arrange appointments, transportation, or childcare during consultations. | Pressuring her to stop treatment or rely exclusively on nonmedical advice. |
| Safety during a crisis | Arrange emergency care immediately and stay with her when there is an imminent risk. | Dismissing hallucinations or severe confusion as ordinary postpartum fatigue. |
Supportive communication might begin with: "I've noticed that things have been difficult lately. How can I help?"
Another practical offer could be: "We can find a healthcare professional together, and I'll help with the baby during your appointment."
It is better to avoid comments that minimize her experience, such as "Every mother gets tired" or "You have a beautiful baby, so why are you sad?"
Yes. Fathers and partners can experience depressive symptoms after the arrival of a new baby.
These experiences may involve emotional, social, and health-related factors, but they should not be confused with the specific physical changes associated with pregnancy and childbirth.
Anyone experiencing persistent depressive symptoms may benefit from appropriate assessment. [3]
Not every case of postpartum depression can be prevented.
However, identifying risk factors early, maintaining appropriate follow-up, and ensuring access to support may help reduce risk for some individuals or allow symptoms to be recognized sooner.
Preventive psychological interventions may be appropriate for some women at increased risk, but no single strategy guarantees that postpartum depression will not occur. [5]
Yes. A previous episode of depression during pregnancy or after childbirth may increase the likelihood of another episode.
However, recurrence is not inevitable.
Mothers with a history of postpartum depression may benefit from discussing future pregnancy plans with their obstetric and mental health clinicians to establish an individualized monitoring and support plan.
Baby blues involve temporary mood changes that generally improve within one to two weeks. Postpartum depression involves symptoms that are more persistent, severe, or disruptive to everyday life and may require professional treatment.
Symptoms often begin during the first weeks after childbirth, but they can appear several months later. Depression may also begin during pregnancy, so the postpartum period is not the only relevant time for assessment.
The duration varies. Symptoms may persist for weeks, months, or longer, especially without appropriate care. Recovery depends on the individual and response to treatment, and there is no universal timeline.
Yes. Postpartum depression can develop after either cesarean or vaginal birth. Recovery experiences and medical complications may contribute to stress, but the delivery method alone does not determine who will develop depression.
Yes. Postpartum depressive symptoms may begin at different points during the first year after childbirth. Persistent or concerning symptoms deserve evaluation even when the mother initially felt well.
Yes. Treatment options are available, and selected medications may be appropriate during breastfeeding. The clinician assesses the mother's symptoms, medication choice, infant health, and the individual benefits and risks before recommending a plan.
No. Some mothers experience difficulty feeling emotionally connected to their newborn during depression or other stressful circumstances. This does not define their love or ability to care for their child, but persistent difficulties may benefit from professional support.
No single blood test diagnoses postpartum depression. Clinicians use a comprehensive assessment and may include screening tools such as the EPDS or PHQ-9. Tests may be recommended when another medical condition is suspected.
Intrusive thoughts are often unwanted and distressing, particularly when associated with anxiety or OCD. Postpartum psychosis may involve hallucinations, delusions, and severe confusion and is a medical emergency. Any concern about intent to harm oneself or the baby requires appropriate risk assessment.
A partner can listen without judgment, share infant-care responsibilities, provide opportunities for rest, support access to professional care, and assist with appointments and follow-up.
Yes, recurrence is possible, and a previous episode can increase risk. However, another episode is not inevitable. Discussing mental health history before or during a future pregnancy can help guide early monitoring and care.
Physical and emotional changes are common after childbirth, and many mothers experience temporary baby blues that resolve within the first two weeks.
However, persistent sadness, loss of pleasure, severe anxiety, or symptoms that interfere with everyday functioning may indicate postpartum depression and should be professionally assessed.
A mother does not have to wait until she feels unable to manage her responsibilities before seeking help. Understanding from partners and family members, early assessment, and an appropriate treatment plan can support recovery and the well-being of both mother and baby.
For professional support, explore the Psychiatry Department at Mouwasat Hospital and review available physicians at your preferred hospital location.
Medical disclaimer: This article provides general health education and does not replace professional medical evaluation, diagnosis, or treatment. Immediate safety concerns involving the mother or baby require emergency care without delay.

If you experience knee pain when walking or climbing stairs, you may wonder whether continuing to move will make the condition worse. Resting the knee can seem like the safest option, but appropriate movement and muscle-strengthening exercises are among the most important treatments for knee osteoarthritis.
Knee osteoarthritis is a chronic condition affecting the knee joint and its surrounding tissues. It may cause pain, stiffness, swelling, and difficulty with everyday movements. Clinical guidelines recommend regular, individualized therapeutic exercise because it can improve pain, physical function, and quality of life. Some discomfort may occur when starting an exercise program, but activity should be adapted when pain becomes severe, swelling increases, or walking becomes significantly more difficult. [1] [2]
This article explains the symptoms and causes of knee osteoarthritis, whether walking is beneficial, which exercises may help, the available nonsurgical treatments, and when knee replacement surgery may be considered.
Sudden severe pain with marked swelling, warmth, or redness, especially when accompanied by fever or feeling generally unwell, requires urgent medical assessment. A joint infection or another serious condition may need to be excluded. Inability to bear weight after an injury or obvious knee deformity also requires urgent evaluation. Do not assume these symptoms are simply an osteoarthritis flare, and do not attempt to treat them by continuing to walk or exercise. [7]
Knee osteoarthritis is a form of osteoarthritis, a chronic joint condition involving changes in cartilage, bone, and surrounding joint tissues.
Healthy cartilage helps the joint surfaces move smoothly. In osteoarthritis, changes may involve cartilage thinning, alterations in the underlying bone, bone spur formation, and changes in other tissues around the joint.
Therefore, knee osteoarthritis is not simply a condition in which two bones rub together after all the cartilage disappears. It affects the entire joint, and symptoms can vary significantly between individuals. [3]
The World Health Organization identifies the knee as the most frequently affected joint worldwide. It also emphasizes exercise, rehabilitation, and weight management when appropriate as important components of osteoarthritis care. [3]
No. Knee osteoarthritis primarily involves degenerative changes affecting the joint, whereas rheumatoid arthritis is an autoimmune inflammatory disease that may involve multiple joints and requires a different treatment approach.
Knee pain does not necessarily indicate either condition. Other possible causes include ligament injuries, meniscal problems, tendon disorders, gout, and other joint conditions.
Learn more in our article Arthritis: Types, Symptoms, and How Osteoarthritis Differs From Rheumatoid Arthritis.
The symptoms of knee osteoarthritis vary according to joint changes, muscle strength, activity levels, and other individual factors. They often develop gradually.
Pain may occur when walking longer distances, standing for extended periods, climbing or descending stairs, or getting out of a chair.
Some people with more advanced symptoms also experience pain at rest or during the night.
However, the timing and severity of pain alone cannot determine the stage of osteoarthritis.
People may notice temporary stiffness when getting out of bed or standing after sitting for a long time.
Morning stiffness associated with osteoarthritis is often relatively brief, commonly lasting less than 30 minutes.
More prolonged morning stiffness, especially with swelling in several joints, may warrant assessment for an inflammatory joint condition. [4]
Some people notice clicking, cracking, or a grinding sensation when bending or straightening the knee. This is sometimes called crepitus.
However, knee clicking without pain or swelling does not automatically indicate osteoarthritis.
Clicking alone also cannot establish the severity of joint damage or whether treatment is necessary.
Mild or intermittent swelling may occur around the knee. In some advanced cases, the alignment of the leg may gradually change.
In contrast, sudden marked swelling with redness, warmth, or fever should not automatically be attributed to osteoarthritis.
The knee may become more difficult to bend or straighten fully.
This can interfere with squatting, getting up from a chair, and everyday activities requiring repeated knee bending.
Reduced physical activity and thigh muscle weakness may further contribute to functional limitations.
Some people report that their knee feels unsteady while walking or changing direction.
This sensation can relate to muscle weakness or changes in joint mechanics.
True knee locking or sudden instability following an injury may indicate a different problem, such as meniscal or ligament damage, and should be assessed accordingly.
Knee osteoarthritis does not have one universal cause. Several factors can contribute to its development or increase an individual's risk.
Although osteoarthritis is more common among older adults, younger people can also develop it, particularly following significant joint injuries. [3]
Walking is generally beneficial for people with knee osteoarthritis when the activity is adapted to their symptoms, fitness level, and physical capacity.
NICE recommends individualized therapeutic exercise for all people with osteoarthritis, including local muscle strengthening and general aerobic activity.
The guidance also explains that pain or discomfort may initially increase during therapeutic exercise, but regular, sustainable activity can improve pain, function, and quality of life over time. [1]
Appropriate walking can:
Walking does not rebuild damaged cartilage, and it is not the only exercise needed for every patient.
Some individuals benefit from combining walking with physiotherapy and strengthening exercises. Others may need activities that place less load on the knee while building their tolerance gradually.
Appropriate, moderate walking should not automatically be considered a cause of accelerated cartilage damage in every person with knee osteoarthritis.
However, suddenly increasing walking speed or distance can temporarily worsen pain, especially when muscle strength and exercise tolerance are limited.
The aim is to build activity gradually and observe how the knee responds, rather than avoiding movement because of fear that any discomfort indicates damage.
Short periods of rest may help during a painful flare, but prolonged inactivity can contribute to stiffness, muscle weakness, and reduced physical capacity.
In many cases, balancing activity and rest and adjusting exercise intensity is more helpful than avoiding movement entirely.
When walking is difficult, alternative activities such as stationary cycling or water-based exercise may be considered after appropriate assessment.
Some discomfort may occur when starting an exercise program. Not every increase in pain means that a new injury has developed.
However, the intensity, duration, and progression of symptoms matter.
| What happens while walking? | Suggested response |
|---|---|
| Mild, manageable discomfort that does not progressively worsen and settles after activity | Continuing at a comfortable, low intensity may be reasonable while monitoring symptoms. |
| Pain increases with distance, causes limping, or continues to worsen after activity | Reduce distance or pace, rest, and discuss adjusting the exercise plan if it recurs. |
| Marked swelling, severe pain, or a significant increase in stiffness the following day | Temporarily stop the aggravating activity and seek assessment if symptoms are severe or persistent. |
| Sudden severe pain with redness, warmth, fever, or inability to bear weight | Seek urgent medical assessment rather than treating it as routine osteoarthritis pain. |
Important: This table provides general guidance, not a diagnostic test or individualized exercise prescription. A clinician or physiotherapist may recommend different activity limits depending on the person's health and symptoms.
The best walking program is one that matches your current abilities and can be maintained safely over time.
There is no single walking distance, speed, or duration that is appropriate for everyone with knee osteoarthritis. [2]
If you have been inactive, walking for a few comfortable minutes on a level surface may be more appropriate than attempting a long walk immediately.
Short walking periods can be spread throughout the day and increased gradually as tolerated.
A level walking surface and comfortable, supportive footwear may help make walking more manageable.
Avoid sudden increases in activity intensity or challenging terrain if these consistently aggravate symptoms.
If your knee repeatedly becomes more painful after a certain walking distance, try a shorter distance and discuss gradual progression with a physiotherapist.
Meeting an arbitrary daily step target is less important than maintaining activity without substantial symptom worsening.
Walking helps support general fitness and mobility, but it does not replace exercises targeting the thigh, hip, and other muscles that support the knee.
Combining strengthening and aerobic exercise is often more useful than relying on walking alone. [1] [2]
Some people may benefit from a walking stick or another mobility aid if pain or instability affects safe walking.
NICE recommends considering walking aids for individuals with lower-limb osteoarthritis when appropriate. [1]
There is no universal therapeutic duration.
A practical starting point is a period that is comfortable for your current physical capacity, followed by gradual adjustments based on your response.
People with persistent pain, significant weakness, or limited mobility may benefit from an individualized program supervised by a physiotherapist.
Therapeutic exercise is a cornerstone of knee osteoarthritis management.
Exercise aims to improve muscle strength, maintain joint movement, and support everyday function.
The American College of Rheumatology strongly recommends exercise for knee osteoarthritis, while emphasizing that the type of activity should reflect the person's needs, preferences, and abilities. [2]
Gentle contraction of the front thigh muscles while sitting or lying down may be included in a strengthening program.
These exercises aim to activate muscles supporting the knee without requiring forceful joint movement.
The appropriate technique, frequency, and repetitions should be determined according to individual needs.
Raising the leg while keeping the knee straight may be useful in some rehabilitation programs.
However, the exercise should not cause severe pain or excessive strain, and it may need to be modified for people with other knee, hip, or back conditions.
Comfortable range-of-motion exercises may help maintain knee flexibility and reduce stiffness.
The joint should not be forced into a painful range or pushed aggressively beyond what can be tolerated.
Practicing standing up from and sitting down on a stable chair may help build functional strength when a person's balance and symptoms allow.
Some individuals may need a higher chair, stable support, or supervision.
Stationary cycling or exercising in water may offer alternative ways to remain active when long walks are difficult.
The most suitable choice depends on symptoms, fitness, medical conditions, and access to the activity.
Physiotherapy can help many patients reduce pain, improve movement, and maintain independence.
For some, the improvement is sufficient to delay or avoid considering surgery.
However, physiotherapy cannot guarantee that surgery will never be needed, particularly when symptoms remain severe despite an appropriate treatment program.
The Physiotherapy Department at Mouwasat Hospital provides musculoskeletal rehabilitation, therapeutic exercises, strengthening, and movement training tailored to individual needs.
No. Knee pain has many possible causes, and the likely explanation depends on factors such as symptom onset, location, swelling, previous injuries, and other associated symptoms.
| Symptom pattern | Possible cause | What to consider |
|---|---|---|
| Gradual pain with joint use and brief stiffness after rest | Knee osteoarthritis | Common pattern, but not sufficient for diagnosis by itself. |
| Pain after twisting or injury, sometimes with locking or instability | Meniscal or ligament injury | May require an injury-focused examination and selected imaging. |
| Several swollen joints with prolonged morning stiffness | Inflammatory arthritis, including rheumatoid arthritis | May warrant rheumatology assessment. |
| Sudden severe pain in a hot, swollen joint | Gout, septic arthritis, or another acute condition | Requires urgent assessment to exclude joint infection. |
| Localized pain triggered by a particular movement or repetitive activity | Tendon or surrounding soft-tissue problem | Examination can help identify the actual source of pain. |
These patterns provide general guidance, not a diagnosis.
For a broader explanation, read Joint Pain: What Causes It and When Is It Serious? and Early Rheumatoid Arthritis Symptoms: How RA Starts and How It Is Treated.
Diagnosis begins with a clinical assessment of symptoms, their duration, the effect on everyday movement, and relevant medical history.
A physical examination may assess knee movement, alignment, swelling, tenderness, stability, and functional limitations.
Often, yes.
NICE states that osteoarthritis can be diagnosed clinically in adults aged 45 or older who have activity-related joint pain and no morning stiffness, or stiffness lasting no longer than 30 minutes, provided there are no atypical features suggesting another diagnosis. [1]
This does not mean that younger people cannot develop osteoarthritis or that age 45 is an absolute diagnostic requirement.
X-rays may be useful when the diagnosis is uncertain, atypical symptoms are present, or further treatment planning requires imaging.
They can reveal changes such as narrowing of the joint space, bone spurs, and alterations in the bone beneath the joint surface.
However, routine imaging is not necessary for every patient with typical osteoarthritis, and repeat imaging is not generally required simply to monitor symptoms. [1]
An MRI is not routinely required for typical knee osteoarthritis.
It may be considered when the clinician suspects another injury or condition that cannot be adequately assessed through the examination and initial investigations.
One commonly used radiographic classification is the Kellgren–Lawrence grading system, which describes X-ray changes on a scale from 0 to 4.
| Radiographic grade | General description |
|---|---|
| 0 | No definite radiographic signs of osteoarthritis. |
| 1 | Possible or very minor radiographic changes. |
| 2 | More definite changes, including identifiable bone spurs. |
| 3 | Moderate to pronounced changes, including joint-space narrowing and bone changes. |
| 4 | Severe radiographic changes, including substantial joint-space narrowing and advanced bone changes. |
Important: These are imaging grades, not direct measures of pain or disability.
A person with relatively mild X-ray changes may experience significant pain, while another with more advanced radiographic changes may have fewer symptoms.
Decisions about treatment and surgery therefore depend on clinical symptoms, daily function, and response to appropriate care, not the X-ray grade alone.
No medication has been proven to restore an osteoarthritic knee joint completely to its original condition.
However, a combination of treatments can substantially improve pain, mobility, and quality of life.
Management generally focuses on individualized exercise, weight management when appropriate, education, symptom control, and selected additional interventions. [1] [2]
Muscle strengthening and appropriate aerobic activity are foundational treatments.
Physiotherapy can help patients learn safe exercise techniques, improve strength and mobility, and build a sustainable activity program.
Long-term consistency is often more beneficial than completing an intense exercise program for a short period and then stopping.
For people living with overweight or obesity, weight loss may reduce knee pain and improve physical function.
NICE notes that any sustained weight reduction can be beneficial and that a reduction of approximately 10% may provide greater improvement than 5% for some individuals when achieved safely. [1]
Weight management should be individualized rather than imposed as a universal requirement for every patient.
For more information about nutrition and joint health, see Foods to Avoid With Arthritis: What Should You Limit and What Does Not Need to Be Banned?.
NICE recommends offering topical nonsteroidal anti-inflammatory drugs (NSAIDs) to people with knee osteoarthritis when medication is needed.
These treatments may be appropriate for some patients, although allergies, contraindications, and possible medication interactions still need consideration. [1]
Oral NSAIDs may be considered when appropriate, but they can have gastrointestinal, kidney, cardiovascular, and other adverse effects.
NICE recommends using the lowest effective dose for the shortest necessary period and considering suitable stomach protection when oral NSAIDs are prescribed. [1]
Do not take anti-inflammatory pain medicines frequently or for extended periods without medical guidance, especially if you have kidney disease, a history of stomach ulcers, cardiovascular conditions, or take blood-thinning medication.
Walking sticks and selected supports may benefit individuals with pain, instability, or abnormal joint loading.
However, braces, specialized insoles, and other devices are not routinely necessary for everyone with knee osteoarthritis.
Selection should depend on the person's symptoms and an appropriate clinical assessment.
Some people obtain temporary symptom relief from gentle warmth when stiffness is prominent or cold applications when discomfort and swelling increase after activity.
These measures do not rebuild cartilage and should be used carefully when sensation, circulation, or skin integrity is impaired.
Some knee injections may provide symptom relief in selected circumstances, but their benefits, limitations, and evidence differ considerably.
Intra-articular corticosteroid injections may provide short-term relief for some patients when other treatment options are unsuitable or insufficient.
NICE advises that any benefit is generally temporary, typically around 2 to 10 weeks, and injections may be considered to help patients participate in therapeutic exercise. [1]
They do not reverse osteoarthritis or restore damaged cartilage. The risks and benefits of repeated injections should be discussed with a clinician.
Hyaluronic acid injections have been used for symptom relief, but research findings are inconsistent and do not establish sufficient benefit for routine use in all patients.
NICE recommends against offering intra-articular hyaluronan for osteoarthritis, and the ACR guideline conditionally recommends against its routine use for knee osteoarthritis. [1] [2]
Platelet-rich plasma injections have been studied for knee osteoarthritis, but the preparation methods, platelet concentrations, and treatment protocols vary substantially across studies.
The ACR guideline strongly recommends against PRP injections for knee osteoarthritis, citing insufficient standardization and limitations in the evidence supporting consistent benefit. [2]
PRP should not be marketed as a proven method of restoring cartilage or guaranteeing that knee replacement will never be necessary.
Some regenerative treatments remain experimental or insufficiently supported by high-quality clinical evidence.
There is currently no established basis for promising that a stem cell injection can reliably rebuild damaged knee cartilage or permanently cure osteoarthritis.
Patients should discuss evidence, potential harms, cost, and regulatory approval with qualified clinicians before considering such treatments.
Not everyone with knee osteoarthritis needs surgery.
Many patients improve with appropriate exercise, physiotherapy, weight management, and medication.
However, knee replacement may be considered when pain, stiffness, or reduced mobility substantially affects quality of life and adequate nonsurgical treatment has not provided sufficient relief. [1] [6]
No. Advanced radiographic changes do not automatically mean that surgery is necessary.
Clinical guidelines emphasize the impact of symptoms, quality of life, and response to nonsurgical management rather than using an imaging grade alone to determine referral. [1]
Arthroscopic washing or debridement is not recommended as a routine treatment for osteoarthritis alone because meaningful benefit has not been reliably established for this purpose.
Arthroscopy may still be considered for a separate, clearly identified knee problem in selected circumstances after orthopedic assessment.
It should not be presented as a procedure that restores osteoarthritic cartilage.
The Orthopedic Department at Mouwasat Hospital provides evaluation and treatment for musculoskeletal conditions, including joint disorders and knee replacement services when indicated.
Arrange a professional evaluation if:
Seek urgent medical assessment for sudden severe pain with warmth, redness, or significant swelling, especially if accompanied by fever or feeling unwell.
Inability to bear weight, obvious deformity, or signs of a serious injury also require prompt evaluation.
These symptoms may indicate a condition other than osteoarthritis, including septic arthritis or an acute injury. [7]
The appropriate specialty depends on the likely diagnosis:
You can explore the Orthopedic Department and Physiotherapy Department at Mouwasat Hospital and review the services available at your preferred hospital location.
Yes. Appropriate walking can improve mobility, fitness, and daily function. It is generally most helpful when combined with muscle-strengthening exercises and gradual activity progression.
Walking recommendations cannot be determined from an X-ray grade alone. Some people can walk comfortably with suitable adjustments, while others need shorter distances, walking aids, or alternative exercises based on their symptoms and clinical assessment.
Not necessarily for mild, manageable discomfort when starting an exercise program. However, sharp or progressively worsening pain, limping, significant swelling, or inability to bear weight warrants stopping the aggravating activity and seeking appropriate assessment.
There is no single best exercise for everyone. Walking, stationary cycling, water-based exercise, and strengthening of the thigh and hip muscles may all be useful. An appropriate program depends on the individual's symptoms, fitness, and medical history.
No treatment has been proven to restore an osteoarthritic knee joint completely to its original condition. However, appropriate treatment can substantially reduce pain and improve mobility and quality of life.
No. Clicking can occur without osteoarthritis or another serious knee problem. It is more relevant when accompanied by pain, swelling, locking, or significant instability.
Yes. Although osteoarthritis becomes more common with age, younger people may develop it, particularly after previous knee injuries or in the presence of other risk factors.
Yes. For people with knee osteoarthritis who are overweight or living with obesity, appropriate weight reduction can help reduce pain and improve function. The goal should be safe, realistic, and sustainable.
No. These injections have not been reliably shown to restore damaged cartilage or permanently cure knee osteoarthritis. Some clinical guidelines recommend against their routine use because of limited or inconsistent evidence of benefit.
Not in most typical cases. A clinician may diagnose osteoarthritis based on the symptom pattern and examination, using X-rays or other imaging when there is a specific clinical indication.
Knee replacement may be discussed when persistent pain, stiffness, and functional limitations significantly affect daily life despite appropriate nonsurgical treatment. The decision depends on a clinical assessment and discussion of the benefits, risks, and alternatives.
Stair climbing may increase symptoms because it requires greater effort from the knee and supporting muscles. However, pain while using stairs does not automatically prove that new joint damage has occurred. Activity modification and strengthening may help according to the individual's condition.
Knee osteoarthritis does not mean that you must stop walking or avoid using your knee.
Appropriate physical activity, muscle-strengthening exercises, and physiotherapy are among the most effective approaches for improving symptoms and maintaining everyday function.
The key is choosing suitable activities and progressing gradually while recognizing worsening pain, swelling, or warning signs that may indicate another condition.
Weight management when appropriate, carefully selected medications, and other treatments can complement exercise. Surgery is generally considered when substantial symptoms persist despite appropriate nonsurgical care.
If knee pain limits your ability to walk or affects your quality of life, explore the Orthopedic Department and Physiotherapy Department at Mouwasat Hospital for assessment and an individualized treatment plan.
Medical disclaimer: This article is intended for general health education and does not replace professional medical examination, diagnosis, or individualized treatment. Do not begin painful exercises or new medication without appropriate advice if you have a recent injury or unusual symptoms.

































