Overview:
Everyone knows about the damage smoking causes. However, a lot of people, of all ages, still smoke and end up suffering from its effects. MOH seeks to put an end to smoking and help smokers quit, with the aim of saving their lives and protecting them from diseases, as well as ensuring all members of society remain healthy and free of diseases. Smoking is not limited to just traditional cigarettes. It can also include e-cigarettes, hookah, etc.
May 31st of every year marks a day of raising awareness about the importance of combating smoking in all its forms and informing people about its hazards, including many diseases, or even death.
Facts:
Objectives:
Official date:
Globally: May 31st, 2022
Locally: Dhul-Qi’dah 1st, 1443H.
Theme Tobacco:
Threat to our environment
References:
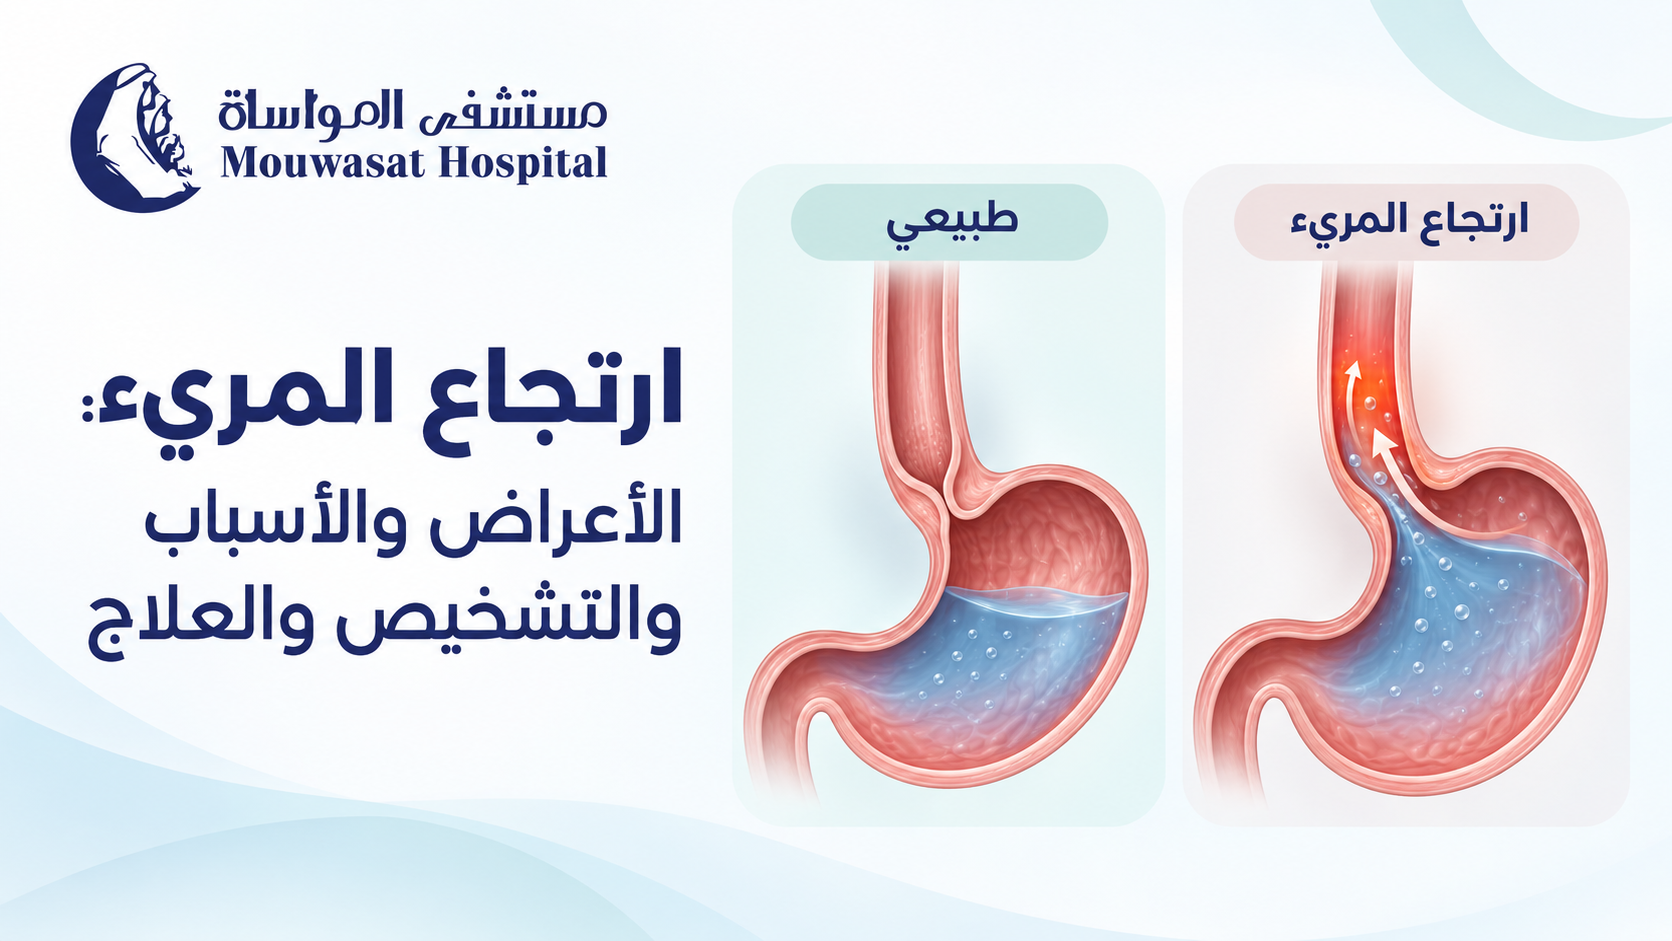
Gastroesophageal reflux occurs when stomach contents move back into the esophagus. It may cause heartburn behind the breastbone or a sour taste in the mouth. However, occasional heartburn does not necessarily mean that a person has chronic gastroesophageal reflux disease (GERD). [1]
GERD becomes more important when symptoms are frequent or troublesome, affect daily life, or lead to complications. Some patients may also experience cough, hoarseness, or swallowing problems without typical heartburn. [2]
Gastroesophageal reflux occurs when stomach contents flow back into the esophagus. GERD refers to reflux that causes repeated troublesome symptoms or complications. [1]
A muscular valve called the lower esophageal sphincter normally opens to allow food into the stomach and then closes. GERD may develop when this valve becomes weak or relaxes when it should not. [2]
Many people occasionally experience heartburn after a large meal or after lying down soon after eating. This does not automatically mean they have chronic GERD.
| Condition | Typical pattern |
|---|---|
| Occasional reflux | Occurs from time to time and then settles. |
| GERD | Symptoms are recurrent or troublesome, or reflux causes injury or complications. |
The most common symptoms are heartburn and regurgitation. [2]
For a deeper look at the symptoms, see our guide to GERD symptoms.
Yes. Some patients may experience cough, hoarseness, or throat symptoms without classic heartburn. [2]
However, these symptoms have many possible causes and should not automatically be attributed to reflux.
If you have throat or voice symptoms without obvious heartburn, read our guide to silent reflux.
When symptoms occur mainly outside the digestive system, doctors may need to consider other causes instead of assuming reflux is responsible.
GERD can occur when the lower esophageal sphincter allows stomach contents to flow back into the esophagus more often than it should.
Factors associated with GERD include:
Foods and drinks that worsen symptoms are not necessarily the underlying cause of GERD.
Coffee, chocolate, fatty meals, spicy foods, acidic foods, or mint may worsen symptoms in some people but not others.
This is why patients do not necessarily need to avoid the same long list of foods. Identifying personal triggers is usually more practical.
In many patients, GERD can initially be evaluated through symptoms and medical history. Doctors may recommend lifestyle changes and treatment without immediate testing.
Testing may be needed when symptoms suggest complications, treatment does not work as expected, or the diagnosis is uncertain.
| Test | When it may help |
|---|---|
| Upper endoscopy | Evaluates the esophagus and stomach when alarm symptoms or possible complications are present. |
| Reflux or pH monitoring | Measures reflux when the diagnosis is uncertain or objective confirmation is needed. |
| Other esophageal tests | May be used when another esophageal disorder is suspected or before selected procedures. |
No. Many patients can initially be assessed from symptoms and medical history.
Endoscopy becomes more important when there is difficulty swallowing, bleeding, unexplained weight loss, persistent symptoms despite treatment, or concern about complications.
When symptoms continue but endoscopy does not provide clear evidence of GERD, reflux monitoring may help determine whether abnormal reflux is actually present.
Persistent symptoms despite acid-suppressing medication do not necessarily mean severe reflux. The diagnosis and treatment approach may need to be reassessed.
Treatment depends on symptom severity, frequency, and whether complications are present. Management commonly includes lifestyle changes and medication, while procedures may be considered in selected patients.
For more detail, see our dedicated guide to GERD treatment.
Persistent symptoms do not always mean that more acid suppression is needed.
Learn more about the Gastroenterology & Endoscopy Department at Mouwasat Hospital and the diagnostic and therapeutic services available according to each patient's condition.
Medical assessment is appropriate when reflux symptoms are frequent, troublesome, affect daily life, or continue despite lifestyle changes or treatment.
The most common symptoms are heartburn and regurgitation. Some people may also have difficulty swallowing, cough, or hoarseness.
Many people achieve good long-term symptom control with lifestyle changes and appropriate treatment. However, GERD varies between patients and some require longer-term management.
Reflux may be associated with cough or throat symptoms in some people, but breathing difficulty and choking have many other possible causes.
GERD itself is not usually life-threatening, but persistent reflux can cause complications in some patients. Chest pain that appears to be heartburn may also have another serious cause.
No. Many cases can initially be evaluated from symptoms and medical history. Endoscopy is more useful when alarm symptoms, complications, or persistent symptoms are present.
No. Some patients have GERD without visible esophageal injury. Reflux monitoring may be used when objective confirmation is needed.
Not necessarily. Coffee worsens symptoms in some people but not everyone. Identifying personal triggers is usually more useful.
The medication may not be taken at the appropriate time, or the symptoms may have another cause. Persistent symptoms should be reassessed rather than automatically treated with higher doses.
GERD treatment depends on how often symptoms occur, how severe they are, and how well they respond to lifestyle changes and medication. Many people can control gastroesophageal reflux disease effectively with lifestyle measures and appropriate medical treatment, while others may need additional evaluation to confirm the diagnosis or check for complications.
Whether GERD can disappear completely depends on the underlying factors and the severity of the condition. Some people experience long periods without symptoms after losing excess weight, changing eating habits, and addressing factors that worsen reflux. Others may require intermittent or longer-term treatment.
The goal of GERD treatment is therefore not simply to stop heartburn temporarily. Treatment aims to control symptoms, heal esophageal inflammation when present, and reduce the risk of complications. The American College of Gastroenterology identifies proton pump inhibitors as the main medical therapy for GERD. [3]
For a broader explanation of the condition, see our guide to GERD symptoms, causes, diagnosis and treatment.
Treatment is individualized according to symptom frequency and severity, previous response to treatment, and whether warning signs or possible complications are present.
| Situation | Possible approach |
|---|---|
| Occasional mild symptoms | Lifestyle measures, identification of personal triggers and appropriate symptom-relieving medicines when needed. |
| Frequent or troublesome symptoms | A doctor may recommend acid-suppressing treatment and assess the response. |
| Symptoms despite appropriate treatment | Review how treatment is being used, reassess the diagnosis and consider further testing. |
| Difficulty swallowing or warning signs | Medical assessment and appropriate diagnostic testing rather than symptom treatment alone. |
Lifestyle measures may reduce reflux symptoms. Recommendations include avoiding lying down soon after meals, allowing two to three hours between eating and bedtime, maintaining a healthy weight, and elevating the head during sleep when appropriate. [1]
Leaving time between the last meal of the day and bedtime may be particularly helpful for people with nighttime reflux.
For people who are overweight or have obesity, weight loss may reduce GERD symptoms. [2]
Common triggers can include high-fat or fried foods, chocolate, spicy foods, tomato products, caffeine and mint. However, triggers vary between individuals. [1]
A food does not need to be eliminated simply because it appears on a general GERD list if it does not actually trigger symptoms for that individual.
Smaller meals may help some people because excessive stomach fullness can increase the likelihood of reflux.
Several types of medicines can be used for reflux. The choice depends on the severity and frequency of symptoms.
| Medicine type | What it does | Key point |
|---|---|---|
| Antacids | Neutralize stomach acid and can provide quick relief of mild symptoms. | Frequent or severe symptoms should not be managed indefinitely with antacids alone. |
| H2 blockers | Reduce the amount of acid produced by the stomach. | They may be appropriate in selected patients. |
| Proton pump inhibitors (PPIs) | More strongly reduce acid production and can help heal the esophageal lining. | They are a major medical treatment for GERD. |
NIDDK notes that PPIs are more effective than H2 blockers for treating GERD symptoms and healing the esophageal lining in many patients. [2]
There is no single medicine that is best for everyone with GERD. The right option depends on symptom frequency, severity, other medications, overall health and whether esophageal inflammation or complications are present.
Repeatedly switching medicines based on another person's experience may therefore delay appropriate evaluation when symptoms persist.
When symptoms continue, the important question is not always “Which medicine is stronger?” It may be “Is GERD definitely causing these symptoms, and is the treatment being used appropriately?”
Persistent symptoms do not automatically mean that GERD has become more severe. A doctor may consider several possibilities, including:
NIDDK recommends considering diagnostic testing when symptoms do not improve after lifestyle changes and medicines, when complications are suspected, or when another condition may be causing similar symptoms. [4]
No. Doctors can diagnose many cases initially by reviewing symptoms and medical history and may recommend treatment before ordering tests. [4]
Testing becomes more relevant when:
Upper endoscopy allows the doctor to examine the lining of the esophagus and stomach and may help identify esophagitis, complications or alternative causes of symptoms. [4]
Reflux monitoring can measure acid exposure in the esophagus and may be used in selected patients to confirm GERD or investigate persistent symptoms. [4]
Natural remedies such as herbs and honey are frequently promoted for reflux, but they should not replace proven treatment or medical assessment when symptoms are recurrent.
Some people may experience temporary relief after a particular food or drink, but temporary symptom relief does not demonstrate that the underlying problem has been treated. Natural products may also interact with medicines or be unsuitable for some people.
Persistent reflux is therefore better approached by identifying the cause of symptoms and creating an appropriate treatment plan rather than relying indefinitely on unproven home remedies.
Most people with GERD do not need surgery. Procedures may be considered in selected patients with confirmed GERD when symptoms remain problematic despite an appropriate treatment plan or when other clinical factors make an intervention reasonable.
NIDDK notes that surgery may be considered when symptoms do not improve with lifestyle changes and medicines, or in selected patients discussing alternatives to long-term medication with their doctor. [2]
Treatment success is not measured only by whether heartburn disappears for a day or two. Doctors may consider:
For this reason, the duration of treatment can differ significantly between patients.
Medical assessment is important when reflux is frequent, symptoms persist despite medication, swallowing becomes difficult, vomiting continues, or unexplained weight loss occurs. [1]
Mouwasat Hospital's Gastroenterology & Endoscopy Department provides diagnostic and therapeutic services for digestive disorders, including the evaluation of reflux disease.
Treatment duration depends on symptom severity, whether esophagitis is present and how well the patient responds. Some people need a defined course of treatment, while others need longer-term management.
Yes. Symptoms can return, particularly when factors that promote reflux remain or when GERD is chronic. Recurrence does not necessarily mean treatment has failed, but the management plan may need to be reviewed.
Lifestyle measures may be sufficient for some people with mild symptoms, while recurrent or more severe symptoms may require medication or medical assessment.
Not necessarily. If coffee consistently worsens your symptoms, reducing or avoiding it may help. If it is not a personal trigger, complete avoidance is not automatically required.
Milk may temporarily relieve heartburn in some people, but it does not treat GERD itself. Higher-fat milk may also worsen symptoms in some individuals. [1]
No. The diagnosis and the way treatment is being used should first be reviewed. Further testing may be needed to confirm that reflux is actually responsible for the symptoms before an invasive procedure is considered.
GERD treatment depends on how often symptoms occur, how severe they are, and how well they respond to lifestyle changes and medication. Many people can control gastroesophageal reflux disease effectively with lifestyle measures and appropriate medical treatment, while others may need additional evaluation to confirm the diagnosis or check for complications.
Whether GERD can disappear completely depends on the underlying factors and the severity of the condition. Some people experience long periods without symptoms after losing excess weight, changing eating habits, and addressing factors that worsen reflux. Others may require intermittent or longer-term treatment.
The goal of GERD treatment is therefore not simply to stop heartburn temporarily. Treatment aims to control symptoms, heal esophageal inflammation when present, and reduce the risk of complications. The American College of Gastroenterology identifies proton pump inhibitors as the main medical therapy for GERD. [3]
For a broader explanation of the condition, see our guide to GERD symptoms, causes, diagnosis and treatment.
Treatment is individualized according to symptom frequency and severity, previous response to treatment, and whether warning signs or possible complications are present.
| Situation | Possible approach |
|---|---|
| Occasional mild symptoms | Lifestyle measures, identification of personal triggers and appropriate symptom-relieving medicines when needed. |
| Frequent or troublesome symptoms | A doctor may recommend acid-suppressing treatment and assess the response. |
| Symptoms despite appropriate treatment | Review how treatment is being used, reassess the diagnosis and consider further testing. |
| Difficulty swallowing or warning signs | Medical assessment and appropriate diagnostic testing rather than symptom treatment alone. |
Lifestyle measures may reduce reflux symptoms. Recommendations include avoiding lying down soon after meals, allowing two to three hours between eating and bedtime, maintaining a healthy weight, and elevating the head during sleep when appropriate. [1]
Leaving time between the last meal of the day and bedtime may be particularly helpful for people with nighttime reflux.
For people who are overweight or have obesity, weight loss may reduce GERD symptoms. [2]
Common triggers can include high-fat or fried foods, chocolate, spicy foods, tomato products, caffeine and mint. However, triggers vary between individuals. [1]
A food does not need to be eliminated simply because it appears on a general GERD list if it does not actually trigger symptoms for that individual.
Smaller meals may help some people because excessive stomach fullness can increase the likelihood of reflux.
Several types of medicines can be used for reflux. The choice depends on the severity and frequency of symptoms.
| Medicine type | What it does | Key point |
|---|---|---|
| Antacids | Neutralize stomach acid and can provide quick relief of mild symptoms. | Frequent or severe symptoms should not be managed indefinitely with antacids alone. |
| H2 blockers | Reduce the amount of acid produced by the stomach. | They may be appropriate in selected patients. |
| Proton pump inhibitors (PPIs) | More strongly reduce acid production and can help heal the esophageal lining. | They are a major medical treatment for GERD. |
NIDDK notes that PPIs are more effective than H2 blockers for treating GERD symptoms and healing the esophageal lining in many patients. [2]
There is no single medicine that is best for everyone with GERD. The right option depends on symptom frequency, severity, other medications, overall health and whether esophageal inflammation or complications are present.
Repeatedly switching medicines based on another person's experience may therefore delay appropriate evaluation when symptoms persist.
When symptoms continue, the important question is not always “Which medicine is stronger?” It may be “Is GERD definitely causing these symptoms, and is the treatment being used appropriately?”
Persistent symptoms do not automatically mean that GERD has become more severe. A doctor may consider several possibilities, including:
NIDDK recommends considering diagnostic testing when symptoms do not improve after lifestyle changes and medicines, when complications are suspected, or when another condition may be causing similar symptoms. [4]
No. Doctors can diagnose many cases initially by reviewing symptoms and medical history and may recommend treatment before ordering tests. [4]
Testing becomes more relevant when:
Upper endoscopy allows the doctor to examine the lining of the esophagus and stomach and may help identify esophagitis, complications or alternative causes of symptoms. [4]
Reflux monitoring can measure acid exposure in the esophagus and may be used in selected patients to confirm GERD or investigate persistent symptoms. [4]
Natural remedies such as herbs and honey are frequently promoted for reflux, but they should not replace proven treatment or medical assessment when symptoms are recurrent.
Some people may experience temporary relief after a particular food or drink, but temporary symptom relief does not demonstrate that the underlying problem has been treated. Natural products may also interact with medicines or be unsuitable for some people.
Persistent reflux is therefore better approached by identifying the cause of symptoms and creating an appropriate treatment plan rather than relying indefinitely on unproven home remedies.
Most people with GERD do not need surgery. Procedures may be considered in selected patients with confirmed GERD when symptoms remain problematic despite an appropriate treatment plan or when other clinical factors make an intervention reasonable.
NIDDK notes that surgery may be considered when symptoms do not improve with lifestyle changes and medicines, or in selected patients discussing alternatives to long-term medication with their doctor. [2]
Treatment success is not measured only by whether heartburn disappears for a day or two. Doctors may consider:
For this reason, the duration of treatment can differ significantly between patients.
Medical assessment is important when reflux is frequent, symptoms persist despite medication, swallowing becomes difficult, vomiting continues, or unexplained weight loss occurs. [1]
Mouwasat Hospital's Gastroenterology & Endoscopy Department provides diagnostic and therapeutic services for digestive disorders, including the evaluation of reflux disease.
Treatment duration depends on symptom severity, whether esophagitis is present and how well the patient responds. Some people need a defined course of treatment, while others need longer-term management.
Yes. Symptoms can return, particularly when factors that promote reflux remain or when GERD is chronic. Recurrence does not necessarily mean treatment has failed, but the management plan may need to be reviewed.
Lifestyle measures may be sufficient for some people with mild symptoms, while recurrent or more severe symptoms may require medication or medical assessment.
Not necessarily. If coffee consistently worsens your symptoms, reducing or avoiding it may help. If it is not a personal trigger, complete avoidance is not automatically required.
Milk may temporarily relieve heartburn in some people, but it does not treat GERD itself. Higher-fat milk may also worsen symptoms in some individuals. [1]
No. The diagnosis and the way treatment is being used should first be reviewed. Further testing may be needed to confirm that reflux is actually responsible for the symptoms before an invasive procedure is considered.
Gastroesophageal reflux occurs when stomach contents move back into the esophagus. It may cause heartburn behind the breastbone or a sour taste in the mouth. However, occasional heartburn does not necessarily mean that a person has chronic gastroesophageal reflux disease (GERD). [1]
GERD becomes more important when symptoms are frequent or troublesome, affect daily life, or lead to complications. Some patients may also experience cough, hoarseness, or swallowing problems without typical heartburn. [2]
Gastroesophageal reflux occurs when stomach contents flow back into the esophagus. GERD refers to reflux that causes repeated troublesome symptoms or complications. [1]
A muscular valve called the lower esophageal sphincter normally opens to allow food into the stomach and then closes. GERD may develop when this valve becomes weak or relaxes when it should not. [2]
Many people occasionally experience heartburn after a large meal or after lying down soon after eating. This does not automatically mean they have chronic GERD.
| Condition | Typical pattern |
|---|---|
| Occasional reflux | Occurs from time to time and then settles. |
| GERD | Symptoms are recurrent or troublesome, or reflux causes injury or complications. |
The most common symptoms are heartburn and regurgitation. [2]
For a deeper look at the symptoms, see our guide to GERD symptoms.
Yes. Some patients may experience cough, hoarseness, or throat symptoms without classic heartburn. [2]
However, these symptoms have many possible causes and should not automatically be attributed to reflux.
If you have throat or voice symptoms without obvious heartburn, read our guide to silent reflux.
When symptoms occur mainly outside the digestive system, doctors may need to consider other causes instead of assuming reflux is responsible.
GERD can occur when the lower esophageal sphincter allows stomach contents to flow back into the esophagus more often than it should.
Factors associated with GERD include:
Foods and drinks that worsen symptoms are not necessarily the underlying cause of GERD.
Coffee, chocolate, fatty meals, spicy foods, acidic foods, or mint may worsen symptoms in some people but not others.
This is why patients do not necessarily need to avoid the same long list of foods. Identifying personal triggers is usually more practical.
In many patients, GERD can initially be evaluated through symptoms and medical history. Doctors may recommend lifestyle changes and treatment without immediate testing.
Testing may be needed when symptoms suggest complications, treatment does not work as expected, or the diagnosis is uncertain.
| Test | When it may help |
|---|---|
| Upper endoscopy | Evaluates the esophagus and stomach when alarm symptoms or possible complications are present. |
| Reflux or pH monitoring | Measures reflux when the diagnosis is uncertain or objective confirmation is needed. |
| Other esophageal tests | May be used when another esophageal disorder is suspected or before selected procedures. |
No. Many patients can initially be assessed from symptoms and medical history.
Endoscopy becomes more important when there is difficulty swallowing, bleeding, unexplained weight loss, persistent symptoms despite treatment, or concern about complications.
When symptoms continue but endoscopy does not provide clear evidence of GERD, reflux monitoring may help determine whether abnormal reflux is actually present.
Persistent symptoms despite acid-suppressing medication do not necessarily mean severe reflux. The diagnosis and treatment approach may need to be reassessed.
Treatment depends on symptom severity, frequency, and whether complications are present. Management commonly includes lifestyle changes and medication, while procedures may be considered in selected patients.
For more detail, see our dedicated guide to GERD treatment.
Persistent symptoms do not always mean that more acid suppression is needed.
Learn more about the Gastroenterology & Endoscopy Department at Mouwasat Hospital and the diagnostic and therapeutic services available according to each patient's condition.
Medical assessment is appropriate when reflux symptoms are frequent, troublesome, affect daily life, or continue despite lifestyle changes or treatment.
The most common symptoms are heartburn and regurgitation. Some people may also have difficulty swallowing, cough, or hoarseness.
Many people achieve good long-term symptom control with lifestyle changes and appropriate treatment. However, GERD varies between patients and some require longer-term management.
Reflux may be associated with cough or throat symptoms in some people, but breathing difficulty and choking have many other possible causes.
GERD itself is not usually life-threatening, but persistent reflux can cause complications in some patients. Chest pain that appears to be heartburn may also have another serious cause.
No. Many cases can initially be evaluated from symptoms and medical history. Endoscopy is more useful when alarm symptoms, complications, or persistent symptoms are present.
No. Some patients have GERD without visible esophageal injury. Reflux monitoring may be used when objective confirmation is needed.
Not necessarily. Coffee worsens symptoms in some people but not everyone. Identifying personal triggers is usually more useful.
The medication may not be taken at the appropriate time, or the symptoms may have another cause. Persistent symptoms should be reassessed rather than automatically treated with higher doses.
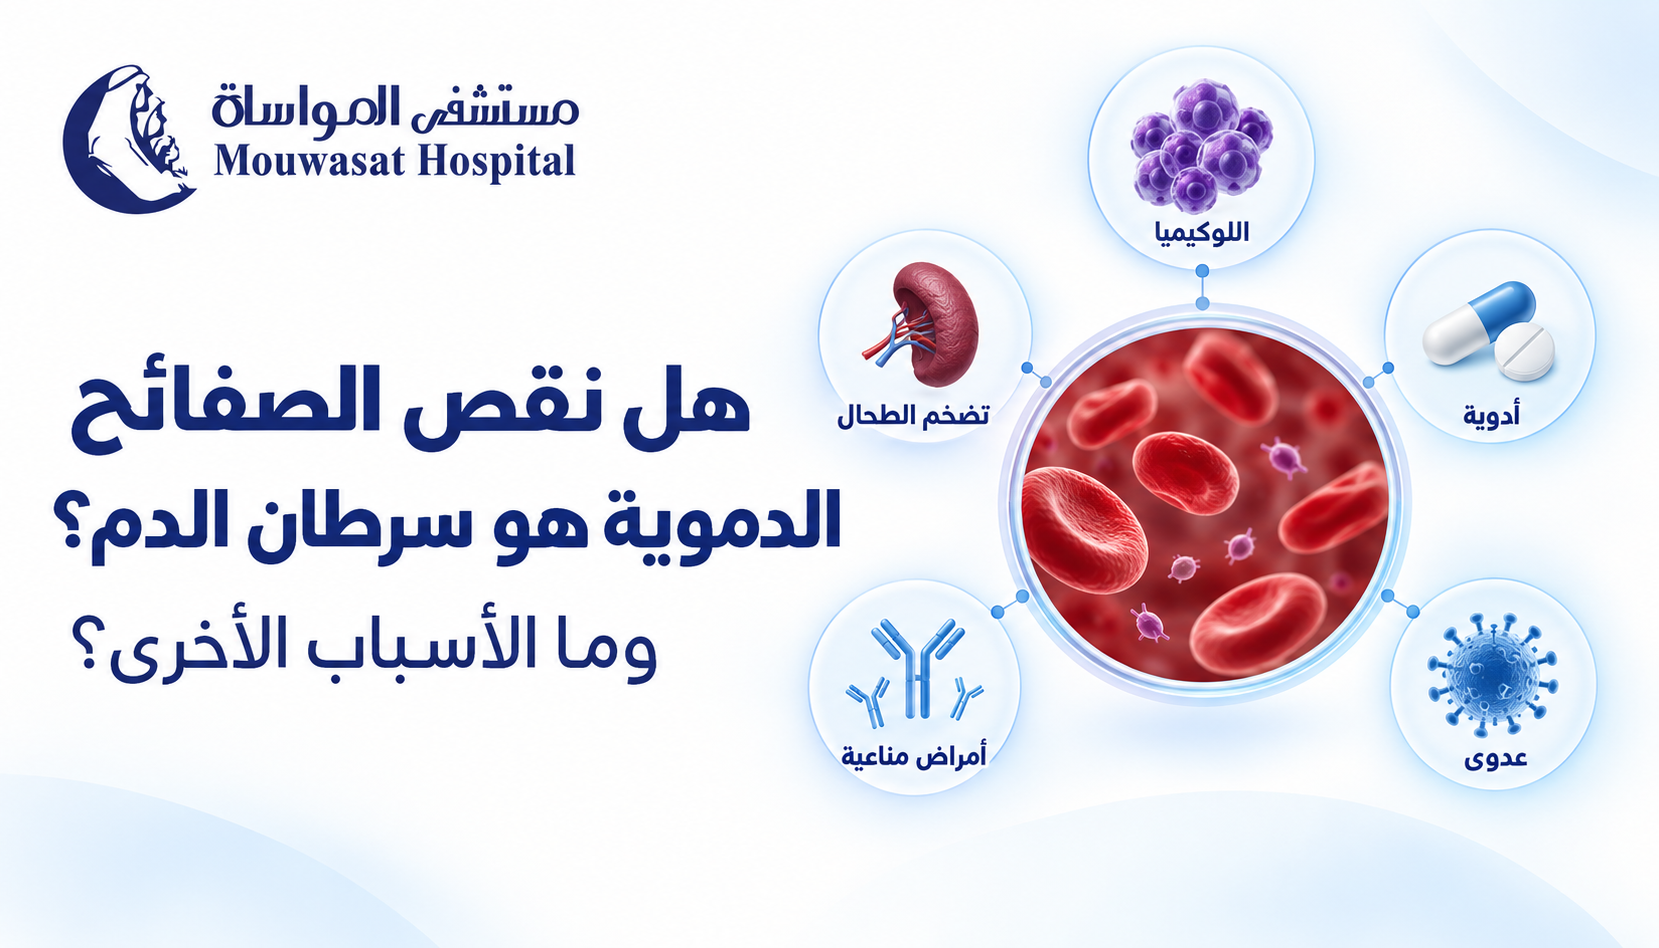
A low platelet count does not automatically mean that someone has leukemia or another blood cancer. Thrombocytopenia has many possible causes, including infections, medicines, immune disorders, liver or spleen conditions, nutritional deficiencies, and certain bone marrow disorders.
Doctors therefore do not interpret the platelet count in isolation. They also review the rest of the complete blood count, symptoms, medical history, and blood smear before deciding whether further testing is needed.[1][2]
Platelets are small blood components that help form clots and stop bleeding after a blood vessel is injured.
Thrombocytopenia means that the platelet count is below the normal range, generally below about 150,000 platelets per microliter of blood, although laboratory reference ranges may vary slightly.[1]
Mild thrombocytopenia may cause no symptoms and may be discovered during routine blood testing. More significant reductions can increase the tendency to bruise or bleed.
No. A low platelet count by itself does not mean that a person has blood cancer.
Platelet counts can fall because of immune conditions, infections, medicines, liver or spleen disorders, and many other causes.[1][3]
Leukemia can affect bone marrow and reduce normal platelet production in some patients, but it is only one possible cause of thrombocytopenia.[3][4]
A low platelet count is a laboratory finding that needs an explanation, not a diagnosis by itself. Doctors look at why the platelet count is low and what the rest of the blood count shows.
For a broader overview, read: Blood Cancers: Types, Symptoms, Diagnosis and Treatment
Many leukemias begin in blood-forming tissues, most often the bone marrow. As abnormal cells increase, they may interfere with the production of normal blood cells, including platelets.[4]
Some patients with leukemia may therefore have:
However, blood count patterns vary between leukemia types and patients. A platelet count alone cannot confirm or rule out leukemia.
Read also: Leukemia: Early Symptoms, Types and How It Is Diagnosed
Many conditions unrelated to cancer can cause thrombocytopenia.[1][3]
Rather than thinking of thrombocytopenia as one disease, most causes can be understood through three major mechanisms.[1]
| Mechanism | What happens? | Examples |
|---|---|---|
| Reduced production | The bone marrow does not produce enough platelets. | Certain bone marrow diseases, leukemia, and some medicines or cancer treatments. |
| Increased destruction or consumption | Platelets are produced but are destroyed or used faster than they can be replaced. | Immune thrombocytopenia and certain clotting disorders. |
| Sequestration in the spleen | The spleen holds a larger proportion of platelets, leaving fewer circulating in the blood. | An enlarged spleen and certain liver or splenic conditions. |
An important part of interpreting a low platelet count is determining whether platelets are the only abnormal blood cell line.
| CBC pattern | How it may guide evaluation |
|---|---|
| Low platelets with otherwise normal CBC | May direct evaluation toward conditions primarily affecting platelets, such as immune thrombocytopenia or drug-related thrombocytopenia, after other causes are considered.[5] |
| Low platelets plus red or white blood cell abnormalities | Usually requires a broader evaluation for conditions that can affect several blood cell types, including bone marrow disorders and many other possible causes. |
Even multiple abnormal CBC values do not automatically mean cancer. They simply provide more information about which causes need to be investigated.
Yes. A phenomenon called pseudothrombocytopenia can occur when platelets clump together inside the blood collection tube, causing automated equipment to report an artificially low platelet count.[5]
In appropriate cases, a doctor may repeat the blood count using another collection method and review a peripheral blood smear before concluding that true thrombocytopenia is present.
One unexpectedly low platelet result is not always the end of the diagnostic process. Sometimes the first step is confirming that the low result is real before investigating complex medical causes.
Mild thrombocytopenia may cause no symptoms. As platelet levels fall further, bleeding-related symptoms may become more noticeable.[1]
Risk is not determined by the platelet number alone. The degree of thrombocytopenia, active bleeding, how quickly the count is changing, medicines, and other medical conditions all influence the level of concern.[1][5]
Bleeding that does not stop or very severe thrombocytopenia accompanied by symptoms requires prompt medical assessment.
Evaluation begins with the CBC, symptoms, medical history, and medicines. Further testing depends on the findings.[2]
| Step | Why it may be useful |
|---|---|
| Repeat CBC when appropriate | Confirms whether thrombocytopenia persists and reviews the other blood cell counts. |
| Peripheral blood smear | Allows evaluation of blood cells and may identify platelet clumping or other abnormalities. |
| Medical and medication review | Helps identify medicines, infections, or medical conditions that may explain the low count. |
| Additional blood or imaging tests | May be selected according to suspected liver, spleen, immune, or infectious causes. |
| Bone marrow testing when needed | May help determine whether a bone marrow disorder is affecting blood cell production.[2] |
Treatment depends on why the platelet count is low, how low it is, and whether bleeding or other symptoms are present.[1]
Some people with mild thrombocytopenia may only require monitoring, while others need treatment directed at the underlying cause. This may involve addressing a medical condition or modifying a medication under medical supervision.
Trying to raise the platelet count without first identifying the cause may not address the underlying problem.
The Hemato-Oncology Department at Mouwasat Hospital provides specialized assessment for blood and platelet disorders as well as hematologic cancers, with diagnostic testing and management tailored to each patient's condition.
Specialist evaluation may be appropriate when thrombocytopenia is persistent, severe, unexplained, or accompanied by abnormalities in other blood cells.
No. Many conditions can cause thrombocytopenia. Leukemia is only one possible cause, and diagnosis depends on the rest of the blood count, symptoms, and additional testing when necessary.[1][4]
No. Immune disorders, infections, medicines, liver or spleen disease, and several other conditions can also lower platelet counts.
No. Isolated thrombocytopenia has several possible causes. Immune thrombocytopenia and medication-related causes are among the conditions doctors consider when the rest of the blood count is otherwise normal.[5]
Yes. Platelet clumping inside the sample tube can cause an artificially low result known as pseudothrombocytopenia. Repeating the test or examining a peripheral blood smear may help confirm whether the result is genuine.[5]
Concern increases when the platelet count is very low, when active bleeding is present, or when other medical factors increase bleeding risk. The number should always be interpreted in clinical context.
Most cases are not life-threatening, but severe thrombocytopenia with serious bleeding can be an emergency and requires prompt medical attention.[1]
There is no single diet that treats all causes of thrombocytopenia. Correcting a nutritional deficiency may help when it is the cause, while immune, medication-related, or bone marrow causes require treatment directed at the underlying condition.
No. Blood count findings vary between leukemia types and individual patients. Platelet levels alone cannot diagnose or exclude leukemia.
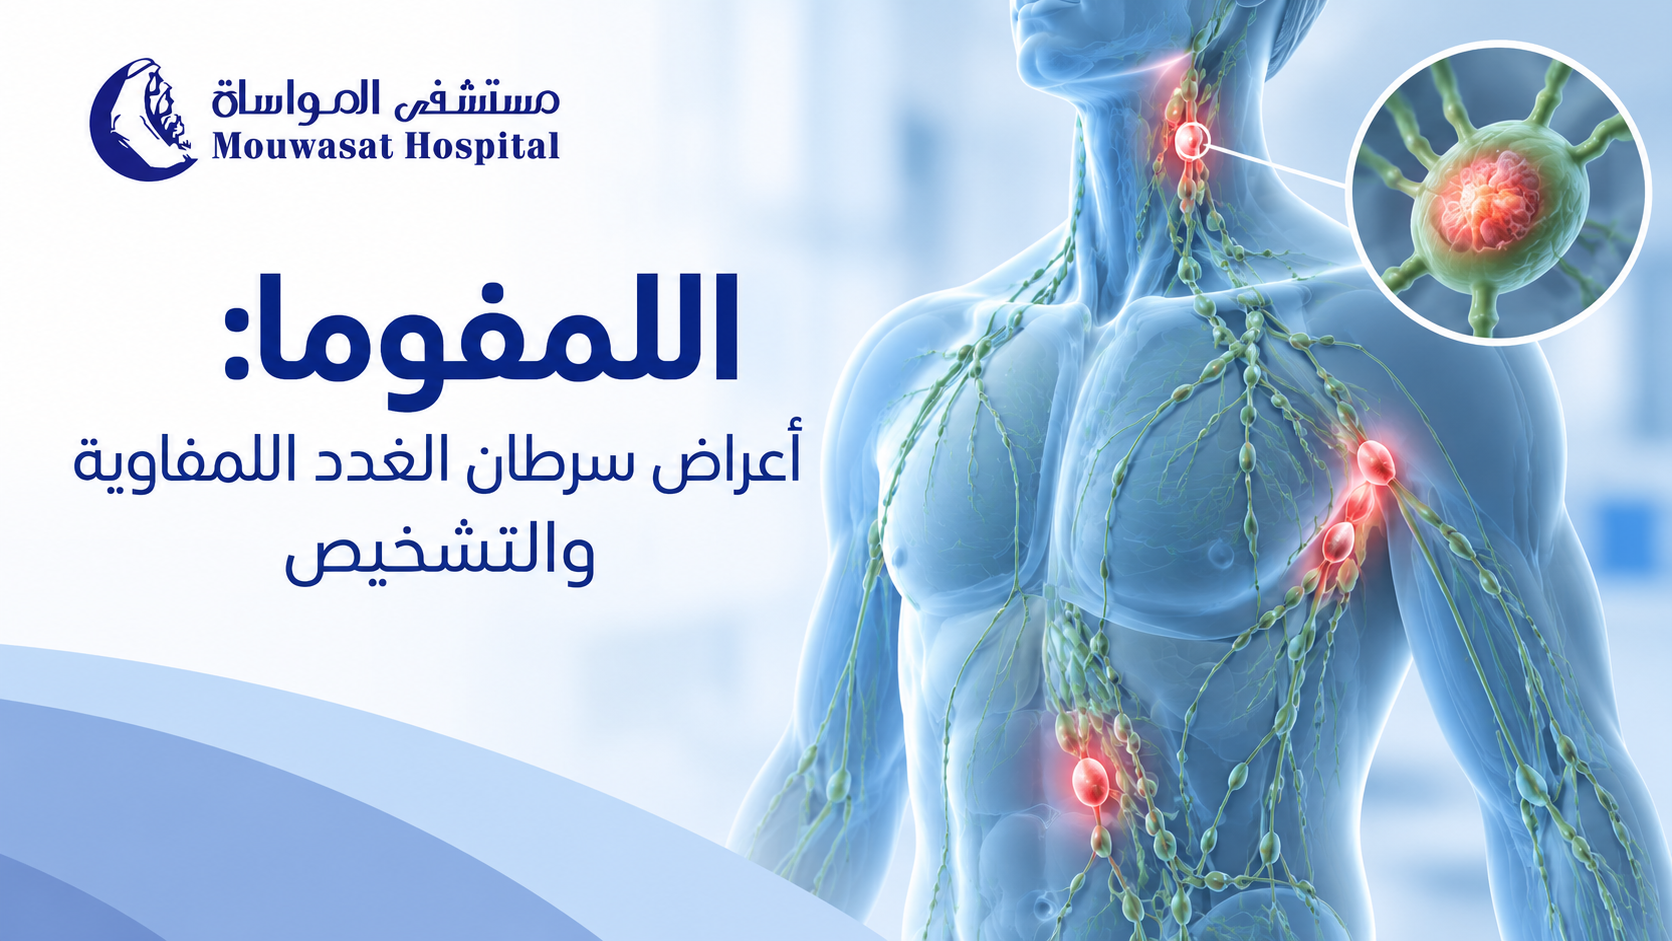
Lymphoma is a group of cancers that begin in cells of the lymphatic system, which is part of the immune system. The two main groups are Hodgkin lymphoma and non-Hodgkin lymphoma, and each includes different subtypes with different patterns of growth and treatment.[1]
Swollen lymph nodes can occur with lymphoma, particularly in the neck, underarm, or groin. However, lymph nodes also commonly enlarge because of infections and other non-cancerous conditions, so an enlarged lymph node alone cannot diagnose lymphoma.[2][3]
Lymphoma is a broad term for cancers that begin in lymphocytes, a type of white blood cell that plays an important role in the immune system.[1]
Because lymphatic tissue is found throughout the body, lymphoma can begin in lymph nodes or in other tissues and organs that contain lymphocytes.
For a broader overview, read: Blood Cancers: Types, Symptoms, Diagnosis and Treatment
Lymphomas are divided mainly into:
Non-Hodgkin lymphoma is not one disease. It includes many subtypes, some of which grow slowly while others develop more rapidly.[1][3]
| Feature | Hodgkin lymphoma | Non-Hodgkin lymphoma |
|---|---|---|
| Group | A defined group of lymphomas with characteristic cellular features. | A large group containing many different lymphoma subtypes. |
| Cells | Classic Hodgkin lymphoma typically includes Reed-Sternberg cells on tissue examination. | Includes lymphomas arising from different lymphocyte types, including B cells and T cells. |
| Growth pattern | Varies according to the individual disease and stage. | Includes both indolent, slower-growing and aggressive, faster-growing forms. |
| Treatment | Depends on subtype, stage, and patient factors. | Varies considerably according to subtype, growth rate, and stage. |
Lymphoma symptoms vary according to the type of lymphoma, where it develops, and how extensive the disease is. Not every patient develops all possible symptoms.[2][3]
Possible symptoms include:
Most of these symptoms are not specific to lymphoma. Swollen lymph nodes, for example, are commonly caused by infections, so lymphoma cannot be diagnosed from symptoms or lymph node size alone.
Lymphoma can cause enlargement of one or more lymph nodes, sometimes without pain. Enlarged nodes may occur in the neck, underarm, groin, or deeper inside the body.[2][3]
There is no single feature that allows a person to determine at home whether a lymph node is cancerous. Its location, size, duration, associated symptoms, and the patient's medical history all influence the medical evaluation.
No. A swollen lymph node under the jaw does not automatically mean lymphoma.
These lymph nodes are close to the mouth, throat, and teeth and may enlarge with many infections or inflammatory conditions in these areas. In many cases, they become smaller after the underlying problem resolves.
Medical evaluation may be appropriate when swelling persists without an obvious cause, continues to enlarge, or occurs with unexplained weight loss, persistent fever, drenching night sweats, or other concerning symptoms.
Doctors may pay particular attention to three systemic symptoms in some lymphomas:
These are sometimes referred to as B symptoms and can contribute to staging and assessment in certain lymphomas.[2][3]
However, the absence of B symptoms does not rule out lymphoma. Some people with lymphoma may have enlarged lymph nodes without fever, night sweats, or weight loss.
A complete blood count measures red blood cells, white blood cells, and platelets. It may help doctors assess a patient's general health and identify abnormalities in blood cell counts.[2]
However, a CBC does not diagnose lymphoma, and blood counts may remain within the normal range in some patients, particularly when the bone marrow or normal blood cell production is not affected.[5]
A normal CBC cannot rule out lymphoma. Unlike some leukemias that may cause obvious blood count abnormalities, lymphoma usually begins in the lymphatic system, so tissue evaluation becomes particularly important when the disease is suspected.
Read also: Leukemia: Early Symptoms, Types and How It Is Diagnosed
Diagnosis begins with a review of symptoms and medical history and a physical examination, including assessment of enlarged lymph nodes. Further testing is then selected according to the findings.[2][3]
| Test | Role |
|---|---|
| Physical examination | Assesses lymph nodes, symptoms, and other clinical findings. |
| Blood tests | Help assess blood cells, organ function, and general health but do not confirm lymphoma by themselves. |
| Lymph node or tissue biopsy | Allows tissue examination to determine whether lymphoma cells are present and identify the subtype. |
| Specialized tissue tests | Help classify the lymphoma and identify cellular characteristics. |
| CT or PET/CT | Helps identify disease locations and extent and supports staging and response assessment. |
There are many types of lymphoma, and treatment can differ significantly between them. Doctors therefore need to identify the type of abnormal cells rather than simply determine that a lymph node is enlarged.[3]
A lymph node or tissue biopsy is therefore a key part of diagnosis. A pathologist examines the sample and additional laboratory tests may be used to classify the lymphoma more precisely.[2][3]
Imaging can show enlarged lymph nodes or areas of increased activity, but it cannot always determine why they are abnormal or identify the exact disease subtype. Tissue examination allows doctors to determine whether cancer cells are present and classify the lymphoma.
CT or PET/CT may be used to help identify where lymphoma is located, determine its extent, and assess response to treatment in selected lymphoma types.[2][3]
However, an area of increased activity on PET/CT does not by itself prove lymphoma, because inflammation and other conditions can also cause increased activity. Imaging findings are interpreted together with biopsy results and other tests.
Treatment depends on the exact lymphoma subtype, stage, growth rate, patient age and health, and biological characteristics of the disease.[2][3]
Depending on the condition, treatment may include:
The word “lymphoma” alone is therefore not enough to select treatment. Precise subtype identification is an essential part of treatment planning.
The Hemato-Oncology Department at Mouwasat Hospital provides specialized evaluation, diagnosis, and treatment for hematologic cancers, including lymphomas, with care tailored to the disease subtype and each patient's condition.
Swollen lymph nodes are commonly caused by conditions other than cancer, but some situations deserve medical evaluation.
Consider seeing a doctor if you have:
These signs do not confirm lymphoma, but evaluation can help identify the underlying cause.
Lymphoma is a group of cancers that begin in cells of the lymphatic system. The two main groups are Hodgkin lymphoma and non-Hodgkin lymphoma.[1]
A painless swollen lymph node can be an early symptom in some patients. Other possible symptoms include fever, drenching night sweats, unexplained weight loss, and fatigue. No single symptom confirms lymphoma.[2][3]
No. Lymph nodes under the jaw often enlarge because of dental, mouth, throat, or other infections. Persistent or unexplained swelling should be medically evaluated.
Pain or lack of pain alone cannot reliably confirm or rule out lymphoma. Doctors consider the node's duration, location, size, associated symptoms, and other findings.
A CBC may show blood cell abnormalities in some patients, but it does not diagnose lymphoma and can remain normal in some cases.[5]
No. Lymphoma begins in the lymphatic system and may not affect blood counts, particularly when the bone marrow and normal blood cell production are not involved. Diagnosis relies on clinical evaluation and tissue biopsy when indicated.
PET/CT does not confirm lymphoma by itself. It helps show disease locations and extent, while tissue examination is generally needed to establish the diagnosis and subtype.[2][3]
Treatment outcomes vary widely between lymphoma subtypes, and many lymphomas can respond well to treatment. Prognosis depends on the exact type, stage, patient factors, and response to therapy.
Blood cancers are a group of cancers that affect the blood, bone marrow, or lymphatic system. They differ in how they develop, how quickly they progress, and how they are treated, which means that “blood cancer” does not refer to a single disease.
The main types include leukemia, lymphoma, and multiple myeloma. Depending on the type, symptoms may include persistent fatigue, frequent infections, easy bruising or bleeding, or swollen lymph nodes. However, these symptoms can also occur with many conditions that are not cancer.[1]
Blood cancers begin in blood-forming tissues such as the bone marrow or in cells of the immune system. Examples include leukemia, lymphoma, and multiple myeloma.[1]
For this reason, blood cancers do not all behave in the same way. One type may begin in bone marrow, while another begins in the lymphatic system or in a particular type of blood cell.
The term “blood cancer” is sometimes used to mean leukemia, but blood cancers more broadly also include lymphoma and multiple myeloma.
There are many different blood cancers, but three of the best-known groups are:
| Type | Where does it begin? | Possible symptoms |
|---|---|---|
| Leukemia | Blood-forming tissues such as bone marrow. | Fatigue, frequent infections, bruising or bleeding, fever, or paleness. |
| Lymphoma | Cells of the lymphatic system. | Swollen lymph nodes, fatigue, fever, night sweats, or unexplained weight loss in some patients. |
| Multiple myeloma | Plasma cells in the bone marrow. | Fatigue, bone pain, frequent infections, or abnormalities in some laboratory tests. |
Leukemia is a group of cancers that begin in blood-forming tissues such as the bone marrow and lead to the production of abnormal blood cells.[2]
There are several types of leukemia. Some grow quickly and are described as acute, while others develop more slowly and are described as chronic. Leukemias are also classified according to the type of blood cell affected.
Lymphoma is a broad group of cancers that begin in cells of the lymphatic system, which is part of the immune system. The two main groups are Hodgkin lymphoma and non-Hodgkin lymphoma.[3]
Possible symptoms may include swollen lymph nodes, fatigue, fever, night sweats, or unexplained weight loss. However, swollen lymph nodes are commonly caused by infections and do not by themselves mean that someone has lymphoma.
Multiple myeloma is a cancer involving plasma cells, a type of white blood cell found in the bone marrow. Plasma cells normally help produce antibodies that protect the body from infection.[4]
Multiple myeloma may affect the bones and normal blood cell production, and in some people it may be associated with anemia, bone pain, frequent infections, kidney problems, or changes in calcium levels.
Symptoms vary depending on the type of blood cancer, the cells affected, and how quickly the disease develops. Some blood cancers may cause few or no obvious symptoms at first.
Possible symptoms can include:
Having one or more of these symptoms does not necessarily mean that a person has blood cancer. Many can also result from common conditions such as infections, anemia, or other blood disorders.
No. Bruising and bleeding have many possible causes and do not automatically indicate blood cancer.
However, some leukemias can affect platelet production, which may make bruising or bleeding easier in some patients.
Healthy white blood cells play an important role in fighting infection. Some blood cancers can affect how these cells are produced or how well they function.
This can make infections more frequent in some patients. However, recurrent infections have many other possible causes and cannot be used alone to diagnose blood cancer.
The tests used depend on the symptoms and the specific disease being considered. There is no single test that diagnoses every type of blood cancer.
| Test | Possible role |
|---|---|
| Complete blood count (CBC) | Measures red blood cells, white blood cells, and platelets and may identify changes that need further assessment. |
| Blood sample examination | May help doctors assess blood cells when appropriate. |
| Bone marrow testing | May be used to diagnose leukemia, myeloma, and certain other blood disorders. |
| Lymph node biopsy | May be required when lymphoma is suspected. |
| Imaging and other tests | May help evaluate the location and extent of disease depending on the type of blood cancer. |
Blood cancers do not all produce the same laboratory findings. Some leukemias may cause clear changes in circulating blood cells, while diagnosing lymphoma or myeloma may require different tests. Diagnosis therefore does not depend on a single blood test.
Some blood cancers, particularly certain leukemias, may cause changes in a complete blood count, such as unusually high or low levels of specific blood cells or platelets.
However, a blood test alone cannot always confirm blood cancer or identify the exact type. Further testing may be needed depending on the results and symptoms.
Abnormal white blood cell or platelet counts can also occur for many reasons unrelated to cancer, so laboratory results need to be interpreted in the context of the patient's overall health.
Treatment depends on the exact type of blood cancer, how quickly it is developing, its biological features, the patient's age, and overall health.
Depending on the condition, treatment options may include:
There is no single treatment plan that is suitable for every blood cancer or every patient.[2][3][4]
The Hemato-Oncology Department at Mouwasat Hospital provides specialized care for blood disorders and hematologic cancers, including evaluation, diagnosis, treatment planning, and follow-up.
Specialist assessment can help interpret blood test results correctly and determine whether additional investigations are needed.
Many possible symptoms of blood cancer can be caused by other conditions. However, persistent or unexplained symptoms should be medically assessed.
Consider medical evaluation for:
These findings do not necessarily mean cancer is present, but medical assessment can help identify the underlying cause.
Leukemia is a type of blood cancer, but the broader term also includes lymphoma and multiple myeloma.[1]
Three of the main groups are leukemia, lymphoma, and multiple myeloma. Each group also includes different subtypes with different characteristics and treatments.
Fatigue can occur in some people with blood cancer, particularly when anemia is present, but fatigue is very common and has many other possible causes.
No. Some leukemias may affect platelet levels and increase bruising, but there are many other causes of frequent bruising.
No. Low platelets have many possible causes. The result needs to be interpreted together with other blood counts, symptoms, medical history, and any additional tests that may be needed.
A CBC may reveal abnormalities that require further investigation, but it cannot confirm every blood cancer or identify the exact type on its own.
No. Infections are a common cause of swollen lymph nodes. Persistent swelling or swelling accompanied by other unexplained symptoms should be assessed by a doctor.
Treatment options and outcomes vary greatly depending on the specific type of blood cancer, its characteristics, the patient's age, overall health, and response to treatment.
Leukemia is a group of blood cancers that begin in blood-forming tissues, most often the bone marrow. Different types of leukemia affect different blood cells and may develop quickly or slowly, which is why symptoms and treatment vary from one type to another.[1]
Possible symptoms include persistent fatigue, fever, frequent infections, and easy bruising or bleeding. However, these symptoms can also occur with many other conditions and cannot diagnose leukemia on their own.[2]
Leukemia is a group of cancers that begin in blood-forming cells. In many cases, it starts in the bone marrow, where abnormal blood cells grow and can reduce the space available for healthy blood cells.[1][3]
As abnormal cells build up, the body may have fewer healthy cells available to carry oxygen, fight infection, or control bleeding. This helps explain symptoms such as fatigue, infections, and easy bruising or bleeding.[3]
For a broader overview, read: Blood Cancers: Types, Symptoms, Diagnosis and Treatment
Leukemia is usually classified according to how quickly it develops and the type of blood-forming cell involved.[3]
| Type | Abbreviation | Main feature |
|---|---|---|
| Acute lymphoblastic leukemia | ALL | An acute leukemia involving lymphoid cells that develops quickly. |
| Acute myeloid leukemia | AML | An acute leukemia involving myeloid cells that develops quickly. |
| Chronic lymphocytic leukemia | CLL | A chronic leukemia involving lymphocytes that usually develops more slowly. |
| Chronic myeloid leukemia | CML | A chronic leukemia involving myeloid cells that usually develops more slowly. |
The main difference is how quickly the disease develops and how mature the abnormal cells are.
This is why the word “leukemia” alone does not determine treatment. Identifying the exact type is essential.[1]
Early leukemia symptoms can be non-specific and may resemble common conditions such as infections or anemia. Symptoms also vary between people and between leukemia types.
Possible symptoms include:[2][4]
There is no single symptom that confirms leukemia. Most of these symptoms have many more common causes, so diagnosis depends on medical assessment and testing rather than symptoms alone.
Bone marrow produces platelets, which help control bleeding. When leukemia interferes with normal blood cell production, platelet levels may fall in some patients, making bruising or bleeding more likely.[4]
However, bruising and low platelet counts have many other possible causes and do not automatically mean leukemia is present.
Leukemia can produce abnormal white blood cells that do not fight infection normally and can also reduce the production of healthy blood cells.[3]
As a result, some patients may experience frequent infections. However, recurrent infections have many other possible causes and cannot diagnose leukemia by themselves.
There is no single known cause for all leukemias. Leukemia develops after changes occur in the genetic material of blood-forming cells, although why these changes occur in a particular person may not be known.[1]
Risk factors vary by leukemia type and may include:
Having a risk factor does not mean that someone will develop leukemia, and leukemia may also occur without any known risk factor.[5]
Evaluation usually begins with a review of symptoms and medical history and a physical examination. The doctor then selects the appropriate tests.
| Test | What can it help assess? |
|---|---|
| Complete blood count (CBC) | Measures white blood cells, red blood cells, and platelets and may reveal abnormalities that require further investigation. |
| Blood smear | May help assess blood cell appearance and identify abnormal cells when appropriate. |
| Bone marrow examination | Can help confirm the diagnosis and identify abnormal cell types in many leukemias. |
| Specialized cell tests | Help identify the leukemia type and cellular features that may influence treatment decisions. |
A complete blood count may be one of the first tests to reveal abnormalities in some people with leukemia. These may include changes in white blood cells or reduced red blood cells or platelets.
However, a CBC alone may not be enough to confirm leukemia. Blood smear testing, bone marrow examination, and other specialized tests may be required to identify the exact type.[4]
Leukemia does not always cause a high white blood cell count. Some patients may have high levels, while others may have low white blood cell counts or abnormalities involving other blood cells. A white blood cell count alone cannot confirm or rule out leukemia.[6]
No. White blood cell counts can rise for many reasons, including infection and inflammation.[7]
Leukemia diagnosis depends not only on the number of white blood cells but also on the types and appearance of the cells and the results of other tests.
There is no single treatment for all leukemias. Treatment depends on the exact type, cellular characteristics, the patient's age and general health, and how the disease responds to therapy.
Depending on the leukemia type, treatment may include:[4][5]
The Hemato-Oncology Department at Mouwasat Hospital provides specialized evaluation and care for blood disorders and blood cancers, including acute and chronic leukemias.
Specialist assessment helps interpret blood test results correctly and determine which additional investigations may be required.
Most possible leukemia symptoms can be caused by more common conditions. However, persistent or unexplained symptoms should be medically assessed, especially when several occur together.
Examples include:
These symptoms do not necessarily mean leukemia, but medical assessment can help identify their cause.
Leukemia is a group of cancers involving blood-forming cells, often beginning in the bone marrow and producing abnormal cells that can interfere with healthy blood cell production.[1]
Possible symptoms include fatigue, fever, frequent infections, easy bruising or bleeding, paleness, unexplained weight loss, and night sweats. These symptoms are not specific to leukemia.[2]
No. White blood cells can rise because of infections, inflammation, and other conditions. Some patients with leukemia may even have a low white blood cell count, so diagnosis cannot be made from the number alone.[6][7]
No. Low platelets have many possible causes. They can occur with leukemia, but the cause must be determined from the full blood count, symptoms, medical history, and additional testing when needed.
Leukemia is not a single disease, and outcomes vary greatly between different types. Prognosis depends on the leukemia type, its biological features, age, overall health, and response to treatment. Treatment options have improved substantially for many leukemias.
There is no single rate that applies to all leukemias. Outcomes differ substantially between ALL, AML, CLL, and CML and also vary according to age, disease features, and response to treatment.
A blood count may reveal important abnormalities, but it does not always confirm leukemia or determine the exact type. Additional testing, including bone marrow examination, may be required.[4]
Acute leukemias develop more quickly, while chronic leukemias generally develop more slowly. The affected blood cell type and treatment also differ between leukemia subtypes.[3]