How can i help you?
Latest Blogs
Explore All



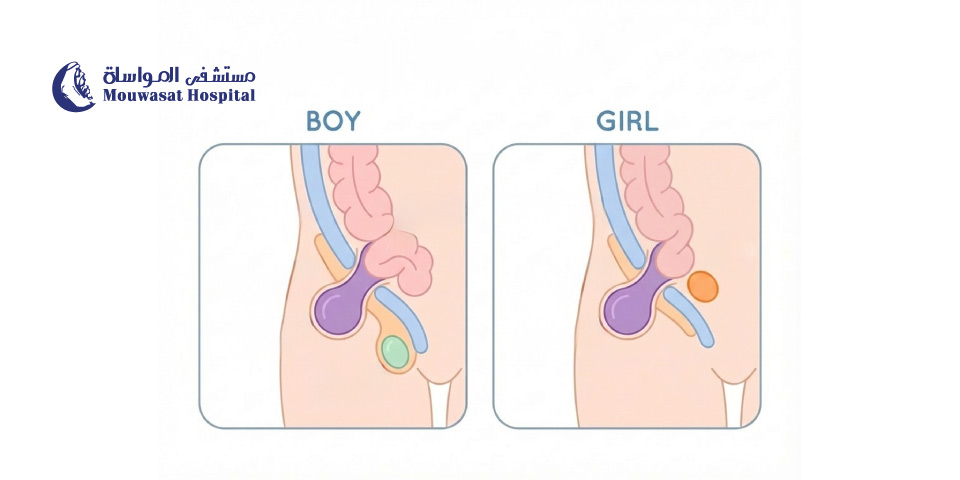

Have you noticed a soft bulge or lump in your child’s lower abdomen or groin area that becomes more visible when they cry and disappears when they are lying down or calm? This is often a sign of inguinal hernia in children.
Inguinal hernia is a common condition that can affect infants and children. If not treated promptly, it may lead to serious complications such as intestinal obstruction or loss of blood supply to tissues.
In this article, we’ll cover in detail the causes of inguinal hernia in children, symptoms to watch for, available treatment options, and when surgery becomes necessary to ensure your child’s safety.
We’ll also answer the most common questions parents ask, such as:
The story of inguinal hernia begins during fetal development. In male babies, the testicles first develop inside the abdomen and then gradually move through a small passage called the inguinal canal into the scrotum. This canal also exists in females.
However, any bulge or signs of pain should never be ignored. Seek medical attention immediately or visit the emergency room.
If left untreated, inguinal hernia can lead to serious complications such as bowel incarceration or strangulation, which is why surgery is the best solution to protect your child’s health.
Inguinal hernia can occur at any age but is most common in newborns. It may not be noticeable for several weeks or months after birth.
Typical signs include:
Most cases are diagnosed through a physical examination, where the doctor observes the bulge that appears during crying or straining and disappears when relaxed.
If the bulge is persistent or the doctor suspects a mass rather than a hernia, an ultrasound may be recommended. However, imaging is not always necessary.
If the bulge remains even when the child is relaxed, it may indicate that part of the intestine or abdominal organs is trapped inside the hernia.
This is called an incarcerated hernia and requires urgent medical attention.
Symptoms include:
If blood supply to the trapped tissue is cut off, the condition becomes more critical, known as strangulated hernia.
Symptoms include:
This is a medical emergency requiring immediate surgery.
Surgery is the only effective treatment for inguinal hernia in children.
The procedure usually takes less than an hour and is considered a day of surgery, meaning your child can go home the same day unless they are premature or have other health conditions.
Our Pediatric Surgery Department offers comprehensive care for infants, children, and adolescents, from consultation to surgery and post-operative follow-up.
Key Advantages:
Medical Disclaimer
This article is for educational purposes only and is not a substitute for professional medical advice. Always consult a pediatrician for diagnosis and treatment.
Yes. Although more common in boys, girls can also develop inguinal hernias, sometimes involving an ovary.
When intestines or organs become trapped (incarcerated) or blood supply is cut off (strangulated), requiring emergency surgery.
Look for a bulge in the groin or scrotum that appears when crying and disappears when relaxed. Persistent bulges or pain require immediate medical attention.
No. Surgery is necessary to repair the hernia and prevent complications.
Yes. It is a quick, safe procedure performed by specialists, usually as same-day surgery.
Read more:
Umbilical Hernia in Children: Causes, Symptoms, and Treatment
Undescended Testicle in Children: Causes, Symptoms, and Treatment
Is a blood sugar reading of 100 normal? What about 140 after eating or 180 two hours after a meal? These numbers can have very different meanings depending on when glucose is measured, which test is used, and whether the person has already been diagnosed with diabetes.
Normal blood sugar levels depend on the testing method and clinical circumstances. For example, fasting plasma glucose below 100 mg/dL is considered within the normal diagnostic range for nonpregnant individuals. However, people who are already receiving diabetes treatment may have different glucose targets.
Another important distinction is that a glucose reading after an ordinary meal is not equivalent to the result of a laboratory oral glucose tolerance test, even if both are measured two hours later.
This guide explains normal fasting glucose, what happens to blood sugar before and after eating, the difference between diagnostic thresholds and treatment targets, and when an unexpected reading warrants further testing or medical assessment.
Seek emergency care immediately if high blood glucose is accompanied by repeated vomiting, abdominal pain, deep or rapid breathing, severe dehydration, or altered consciousness. If someone with suspected severe hypoglycemia is unconscious or unable to swallow safely, do not give food or drinks by mouth. Call emergency medical services. [4] [5]
There is no single blood glucose value that is considered normal for everyone at every moment.
Glucose levels change throughout the day in response to meals, physical activity, hormones, medications, and other health factors.
Understanding a glucose result requires knowing three things:
A diagnostic threshold does not necessarily represent the glucose target for someone receiving treatment.
Likewise, a reading that fits a patient's individualized diabetes management goal cannot automatically establish whether someone else has diabetes.
A fasting plasma glucose (FPG) test measures glucose in a laboratory blood plasma sample after at least eight hours without caloric intake.
For nonpregnant individuals, the following ranges are used:
These thresholds are consistent with the American Diabetes Association's 2026 diagnostic standards. [1]
A laboratory fasting plasma glucose result of 100 or 110 mg/dL is not within the defined normal fasting range of less than 100 mg/dL.
Both values fall within the prediabetes range.
However, a single reading—especially from a home device—should not be treated as a definitive diagnosis.
Your clinician may review preparation, medications, other clinical factors, and whether another laboratory test is needed.
No. Fasting is necessary for a fasting plasma glucose test, but other tests, such as HbA1c, generally do not require fasting.
An oral glucose tolerance test requires its own specific preparation.
Do not change or stop prescribed medicines before testing unless your healthcare professional instructs you to do so.
Blood glucose normally rises after a meal as carbohydrates are digested and absorbed.
The body then uses insulin and other regulatory processes to manage glucose levels.
However, the amount and timing of the increase depend on meal composition, carbohydrate quantity, physical activity, medication, and individual health.
Glucose may be higher about an hour after starting a meal than it was before eating.
But there is no single one-hour home glucose cutoff following an ordinary meal that independently diagnoses diabetes in all nonpregnant individuals.
Interpretation depends on the reason for measuring and the person's medical circumstances.
A common mistake is to apply laboratory oral glucose tolerance test thresholds directly to readings measured two hours after lunch or dinner.
In a standard oral glucose tolerance test (OGTT), a person drinks a carefully measured glucose solution after appropriate preparation, and blood plasma glucose is measured two hours later.
A home glucose measurement after an ordinary meal reflects a different situation because food type, quantity, and timing can vary considerably.
A glucose reading of 140 or 180 mg/dL after an ordinary meal therefore cannot independently diagnose prediabetes or diabetes.
When monitoring postmeal glucose in people with diabetes, ADA 2026 guidance specifies measuring one to two hours after the beginning of the meal.
Using consistent timing makes it easier to compare results and identify patterns with your care team. [2]
The following table summarizes commonly used laboratory diagnostic thresholds for nonpregnant individuals.
These results should not be confused with home glucose monitoring goals or gestational diabetes testing criteria.
| Laboratory test | Normal range | Prediabetes | Diabetes diagnostic range |
|---|---|---|---|
| Fasting plasma glucose (FPG) | Below 100 mg/dL | 100–125 mg/dL | 126 mg/dL or higher |
| Two-hour 75-g oral glucose tolerance test (OGTT) | Below 140 mg/dL | 140–199 mg/dL | 200 mg/dL or higher |
| HbA1c (A1C) | Below 5.7% | 5.7%–6.4% | 6.5% or higher |
Important: The OGTT row does not describe ordinary postmeal home glucose readings. These thresholds are not individual treatment targets, and separate criteria apply to gestational diabetes.
In the absence of unequivocal hyperglycemia, diabetes diagnosis generally requires two abnormal results from the same or different appropriate tests. [1] [3]
For a complete overview of testing and follow-up, read Diabetes: Early Detection, Diagnosis, and Your Next Steps.
If your results are above normal but do not meet the criteria for diabetes, see Prediabetes: Understanding Your Results and Reducing Your Risk.
Once someone has been diagnosed with diabetes, glucose measurements serve a different purpose.
They help assess day-to-day glucose management and support clinical decisions rather than establish the diagnosis again.
According to the ADA 2026 Standards of Care, the following goals are appropriate for many nonpregnant adults with diabetes:
| Measurement | Common goal for many nonpregnant adults with diabetes | Important note |
|---|---|---|
| Before meals | 80–130 mg/dL | A treatment goal, not the normal fasting diagnostic range |
| One to two hours after starting a meal | Below 180 mg/dL | A common peak postmeal treatment target |
| HbA1c | Below 7% for many adults | The individualized goal may be more or less stringent |
These targets should not be applied automatically to everyone with diabetes. Appropriate goals depend on age, treatment, pregnancy, hypoglycemia risk, other medical conditions, and personal circumstances. [2]
For someone without a diabetes diagnosis, a laboratory fasting plasma glucose of 115 mg/dL falls within the prediabetes range.
For someone already receiving treatment for diabetes, a premeal glucose reading of 115 mg/dL may fall within their individualized treatment goal.
Both interpretations can be correct because the measurements are being used for different clinical purposes.
It depends on the test and the patient's circumstances:
Neither threshold should be used in place of the other without understanding the measurement.
Glucose goals during pregnancy differ from those used for most nonpregnant adults.
Pregnant patients with diabetes require careful monitoring to support maternal and fetal health.
ADA 2026 guidance lists the following commonly used blood glucose goals for pregnancies complicated by diabetes:
| Measurement timing | Common target during pregnancy complicated by diabetes |
|---|---|
| Fasting glucose | Below 95 mg/dL |
| One hour after starting a meal | Below 140 mg/dL |
| Two hours after starting a meal | Below 120 mg/dL |
The care team may recommend either one-hour or two-hour postmeal monitoring and individualize goals if necessary to avoid hypoglycemia.
These are glucose management targets for diabetes during pregnancy, not the diagnostic criteria for gestational diabetes. [6]

The following hypothetical examples show why the same number can mean different things in different settings.
They are provided for education, not for diagnosing an individual.
| Example reading | Testing context | Interpretation |
|---|---|---|
| 92 mg/dL | Laboratory fasting plasma glucose in a nonpregnant person | Within the normal fasting diagnostic range |
| 112 mg/dL | Laboratory fasting plasma glucose in someone without a previous diagnosis | Within the prediabetes range; further assessment is appropriate |
| 165 mg/dL | Home glucose reading two hours after an ordinary meal | Cannot independently diagnose prediabetes or diabetes; context and patterns matter |
| 165 mg/dL | Two-hour result from a standardized laboratory OGTT | Within the impaired glucose tolerance range, a prediabetes criterion in nonpregnant individuals |
| 165 mg/dL | One to two hours after starting a meal in a nonpregnant adult with diabetes | May be within the common treatment target if their individualized goal is below 180 mg/dL |
The repeated 165 mg/dL example demonstrates that a glucose reading only becomes meaningful when its purpose, timing, and testing method are known.
People living with diabetes may use finger-prick glucose meters or continuous glucose monitoring (CGM) devices.
These methods can help monitor treatment, but neither replaces appropriate laboratory testing for initial diagnosis.
When keeping a glucose log, record the time, whether you were fasting or eating, when the meal began, any symptoms, and relevant factors such as exercise, illness, or medication.
These details help your healthcare team identify patterns rather than react to a single number.
Yes. Glucose meter readings can differ because of sampling methods, device accuracy, technique, and other conditions.
A small difference does not necessarily indicate a medical problem or a defective device.
If the reading is unexpectedly high or low, particularly when it does not match your symptoms, check your testing technique and seek appropriate medical advice.
No. CGM devices measure glucose in interstitial fluid, while finger-prick meters measure blood glucose.
Values may differ, especially when glucose is changing rapidly.
Follow your device instructions and your care team's advice about when a finger-prick reading is necessary to confirm a CGM value.
Blood glucose changes can be part of normal physiology or related to health conditions and treatment.
No. Some people with diabetes experience an early-morning glucose rise related to hormonal changes, often called the dawn phenomenon.
However, a single elevated morning reading does not establish its cause or confirm diabetes.
Repeated abnormal results may require laboratory testing and a review of medication, sleep, and other factors.
Medical assessment is appropriate when readings are repeatedly outside the expected range, particularly if accompanied by excessive thirst, frequent urination, or unexplained weight loss.
Other reasons to seek professional advice include:
For more information about the signs of elevated glucose, read High Blood Sugar: Symptoms and When to Seek Urgent Care.
To understand low readings, read Low Blood Sugar: Symptoms and When to Seek Help.
Seek emergency care if high glucose is accompanied by repeated vomiting, abnormal breathing, or altered consciousness.
Likewise, a child developing excessive thirst, frequent urination, and unexplained weight loss over a short period needs urgent same-day evaluation for possible type 1 diabetes. [4]
Interpreting blood sugar results involves more than reviewing a number. Age, medical history, medicines, symptoms, and the type of test all matter.
Explore the Diabetic Center at Mouwasat Hospital for diabetes assessment, glucose monitoring support, and individualized follow-up, according to services available at each hospital.
If you want to understand the warning signs that may indicate testing is needed, read Early Signs of Diabetes: Symptoms and When to Get Tested.
For more information about long-term glucose measurements, see HbA1c Test: Understanding Your Result and When to Repeat It.
Laboratory fasting plasma glucose below 100 mg/dL is within the normal diagnostic range for nonpregnant individuals.
The prediabetes range begins at 100 mg/dL for laboratory fasting plasma glucose. A single home reading cannot independently confirm a diagnosis.
A laboratory fasting plasma glucose result of 110 mg/dL is within the prediabetes range in nonpregnant individuals and should be interpreted with other clinical findings.
There is no universal diagnostic cutoff for a home measurement after an ordinary meal. In a standardized laboratory OGTT, a two-hour result below 140 mg/dL is within the normal range for nonpregnant individuals.
It depends on the test. A two-hour OGTT laboratory result of 140 mg/dL falls within the impaired glucose tolerance range. A home reading after an ordinary meal cannot be interpreted using that diagnostic threshold directly.
Not every 180 mg/dL reading is an emergency. Its significance depends on the timing, symptoms, health status, and treatment goals. Repeated elevations or concerning symptoms deserve medical review.
Such a reading can occur depending on meal timing, activity, medication, and individual circumstances. New or unusual symptoms should be assessed rather than relying on the number alone.
A common premeal treatment goal for many nonpregnant adults with diabetes is 80–130 mg/dL, although individualized goals may differ.
For diabetes management, ADA guidance recommends measuring postmeal glucose one to two hours after the beginning of the meal when such measurements are indicated.
For pregnancies complicated by diabetes, common targets are below 140 mg/dL one hour after a meal or below 120 mg/dL two hours afterward, depending on the care plan.
Yes. Fasting glucose measures a specific point in time, while HbA1c reflects glucose exposure over previous months. Discordant results may require clinical assessment or further testing.
No. A high reading may indicate a need for evaluation, but diagnosis relies on appropriate laboratory tests and medical assessment.
Normal blood sugar is not represented by one number that applies to everyone.
Fasting glucose, an oral glucose tolerance test, an ordinary postmeal reading, and HbA1c provide different types of information.
Diagnostic thresholds such as fasting glucose below 100 mg/dL and two-hour OGTT glucose below 140 mg/dL are used in nonpregnant individuals, while treatment targets differ for people with diabetes and during pregnancy.
If you have unexpected readings or need help interpreting a laboratory result, the Diabetic Center at Mouwasat Hospital</a can help you discuss appropriate testing and follow-up with a medical professional.
Medical disclaimer: This article provides general health education and must not be used to diagnose diabetes or independently change medication. Testing criteria and treatment goals vary with age, pregnancy, other medical conditions, and individual care plans. Seek immediate medical attention for emergency warning signs.

The early signs of diabetes can be easy to overlook. You might find yourself drinking more water than usual, waking up frequently to use the bathroom, or feeling unusually tired. Some people lose weight without trying or notice blurry vision, while others have no obvious symptoms despite elevated blood glucose.
Diabetes symptoms vary from person to person. They may develop gradually over several years or appear within days or weeks, particularly with type 1 diabetes.
Recognizing these changes can help you seek medical assessment at the right time. However, symptoms alone cannot confirm whether you have diabetes.
This guide explains common early symptoms, differences between type 1 and type 2 diabetes, warning signs in children, when to seek urgent care, and when blood glucose testing is recommended even if you feel well.
Seek emergency medical care if excessive thirst and frequent urination are accompanied by repeated vomiting, abdominal pain, deep or rapid breathing, fruity-smelling breath, marked drowsiness, or confusion. These symptoms may indicate a serious condition such as diabetic ketoacidosis. Do not wait for a routine laboratory test or outpatient appointment. [3]
Several early symptoms are associated with elevated blood glucose and can occur in more than one type of diabetes.
However, having one symptom does not establish the diagnosis, and having no symptoms does not rule out diabetes.
You may notice that you need to use the bathroom more often than usual or wake up repeatedly during the night to urinate.
When blood glucose rises beyond the kidneys' capacity to reabsorb it, some glucose passes into the urine and draws additional water with it.
This can increase urine output.
Losing extra fluid through urination can make you feel unusually thirsty, even when you are drinking water regularly.
Some people also experience a persistently dry mouth.
Persistent tiredness may occur when the body cannot use glucose effectively and when increased urination contributes to fluid loss.
However, fatigue is nonspecific and can also result from insufficient sleep, anemia, thyroid disorders, and numerous other conditions.
Unintentional weight loss is an important warning sign, particularly when it occurs together with excessive thirst and frequent urination.
When insulin is severely deficient, the body may begin breaking down stored fat and other tissues for energy.
Weight loss can be especially noticeable at the onset of type 1 diabetes, although it is not exclusive to that type.
Significant changes in blood glucose can alter fluid balance within the lens of the eye, causing temporary changes in vision.
Blurred vision can also have many other causes, so it should not automatically be attributed to diabetes.
Sudden loss of vision or a severe new visual disturbance requires urgent medical assessment.
Some people feel hungrier than usual, sometimes even while losing weight, because the body is not using glucose efficiently.
Some people notice that cuts take longer to heal or that urinary tract infections and yeast infections occur repeatedly.
These problems may be more apparent in people who have had undiagnosed type 2 diabetes for some time.
Some people with previously unrecognized type 2 diabetes experience tingling or numbness in the hands or feet.
Dark, thickened patches of skin around the neck, underarms, or other skin folds may be associated with insulin resistance. This condition is known as acanthosis nigricans.
However, neither skin changes nor tingling alone can diagnose diabetes. Other causes must also be considered. [1] [6]
These symptoms often occur together because of the way elevated blood glucose affects the body.
When glucose levels become sufficiently high, the kidneys release some excess glucose into the urine. Water is lost with it, which may lead to increased urination.
That fluid loss can then cause excessive thirst.
At the same time, difficulty using glucose effectively can contribute to tiredness or increased hunger.
In cases of severe insulin deficiency, the body may break down fat and other tissues for energy, leading to weight loss.
Although this pattern can raise suspicion of diabetes, it does not mean that everyone with thirst, urinary frequency, or fatigue has the condition.
Both types share several symptoms, but they often differ in how quickly symptoms appear and how the condition develops.
Type 1 diabetes can cause symptoms that develop over days or weeks, including marked thirst, frequent urination, fatigue, and weight loss.
The condition usually results from an autoimmune process that damages insulin-producing cells in the pancreas.
Although often diagnosed in children, type 1 diabetes can occur at any age.
Some people are first diagnosed when they develop diabetic ketoacidosis, a serious emergency caused by severe insulin deficiency. [2]
Type 2 diabetes often develops gradually over several years, and symptoms can be mild or absent.
It may be discovered during routine testing or when someone seeks medical advice about fatigue, blurry vision, recurring infections, or another health concern.
Although it is more common in adults, type 2 diabetes can also occur in children and adolescents. [1] [5]
| Feature | Type 1 diabetes | Type 2 diabetes |
|---|---|---|
| Symptom onset | May develop quickly over days or weeks, although slower presentations occur | Often gradual; symptoms may be absent for years |
| Thirst and urination | May be prominent and severe | May develop gradually or go unnoticed |
| Weight loss | May be noticeable at diagnosis | Can occur but is not present in everyone |
| Age | Can begin at any age | More common in adults but also occurs in younger people |
| Next step | Suspected new-onset type 1 diabetes requires urgent same-day assessment | Testing is important with symptoms or risk factors, even without symptoms |
Important: Age, weight, and symptoms cannot reliably determine the type of diabetes. Additional clinical evaluation and laboratory testing may be necessary. [4]
Young children may not be able to describe thirst, tiredness, or changes in how they feel.
Parents and caregivers can instead watch for changes in everyday habits, including:
Organizations such as the NHS and Diabetes UK use the 4Ts to help families remember common warning signs:
If you suspect type 1 diabetes in your child, arrange an urgent medical assessment on the same day. Do not wait several days to see whether symptoms disappear. [2] [7]
If a child has increased thirst and urination alongside vomiting, abdominal pain, deep or rapid breathing, marked drowsiness, or confusion, seek emergency medical care immediately.
These may be signs of diabetic ketoacidosis.
The main symptoms, including thirst, frequent urination, fatigue, and blurred vision, can occur in women and men alike.
Recurring yeast infections, including vaginal yeast infections, may prompt an assessment for diabetes, particularly when accompanied by other symptoms or risk factors.
However, these infections are common and have several possible causes. They do not establish a diabetes diagnosis on their own.
There is no completely separate set of early diabetes symptoms exclusive to men.
Men can experience the same common warning signs. Problems such as erectile dysfunction may occur in people with longer-standing diabetes-related nerve or vascular complications, but they also have many other potential causes.
Gestational diabetes usually causes no obvious symptoms.
Screening is therefore recommended during pregnancy, commonly between 24 and 28 weeks, with timing adjusted when earlier testing is clinically indicated.
Pregnant patients should not wait for symptoms before completing recommended screening. [1] [6]
Yes. Some people live with type 2 diabetes or prediabetes without knowing it, because they do not experience noticeable symptoms.
Type 1 diabetes can also have early stages before obvious hyperglycemia or symptoms develop, although identifying these stages involves specialized testing in selected circumstances.
This is why screening decisions depend on age, medical history, family history, weight, and other risk factors—not simply how a person feels.
If your laboratory results are above the normal range but do not meet diabetes diagnostic thresholds, read Prediabetes: Understanding Your Results and Reducing Your Risk.
The appropriate response depends on how quickly symptoms develop, their severity, and the person's overall health.
The following comparison can help explain when routine assessment is appropriate and when more urgent medical attention is required.
| Situation | Possible signs | Recommended next step |
|---|---|---|
| Nonspecific symptoms or risk factors without symptoms | Persistent fatigue, family history, or excess weight without acute warning signs | Arrange a medical assessment and appropriate testing |
| Possible new-onset diabetes requiring prompt evaluation | Increasing thirst and urination with weight loss, especially in a child or with rapidly developing symptoms | Urgent same-day assessment for possible type 1 diabetes |
| Possible serious hyperglycemic emergency | Repeated vomiting, abdominal pain, deep rapid breathing, fruity breath, severe dehydration, or altered consciousness | Seek emergency medical care immediately |
Diabetic ketoacidosis can be the first recognized presentation of diabetes in someone who has not previously been diagnosed.
It is more common in type 1 diabetes but can also occur in people with type 2 diabetes. [3]
For more detailed information about high blood glucose in someone who has diabetes, read High Blood Sugar: Symptoms and When to Seek Urgent Care.
If you repeatedly experience unusual thirst, frequent urination, unexplained weight loss, or several symptoms together, arrange medical assessment without unnecessary delay.
Suspected type 1 diabetes, particularly in a child or someone with rapidly progressing symptoms, requires same-day evaluation.
Even without symptoms, screening may be appropriate based on age and risk factors.
The American Diabetes Association's 2026 Standards of Care recommend general screening for adults beginning at age 35, with earlier testing for certain people who have overweight or obesity and additional risk factors.
People with a history of prediabetes or gestational diabetes may require more frequent follow-up testing. [4]
The most appropriate test depends on your symptoms, risk factors, and medical circumstances.
This laboratory test measures glucose after at least eight hours without caloric intake, according to the testing instructions.
HbA1c reflects average glucose exposure over approximately the previous two to three months.
It can be used for diagnosis when an appropriate laboratory method is used, although certain medical conditions can affect its reliability.
This measures how the body processes a standardized glucose drink under a clinical testing protocol.
The two-hour glucose result is one accepted diagnostic measurement for nonpregnant individuals.
In someone with classic symptoms of hyperglycemia or a hyperglycemic crisis, a random laboratory plasma glucose result of 200 mg/dL (11.1 mmol/L) or higher meets a diabetes diagnostic criterion.
Without unequivocal hyperglycemia, diagnosis generally requires confirmation with two abnormal results according to accepted criteria.
A home blood glucose meter alone is not sufficient to confirm a diabetes diagnosis. [4]
For a more complete explanation of diagnosis and follow-up, read Diabetes: Early Detection, Diagnosis, and Your Next Steps.
To understand the difference between fasting, after-meal, and other glucose measurements, read Normal Blood Sugar Levels: Fasting, After Meals, and Test Timing.
For detailed guidance on your A1C result, explore HbA1c Test: Understanding Your Result and When to Repeat It.
Yes. Although thirst, frequent urination, fatigue, and unexplained weight loss can suggest diabetes, none is exclusive to the condition.
Dehydration, high temperatures, and some medications can cause increased thirst or urination.
Fatigue may be related to sleep problems, anemia, thyroid disorders, or many other health conditions.
A separate condition known as diabetes insipidus can cause excessive thirst and urination because of a problem with fluid regulation. Despite its name, it is different from diabetes mellitus, which involves blood glucose.
Sudden shaking and sweating should not be interpreted as specific signs of newly developing diabetes either. They may be associated with low blood glucose or other causes.
For people already taking diabetes medication, hypoglycemia can occur as a treatment-related problem.
Read Low Blood Sugar: Symptoms and When to Seek Help for more information.
A medical evaluation considers the whole pattern of symptoms alongside medical history and appropriate testing.
If you have recurring symptoms such as excessive thirst, frequent urination, unexplained fatigue, or other risk factors, a medical assessment can help determine whether diabetes testing or another investigation is needed.
The Diabetic Center at Mouwasat Hospital offers diabetes assessment, diagnosis, follow-up, and patient education, according to the services available at each hospital.
For emergency warning signs such as vomiting with abnormal breathing or altered consciousness, seek emergency medical care immediately rather than waiting for a routine clinic appointment.
Early signs may include excessive thirst, frequent urination, fatigue, blurry vision, and unexplained weight loss. However, some people have no noticeable symptoms.
It can be, particularly when accompanied by excessive thirst or weight loss. However, urinary frequency has many possible causes and requires appropriate assessment if persistent.
No. Thirst can result from dehydration, heat, medications, or other conditions. Diabetes requires appropriate testing for diagnosis.
They may develop over days or weeks, although slower presentations also occur, particularly in adults. Suspected type 1 diabetes requires urgent same-day assessment.
Type 2 diabetes generally develops gradually, and symptoms may remain unnoticed for years. Some people can experience more noticeable hyperglycemia, especially during illness or infection.
Yes. Not everyone experiences all the common symptoms, and diabetes may be detected through routine laboratory screening.
It can be, especially when accompanied by excessive thirst and frequent urination. Unexplained weight loss also has other possible causes and deserves medical assessment.
The main symptoms are similar in women and men. Some women may experience recurring yeast infections, but this does not confirm diabetes.
No. Gestational diabetes is often asymptomatic, making recommended pregnancy screening important.
No. Symptoms can raise suspicion, but diagnosis requires appropriate laboratory testing and medical interpretation.
They are not specific diagnostic signs of new-onset diabetes. They can occur with hypoglycemia or other conditions. People taking glucose-lowering medicines should follow their prescribed hypoglycemia action plan.
Seek emergency care for repeated vomiting, abdominal pain, rapid deep breathing, fruity-smelling breath, severe dehydration, or altered consciousness, particularly alongside excessive thirst and frequent urination.
Recognizing early diabetes symptoms may help people seek timely assessment, particularly when persistent thirst occurs alongside frequent urination, fatigue, or unexplained weight loss.
However, diabetes can exist without obvious symptoms, and similar complaints may result from other conditions.
Appropriate medical assessment and laboratory testing are therefore essential.
Rapidly developing symptoms in a child, or symptoms accompanied by vomiting, abnormal breathing, or confusion, require urgent medical care.
For nonemergency assessment and follow-up, learn more about the Diabetic Center at Mouwasat Hospital.
Medical disclaimer: This article provides general health information and does not replace individualized medical assessment or diagnosis. The appropriate action depends on age, symptoms, severity, and medical circumstances. Seek emergency care immediately when serious warning signs occur.
Is a blood sugar reading of 100 normal? What about 140 after eating or 180 two hours after a meal? These numbers can have very different meanings depending on when glucose is measured, which test is used, and whether the person has already been diagnosed with diabetes.
Normal blood sugar levels depend on the testing method and clinical circumstances. For example, fasting plasma glucose below 100 mg/dL is considered within the normal diagnostic range for nonpregnant individuals. However, people who are already receiving diabetes treatment may have different glucose targets.
Another important distinction is that a glucose reading after an ordinary meal is not equivalent to the result of a laboratory oral glucose tolerance test, even if both are measured two hours later.
This guide explains normal fasting glucose, what happens to blood sugar before and after eating, the difference between diagnostic thresholds and treatment targets, and when an unexpected reading warrants further testing or medical assessment.
Seek emergency care immediately if high blood glucose is accompanied by repeated vomiting, abdominal pain, deep or rapid breathing, severe dehydration, or altered consciousness. If someone with suspected severe hypoglycemia is unconscious or unable to swallow safely, do not give food or drinks by mouth. Call emergency medical services. [4] [5]
There is no single blood glucose value that is considered normal for everyone at every moment.
Glucose levels change throughout the day in response to meals, physical activity, hormones, medications, and other health factors.
Understanding a glucose result requires knowing three things:
A diagnostic threshold does not necessarily represent the glucose target for someone receiving treatment.
Likewise, a reading that fits a patient's individualized diabetes management goal cannot automatically establish whether someone else has diabetes.
A fasting plasma glucose (FPG) test measures glucose in a laboratory blood plasma sample after at least eight hours without caloric intake.
For nonpregnant individuals, the following ranges are used:
These thresholds are consistent with the American Diabetes Association's 2026 diagnostic standards. [1]
A laboratory fasting plasma glucose result of 100 or 110 mg/dL is not within the defined normal fasting range of less than 100 mg/dL.
Both values fall within the prediabetes range.
However, a single reading—especially from a home device—should not be treated as a definitive diagnosis.
Your clinician may review preparation, medications, other clinical factors, and whether another laboratory test is needed.
No. Fasting is necessary for a fasting plasma glucose test, but other tests, such as HbA1c, generally do not require fasting.
An oral glucose tolerance test requires its own specific preparation.
Do not change or stop prescribed medicines before testing unless your healthcare professional instructs you to do so.
Blood glucose normally rises after a meal as carbohydrates are digested and absorbed.
The body then uses insulin and other regulatory processes to manage glucose levels.
However, the amount and timing of the increase depend on meal composition, carbohydrate quantity, physical activity, medication, and individual health.
Glucose may be higher about an hour after starting a meal than it was before eating.
But there is no single one-hour home glucose cutoff following an ordinary meal that independently diagnoses diabetes in all nonpregnant individuals.
Interpretation depends on the reason for measuring and the person's medical circumstances.
A common mistake is to apply laboratory oral glucose tolerance test thresholds directly to readings measured two hours after lunch or dinner.
In a standard oral glucose tolerance test (OGTT), a person drinks a carefully measured glucose solution after appropriate preparation, and blood plasma glucose is measured two hours later.
A home glucose measurement after an ordinary meal reflects a different situation because food type, quantity, and timing can vary considerably.
A glucose reading of 140 or 180 mg/dL after an ordinary meal therefore cannot independently diagnose prediabetes or diabetes.
When monitoring postmeal glucose in people with diabetes, ADA 2026 guidance specifies measuring one to two hours after the beginning of the meal.
Using consistent timing makes it easier to compare results and identify patterns with your care team. [2]
The following table summarizes commonly used laboratory diagnostic thresholds for nonpregnant individuals.
These results should not be confused with home glucose monitoring goals or gestational diabetes testing criteria.
| Laboratory test | Normal range | Prediabetes | Diabetes diagnostic range |
|---|---|---|---|
| Fasting plasma glucose (FPG) | Below 100 mg/dL | 100–125 mg/dL | 126 mg/dL or higher |
| Two-hour 75-g oral glucose tolerance test (OGTT) | Below 140 mg/dL | 140–199 mg/dL | 200 mg/dL or higher |
| HbA1c (A1C) | Below 5.7% | 5.7%–6.4% | 6.5% or higher |
Important: The OGTT row does not describe ordinary postmeal home glucose readings. These thresholds are not individual treatment targets, and separate criteria apply to gestational diabetes.
In the absence of unequivocal hyperglycemia, diabetes diagnosis generally requires two abnormal results from the same or different appropriate tests. [1] [3]
For a complete overview of testing and follow-up, read Diabetes: Early Detection, Diagnosis, and Your Next Steps.
If your results are above normal but do not meet the criteria for diabetes, see Prediabetes: Understanding Your Results and Reducing Your Risk.
Once someone has been diagnosed with diabetes, glucose measurements serve a different purpose.
They help assess day-to-day glucose management and support clinical decisions rather than establish the diagnosis again.
According to the ADA 2026 Standards of Care, the following goals are appropriate for many nonpregnant adults with diabetes:
| Measurement | Common goal for many nonpregnant adults with diabetes | Important note |
|---|---|---|
| Before meals | 80–130 mg/dL | A treatment goal, not the normal fasting diagnostic range |
| One to two hours after starting a meal | Below 180 mg/dL | A common peak postmeal treatment target |
| HbA1c | Below 7% for many adults | The individualized goal may be more or less stringent |
These targets should not be applied automatically to everyone with diabetes. Appropriate goals depend on age, treatment, pregnancy, hypoglycemia risk, other medical conditions, and personal circumstances. [2]
For someone without a diabetes diagnosis, a laboratory fasting plasma glucose of 115 mg/dL falls within the prediabetes range.
For someone already receiving treatment for diabetes, a premeal glucose reading of 115 mg/dL may fall within their individualized treatment goal.
Both interpretations can be correct because the measurements are being used for different clinical purposes.
It depends on the test and the patient's circumstances:
Neither threshold should be used in place of the other without understanding the measurement.
Glucose goals during pregnancy differ from those used for most nonpregnant adults.
Pregnant patients with diabetes require careful monitoring to support maternal and fetal health.
ADA 2026 guidance lists the following commonly used blood glucose goals for pregnancies complicated by diabetes:
| Measurement timing | Common target during pregnancy complicated by diabetes |
|---|---|
| Fasting glucose | Below 95 mg/dL |
| One hour after starting a meal | Below 140 mg/dL |
| Two hours after starting a meal | Below 120 mg/dL |
The care team may recommend either one-hour or two-hour postmeal monitoring and individualize goals if necessary to avoid hypoglycemia.
These are glucose management targets for diabetes during pregnancy, not the diagnostic criteria for gestational diabetes. [6]
The following hypothetical examples show why the same number can mean different things in different settings.
They are provided for education, not for diagnosing an individual.
| Example reading | Testing context | Interpretation |
|---|---|---|
| 92 mg/dL | Laboratory fasting plasma glucose in a nonpregnant person | Within the normal fasting diagnostic range |
| 112 mg/dL | Laboratory fasting plasma glucose in someone without a previous diagnosis | Within the prediabetes range; further assessment is appropriate |
| 165 mg/dL | Home glucose reading two hours after an ordinary meal | Cannot independently diagnose prediabetes or diabetes; context and patterns matter |
| 165 mg/dL | Two-hour result from a standardized laboratory OGTT | Within the impaired glucose tolerance range, a prediabetes criterion in nonpregnant individuals |
| 165 mg/dL | One to two hours after starting a meal in a nonpregnant adult with diabetes | May be within the common treatment target if their individualized goal is below 180 mg/dL |
The repeated 165 mg/dL example demonstrates that a glucose reading only becomes meaningful when its purpose, timing, and testing method are known.
People living with diabetes may use finger-prick glucose meters or continuous glucose monitoring (CGM) devices.
These methods can help monitor treatment, but neither replaces appropriate laboratory testing for initial diagnosis.
When keeping a glucose log, record the time, whether you were fasting or eating, when the meal began, any symptoms, and relevant factors such as exercise, illness, or medication.
These details help your healthcare team identify patterns rather than react to a single number.
Yes. Glucose meter readings can differ because of sampling methods, device accuracy, technique, and other conditions.
A small difference does not necessarily indicate a medical problem or a defective device.
If the reading is unexpectedly high or low, particularly when it does not match your symptoms, check your testing technique and seek appropriate medical advice.
No. CGM devices measure glucose in interstitial fluid, while finger-prick meters measure blood glucose.
Values may differ, especially when glucose is changing rapidly.
Follow your device instructions and your care team's advice about when a finger-prick reading is necessary to confirm a CGM value.
Blood glucose changes can be part of normal physiology or related to health conditions and treatment.
No. Some people with diabetes experience an early-morning glucose rise related to hormonal changes, often called the dawn phenomenon.
However, a single elevated morning reading does not establish its cause or confirm diabetes.
Repeated abnormal results may require laboratory testing and a review of medication, sleep, and other factors.
Medical assessment is appropriate when readings are repeatedly outside the expected range, particularly if accompanied by excessive thirst, frequent urination, or unexplained weight loss.
Other reasons to seek professional advice include:
For more information about the signs of elevated glucose, read High Blood Sugar: Symptoms and When to Seek Urgent Care.
To understand low readings, read Low Blood Sugar: Symptoms and When to Seek Help.
Seek emergency care if high glucose is accompanied by repeated vomiting, abnormal breathing, or altered consciousness.
Likewise, a child developing excessive thirst, frequent urination, and unexplained weight loss over a short period needs urgent same-day evaluation for possible type 1 diabetes. [4]
Interpreting blood sugar results involves more than reviewing a number. Age, medical history, medicines, symptoms, and the type of test all matter.
Explore the Diabetic Center at Mouwasat Hospital for diabetes assessment, glucose monitoring support, and individualized follow-up, according to services available at each hospital.
If you want to understand the warning signs that may indicate testing is needed, read Early Signs of Diabetes: Symptoms and When to Get Tested.
For more information about long-term glucose measurements, see HbA1c Test: Understanding Your Result and When to Repeat It.
Laboratory fasting plasma glucose below 100 mg/dL is within the normal diagnostic range for nonpregnant individuals.
The prediabetes range begins at 100 mg/dL for laboratory fasting plasma glucose. A single home reading cannot independently confirm a diagnosis.
A laboratory fasting plasma glucose result of 110 mg/dL is within the prediabetes range in nonpregnant individuals and should be interpreted with other clinical findings.
There is no universal diagnostic cutoff for a home measurement after an ordinary meal. In a standardized laboratory OGTT, a two-hour result below 140 mg/dL is within the normal range for nonpregnant individuals.
It depends on the test. A two-hour OGTT laboratory result of 140 mg/dL falls within the impaired glucose tolerance range. A home reading after an ordinary meal cannot be interpreted using that diagnostic threshold directly.
Not every 180 mg/dL reading is an emergency. Its significance depends on the timing, symptoms, health status, and treatment goals. Repeated elevations or concerning symptoms deserve medical review.
Such a reading can occur depending on meal timing, activity, medication, and individual circumstances. New or unusual symptoms should be assessed rather than relying on the number alone.
A common premeal treatment goal for many nonpregnant adults with diabetes is 80–130 mg/dL, although individualized goals may differ.
For diabetes management, ADA guidance recommends measuring postmeal glucose one to two hours after the beginning of the meal when such measurements are indicated.
For pregnancies complicated by diabetes, common targets are below 140 mg/dL one hour after a meal or below 120 mg/dL two hours afterward, depending on the care plan.
Yes. Fasting glucose measures a specific point in time, while HbA1c reflects glucose exposure over previous months. Discordant results may require clinical assessment or further testing.
No. A high reading may indicate a need for evaluation, but diagnosis relies on appropriate laboratory tests and medical assessment.
Normal blood sugar is not represented by one number that applies to everyone.
Fasting glucose, an oral glucose tolerance test, an ordinary postmeal reading, and HbA1c provide different types of information.
Diagnostic thresholds such as fasting glucose below 100 mg/dL and two-hour OGTT glucose below 140 mg/dL are used in nonpregnant individuals, while treatment targets differ for people with diabetes and during pregnancy.
If you have unexpected readings or need help interpreting a laboratory result, the Diabetic Center at Mouwasat Hospital</a can help you discuss appropriate testing and follow-up with a medical professional.
Medical disclaimer: This article provides general health education and must not be used to diagnose diabetes or independently change medication. Testing criteria and treatment goals vary with age, pregnancy, other medical conditions, and individual care plans. Seek immediate medical attention for emergency warning signs.
Is an HbA1c result of 6% normal? Does an A1C of 7% mean you have diabetes? And what does it mean if your A1C is 8% or 9% even though your home glucose readings often look acceptable?
The HbA1c test, also called A1C or glycated hemoglobin, provides an estimate of average blood glucose exposure over approximately the previous two to three months. Healthcare professionals use it to help diagnose diabetes and prediabetes and to monitor glucose management in people already living with diabetes.
However, the meaning of an A1C result depends on the clinical situation. A percentage used to diagnose diabetes is not necessarily the treatment target for someone who already has the condition.
The test also has limitations. It cannot identify individual episodes of high or low blood glucose, and certain conditions affecting red blood cells can make the result misleading.
This guide explains normal HbA1c levels, how to interpret different results, when repeat testing is appropriate, how A1C relates to estimated average glucose, and when another test may be more reliable.
HbA1c is not a test for identifying an immediate glucose emergency. If someone develops repeated vomiting, abdominal pain, deep or rapid breathing, severe dehydration, or altered consciousness, seek emergency medical care rather than waiting for an A1C result. [8]
Hemoglobin is the protein inside red blood cells that carries oxygen throughout the body.
Some glucose in the bloodstream attaches to hemoglobin. The more glucose circulates in the blood over time, the greater the proportion of glycated hemoglobin tends to become.
The HbA1c test measures this proportion as a percentage.
For example, an A1C result of 7% means approximately 7% of the measured hemoglobin is glycated. It does not mean that blood glucose itself is 7%.
Because red blood cells normally survive for about 120 days, HbA1c reflects average glucose exposure during approximately the previous two to three months.
However, recent glucose levels influence the result more heavily than older measurements, so meaningful changes during the last several weeks can affect A1C before three full months have passed. [3] [4]
No. An HbA1c test generally does not require fasting and can usually be performed at any time of day.
If your healthcare professional has ordered additional tests, such as fasting plasma glucose, follow the preparation instructions for those tests.
For diabetes diagnosis, the test should use an appropriate laboratory method that meets recognized quality and standardization requirements.
Point-of-care devices may be useful for monitoring during clinic visits, but not every rapid A1C device is suitable for making a diabetes diagnosis. [1]
According to the American Diabetes Association's 2026 Standards of Care, the following HbA1c ranges are used for diagnosing diabetes and prediabetes in nonpregnant individuals.
| HbA1c result | Diagnostic category | What it means |
|---|---|---|
| Below 5.7% | Normal range | Below the A1C threshold for prediabetes, assuming the test is reliable. |
| 5.7%–6.4% | Prediabetes | Higher-than-normal glucose exposure that warrants assessment of risk factors and preventive care. |
| 6.5% or higher | Diabetes diagnostic range | Meets one diabetes diagnostic criterion; confirmation is generally needed unless hyperglycemia is unequivocal. |
Important: These are diagnostic ranges, not individualized treatment goals for people who already have diabetes. Pregnancy has separate diagnostic considerations. [1]
An A1C result of 6.5% or higher meets a diabetes diagnostic threshold.
However, when unequivocal hyperglycemia is absent, the diagnosis generally requires two abnormal results.
Confirmation may involve repeating A1C using an appropriate test or obtaining another accepted laboratory measurement, depending on the clinical circumstances.
If different tests disagree, the healthcare professional may repeat the test that exceeded the diagnostic threshold and consider factors that could affect test accuracy.
For the broader diagnostic pathway, read Diabetes: Early Detection, Diagnosis, and Your Next Steps.
People frequently search for the meaning of a specific A1C percentage. However, results must always be interpreted according to whether the person has already been diagnosed with diabetes.
An HbA1c of 5.7% is at the beginning of the prediabetes range.
It does not mean progression to type 2 diabetes is inevitable, but it provides an opportunity to assess risk factors and discuss preventive measures.
For someone without a diabetes diagnosis, 6% falls within the prediabetes range.
Evaluation may include family history, body weight, physical activity, blood pressure, and cardiovascular risk factors.
This result is at the upper end of the prediabetes range.
It warrants attention to appropriate prevention and follow-up, especially when additional risk factors are present.
At 6.5%, the result reaches the diabetes diagnostic threshold.
Confirmation and further assessment are usually required before establishing the diagnosis in someone without unequivocal hyperglycemia.
For someone not previously diagnosed, 7% is within the diabetes diagnostic range.
For someone receiving diabetes treatment, an A1C of 7% may be close to their individualized treatment target.
An A1C below 7% is appropriate for many nonpregnant adults with diabetes, although goals may differ.
An A1C of 8% is above the common treatment goal for many adults living with diabetes.
It may prompt a review of glucose patterns, medications, lifestyle factors, and the treatment plan.
Medication doses should not be changed independently based on this number alone.
These values indicate substantially elevated average glucose exposure over recent months.
Medical assessment is important to determine why glucose remains high and whether changes in treatment are required.
An elevated A1C does not independently establish an immediate emergency. However, symptoms such as repeated vomiting, abdominal pain, abnormal breathing, or altered consciousness require urgent care regardless of the A1C percentage.
Markedly elevated A1C, especially with symptoms of hyperglycemia, may require more prompt evaluation and treatment planning. [2] [7]
Some laboratories report HbA1c alongside an estimated average glucose value, often called eAG.
This converts A1C into an approximate average glucose concentration using familiar units such as mg/dL.
| HbA1c | Estimated average glucose (eAG) |
|---|---|
| 6% | Approximately 126 mg/dL |
| 6.5% | Approximately 140 mg/dL |
| 7% | Approximately 154 mg/dL |
| 8% | Approximately 183 mg/dL |
| 9% | Approximately 212 mg/dL |
| 10% | Approximately 240 mg/dL |
These are approximate population-based estimates rather than expected glucose readings at every moment. The relationship between A1C and average glucose can differ among individuals, particularly when factors affect HbA1c accuracy. [6]
No. An eAG of approximately 154 mg/dL represents an estimated average.
Actual glucose may rise significantly after meals and fall at other times.
Someone could experience repeated highs and lows while maintaining an apparently acceptable overall average.
This is one reason A1C cannot independently show glucose variability or hypoglycemia episodes.
The ADA 2026 Standards of Care recommend an A1C goal below 7% for many nonpregnant adults with diabetes when it can be achieved safely without severe or burdensome hypoglycemia.
However, treatment targets should be individualized.
Some people may benefit from a lower goal, such as below 6.5%, if the risks and treatment burden are low.
Others may need a less stringent goal because of age, frailty, other illnesses, or increased hypoglycemia risk. [2]
Not necessarily.
Attempting to reach an excessively low A1C using treatments that increase hypoglycemia risk can be harmful for some patients.
The goal is to achieve an appropriate balance between glucose management, complication prevention, treatment burden, and patient safety.
Targets may differ according to age, diabetes type, health status, and individual needs.
During pregnancy, HbA1c alone is not sufficient to assess day-to-day glucose management, and pregnancy-specific blood glucose targets form an important part of care. [9]
There is no single retesting schedule suitable for everyone.
The appropriate interval depends on why the test was ordered, the previous result, and whether diabetes has already been diagnosed.
| Situation | Typical follow-up timing | Reason |
|---|---|---|
| First result within the diabetes diagnostic range without clear symptoms | Confirm without unnecessary delay, as clinically appropriate | Confirming a new diagnosis does not automatically require waiting three months. |
| Prediabetes | Generally yearly, or sooner based on risk | Monitor progression and reassess risk factors. |
| Borderline or conflicting results | Sometimes within 3–6 months, or sooner depending on the discrepancy | Clarify the result and investigate possible test interference. |
| Diagnosed diabetes with stable management and goals being met | At least twice yearly | Monitor continued glucose management. |
| Diagnosed diabetes with treatment changes or unmet goals | Often every three months | Assess treatment response and guide follow-up decisions. |
These intervals reflect general ADA 2026 recommendations and may be adjusted for individual circumstances. [1] [2]
Yes. HbA1c can begin to reflect recent glucose changes within several weeks.
However, a short interval does not provide the same long-term view as a later follow-up test.
Home glucose monitoring or CGM may be more useful for understanding the immediate response to treatment changes.
This should not be confused with confirmatory testing after a first diagnostic-range result, which may need to be performed promptly.
HbA1c is a valuable test, but its accuracy depends partly on red blood cell characteristics and lifespan.
Some medical conditions can therefore affect the relationship between A1C and actual blood glucose exposure.
Iron deficiency and certain forms of anemia can affect HbA1c.
Iron deficiency may lead to a falsely elevated result in some circumstances.
By contrast, conditions that shorten red blood cell survival, such as hemolytic anemia, can produce misleadingly low A1C results.
Some types of thalassemia, sickle cell disease, and other hemoglobin variants may interfere with HbA1c measurement.
However, not every hemoglobin variant makes every A1C assay unreliable. The effect depends on the condition and laboratory method.
Certain forms of glucose-6-phosphate dehydrogenase (G6PD) deficiency can affect the relationship between HbA1c and average glucose.
In situations where A1C is considered unreliable, plasma glucose criteria may be more appropriate for diagnosis.
Recent bleeding or blood transfusion may alter red blood cell populations and affect A1C interpretation.
The direction of the effect is not necessarily the same in every situation.
Advanced kidney disease, dialysis, and treatments that stimulate red blood cell production can affect HbA1c reliability.
Pregnancy changes red blood cell turnover and glucose metabolism.
HbA1c therefore has important limitations in this setting and does not replace recommended testing for gestational diabetes.
The ADA 2026 Standards of Care, NIDDK, and NGSP emphasize using plasma glucose criteria when medical conditions alter the relationship between HbA1c and actual glucose exposure. [1] [4] [5]
This discrepancy does not automatically mean that either test is wrong.
Home measurements may not capture glucose elevations after meals or overnight.
Alternatively, the result may reflect differences between measurement methods or a condition affecting A1C reliability.
Your healthcare professional may review glucose logs, repeat appropriate laboratory tests, or consider CGM data.
Do not change medication based on conflicting results without medical assessment.
Each test answers a different clinical question:
Yes.
A person may have an apparently favorable average while experiencing substantial glucose fluctuations, including frequent hypoglycemia.
A1C alone cannot show when low glucose occurred or how often it happened.
Finger-prick measurements and CGM data may therefore be essential, particularly for people taking insulin or other treatments associated with hypoglycemia. [2]
To understand fasting and after-meal readings, see Normal Blood Sugar Levels: Fasting, After Meals, and When to Get Tested.
For warning signs of hypoglycemia, read Low Blood Sugar: Symptoms and When to Seek Help.
Improving A1C depends on the type of diabetes, the reasons for elevated glucose, current treatment, and overall health.
There is no single approach that suits everyone, and attempting to lower glucose too aggressively can increase the risk of hypoglycemia in some patients.
Balanced meals, suitable carbohydrate portions, and limiting sugar-sweetened drinks can support glucose management.
However, eliminating all carbohydrates is not necessary for everyone.
The goal is an individualized eating pattern that can be maintained safely.
Appropriate physical activity can improve insulin sensitivity and support weight management, cardiovascular health, and blood pressure control.
People using insulin or medications associated with hypoglycemia may need additional precautions around exercise.
Treatment choices depend on diabetes type, kidney function, cardiovascular health, body weight, and hypoglycemia risk.
Do not increase doses, stop insulin, or add medicines without medical guidance.
Daily glucose measurements and CGM data can help identify patterns related to meals, exercise, illness, and treatment.
Blood pressure, cholesterol, kidney health, and eye care also remain important parts of comprehensive diabetes management. [2]
The appropriate next step depends on why the test was performed and your medical history.
For prevention and follow-up when glucose is elevated but below the diabetes diagnostic threshold, read Prediabetes: Understanding Your Results and Reducing Your Risk.
If you have excessive thirst, frequent urination, or unexplained weight loss, see Early Signs of Diabetes: Symptoms and When to Get Tested.
The Diabetic Center at Mouwasat Hospital offers diabetes assessment and follow-up services.
Its published comprehensive diagnostic services include HbA1c testing as part of long-term glucose evaluation.
Medical assessment can help interpret the result alongside other glucose measurements, health conditions, and current treatment, and determine when further testing or follow-up is appropriate.
Yes. It falls within the normal diagnostic range for nonpregnant individuals, assuming the test is reliable and no relevant medical condition affects interpretation.
No. An A1C of 5.7% is at the beginning of the prediabetes range, not the diabetes diagnostic range.
An A1C of 6% does not by itself indicate an emergency. It falls within the prediabetes range and warrants appropriate assessment and follow-up.
It meets a diabetes diagnostic threshold, but treatment decisions depend on confirming the diagnosis, identifying diabetes type, and assessing the person's overall health.
It may be close to an appropriate target for many adults with diabetes. However, goals are individualized. For someone not previously diagnosed, 7% is within the diabetes diagnostic range.
Yes. These levels are above the usual treatment target for many adults with diabetes and may indicate a need to review glucose patterns and treatment. The percentage alone does not establish an immediate emergency.
Yes. Recent glucose improvements can begin affecting the result within weeks. However, an assessment after approximately three months often provides a more useful view of treatment response.
Not usually. Fasting may only be necessary when other tests ordered at the same time require it.
Yes, some forms of anemia, particularly iron deficiency, may increase A1C results in certain circumstances. Conditions that shorten red blood cell survival may instead lower the result.
No. A1C reflects average glucose exposure and cannot show the timing or frequency of hypoglycemia. Home glucose or CGM data may be needed.
The two tests measure different aspects of glucose regulation. Significant differences may require clinical evaluation, repeated testing, or investigation of factors affecting test accuracy.
People with stable diabetes who meet treatment goals are generally assessed at least twice yearly. Testing is often performed approximately every three months when treatment changes or goals are not being met.
The HbA1c test helps identify diabetes-related glucose abnormalities and assess long-term glucose management.
In nonpregnant individuals, results below 5.7% fall within the normal diagnostic range, 5.7%–6.4% indicates prediabetes, and 6.5% or higher meets a diabetes diagnostic threshold.
However, treatment goals differ after diagnosis, and some conditions affecting red blood cells or hemoglobin may make HbA1c results less reliable.
The best approach is to interpret A1C alongside symptoms, glucose measurements, medical history, and individualized treatment goals.
Learn more about the Diabetic Center at Mouwasat Hospital for diabetes assessment, laboratory testing, and follow-up care.
Medical disclaimer: This article provides general health education and does not replace individualized medical advice. Do not adjust prescribed diabetes medications based on HbA1c results without consulting your healthcare professional.
Your blood glucose meter shows 200, 250, or even 300 mg/dL. Does this mean you are in danger? Should you go to the emergency department, or can the situation be managed with your usual diabetes care plan?
High blood sugar, also called hyperglycemia, occurs when glucose rises above the desired range. It may cause excessive thirst, frequent urination, fatigue, and blurred vision, although some people have no noticeable symptoms.
Importantly, the seriousness of hyperglycemia cannot be determined from one number alone. It also depends on how long glucose remains elevated, whether concerning symptoms are present, the type of diabetes, medications, ketone levels, and overall health.
This guide explains high blood sugar symptoms, common causes, what different glucose readings may mean, when to check ketones, what you can safely do, and the warning signs that require emergency care.
Seek emergency medical attention for repeated vomiting with abdominal pain, deep or rapid breathing, fruity-smelling breath, marked confusion, loss of consciousness, severe dehydration, or inability to keep fluids down. Do not wait for blood glucose to reach a particular number if signs of diabetic ketoacidosis or another hyperglycemic emergency are present. [1] [2]
Glucose is a major source of energy, and insulin helps cells take up and use it.
Hyperglycemia develops when the body does not have enough effective insulin, when cells become less responsive to insulin, or when illness and other stresses increase insulin requirements.
High blood glucose can occur in type 1 or type 2 diabetes. It may also be one of the first signs of previously undiagnosed diabetes.
Symptoms are not always present, so elevated glucose may be discovered through home testing, continuous glucose monitoring, or laboratory investigations.
Glucose naturally rises after meals, but the extent and duration depend on the meal, medications, and individual health.
For many nonpregnant adults with diabetes, a commonly recommended treatment target is below 180 mg/dL one to two hours after the beginning of a meal.
Individual targets may differ. Laboratory diabetes diagnostic thresholds should not be applied directly to an ordinary home postmeal measurement.
For a detailed explanation, read Normal Blood Sugar Levels: Fasting, After Meals, and When to Get Tested.
Symptoms may develop gradually, particularly when glucose remains elevated for a prolonged period.
When glucose rises sufficiently, the kidneys release some of it into the urine, drawing additional water with it.
This fluid loss can cause increased thirst and a dry mouth.
You may notice more frequent urination or waking repeatedly during the night to use the bathroom.
The combination of increased thirst and urination is particularly important when accompanied by unexplained weight loss.
Unusual tiredness may result from impaired glucose utilization, fluid loss, or an illness contributing to hyperglycemia.
However, fatigue has many possible causes and cannot independently establish a diabetes diagnosis.
Significant changes in glucose may affect fluid balance in the eye's lens, temporarily altering vision.
Sudden vision loss or severe new visual changes require urgent assessment and should not automatically be attributed to blood sugar.
Headache or reduced concentration may accompany high glucose, particularly with dehydration or illness.
These are nonspecific symptoms and can occur in many other conditions.
Weight loss may occur when severe insulin deficiency prevents the body from using glucose effectively, leading it to break down fat and other tissues for energy.
Persistent poor glucose management can contribute to slow wound healing and recurring infections.
Longer-term complications may develop when hyperglycemia remains inadequately managed over time.
Not having symptoms does not guarantee that glucose is within your target range. [3] [4]
Many people want one number that separates ordinary hyperglycemia from a medical emergency.
However, the clinical situation is more complex.
A modest temporary elevation after a meal may be less concerning than persistent hyperglycemia during infection. Conversely, diabetic ketoacidosis can sometimes occur without extremely high glucose.
| Reading or situation | What it may mean | Appropriate response |
|---|---|---|
| 180 mg/dL after a meal | May be above a common postmeal target, depending on timing and individual goals. | Review timing and your care plan. The number alone does not establish an emergency. |
| Repeated readings above your individual target | May indicate a need to review medications, illness, meals, or other factors. | Contact your diabetes care team, especially if readings remain elevated or symptoms develop. |
| Approximately 240–250 mg/dL or higher | May require ketone testing, especially during illness and in people at risk of DKA. | Follow your individualized sick-day and ketone management plan. |
| Persistently 300 mg/dL or higher | Significant ongoing hyperglycemia requiring urgent assessment. | Seek urgent medical care; CDC advises emergency assessment when glucose stays at this level. |
| Repeated vomiting, abnormal breathing, or altered consciousness, regardless of glucose | Possible DKA or another serious hyperglycemic emergency. | Seek emergency care immediately. |
Important: These examples help explain urgency. They are not universal diagnostic cutoffs or personalized treatment instructions. Type 1 diabetes, pregnancy, medications, symptoms, and ketone results may require urgent action at lower glucose levels. [1] [2] [5]
Its significance depends on timing, symptoms, and medical history.
For someone without a diabetes diagnosis, random laboratory plasma glucose of at least 200 mg/dL together with classic symptoms of hyperglycemia or a hyperglycemic crisis meets a diabetes diagnostic criterion.
However, one home glucose reading cannot independently confirm diabetes, and not every reading of 200 mg/dL represents an emergency. [6]
Glucose that remains at 300 mg/dL or higher requires urgent attention. CDC advises emergency assessment when blood sugar stays at this level.
Emergency care is also necessary for symptoms of DKA, severe dehydration, or altered consciousness, even when glucose is below 300 mg/dL.
More than one factor may contribute to hyperglycemia.
Glucose can rise if prescribed medication is missed, insulin delivery is interrupted, or the current treatment plan does not meet the body's needs.
Insulin pump delivery problems can cause a rapid rise, especially in people with type 1 diabetes.
Infection and fever can trigger hormones that increase glucose levels and insulin requirements, even when appetite is reduced.
Large carbohydrate portions or reduced activity may contribute to glucose elevations.
Physical and psychological stress and disrupted sleep may affect glucose regulation.
Some medications, including corticosteroids, can increase glucose.
Tell your healthcare professional about all medicines and supplements you use.
Understanding the cause can support treatment decisions but does not justify making medication changes without an established medical plan. [3] [7]
For someone with diagnosed diabetes who has no emergency warning signs, the following steps may help assess the situation safely.
Review when glucose was measured. For finger-prick testing, wash and dry your hands and check that the test strips and device are being used correctly.
If a CGM reading does not match how you feel, confirm it with a finger-prick test when recommended by your device instructions or care plan.
Look beyond the number.
Repeated vomiting, abdominal pain, unusual breathing, severe dizziness, altered consciousness, or signs of significant dehydration may indicate urgent danger.
If you are alert, can swallow normally, and have no medical restriction on fluid intake, drinking water may help replace fluid lost through increased urination.
Persistent vomiting or inability to keep fluids down requires urgent medical assessment.
Take diabetes medicines as directed and use an individualized written insulin correction plan only if your care team has provided one.
Do not double insulin doses, repeat correction doses at random, or stop necessary basal insulin without medical guidance.
People at risk of DKA may need to check ketones during illness or elevated glucose, and sometimes even when glucose is not markedly high.
Physical activity can support glucose management in appropriate circumstances, but it is not a treatment for severe hyperglycemia accompanied by ketones or symptoms of illness.
Avoid strenuous exercise when ketones are elevated or DKA is suspected. Follow your healthcare team's advice on when exercise is safe.
If glucose remains elevated despite following your established plan, contact your care team rather than repeatedly attempting unplanned corrections. [1] [3]
Ketones are substances produced when the body breaks down fat for energy.
They can accumulate dangerously when insulin is severely insufficient, increasing the risk of diabetic ketoacidosis (DKA).
Ketone monitoring is particularly important for people with type 1 diabetes and others at risk of DKA, including some people using insulin or certain diabetes medicines.
Sources such as CDC and the Saudi Ministry of Health recommend checking ketones during illness or when glucose reaches approximately 240–250 mg/dL or higher in relevant at-risk situations, with individualized instructions taking priority. [2] [7]
Ketones can be measured using a blood ketone meter or urine ketone strips.
Blood testing measures beta-hydroxybutyrate, an important ketone in the assessment of DKA.
The appropriate response depends on the testing method, level, symptoms, and your medical plan.
The American Diabetes Association advises seeking emergency medical attention when blood ketones reach 1.6 mmol/L or higher.
Severe symptoms require emergency assessment regardless of a home ketone result.
Do not wait for a ketone test if someone is repeatedly vomiting, breathing abnormally, or becoming confused. [5]
Yes.
Some people develop euglycemic diabetic ketoacidosis, meaning DKA occurs without markedly elevated blood glucose.
This can happen in certain circumstances, including in some people taking SGLT2 inhibitors.
It is another reason that one glucose reading cannot safely rule out an emergency. [1] [8]
Severe disturbances in glucose regulation can cause life-threatening emergencies, particularly diabetic ketoacidosis (DKA) and hyperosmolar hyperglycemic state (HHS).
| Feature | Diabetic ketoacidosis (DKA) | Hyperosmolar hyperglycemic state (HHS) |
|---|---|---|
| What happens? | Insulin deficiency leads to ketone accumulation and metabolic acidosis. | Severe hyperglycemia causes major fluid loss and increased blood osmolality. |
| Most commonly associated with | Type 1 diabetes, but can occur in type 2. | Type 2 diabetes, particularly in older adults. |
| Important warning signs | Nausea, vomiting, abdominal pain, rapid or deep breathing, fruity breath. | Severe dehydration, progressive weakness, altered consciousness, often very high glucose. |
| Urgency | Medical emergency. | Medical emergency. |
These emergencies can overlap and cannot be reliably distinguished from home glucose readings or symptoms alone.
Diagnosis requires hospital assessment, including glucose, ketones, acid-base balance, electrolytes, and fluid status. [8]
Glucose can rise during influenza, infections, fever, or other illnesses, even when someone eats less than usual.
Hormones released during illness may increase insulin resistance and insulin requirements.
For this reason, people with diabetes are encouraged to create an individualized sick-day plan with their healthcare team before illness occurs.
A useful plan should explain:
Not all diabetes medicines should be managed in the same way during illness. Some treatments require specific instructions, so discuss them with your healthcare professional in advance.
Seek urgent assessment if you cannot keep fluids down, have repeated vomiting, abnormal breathing, or elevated ketones. [9] [10]
Preventing repeated hyperglycemia involves identifying causes and following a treatment and monitoring plan tailored to your diabetes type and overall health.
To understand how recent glucose patterns relate to long-term results, read HbA1c Test: Normal Ranges, Results, and When to Repeat It.
Arrange medical assessment when readings repeatedly exceed your individual target, hyperglycemia persists despite following your prescribed plan, or symptoms such as thirst, frequent urination, or weight loss develop.
Someone without a previous diabetes diagnosis also needs appropriate evaluation when these symptoms appear. A single home glucose reading is not sufficient to confirm diabetes.
Possible new-onset type 1 diabetes, especially in children or when symptoms develop rapidly, requires urgent same-day assessment.
For more on early warning signs, read Early Signs of Diabetes: Symptoms and When to Get Tested.
Managing repeated hyperglycemia requires assessing diabetes type, current medications, daily glucose patterns, overall health, and possible contributing factors.
The Diabetic Center at Mouwasat Hospital offers diabetes assessment, follow-up, individualized glucose management plans, and patient education, according to services available at each hospital.
When symptoms suggest an acute hyperglycemic emergency, seek emergency care immediately rather than waiting for a routine clinic appointment.
Symptoms may include thirst, frequent urination, fatigue, and blurred vision, although some people experience no symptoms. Vomiting, abdominal pain, abnormal breathing, or altered consciousness are emergency warning signs.
Headaches may occur with high glucose, particularly when dehydration is present, but they are nonspecific and have many possible causes.
Its significance depends on timing, symptoms, diabetes type, and whether the elevation persists. A reading of 200 alone does not automatically represent an emergency but may require evaluation.
Not necessarily based on the number alone. However, ketone testing may be needed in people at risk of DKA, particularly during illness. Symptoms or elevated ketones may require urgent care.
Glucose that remains at 300 mg/dL or higher requires urgent attention, and CDC recommends emergency assessment when it stays at this level. Do not delay emergency care if serious symptoms are present.
Yes. Hyperglycemia can occur without noticeable symptoms, which is why appropriate monitoring is important.
Water may be appropriate if you are alert, can swallow safely, and have no medical fluid restriction. Persistent vomiting or inability to keep fluids down requires urgent assessment.
Physical activity can help glucose management in suitable circumstances, but exercise should not be used to treat severe hyperglycemia with ketones or symptoms suggesting DKA.
Only follow a correction plan prescribed by your healthcare team. Do not increase or repeat doses at random. Seek medical guidance if glucose does not improve according to your plan.
Severe hyperglycemia may be accompanied by nausea or vomiting. These symptoms can indicate a serious emergency, particularly when abdominal pain or abnormal breathing is present.
Yes. Euglycemic DKA can occur in certain circumstances, including in some people taking SGLT2 inhibitors. A relatively lower glucose reading does not exclude DKA.
High glucose commonly causes thirst and frequent urination, while low glucose may cause shaking, sweating, palpitations, or sudden hunger. Symptoms can overlap, so checking glucose when possible helps guide appropriate action.
For more information, read Low Blood Sugar: Symptoms and When to Seek Help.
Hyperglycemia can cause thirst, frequent urination, fatigue, and blurred vision, but it may also occur without obvious symptoms.
The appropriate response depends on glucose levels, how long they remain elevated, diabetes type, illness, ketones, and concerning symptoms.
Repeated high readings deserve a review of the management plan. Repeated vomiting, abnormal breathing, or altered consciousness require immediate emergency care.
If you experience recurring elevations or need help reviewing your diabetes care plan, explore the Diabetic Center at Mouwasat Hospital and discuss the appropriate next steps with your healthcare team.
Medical disclaimer: This article provides general health education and must not be used to diagnose diabetes, calculate insulin doses, or independently change medication. Hyperglycemia action plans vary, particularly for children, pregnant patients, insulin users, and people with other medical conditions.
Has your doctor recommended an H. pylori test, leaving you unsure whether you need a breath test, stool test, or blood test? Do you need to fast before testing, and what does a positive or negative result actually mean?
There are several ways to detect Helicobacter pylori infection, but not all tests serve the same purpose. Some identify an active infection, while others may remain positive because of a previous infection, even after successful treatment.
This guide explains the differences between the urea breath test, stool antigen test, and blood antibody testing; when endoscopy may be needed; how to prepare for accurate results; and when testing should be repeated after treatment.
Seek emergency medical care if you vomit blood or material resembling coffee grounds, pass black tarry stools, develop sudden severe persistent abdominal pain, or faint with suspected gastrointestinal bleeding. Do not delay urgent assessment while waiting for an H. pylori test. [7]
Not everyone with occasional bloating or stomach discomfort needs an H. pylori test.
Testing decisions depend on the person's symptoms, age, medical history, risk factors, and whether another investigation may be more appropriate.
Testing may be recommended in situations such as:
ACG and ACG/CAG guidance emphasizes selecting appropriate patients for testing while considering risk factors and whether endoscopy or other investigations are needed. [1] [5]
If you are unsure whether your symptoms suggest H. pylori, read H. pylori Symptoms: When Should You Get Tested? to understand common symptoms and important warning signs.
H. pylori can be investigated using noninvasive tests, such as breath and stool tests, or tests performed on tissue collected during an upper gastrointestinal endoscopy.
Blood antibody tests are also available, but they cannot reliably distinguish active infection from previous exposure.
The most important question when choosing a test is what the test needs to establish: whether the bacteria are currently present, whether treatment has eradicated the infection, or whether the stomach lining needs direct examination for another reason.
The urea breath test (UBT) is an important noninvasive method for detecting active H. pylori infection.
It takes advantage of the bacterium's ability to produce urease, an enzyme that breaks down urea and generates compounds including carbon dioxide.
When the patient receives urea labeled with a specific carbon isotope, the resulting labeled carbon dioxide can be measured in exhaled breath.
The exact procedure and waiting time depend on the testing system and laboratory protocol. [2] [3]
Some breath testing systems require patients to avoid food and drinks for several hours beforehand.
However, fasting requirements vary by test system and laboratory. You should follow the instructions provided for your specific appointment, including guidance about water, smoking, and medications.
An H. pylori stool antigen test detects proteins or antigens associated with the bacteria in a stool sample.
When performed using an appropriate validated laboratory test, it can identify active infection and confirm eradication after treatment.
Storage conditions and acceptable delivery times vary between laboratories and testing systems, so follow the instructions for your specific test.
Both can be reliable methods for detecting active H. pylori infection.
Accuracy depends on the specific assay, laboratory quality, medication preparation, and timing.
Validated laboratory-based stool antigen tests, particularly appropriate monoclonal antibody assays, can achieve high diagnostic performance.
Rather than choosing a test based on a universal claim that one is always more accurate, the clinician should consider the patient's needs and available validated tests. [2] [6]
Rapid and home-use tests may have different performance characteristics from established laboratory assays.
Do not assume all home tests have equivalent accuracy or rely on a home result alone to choose antibiotics or confirm eradication without appropriate clinical evaluation.
Blood antibody tests measure the immune system's response to H. pylori rather than detecting the bacteria directly.
Antibodies, including IgG, may remain detectable long after an infection has been successfully treated.
Consequently:
This distinction explains why different H. pylori tests are not interchangeable. [3]
Most patients who are suitable for noninvasive testing do not need endoscopy solely to check for H. pylori.
However, upper endoscopy may be appropriate when clinicians need to examine the esophagus, stomach, or duodenum directly, or investigate possible bleeding, a complicated ulcer, or another concerning condition.
During endoscopy, the clinician may collect biopsies for histology, rapid urease testing, or other investigations depending on the patient's needs.
Biopsies allow direct examination of tissue and can support H. pylori diagnosis, but they are not necessary for everyone.
Some biopsy-based tests may also be affected by medications that suppress bacterial activity or reduce bacterial density.
Endoscopy should be selected according to the overall clinical indication, not accuracy comparisons alone. [2] [4]
Some molecular tests, including polymerase chain reaction (PCR), can detect bacterial genetic material.
Certain assays can also identify genetic changes associated with resistance to specific antibiotics.
However, test availability, performance, specimen requirements, and resistance detection vary. PCR is not a routine requirement for every person with suspected H. pylori infection.
| Test | Detects active infection? | Useful for confirming eradication? | Important consideration |
|---|---|---|---|
| Urea breath test | Yes | Yes | Requires appropriate medication preparation |
| Stool antigen test | Yes, using an appropriate validated assay | Yes | Assay quality and sample handling matter |
| Blood antibody test | Cannot reliably distinguish current from previous infection | No | May remain positive after treatment |
| Endoscopic biopsy-based tests | Yes, depending on the test and conditions | May be used when endoscopy is independently indicated | Invasive and selected for specific clinical reasons |
| Appropriate PCR tests | May detect infection depending on the assay and specimen | Not generally the routine first choice for test of cure | Some assays can help identify antibiotic resistance |
Test selection should reflect the clinical purpose, timing, and medication history—not simply convenience or price.
Correct preparation is essential for reliable results, especially with breath and stool testing.
Ask your testing center about fasting, water intake, smoking, chewing gum, and any medication restrictions.
Tell the healthcare team about recent antibiotics, bismuth products, proton pump inhibitors, and other acid-suppressing medications.
Follow the sample collection and storage instructions and confirm when the sample should be returned.
Tell your clinician about medications that may reduce test sensitivity.
Preparation may include fasting, anesthesia assessment, and individualized medication instructions.
Your healthcare team will provide specific guidance based on the procedure and your health.
Some medicines temporarily suppress H. pylori or reduce bacterial activity, potentially producing a negative result even when infection remains present.
Professional guidelines therefore recommend appropriate intervals before breath or stool testing, whether for initial diagnosis or eradication confirmation.
| Medication | Usual interval before testing | Reason |
|---|---|---|
| Proton pump inhibitors (PPIs), such as omeprazole, esomeprazole, and pantoprazole | Withheld for at least 2 weeks under medical guidance | May cause false-negative results |
| Potassium-competitive acid blockers (PCABs), such as vonoprazan | Withheld for at least 2 weeks under medical guidance | May interfere with infection detection |
| Antibiotics | At least 4 weeks since relevant antibiotic exposure | May temporarily suppress the bacteria |
| Bismuth-containing medicines | At least 4 weeks | May reduce test sensitivity |
During the PPI washout period, your clinician may recommend temporary alternatives such as H2 receptor antagonists or antacids, subject to the requirements of the selected test. [1] [2]
Do not stop prescribed medication on your own just to undergo testing. If withholding treatment is not appropriate, your clinician may change the test date or consider an alternative diagnostic approach.
Results are reported differently according to the method and laboratory.
Some are qualitative, such as Positive or Negative, while others include measurements interpreted using method-specific reference limits.
A positive result from an appropriately performed urea breath test or stool antigen test generally indicates an active infection.
A positive blood antibody result, however, may reflect previous exposure rather than ongoing infection.
A negative result from a reliable test performed after appropriate preparation makes active infection less likely.
However, it may not be dependable if the test was performed soon after antibiotics or bismuth, or while using certain acid-suppressing medications.
If clinical suspicion remains, the clinician may recommend repeating testing after correct preparation or investigating other possible causes.
There is no single numerical cutoff that applies to every H. pylori test.
Breath tests may report values interpreted against a system-specific threshold. Stool antigen tests may provide qualitative or assay-dependent results, while antibody tests use different measurements.
A value such as 20 or 50 therefore cannot be interpreted without knowing the test method, units, and laboratory reference range.
Not necessarily.
H. pylori infection can coexist with functional dyspepsia, reflux, or another condition.
Your clinician may need to evaluate whether the infection explains your symptoms and whether further investigations are indicated.
The 2024 ACG guideline recommends confirming H. pylori eradication in all patients who receive treatment, even when symptoms disappear.
A urea breath test or appropriate stool antigen test is commonly used. Blood antibody testing is not suitable for confirming eradication.
These intervals help reduce false-negative results. They do not establish whether treatment succeeded without the actual follow-up test. [1]
Not necessarily. Symptoms may persist because of functional dyspepsia, acid reflux, or another condition even after successful eradication.
Likewise, symptoms may improve despite persistent infection.
Confirmation should therefore rely on an appropriately timed and performed test rather than symptoms alone.
For more about treatment selection, antibiotic resistance, and what happens if the infection persists, read H. pylori Treatment: Choosing Therapy and Confirming Eradication.
Yes. Indications for testing, diagnostic approaches, and follow-up recommendations differ between children and adults.
ESPGHAN/NASPGHAN guidelines advise against routinely using a test-and-treat strategy for children with functional abdominal pain alone.
Children with gastric or duodenal ulcers or erosions may require appropriate evaluation for H. pylori under pediatric guidance.
When confirming eradication in children, the guidelines generally recommend testing 6 to 8 weeks after completing treatment, using an appropriate urea breath test or validated laboratory-based stool antigen test with correct medication preparation. [6]
Children should not be tested or have results interpreted solely according to adult protocols without appropriate clinical assessment.
If you have persistent indigestion, a history of peptic ulcers, or H. pylori results that need interpretation, a gastroenterology assessment may help determine whether a breath test, stool antigen test, or endoscopy is suitable for your condition.
Explore the Gastroenterology and Endoscopy Department at Mouwasat Hospital, including H. pylori assessment and treatment. Availability of individual tests may vary by hospital location and clinical requirements.
Both can reliably detect active infection and confirm eradication when validated tests are used with proper preparation. The choice depends on the patient's needs and test availability.
Urea breath testing may require several hours of fasting, depending on the laboratory protocol. Stool antigen testing has different preparation requirements. Follow the instructions for the specific test.
This depends on the test system and laboratory instructions. Do not assume water is always allowed or always prohibited before breath testing.
It can detect antibodies, but it cannot reliably distinguish active from previous infection and should not be used to confirm eradication.
A positive breath or suitable stool antigen test generally indicates active infection. A positive antibody test may also reflect previous exposure.
Not in every situation. A properly performed negative test makes active infection less likely, but certain medications may cause false-negative results.
No single range applies to every test. Results must be interpreted according to the assay, units, and reference limits reported by the laboratory.
Omeprazole and other PPIs can affect breath and stool testing. A two-week period without PPIs is generally recommended before testing, under medical guidance. Do not stop prescribed medication without consulting your clinician.
In adults, testing is generally performed at least four weeks after antibiotics are completed, with appropriate medication washout intervals.
Not necessarily. Symptoms can improve despite persistent infection, which is why eradication should be confirmed with a suitable test.
No. Breath or stool antigen testing may be appropriate without endoscopy. Endoscopy is used when direct examination of the upper digestive tract is indicated.
Performance can vary between home, rapid, and laboratory tests. Equivalent accuracy should not be assumed without evidence for the specific assay.
Turnaround time varies by test method and laboratory. Ask the testing facility when your results are expected.
Recent guidance includes testing adult household contacts of people with confirmed H. pylori infection using active infection tests, with clinical assessment. Antibiotics should not be given to everyone without appropriate diagnosis.
H. pylori testing is not a single procedure. Breath and stool antigen tests can identify active infection, while blood antibody results cannot reliably establish whether infection is current or treatment has worked.
Medication use, test timing, and preparation affect result accuracy. Some patients may need repeat testing or broader medical assessment.
For a wider overview of the infection, read H. pylori Infection: Causes, Diagnosis, Treatment and Warning Signs. If you need help selecting a test or interpreting your results, explore the Gastroenterology and Endoscopy Department at Mouwasat Hospital.
Medical disclaimer: This article provides general health education and does not replace individualized medical assessment. Do not stop prescribed medication or begin antibiotics based on an uninterpreted result. Seek emergency care for signs of gastrointestinal bleeding or sudden severe abdominal pain.

Can H. pylori be completely cured? Which antibiotics are used to treat it, and how successful are different treatment regimens? These are common questions after a positive Helicobacter pylori test, especially when patients encounter conflicting information about triple therapy, quadruple therapy, and treatment success.
H. pylori treatment involves a combination of medicines designed to eradicate the bacteria. However, not every treatment works equally well for every patient. Antibiotic resistance, previous antibiotic exposure, medication allergies, treatment duration, and adherence all influence the likelihood of success.
Clinical research also shows that H. pylori cure rates vary across treatment regimens and patient populations. This makes it important to understand what published eradication rates mean and why symptom improvement alone cannot confirm recovery.
This guide explains the medications used for H. pylori, the differences between triple and quadruple therapy, eradication rates reported in Saudi studies, possible side effects, reasons for treatment failure, and when follow-up testing is necessary.
Get urgent medical help if you vomit blood, pass black tarry stools, experience sudden severe persistent abdominal pain, or faint with suspected gastrointestinal bleeding. Swelling of the tongue or throat or difficulty breathing after taking medication may indicate a severe allergic reaction and requires immediate emergency assistance. [6] [8]
When active H. pylori infection has been confirmed using an appropriate diagnostic test, eradication treatment is generally recommended to eliminate the bacteria and reduce the risk of associated complications.
Many people with H. pylori have no noticeable symptoms. Nevertheless, chronic infection may cause gastritis or peptic ulcers and is associated with an increased risk of certain stomach cancers. [5]
However, stomach pain and bloating alone do not establish the diagnosis. Blood antibody tests may also remain positive after a previous infection has been eliminated.
For a broader explanation of the infection, how it spreads, and possible complications, read H. pylori Infection: Causes, Diagnosis, Treatment and Warning Signs.
H. pylori eradication usually requires several medicines working together. A single antibiotic or an acid-suppressing medication alone is generally not enough.
Antibiotics target the bacteria and are selected according to the treatment regimen and the patient's circumstances.
Medications that may be included in H. pylori treatment include:
These examples are provided to explain treatment options. They are not instructions to combine or select antibiotics independently.
Reducing stomach acid can support antibiotic effectiveness and promote ulcer healing when an ulcer is present.
The medicines used may include:
Bismuth is included in some quadruple regimens and contributes to eradication treatment alongside antibiotics and acid suppression.
Different bismuth products and treatment combinations are not automatically interchangeable. Medication choice, dose, and schedule must follow the prescribed regimen. [1]
The terms triple and quadruple therapy describe the number of components used in a treatment regimen, not a guarantee of effectiveness.
Traditional triple therapy combines a proton pump inhibitor, amoxicillin, and clarithromycin.
Although it was widely used for many years, increasing resistance to clarithromycin has reduced its effectiveness in numerous settings.
The 2024 ACG guideline recommends avoiding empiric clarithromycin-based triple therapy unless susceptibility testing confirms that the bacteria are sensitive to the antibiotic. [1]
One guideline-recommended optimized bismuth quadruple regimen includes:
The 2024 ACG guideline recommends optimized bismuth quadruple therapy for 14 days as a preferred treatment for many previously untreated adults when antibiotic susceptibility is unknown.
However, medication allergies, pregnancy, interactions, and other clinical circumstances may require a different approach.
Selected alternatives include rifabutin-based regimens, vonoprazan-amoxicillin dual therapy, and susceptibility-guided treatment when appropriate.
These options differ in suitability, regulatory status, and availability. Their inclusion here does not imply that they are suitable for every patient or available at every healthcare facility. [1]
| Treatment approach | Main components | Important consideration |
|---|---|---|
| Traditional triple therapy | PPI, amoxicillin and clarithromycin | Not recommended empirically without confirmed clarithromycin susceptibility |
| Optimized bismuth quadruple therapy | PPI, bismuth, tetracycline and metronidazole | A preferred option in the 2024 ACG guideline for appropriate patients |
| Alternative regimens | May include rifabutin or vonoprazan-based combinations | Suitability depends on medical history, allergies, and availability |
| Susceptibility-guided therapy | Antibiotics selected according to appropriate test findings | May be particularly helpful after previous treatment failure |
There is no single cure rate that applies to every H. pylori treatment.
The term eradication rate refers to the proportion of patients in whom the bacteria are confirmed to have been eliminated through appropriate follow-up testing.
Rates vary because of antibiotic resistance, the regimen used, treatment duration, adherence, and differences between the populations and methods used in studies.
The Saudi H. pylori Working Group reviewed regional and international research, including the following findings from Saudi studies:
| Regimen studied | Eradication rate | Study context |
|---|---|---|
| Traditional clarithromycin-based triple therapy for 14 days | 59% | Saudi study, intention-to-treat (ITT) analysis |
| A fixed-combination bismuth quadruple regimen with acid suppression for 10 days | 78.3% | Separate Saudi study, ITT analysis |
How should these results be interpreted? These percentages came from different Saudi studies, not a single head-to-head randomized comparison.
The 10-day bismuth-containing regimen studied is also not identical to the 14-day optimized bismuth quadruple regimen preferred in the 2024 ACG guideline.
Intention-to-treat analysis considers the participants included under the study's assigned-treatment analysis rather than only patients who fully adhered to the regimen.
The same Saudi studies reported approximately 67.6% and 87.8%, respectively, in their per-protocol analyses. These figures use a different analysis approach and should not be presented as guaranteed outcomes for individual patients. [2]
Effective regimens can achieve high eradication rates in suitable research and treatment settings.
Saudi guidance identifies an eradication rate of 90% or higher as a goal when choosing effective first-line treatment.
However, this is a clinical performance target, not an observed result for every regimen or a guaranteed personal cure rate.
Some published Saudi studies reported lower rates, demonstrating the importance of antibiotic resistance and appropriate treatment selection. [2]
In a randomized trial conducted in the United States and Europe, traditional clarithromycin-based triple therapy achieved an eradication rate of only 31.9% among participants infected with clarithromycin-resistant strains.
This figure applies to that specific resistant subgroup in the trial. It is not the expected cure rate for all patients receiving triple therapy, but it clearly illustrates the impact of antibiotic resistance. [3]
No. Cure of the infection means confirming that H. pylori has been eradicated using an appropriate diagnostic test.
Stomach pain and bloating may improve before the bacteria have been fully eliminated. Conversely, digestive symptoms can persist even after successful eradication.
Antibiotic resistance occurs when bacteria become less susceptible to medications that would otherwise be effective.
Saudi recommendations have documented substantial resistance to certain antibiotics, particularly clarithromycin and metronidazole, with rates varying across studies and periods. [2]
Before selecting treatment, clinicians may review:
A regimen that worked for someone else may not be appropriate for you, even when symptoms appear similar.
Many modern H. pylori treatment regimens last 14 days, including optimized bismuth quadruple therapy recommended by the 2024 ACG guideline.
Some other regimens may have different durations. Patients should follow the treatment period specified in their prescription without shortening or extending it independently.
One week should not be assumed sufficient for every treatment regimen.
Effectiveness depends on the medications, duration, susceptibility, and adherence.
Some people notice symptom improvement within the first few days, but feeling better does not confirm eradication.
There is no reliable symptom or specific day that confirms the bacteria have been eliminated.
Eradication must be assessed using an appropriate follow-up test at the correct time.
Good adherence supports treatment effectiveness, although it cannot overcome every form of antibiotic resistance or other clinical factors.
Some regimens involve several medicines taken multiple times a day, with different instructions concerning meals, other medications, iron, or calcium supplements.
Ask your doctor or pharmacist for a clear schedule, and use reminders if helpful.
Do not stop treatment simply because symptoms improve.
If side effects become difficult to tolerate, contact your healthcare team rather than changing or stopping medication independently.
Missed-dose instructions differ between medicines. Do not double doses without appropriate guidance or substitute another antibiotic based on someone else's experience.
Previous antibiotics, medication allergies, and other health conditions can influence which treatment is suitable.
Discuss the timing and preparation requirements for eradication testing when treatment is first prescribed.
This reduces the chance that follow-up testing will be overlooked once symptoms improve.
Side effects vary according to the medicines prescribed. They may include:
Some H. pylori medications can also interact with other prescriptions or supplements. Tell your healthcare team about everything you take.
Bismuth may cause harmless darkening of stool. However, stool appearance alone cannot always distinguish a medication effect from gastrointestinal bleeding.
Black tarry stools, especially with severe dizziness, fainting, or vomiting blood, require urgent medical evaluation. [8]
Seek prompt advice for severe or persistent diarrhea, vomiting that prevents you from drinking fluids or taking medicines, a new rash, or concerning neurological symptoms.
Difficulty breathing or swelling of the tongue or throat after medication requires emergency care.
Some people feel better during treatment, while others continue to experience symptoms after the medication course ends, particularly when an ulcer needs additional time to heal.
Functional dyspepsia, acid reflux, and other conditions may also explain ongoing digestive symptoms.
Persistent symptoms do not automatically mean eradication failed, and symptom relief does not prove success.
To understand how H. pylori symptoms differ from other digestive complaints, read H. pylori Symptoms: When Should You Get Tested?.
The 2024 ACG guideline recommends confirming eradication in every patient treated for H. pylori infection.
A urea breath test or validated stool antigen test is commonly used. Biopsy-based testing may be appropriate in selected circumstances when endoscopy is independently indicated.
Blood antibody tests should not be used to confirm eradication because they may remain positive after the infection has been eliminated.
Do not stop prescribed acid-suppressing medicines without consulting your clinician. Temporary alternatives or a different test date may be appropriate. [1]
For a detailed explanation of test choices, preparation, and result interpretation, read H. pylori Testing: Breath Test vs. Stool Test and When to Test.
H. pylori may persist after treatment because of antibiotic resistance, difficulty adhering to the regimen, or other factors.
Failure of the first treatment does not mean the bacteria cannot be eradicated. However, the previous regimen should be reviewed before selecting another treatment.
A regimen that has already failed should not automatically be repeated without reviewing its components and the patient's previous exposure.
Your doctor may select an alternative regimen. Current guidance also advises that certain salvage treatments containing clarithromycin or levofloxacin should be based on confirmed susceptibility. [1]
Culture-based susceptibility testing or appropriate molecular testing may help guide subsequent treatment.
The Saudi H. pylori Working Group recommends considering susceptibility testing or PCR, when available, after two different eradication regimens have failed. [2]
Not necessarily. Symptoms may return because of reflux, dyspepsia, or other conditions.
If a later test confirms H. pylori, the clinician may assess whether the previous infection persisted or a new infection occurred.
Garlic, honey, mastic gum, pomegranate peel, and other natural products are sometimes promoted as H. pylori treatments.
However, reliable clinical evidence is insufficient to recommend them as proven substitutes for medical eradication therapy.
Replacing effective treatment with home remedies may delay appropriate care.
Studies have investigated probiotics as additions to H. pylori therapy, with results varying by microbial strain, dose, and treatment regimen.
The 2024 ACG guideline finds insufficient evidence to routinely recommend probiotics as a reliable way to improve eradication success or treatment tolerability. [1]
There is no universal list of prohibited foods for everyone with H. pylori.
Patients can choose balanced meals according to their tolerance and reduce foods that consistently aggravate their symptoms.
However, medication-specific instructions must be followed because certain antibiotics interact with mineral supplements or other products taken around the same time.
Adult eradication regimens should not be applied automatically to children, because testing indications, medication choices, and dosing differ.
Updated ESPGHAN/NASPGHAN guidance emphasizes using antibiotic susceptibility information when available and avoiding empiric clarithromycin treatment without appropriate susceptibility evidence.
Eradication in children is generally confirmed 6 to 8 weeks after treatment using a suitable test. [4]
Some antibiotics used for H. pylori may be unsuitable during pregnancy or breastfeeding.
Decisions depend on symptom severity, ulcers or complications, medication safety, and whether treatment can be deferred.
Pregnant or breastfeeding patients should not begin an eradication regimen without individualized medical assessment.
Confirmed penicillin allergy affects the use of regimens containing amoxicillin.
Your clinician may consider alternative treatments after reviewing the nature of the previous reaction, and formal allergy assessment may be useful in selected circumstances.
If you have a confirmed H. pylori infection, a positive result after previous treatment, or need a follow-up test to establish eradication, a gastroenterology consultation can help determine the appropriate next step.
Explore the Gastroenterology and Endoscopy Department at Mouwasat Hospital for assessment of stomach disorders, peptic ulcers, and H. pylori infection, according to clinical needs and services available at each hospital.
Yes. Appropriate treatment can eradicate H. pylori, but no regimen guarantees success in every patient. A follow-up test is needed to confirm eradication.
Selection depends on resistance, previous treatment, allergies, and clinical circumstances. Optimized bismuth quadruple therapy for 14 days is a preferred option under the 2024 ACG guideline for appropriate patients.
Cure rates depend on the treatment and population studied. Saudi studies have reported 59% with traditional triple therapy for 14 days and 78.3% with a 10-day fixed-combination bismuth quadruple regimen, in separate intention-to-treat analyses. These are not guaranteed outcomes for individual patients.
No. A rate of 90% or higher is an effectiveness goal identified in Saudi treatment guidance, not a guarantee for any particular regimen or patient.
Many modern regimens last 14 days, but duration varies according to the prescribed treatment.
Symptom improvement within one week does not establish eradication, and seven days is not an appropriate duration for every regimen.
Possible reasons include antibiotic resistance, difficulty completing the treatment, and other clinical factors. Persistent infection requires reassessment.
Some regimens can cause nausea, altered taste, bowel changes, or other side effects. Severe or persistent symptoms should be discussed with a clinician or pharmacist.
Bismuth may darken stool, but black tarry stools or symptoms of bleeding require urgent evaluation and should not be assumed to be a harmless medication effect.
For adults, at least four weeks after completing antibiotics, with appropriate intervals without medicines that may affect test accuracy and under medical guidance.
No. Symptoms may improve even when infection persists. Eradication must be confirmed with an appropriate follow-up test.
Consult your clinician with your previous prescriptions and test results. A different regimen or susceptibility testing may be appropriate.
There is insufficient reliable clinical evidence to recommend herbs or foods as proven substitutes for medical eradication treatment.
A new infection can occur. A later positive result may also indicate persistent infection if eradication was never confirmed.
H. pylori can be treated with effective medication combinations, but success varies with antibiotic resistance, individual health factors, and adherence to treatment.
Saudi studies demonstrate that eradication rates can differ substantially between regimens, so there is no universal cure rate or single prescription for every patient.
The final important step is to confirm eradication with an appropriate test at the correct time, rather than relying on symptom relief alone.
For evaluation and follow-up, explore Gastroenterology and Endoscopy Services or find a suitable clinician through Mouwasat Hospital Doctors.
Medical disclaimer: This article is for general health education and is not an individualized prescription. Do not start antibiotics, change doses, or stop prescribed medicines without medical guidance. Published eradication rates are study findings, not guaranteed predictions of your personal treatment outcome.









